
Quinolones (also called Fluoroquinolones) are a group of synthetic (man-made) antibiotics that are used to treat many different types of bacterial infections. They are called "broad-spectrum" because they can kill a wide variety of bacteria — both Gram-positive and Gram-negative bacteria.
Simple Definition: Quinolones are powerful man-made antibiotics that stop bacteria from copying their DNA, which kills the bacteria.
In Uganda and other community settings, quinolones are commonly prescribed for:
- Typhoid fever (caused by Salmonella typhi)
- Urinary tract infections (UTIs)
- Dysentery (bloody diarrhea, often caused by Shigella)
- Pneumonia
- Gonorrhea (a sexually transmitted infection)
- Wound infections
Because these infections are common in our communities, nurses must understand how to safely administer these drugs and teach patients properly.
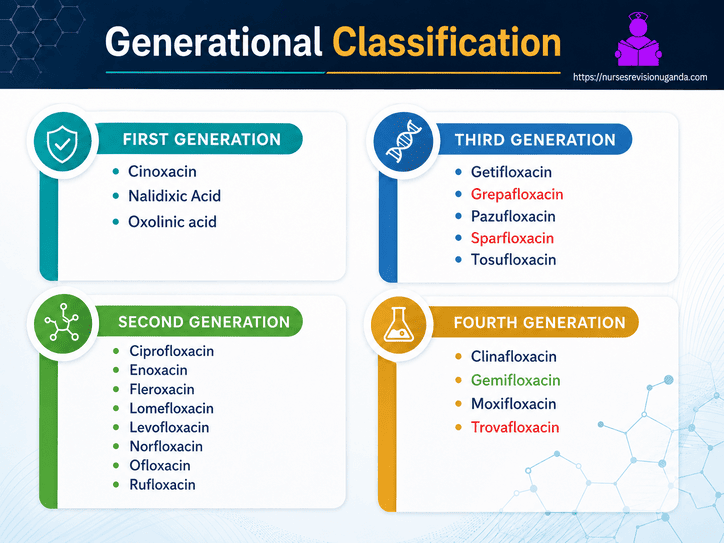
Quinolones are divided into four generations based on when they were developed and how broad their bacterial coverage is.
| Generation | Examples | Key Features |
|---|---|---|
| First Generation | Nalidixic acid, Cinoxacin | Narrow spectrum; mainly Gram-negative; not commonly used today |
| Second Generation | Ciprofloxacin, Norfloxacin, Ofloxacin | Broader spectrum; good against Gram-negative bacteria; first "fluoroquinolones" |
| Third Generation | Levofloxacin | Improved Gram-positive coverage; better for respiratory infections |
| Fourth Generation | Moxifloxacin, Gemifloxacin | Broadest spectrum; covers anaerobes, Gram-positive, and some Gram-negative |
🧠 Memory Tip:
Think of generations like upgrading a phone — each new generation gets better and can do more!
- Ciprofloxacin — the most widely used; excellent for UTIs and typhoid
- Levofloxacin — good for pneumonia and respiratory infections
- Moxifloxacin — broad spectrum; good for complicated infections
- Norfloxacin — used for UTIs and gastrointestinal infections
- Ofloxacin — used for eye and ear infections (topical)
Bacteria are living cells that need to make copies of themselves to survive and spread. To do this, they must copy their DNA (their genetic material). This process involves special enzymes (proteins that speed up chemical reactions). Quinolones work by blocking two important bacterial enzymes:
- This enzyme helps bacteria untangle their DNA so it can be copied.
- Without this enzyme, the DNA gets tangled up like a knotted rope.
- Mechanism: Quinolones block DNA gyrase ➔ DNA cannot untangle ➔ bacteria cannot copy themselves ➔ bacteria die.
- This enzyme helps separate the new DNA copies so they can be distributed into new bacterial cells.
- Mechanism: Quinolones block Topoisomerase IV ➔ new DNA copies cannot separate ➔ bacteria cannot divide ➔ bacteria die.
| Feature | Explanation |
|---|---|
| Bactericidal | Quinolones KILL bacteria directly (they don't just stop them from growing) |
| Target | Only bacterial enzymes — NOT human enzymes (this is why they are safe for humans) |
| Gram-negative bacteria | Quinolones mainly target DNA gyrase |
| Gram-positive bacteria | Quinolones mainly target Topoisomerase IV |
💡 Analogy:
Imagine a photocopier (the bacteria) trying to make copies of a document (DNA). Quinolones are like someone who jams the photocopier — no more copies can be made, and the "business" (bacteria) shuts down!
Quinolones are broad-spectrum antibiotics, meaning they can kill many different types of bacteria.
| Bacteria | Disease Caused |
|---|---|
| Escherichia coli (E. coli) | UTIs, diarrhea |
| Salmonella typhi | Typhoid fever |
| Shigella species | Dysentery (bloody diarrhea) |
| Pseudomonas aeruginosa | Hospital-acquired infections, wound infections |
| Neisseria gonorrhoeae | Gonorrhea (STI) |
| Haemophilus influenzae | Respiratory infections |
| Legionella species | Atypical pneumonia |
| Campylobacter species | Gastroenteritis |
| Klebsiella species | Pneumonia, UTIs |
| Bacteria | Disease Caused |
|---|---|
| Streptococcus pneumoniae | Pneumonia, meningitis |
| Staphylococcus aureus | Skin infections, boils |
| Enterococcus species | UTIs, abdominal infections |
- Mycoplasma pneumoniae
- Chlamydia species
- Mycobacterium tuberculosis (some quinolones are used in TB treatment)
Important Note: Quinolones are NOT effective against viruses, fungi, or parasites. They only kill bacteria!
All quinolones end with the suffix "-floxacin". This makes them easy to identify!
| Generic Name | Common Brand Names | Main Uses |
|---|---|---|
| Ciprofloxacin | Cipro, Ciprotab, Ciprobay | Typhoid, UTIs, diarrhea, anthrax |
| Levofloxacin | Levaquin, Tavanic | Pneumonia, sinusitis, complicated infections |
| Moxifloxacin | Avelox | Respiratory infections, some skin infections |
| Norfloxacin | Noroxin, Norbactin | UTIs, prostatitis, gastroenteritis |
| Ofloxacin | Floxin | Eye infections (drops), ear infections |
| Gemifloxacin | Factive | Community-acquired pneumonia |
🧠 Memory Tip:
If the drug name ends in "-floxacin", it is a quinolone!
This table breaks down the specific indications, standard dosages, and unique contraindications for the most commonly prescribed fluoroquinolones. (Note the differences in dosing frequency—some are twice daily, while the newer generations are once daily due to longer half-lives).
| Drug Name | Commonest Indications | Standard Dosage | Main Side Effects | Contraindications |
|---|---|---|---|---|
| Ciprofloxacin (2nd Generation) |
|
Oral/IV:
|
|
|
| Levofloxacin (3rd Generation) |
|
Oral/IV:
|
|
|
| Moxifloxacin (4th Generation) |
|
Oral/IV:
|
|
|
| Norfloxacin (2nd Generation) |
|
Oral:
|
|
|
| Ofloxacin (2nd Generation) |
|
Oral/IV:
|
|
|
| Gemifloxacin (4th Generation) |
|
Oral:
|
|
|
- UTIs: Ciprofloxacin, Levofloxacin, and Norfloxacin are great for UTIs because they are heavily excreted unchanged in the urine. Moxifloxacin is NOT used for UTIs because it is metabolized in the liver and does not concentrate in the urine!
- Respiratory Infections: Levofloxacin, Moxifloxacin, and Gemifloxacin are dubbed the "Respiratory Fluoroquinolones" because they have excellent coverage against Streptococcus pneumoniae (the most common cause of community-acquired pneumonia). Ciprofloxacin is poor against Strep and should not be used as monotherapy for routine pneumonia.
- Pseudomonas: If you suspect Pseudomonas aeruginosa (hospital-acquired infections), Ciprofloxacin is the most potent quinolone.
Case: A 45-year-old female presents to the clinic with dysuria, frequency, and suprapubic pain. Urinalysis confirms an uncomplicated UTI. The pharmacy is out of Ciprofloxacin. A junior doctor writes a prescription for Moxifloxacin 400mg daily. As the nurse reviewing the chart, why should you question this order?
Answer: You must question this order because Moxifloxacin is primarily metabolized by the liver and excreted in feces/bile. It does not reach high enough concentrations in the urine to effectively treat a urinary tract infection. The doctor should switch to Levofloxacin or Norfloxacin instead!
To remember the Respiratory Fluoroquinolones (the ones that effectively kill Streptococcus pneumoniae):
- My = Moxifloxacin
- Lungs = Levofloxacin
- Grow = Gemifloxacin
Common Infections Treated with Quinolones:
- Urinary Tract Infections (UTIs): Very common in women. Symptoms: burning when passing urine, frequent urination, lower abdominal pain. Ciprofloxacin and Norfloxacin are commonly used.
- Typhoid Fever: Caused by Salmonella typhi. Common in areas with poor sanitation. Symptoms: prolonged fever, headache, abdominal pain, rose spots on skin. Ciprofloxacin is the drug of choice in many cases.
- Dysentery (Bloody Diarrhea): Caused by Shigella species. Symptoms: bloody stools, abdominal cramps, fever. Ciprofloxacin is effective.
- Pneumonia: Infection of the lungs. Symptoms: cough, fever, difficulty breathing, chest pain. Levofloxacin and Moxifloxacin are used.
- Gonorrhea: Sexually transmitted infection. Ciprofloxacin was previously used, but resistance is increasing.
- Skin and Soft Tissue Infections: Wounds, abscesses, cellulitis. Ciprofloxacin may be used.
- Bone and Joint Infections: Osteomyelitis (bone infection). Ciprofloxacin is used for chronic cases.
- Eye and Ear Infections: Bacterial conjunctivitis (pink eye) and Otitis externa (swimmer's ear). Ofloxacin eye drops and ear drops.
- Anthrax: A serious bacterial infection that can be used as a biological weapon. Ciprofloxacin is the drug of choice for post-exposure prophylaxis.
Quinolones can be given in several ways:
| Route | Examples | Nursing Notes |
|---|---|---|
| Oral (by mouth) | Tablets, capsules, suspensions | Most common; absorbed well from the gut |
| Intravenous (IV) | Infusions in hospital settings | Used for serious infections; infuse slowly |
| Topical | Eye drops, ear drops | For eye/ear infections only |
| Otic (ear) | Ofloxacin ear drops | For ear infections |
Oral Absorption: Quinolones are well absorbed when taken by mouth. Food may slow absorption slightly, but they can generally be taken with or without food.
EXCEPTION: Avoid taking with dairy products, antacids, or iron supplements (see Drug Interactions).
- A. Absorption: Oral bioavailability is excellent (70–90%). This means most of the drug gets into the bloodstream when taken by mouth. Peak levels in blood occur 1–2 hours after oral administration.
- B. Distribution: Quinolones are widely distributed throughout the body. They penetrate well into: Urine (good for UTIs), Lungs (good for pneumonia), Bones and joints, Prostate gland, Cerebrospinal fluid (to some extent).
- C. Metabolism: Most quinolones are metabolized in the liver. Some are excreted unchanged by the kidneys.
- D. Excretion: Mainly excreted through the kidneys in urine. This is why they are so effective for UTIs — the drug concentrates in the urine! Some are also excreted in bile/feces.
- E. Half-Life: Varies by drug: Ciprofloxacin (~4 hours), Levofloxacin (~6–8 hours), Moxifloxacin (~12 hours). Dosing is usually twice daily for most quinolones.
Quinolones can cause many side effects. Nurses must monitor patients carefully.
| Side Effect | What to Watch For |
|---|---|
| Nausea | Patient feels like vomiting |
| Vomiting | Actual throwing up |
| Diarrhea | Loose, watery stools |
| Abdominal pain | Stomach cramps |
| Dyspepsia | Indigestion, heartburn |
| C. difficile infection | Severe watery diarrhea, fever, abdominal pain |
💡 Nursing Action: Monitor bowel movements. If patient develops severe diarrhea, notify the doctor immediately — this could be C. difficile, a serious superinfection!
| Side Effect | What to Watch For |
|---|---|
| Headache | Persistent head pain |
| Dizziness | Feeling lightheaded |
| Insomnia | Difficulty sleeping |
| Restlessness | Unable to sit still |
| Confusion | Disorientation, especially in elderly |
| Seizures | Convulsions (rare but serious) |
| Depression | Low mood |
| Nightmares | Bad dreams |
💡 Nursing Action: Monitor mental status. Report any confusion or seizures immediately.
| Side Effect | What to Watch For |
|---|---|
| Tendonitis | Pain, swelling, tenderness in tendons (especially Achilles tendon) |
| Tendon rupture | Sudden "snap" feeling, inability to move foot, severe pain |
| Arthralgia | Joint pain |
| Muscle weakness | Especially dangerous in myasthenia gravis patients |
Risk Factors for Tendon Problems: Age over 60 years, taking corticosteroids (like prednisone), kidney disease, diabetes, history of tendon problems.
💡 Nursing Action: Teach patients to STOP the medication and report immediately if they feel tendon pain, swelling, or hear a "pop" sound!
| Side Effect | What to Watch For |
|---|---|
| QT prolongation | Abnormal heart rhythm on ECG |
| Torsades de Pointes | Life-threatening irregular heartbeat |
| Palpitations | Feeling heart racing |
| Hypotension | Low blood pressure |
💡 Nursing Action: Monitor heart rate and rhythm. Be extra careful if patient is also taking other QT-prolonging drugs (like amiodarone).
| Side Effect | What to Watch For |
|---|---|
| Photosensitivity | Severe sunburn even with brief sun exposure |
| Rash | Skin redness, itching |
| Urticaria (hives) | Raised, itchy welts |
| Stevens-Johnson syndrome | Severe blistering rash (medical emergency!) |
| Toxic epidermal necrolysis | Skin peeling off (medical emergency!) |
💡 Nursing Action: Teach patients to avoid sun exposure and use protective clothing and sunscreen!
- Elevated liver enzymes (ALT, AST)
- Hepatotoxicity (liver damage)
- Jaundice (yellowing of skin and eyes)
💡 Nursing Action: Monitor liver function tests. Watch for jaundice.
| Side Effect | Explanation |
|---|---|
| Crystalluria | Crystals forming in urine (can block kidneys) |
| Hypoglycemia | Low blood sugar (especially in diabetics) |
| Peripheral neuropathy | Numbness, tingling, burning in hands/feet |
| Aortic aneurysm | Bulging of the main artery (rare but serious) |
The FDA (U.S. Food and Drug Administration) has issued the strongest possible warning for quinolones called a "Black Box Warning."
- Tendinitis and Tendon Rupture: Can happen during treatment or up to several months after. Most commonly affects the Achilles tendon. Risk increased in patients over 60, those on corticosteroids, and those with kidney disease.
- Peripheral Neuropathy: Nerve damage causing pain, burning, tingling, numbness. Can be permanent!
- Central Nervous System Effects: Seizures, psychosis, increased intracranial pressure.
- Exacerbation of Myasthenia Gravis: Can cause life-threatening muscle weakness.
💡 Nursing Action: If a patient experiences ANY of these serious adverse reactions, DISCONTINUE THE MEDICATION IMMEDIATELY and notify the healthcare provider!
Quinolones interact with many other drugs. Nurses must check medication lists carefully!
These contain cations (positive ions) that bind to quinolones in the gut:
| Drug/Food | Examples | Action |
|---|---|---|
| Antacids | Maalox, Mylanta, Tums | Separate by at least 2 hours |
| Iron supplements | Ferrous sulfate | Separate by at least 2 hours |
| Calcium supplements | Calcium carbonate | Separate by at least 2 hours |
| Zinc supplements | Zinc tablets | Separate by at least 2 hours |
| Magnesium supplements | Magnesium oxide | Separate by at least 2 hours |
| Dairy products | Milk, cheese, yogurt | Do not take together |
Rule: Give quinolones 2 hours BEFORE or 6 hours AFTER these products!
| Drug | Interaction |
|---|---|
| Corticosteroids (prednisone) | Increased risk of tendon rupture |
| Warfarin | Increased bleeding risk |
| Theophylline | Increased theophylline toxicity (nervousness, seizures) |
| Caffeine | Increased caffeine effects (jitteriness, palpitations) |
| Phenytoin | Altered phenytoin levels |
| Amiodarone | Increased QT prolongation risk |
| Sucralfate | Decreased quinolone absorption |
Quinolones can cause hypoglycemia (low blood sugar) or hyperglycemia (high blood sugar). Monitor blood sugar closely in diabetic patients.
| Situation | Reason |
|---|---|
| Known allergy to quinolones | Risk of anaphylaxis |
| History of tendon rupture with quinolones | High risk of recurrence |
| Myasthenia gravis | Can worsen muscle weakness |
| Situation | Reason |
|---|---|
| Pregnancy | Risk of cartilage damage to fetus |
| Breastfeeding | Drug passes into breast milk |
| Children under 18 | Risk of cartilage damage in growing bones |
| Elderly (>60 years) | Increased risk of tendon rupture |
| Seizure disorders | Can lower seizure threshold |
| Renal impairment | Drug accumulation; dose adjustment needed |
| Hepatic impairment | Altered drug metabolism |
| QT prolongation | Risk of dangerous heart rhythms |
| Diabetes | Risk of blood sugar changes |
- Check allergies — Ask about previous reactions to quinolones
- Obtain culture and sensitivity — Before starting antibiotic (if possible)
- Review medication list — Check for drug interactions
- Assess baseline vital signs and check renal and liver function tests
- Oral: Give with a full glass of water. Can give with food if stomach upset occurs. NEVER give with dairy, antacids, or iron supplements. Ensure patient drinks plenty of fluids (2 liters/day).
- IV Administration: Infuse slowly over 60 minutes (for 500mg) or 90 minutes (for 750mg). Monitor for infusion reactions. Do not mix with other medications in the same IV line.
- Monitor for effectiveness: Decreasing fever, decreasing white blood cell count, improving symptoms, negative culture results.
- Monitor for adverse effects: Tendon pain or swelling, diarrhea (especially watery/bloody), skin rash, mental status changes, heart rhythm changes.
- Monitor intake and output: Ensure adequate urine output (at least 30 mL/hour). Watch for signs of crystalluria.
- A. How to Take the Medication: "Take this medicine with plenty of water. You can take it with food if your stomach hurts. Do NOT take it with milk, yogurt, cheese, or antacids. Wait at least 2 hours before or after."
- B. Fluid Intake: "Drink at least 8 glasses of water every day while taking this medicine. This helps prevent crystals from forming in your urine."
- C. Sun Protection: "This medicine can make your skin very sensitive to the sun. Stay out of direct sunlight. Wear long sleeves, a hat, and use sunscreen. This can happen while taking the medicine AND for several days after."
- D. Tendon Warning: "If you feel pain, swelling, or a 'snap' in your ankle or any tendon, STOP the medicine and come to the clinic immediately! Rest the affected area. Do not exercise while taking this medicine."
- E. Complete the Full Course: "Take ALL the medicine, even if you feel better. If you stop early, the infection may come back stronger."
- F. When to Seek Help: Severe diarrhea, yellowing of skin or eyes, severe skin rash, difficulty breathing, chest pain or irregular heartbeat, severe dizziness or confusion.
What Is Resistance? Bacteria can change (mutate) so that quinolones no longer kill them. This is a growing problem worldwide, including in Uganda.
How Resistance Develops:
- Mutations in target enzymes — Bacteria change their DNA gyrase or topoisomerase IV so the drug cannot bind.
- Efflux pumps — Bacteria develop pumps that push the drug out before it can work.
- Decreased permeability — Bacteria change their cell walls so the drug cannot enter.
How to Prevent Resistance: Only use quinolones when necessary — not for viral infections! Complete the full course of antibiotics. Do not share antibiotics with others. Use narrow-spectrum antibiotics when possible. Practice good hygiene to prevent infections.
💡 Community Teaching:
"Do not buy antibiotics from the shop without a prescription. Using antibiotics when you don't need them makes them stop working when you really need them!"
- Patient: A 25-year-old woman with fever for 7 days, headache, abdominal pain, and constipation.
- Diagnosis: Typhoid fever
- Treatment: Ciprofloxacin 500mg orally twice daily for 14 days
- Nursing Actions: Teach patient to take with water, warn about sun exposure, monitor for tendon pain, ensure completion of full course. Teach family about handwashing and safe water.
- Patient: A 30-year-old pregnant woman with burning urination and frequency.
- Important: Quinolones are contraindicated in pregnancy!
- Alternative: The doctor will likely prescribe a safer antibiotic like amoxicillin or nitrofurantoin.
- Nursing Actions: Do NOT give quinolones to pregnant patients, educate about safe alternatives, encourage plenty of fluids, teach about perineal hygiene.
- Patient: A 65-year-old man on levofloxacin for pneumonia reports pain "above his heel."
- Assessment: Pain over the Achilles tendon.
- Nursing Actions: STOP the medication immediately! Notify the healthcare provider. Rest the affected leg. Do NOT massage or exercise the tendon. Document the adverse reaction.
- F - Fluid intake important (2L/day)
- L - Long QT interval (monitor heart)
- O - Older adults at risk for tendon rupture (>60 years)
- X - Don't give with cations (Ca, Zn, Fe, Mg, Al) or dairy
- A - Avoid in children and pregnancy
- C - Watch for C. difficile diarrhea
- I - Interactions with caffeine, warfarin, theophylline
- N - Neuromuscular blockade (worsens myasthenia gravis)
- S - Sun sensitivity (photosensitivity)
- C - Cartilage damage risk (avoid in children)
- I - Inhibits DNA gyrase
- P - Photosensitivity
- R - Renal excretion (good for UTIs)
- O - Oral and IV routes
- T - Tenderness over tendon
- E - Edema (swelling)
- N - No ability to move the joint
- D - Discomfort with movement
- O - Obvious deformity
- N - Notify doctor immediately!
- Mechanism of action: Inhibits DNA gyrase and topoisomerase IV
- Suffix: All end in "-floxacin"
- Black box warning: Tendon rupture, peripheral neuropathy, CNS effects
- Drug interactions: Antacids, dairy, iron, calcium reduce absorption
- Contraindications: Pregnancy, children <18, myasthenia gravis
- Side effects: Photosensitivity, GI upset, C. difficile, QT prolongation
- Patient teaching: Drink plenty of water, avoid sun, complete full course
- Q1: A patient taking ciprofloxacin reports pain in the Achilles tendon. What is the nurse's best action?
A: Stop the medication immediately and notify the provider. This could be tendonitis, which can lead to tendon rupture. - Q2: A patient asks if they can take their ciprofloxacin with their calcium supplement. What should the nurse say?
A: No. Calcium binds to ciprofloxacin and prevents absorption. Take the antibiotic 2 hours before or 6 hours after the calcium. - Q3: Why are quinolones contraindicated in children?
A: They can damage growing cartilage and affect bone development. - Q4: A patient on levofloxacin develops severe watery diarrhea. What should the nurse suspect?
A: C. difficile infection. This is a superinfection caused by disruption of normal gut bacteria.
| Feature | Details |
|---|---|
| Class | Fluoroquinolones |
| Suffix | -floxacin |
| Action | Bactericidal; inhibits DNA gyrase and topoisomerase IV |
| Spectrum | Broad (Gram-negative and Gram-positive) |
| Common drugs | Ciprofloxacin, Levofloxacin, Moxifloxacin, Norfloxacin, Ofloxacin |
| Routes | Oral, IV, topical (eye/ear drops) |
| Key side effects | GI upset, photosensitivity, tendon rupture, QT prolongation, C. difficile |
| Black box warning | Tendon rupture, peripheral neuropathy, CNS effects, myasthenia gravis |
| Contraindications | Pregnancy, children <18, myasthenia gravis, known allergy |
| Drug interactions | Antacids, dairy, iron, calcium, magnesium, zinc, corticosteroids, warfarin |
| Patient teaching | Plenty of fluids, avoid sun, no dairy/antacids with dose, complete full course |
| Nursing priority | Monitor for tendon pain, diarrhea, rash, mental changes, heart rhythm |
- Typhoid fever: very common; spread through contaminated food/water
- Dysentery: bloody diarrhea; spread through poor sanitation
- UTIs: common in women; related to hygiene and water quality
- Pneumonia: especially in children and HIV-positive patients
- Safe water: Boil or treat drinking water to prevent typhoid and dysentery
- Handwashing: Wash hands with soap after using the toilet and before eating
- Proper toilet use: Use latrines to prevent contamination of water sources
- Complete antibiotics: Finish all prescribed medication
- Don't self-medicate: See a healthcare provider before taking antibiotics
- Report side effects: Tell the nurse or doctor if you have tendon pain, severe diarrhea, or skin rash
- Osmosis. (2025). Antibiotics - Fluoroquinolones: Nursing Pharmacology.
- Open RN. (2023). 3.11 Fluoroquinolones – Fundamentals of Nursing Pharmacology.
- RegisteredNurseRN. (2023). Fluoroquinolones (Quinolones) Nursing Antibiotic Pharmacology Review.
- Muntean et al. (2022). Overview of Side-Effects of Antibacterial Fluoroquinolones. PMC.
- Australian Prescriber. Fluoroquinolone antibiotics and adverse events. PMC.