Nurses Revision

nursesrevision@gmail.com

Systematic Approach to the Patient Presenting with Acute Pyrexia of Unknown Origin

Systematic Approach to the Patient Presenting with Acute Pyrexia of Unknown Origin

Modern Approach to Pyrexia of Unknown Origin (PUO)

1. Introduction and Definitions

Pyrexia of Unknown Origin (PUO) is synonymous with Fever of Unknown Origin (FUO). While PUO is sometimes used, FUO is the term most commonly utilized in medical literature and international guidelines.

The Classic Definition of FUO (Petersdorf and Beeson, 1961)

Historically, the diagnosis of FUO required three strict criteria to be met:

  • Duration: Illness of more than 3 weeks duration. (Rationale: This extended timeframe helps to naturally eliminate self-limiting viral infections, which usually resolve within 1 to 2 weeks).
  • Temperature: Fever greater than 38.3°C (101°F) on several occasions.
  • Investigation: Cause remains uncertain after 1 week of in-hospital investigation.

FUO Redefined (Durack & A.C. Street, 1991)

With the advent of advanced outpatient diagnostics, keeping a patient hospitalized for a week simply for observation became impractical and costly. Furthermore, specific vulnerable patient populations required tailored definitions. Thus, FUO was redefined into four distinct categories:

  1. Classical FUO:
    • Duration: ≥ 3 weeks.
    • Fever: ≥ 38.3°C (101°F).
    • Cause uncertain after 3 days despite appropriate in-hospital investigation OR after 3 out-patient visits.
  2. Nosocomial FUO:
    • Occurs in hospitalized patients.
    • Fever ≥ 38.3°C (101°F) on several occasions.
    • The infection was not present or incubating on admission.
    • Diagnosis remains uncertain after 3 days despite appropriate investigations.
  3. Neutropenic FUO:
    • Neutrophil count is <0.5 x 10⁶/L (or is expected to fall to that level in 1 to 2 days).
    • Fever ≥ 38.3°C (101°F) on several occasions.
    • Diagnosis remains uncertain after 3 days despite appropriate investigations. (Note: These patients lack the white blood cells to mount a normal inflammatory response, making them highly susceptible to rapid, overwhelming sepsis).
  4. HIV-Associated FUO:
    • Confirmed HIV infection.
    • Fever ≥ 38.3°C (101°F) on several occasions.
    • Duration of > 4 weeks for out-patients, or > 3 days for hospitalized patients.
    • Diagnosis remains uncertain after 3 days despite appropriate investigations.

Time for a Change in the Definition of FUO?

Neither the original definition nor the currently-used definitions of FUO clearly define the word "workup" or its required intensity. Because of this, a patient labeled as having "FUO" in a resource-limited rural hospital (without access to advanced imaging or molecular tests) might easily and quickly be diagnosed with tuberculosis or a hidden abscess if transferred to a well-equipped tertiary hospital.

Clinical Argument: Reasonably, only those medical centers with access to specified, modern required diagnostic techniques (like CT, MRI, advanced serology) should be fully authorized to firmly label a patient's condition as a true FUO.

2. Etiology: Causes of Classical FUO

When investigating a prolonged fever, clinicians categorize the potential causes into major groups. Statistically, the breakdown of Classical FUO causes is as follows:

Disease CategoryPercentage of FUO Cases
Infections22 - 58% (Most common globally)
Neoplasms (Cancers)Up to 30%
Non-infectious Inflammatory / Autoimmune DiseasesUp to 25%
Miscellaneous CausesUp to 25%
UndiagnosedUp to 30% (Despite exhaustive workups, some fevers spontaneously resolve without a definitive diagnosis).

A. Infections (22-58%)

Infections remain the leading cause of FUO. They can be deeply sequestered (hidden) or present atypically.

  • Bacterial Infections:
    • Abscesses: Dental, intra-abdominal (liver, spleen, psoas muscle), or pelvic. These can be clinically silent except for fever.
    • Pyomyositis (bacterial infection of skeletal muscle).
    • Loculated effusions or obstructions that are not drained.
    • Osteomyelitis (bone infection) and spine infections (discitis).
    • Prosthetic joint infections or catheter-related bloodstream infections.
    • Infective endocarditis (heart valves) and pericarditis.
    • Mycotic aneurysm (infection of an arterial wall).
    • Biliary tract infections (cholangitis).
    • Occult (hidden) urinary tract infections, renal or perinephric abscesses.
    • Mycobacterial: Extrapulmonary tuberculosis, miliary (disseminated) tuberculosis, MOTT (Mycobacteria Other Than Tuberculosis).
    • Specific organisms: Salmonella infections, Clostridium difficile colitis, Cat scratch disease (Bartonella), Tularemia, Yersiniosis, Brucellosis, Melioidosis, Nocardiosis, Rhodococcosis.
    • Atypical/Intracellular: Q fever (Coxiella burnetii), Spirochaetal, Rickettsial, Mycoplasma, and Chlamydial infections (including Psittacosis).
  • Fungal Infections:
    • Candidiasis, Cryptococcosis, Aspergillosis, Pneumocystis jiroveci, Mucormycosis, Histoplasmosis, Penicilliosis, and other endemic fungi.
  • Viral Infections:
    • Acute HIV infection, HHV8-associated Castleman’s Disease, CMV (Cytomegalovirus) infection, EBV (Epstein-Barr Virus / Infectious mononucleosis), Parvovirus B19 infection.
  • Parasitic Infections:
    • Malaria, Amoebic liver abscess.

B. Neoplastic Diseases (Up to 30%)

Cancers can cause fever in two primary ways:
1) Tumours may cause fever in their own right (by releasing pyrogenic cytokines like IL-1 and TNF-alpha).
2) Solid tumours may cause luminal obstruction, leading to a secondary bacterial infection behind the blockage (e.g., a tumor in the bronchus leading to post-obstructive pneumonia, or a bile duct tumor leading to cholangitis).

  • Hematologic Malignancies: Hodgkin’s lymphoma, Non-Hodgkin’s lymphoma, Leukaemias (including the aleukemic type where abnormal cells don't spill into the blood), Myelodysplasia, Multiple myeloma.
  • Solid Tumors: Renal cell carcinoma (classic cause of neoplastic fever), Adenocarcinomas of the breast, Hepatocellular carcinoma (HCC) or metastases to the liver, Colonic cancer, Lung cancer, Pancreatic tumor, Sarcoma, Kaposi sarcoma, Atrial myxoma (a benign heart tumor that mimics endocarditis), and disseminated carcinomatosis.

C. Hypersensitivity & Autoimmune Diseases (Up to 25%)

Systemic inflammation without an infectious trigger.

  • Systemic lupus erythematosus (SLE) and Rheumatoid arthritis.
  • Rheumatic fever.
  • Adult Onset Still’s disease (characterized by high spiking fevers, salmon-colored rash, and joint pain).
  • Macrophage Activation Syndrome / Hemophagocytosis Syndrome.
  • Temporal arteritis (giant cell arteritis) and Polymyalgia rheumatica (common in the elderly).
  • Polyarteritis nodosa.
  • ANCA-sensitive vasculitides: Microscopic polyangiitis, Churg-Strauss Syndrome, Wegener’s granulomatosis.
  • Other vasculitides: Takayasu arteritis, Hypersensitivity vasculitis, Cryoglobulinemic vasculitis, Behcet’s disease.
  • Relapsing polychondritis, Antiphospholipid syndrome, Mixed connective tissue disease.
  • Hypersensitivity pneumonitis.

Detailed Look: ANCA (Antineutrophil Cytoplasmic Antibodies)

ANCA testing is crucial for diagnosing specific vasculitides that cause FUO.

Disease EntityC-ANCA Sensitivity
(anti-proteinase 3 / PR3)
P-ANCA Sensitivity
(anti-myeloperoxidase / MPO)
Wegener’s Granulomatosis85% (Highly sensitive)10%
Microscopic Polyangiitis45%45%
Idiopathic Crescentic Glomerulonephritis25%65%
Churg-Strauss Syndrome10%60%
Polyarteritis Nodosa5%15%

(Data derived from Kallenberg CGM. The vasculitides: Science and Practice, 1996)

D. Miscellaneous Causes of Classic FUO

  • Kikuchi’s Disease (Histiocytic necrotizing lymphadenitis).
  • Sarcoidosis (Granulomatous disease).
  • Inflammatory bowel disease (Ulcerative colitis, Crohn’s disease).
  • Granulomatous hepatitis & Alcoholic hepatitis.
  • Vascular/Thrombotic: Thrombophlebitis, Deep vein thrombosis (DVT), Recurrent pulmonary emboli (PE), Thrombotic thrombocytopenic purpura (TTP).
  • Endocrine: Subacute thyroiditis (de Quervain's), Adrenal insufficiency.
  • Crystal Arthropathies: Gout, Pseudogout.
  • Hidden Bleeding: Hematoma (e.g., retroperitoneal space, aortic dissection/aneurysm, hip, pelvis). As the body breaks down a large volume of blood, it generates heat and fever.
  • Hereditary periodic fever syndromes (e.g., Familial Mediterranean Fever).
  • Immune reconstitution inflammatory syndrome (IRIS) - especially common with TB and MAC in HIV patients starting antiretrovirals.
  • Sweet’s Syndrome (Acute febrile neutrophilic dermatosis).

3. Specific Febrile Syndromes

I. Hyperthermia Syndrome vs. True Fever

It is clinically vital to distinguish true fever (where the hypothalamus resets the body's core temperature higher in response to pyrogens) from Hyperthermia (where the body's temperature regulation fails and heat generation exceeds heat loss, independent of pyrogens). Antipyretics (like paracetamol) will not lower hyperthermia.

Causes of Hyperthermia Syndrome:

  • Heat Stroke: Induced by intense exercise or impaired sweating (often exacerbated by anticholinergic drugs).
  • Drug-Induced: Overdoses or toxicity from Cocaine, Amphetamines, or MAO inhibitors.
  • Neuroleptic Malignant Syndrome (NMS): A life-threatening reaction to antipsychotic drugs (like Phenothiazines or Haloperidol), causing "lead-pipe" muscle rigidity and extreme temperatures.
  • Malignant Hyperthermia: A severe genetic reaction triggered by inhalational anesthetics during surgery.
  • Endocrinopathy: Severe Thyrotoxicosis (thyroid storm) or Pheochromocytoma (adrenaline-secreting tumor).
  • Hypothalamic Fever: Direct damage to the brain's thermostat due to cerebral trauma, massive hemorrhage, massive stroke, or anoxic brain injury.

II. Drug Fever

Drug fever is a febrile response that coincides temporally with the administration of a drug and disappears after discontinuation of the offending agent.

Pathogenesis of Drug Fever:

  1. Contamination: Contamination of the IV drug/fluid with an exogenous pyrogen or microorganism during manufacturing or administration.
  2. Pharmacologic Action: Related to the direct action of the drug itself (e.g., Amphotericin B causing cytokine release, or massive bacterial die-off causing a Jarisch-Herxheimer reaction).
  3. Allergic (Hypersensitivity): The most common mechanism; an immune-mediated allergic reaction to the drug or its excipients.

Clinical Picture of Drug Fever:

  • Presentation: The fever is often completely out of proportion to the clinical picture (the patient looks surprisingly well despite a very high temperature).
  • Pattern: The pattern of fever is highly variable (can be continuous, spiking, or remittent).
  • Onset: Typically occurs 7 to 10 days (can be up to 21 days) after the initiation of the drug.
  • Resolution: Usually resolves rapidly, within 48 hours after discontinuation of the drug (though this depends on the half-life of the specific medication).
  • Associated Findings:
    • Rigor (43%), Myalgia (25%), Rash (18%), Headache (18%).
    • Lab findings: Leukocytosis (22%), Eosinophilia (22%), Proteinuria, Abnormal liver function tests.
    • Serum sickness (fever, tissue swelling, rash, lymph node enlargement).
Most Common Drugs That Cause Fever:

Almost any drug can cause drug fever, but the classic offenders include:

  • Antimicrobials: Sulfa drugs, Dapsone, Pentamidine, Clindamycin, Penicillins, Cephalosporins, Macrolides, Aminoglycosides, Vancomycin, Nitrofurantoin, Amphotericin.
  • Anti-TB/Antiretrovirals: Isoniazid, Rifampicin, Abacavir, Nevirapine, Fosamprenavir, NRTIs (can cause lactic acidosis presenting with fever).
  • Cardiovascular/Neuro: Phenytoin, Barbiturates, Carbamazepine, Hydralazine, Methyldopa, Procainamide, Quinidine, Haldol, Amphetamines.
  • Others: Interferons, Iodide, Allopurinol, Antihistamines, NSAIDs.

III. Factitious Fever

Factitious fever is a self-induced or artificially manipulated temperature elevation.

  • When to suspect: The diagnosis should be strongly considered in any puzzling FUO, especially in:
    • Young women.
    • Persons with medical training or healthcare backgrounds.
    • Patients who appear clinically completely well despite charting extremely high temperatures.
  • Clinical Clues:
    • Disparity between temperature and pulse: Normally, heart rate rises ~10 bpm for every 1°C increase in temperature. In factitious fever (e.g., dipping the thermometer in hot water), the pulse remains normal while the recorded temperature is sky-high.
    • Absence of the normal diurnal pattern of body temperature.
    • Many patients possess underlying psychiatric features of Munchausen syndrome (factitious disorder imposed on self).

4. Clinical Assessment: The Fever Checklist

To standardize the approach to FUO, Dr. Tso proposes a systematic "Fever Checklist" for patient management.

Defining Fever (Adults)

  • Fever is officially present if the temperature in the mouth (oral) is over 37.5°C (99.5°F).
  • Institution Specific: At UCH, the Genius 2 Infrared Tympanic Electronic Thermometer (set at Oral mode) is used. A temperature > 37.5°C on this device triggers the FUO pathway.

Step 1: Detailed History

The diagnostic approach to adults with prolonged unexplained fever demands a rigorous, exhaustive history.

  • Inquire about symptoms from all major organ systems. Look for general complaints (weight loss, profound night sweats, headaches, transient rashes).
  • Record all complaints, even if they completely disappeared before the current examination. Previous illnesses (including long-past surgeries and psychiatric illnesses) are vital clues.
  • Detailed Evaluation Areas:
    • Family history (genetic periodic fevers, autoimmune diseases).
    • Immunization status.
    • Occupational history (e.g., abattoir worker exposed to Brucellosis).
    • Travel history (crucial for Malaria, Dengue, Typhoid).
    • Nutrition and weight changes.
    • Comprehensive drug history (including all over-the-counter supplements, prescribed meds, and illicit substances).
    • Sexual history (HIV, Syphilis).
    • Recreational habits (hiking/camping exposing to tick-borne diseases).
    • Animal contacts (exposure to ticks, birds/Psittacosis, cats/Bartonella).

Step 2: Careful (Repeated) Physical Examination

  • Ensure definitive documentation of the fever (rule out factitious fever or faulty thermometers).
  • Fever Patterns: The pattern of fever (continuous, remittent, intermittent) is usually of little help in the modern evaluation. In general, the correlation between specific fever patterns and specific diseases is very weak.
    • Notable Exceptions: Tertian and quartan fever patterns in Malaria.
    • Other diseases (Brucellosis, Borreliosis, Hodgkin's disease/Pel-Ebstein fever) tend to cause recurrent, undulating episodes of fever.
  • Repeat the Exam: A regular physical examination must be repeated daily while the patient is hospitalized. The body changes, and physical signs may evolve late in the disease course.
  • Pay special attention to: Rashes, new or changing cardiac murmurs (endocarditis), signs of arthritis/swollen joints, subtle abdominal tenderness or rigidity, lymph node enlargement, fundoscopic changes in the eye (Roth spots, tubercles), and new neurologic deficits.

Associated Clinical Features in Recurrent FUO (Targeted Exam Areas):

Body SystemDiagnostic Clues / Associated Diseases
Eye InvolvementSarcoidosis, SLE, Rheumatoid disease, Giant-cell arteritis.
LymphadenopathyLymphoma, Castleman's disease, Still's disease, Brucellosis, Filariasis, Tuberculosis, Whipple's disease.
Hepatomegaly (Liver)Lymphoproliferative/myeloproliferative disorders, Granulomatous hepatitis, Q fever, Relapsing fever.
SplenomegalyLymphoproliferative disorders, Brucellosis, Malaria, Q-fever, Tuberculosis, Rheumatoid disease, SLE, Sarcoidosis.
Abdominal PainFamilial Mediterranean Fever (FMF), Crohn's disease, Hyper-IgD syndrome.
Skin RashSecondary syphilis, Filariasis, Whipple's, Still's disease, SLE, Sarcoidosis, FMF, Sweet's syndrome.
Joint PainRheumatoid disease, SLE, Ankylosing spondylitis, Still's disease, Brucellosis, Rat-bite fever, FMF.

5. Investigations: Labs, Imaging, and Procedures

Step 3: Appropriate Laboratory Tests

Testing must be based on clinical presentation and the specific system involved. A "shotgun" approach is discouraged; targeted screening is preferred.

  • Baseline Bloods: CBC (with differential count), ESR, CRP, Liver/Renal Function Tests (LRFT), Glucose, PT/APTT, CK, LDH, D-dimer, Amylase.
  • Urine: Routine urinalysis. Early Morning Urine (EMU) x 3 for Acid-Fast Bacilli (AFB/TB). Urine antigen testing for Legionella pneumophila and Pneumococcus.
  • Respiratory: NPS/NPA (Nasopharyngeal aspirate) for Influenza A/B Ag, PCR, viral culture. Sputum/gastric lavage for AFB smear and culture (x3). Sputum for fungal culture (Nocardia/Rhodococcus) and Pneumocystis jiroveci cytology. PCR for TB DNA or Chlamydia psittaci.
  • Fluid & Tissue: Relevant body fluid (joint, pleural, peritoneal, pericardial) for cell count, protein, glucose, pH, Gram stain, cultures, AFB, and cytology. Lumbar puncture for CSF examination.
  • Blood Smear: Peripheral blood smear for morphology. Thick/thin blood smear specifically for Malaria screen.
  • Blood Cultures (C/ST): Standard cultures for blood, sputum, urine, wound. Crucial: Prolong blood cultures to 14 days for suspected endocarditis or fungemia (must specify this on the lab request).
    • Differential time to positivity: Taking blood cultures simultaneously from a peripheral vein and a central catheter lumen to determine if the catheter is the source of sepsis.
    • Fresh blood for CMV pp65. Blood for cryptococcal Ag. Blood for AFB culture (Bactec bottle). Clotted blood for galactomannan or (1->3)-beta-D-Glucan (fungal markers).
  • Stool Exam: Viral study, culture, Ova & Cysts, Amoeba, Clostridium difficile toxin.
  • Immunology & Tumor Markers: ANA, anti-ds-DNA, C3, C4, anti-ENA, RF, ANCA, Serum immunoelectrophoresis (Ig pattern), Cryoglobulin, Ferritin, TFT, Tumor markers (CEA, AFP, PSA).
  • Infection Serology: HIV Ab (and CD4 count if positive), Atypical pneumonia paired sera, Mycoplasma IgM, VDRL, Widal test, Weil-Felix, Rickettsial, Coxiella (Q fever), Brucella, Monospot, EBV (VCA IgM, EBNA IgG), Hepatitis, Dengue, Leptospirosis, Parvovirus B19, Hantavirus, CMV, JEV, HTLV1, Burkholderia, Bartonella, Aspergillus, Histoplasma, Toxoplasma, Amoebic, Cysticercosis.

Note: The Mantoux Test (MT2) can yield false negatives in disseminated TB or severely immunocompromised patients; a negative test does not exclude TB.

Step 4: Appropriate Imaging

  • First Line: Chest X-Ray (CXR) and targeted X-rays of symptomatic regions. Ultrasonography (abdomen/pelvis). Echocardiogram (to rule out endocarditis or atrial myxoma). High-Resolution CT (HRCT) thorax (plain).
  • Advanced CT/MRI: CT with contrast of suspected regions (thorax, abdomen, pelvis).
    • Caution: Avoid contrast CT or MRI if the patient has severe renal failure to prevent contrast-induced nephropathy or Nephrogenic Systemic Fibrosis (NSF from MRI Gadolinium).
    • For mild renal failure, contrast CT may proceed with strict precautions: Encourage aggressive fluid intake/Normal Saline infusion before the scan, and administer Acetylcysteine 600mg twice daily orally for 2 days (the day before and the day of the CT).
  • Vascular Imaging: CT pulmonary angiogram for suspected pulmonary embolism. Venous Doppler Ultrasound of the leg for suspected DVT.
  • Nuclear Medicine: Bone scan, Gallium SPECT/CT, and PET-CT.

The Role of PET-CT in FUO

Positron Emission Tomography-Computed Tomography (using [18F]FDG) is increasingly vital in modern FUO workups.

  • It expertly guides further investigation by pinpointing the exact metabolic site of the lesion for targeted biopsy.
  • It is exceptionally good at detecting hidden inflammatory lesions (both infective and non-infective) and solid tumors (e.g., hidden caecal adenocarcinomas).
  • It has a very high negative predictive value (NPV); if the PET scan is negative, it reliably rules out major inflammatory or malignant solid lesions.
  • It can easily detect large vessel vasculitis (which is notoriously difficult to diagnose with standard imaging).
  • Limitations: It may not detect microscopic lesions isolated entirely within the bone marrow. Negative findings can also be present if the FUO is caused by a systemic viral infection or drug fever (which lack localized inflammatory masses).
  • Advantage in Renal Disease: PET-CT (plain, without IV iodine contrast) can be safely performed in patients with severe renal impairment.
  • It is generally more sensitive than a Gallium SPECT/CT scan.

Step 5: Invasive Procedures

When non-invasive tests fail, direct visualization and tissue sampling are required.

  • Endoscopy: Oesophago-Gastro-Duodenoscopy (OGD), Colonoscopy, ERCP (biliary tract), Bronchoscopy, Mediastinoscopy.
  • Biopsies: Crucial for histology, routine culture/sensitivity, AFB culture, and fungal culture.
    • Bone marrow biopsy (especially if the Complete Blood Picture is abnormal).
    • Pleural or Pericardial biopsy.
    • Skin lesion biopsy.
    • Lymph node biopsy: Note: Fine Needle Aspiration (FNA) may be considered first, but a full excisional biopsy usually provides a much more definitive diagnosis because it preserves the tissue architecture (crucial for lymphoma staging).
    • Liver biopsy (if LFTs are abnormal and undiagnosed).
    • Temporal artery biopsy (gold standard for Giant Cell Arteritis).
    • Bone biopsy (for osteomyelitis).

6. Management & Empirical Treatment Protocols

A major dilemma in treating a patient with prolonged, undiagnosed fever is the temptation to simply "treat blindly" out of frustration.

Empirical Broad-Spectrum Antibiotics

  • For unexplained, prolonged fever in a clinically stable patient who has already failed a standard empiric antimicrobial agent, conducting empirical trials or switching to "big-gun" broad-spectrum antibiotics without identifying a clear cause is strongly discouraged.
  • Why? It breeds antibiotic resistance, exposes the patient to drug toxicity (or drug fever), and often partially suppresses an infection, making it impossible to culture and identify the true organism.

Empirical Anti-Tuberculosis Trial

  • Once an empirical anti-TB trial is started, there is very little potential for ever obtaining a positive TB culture afterward, robbing the clinician of the ability to test for drug resistance.
  • Furthermore, medications in the TB regimen (specifically Rifampicin, Aminoglycosides, or Fluoroquinolones) have broad antibacterial activity and can transiently suppress fever caused by other non-TB bacterial infections, leading to a dangerous false diagnosis of Tuberculosis.

Use of Antipyretic Agents

  • Routine use of antipyretics (Paracetamol, NSAIDs) is discouraged during the diagnostic phase because they mask the true temperature curve and fever pattern.
  • They should be indicated only for patients experiencing substantial physical discomfort, extreme tachycardia, or metabolic stress directly due to the fever itself.

Based on the presentation by Dr. Eugene Tso, Division of Infectious Diseases, Department of Medicine & Geriatrics, United Christian Hospital

Systematic Approach to the Patient Presenting with Acute Pyrexia of Unknown Origin Read More »
Psychiatric Rehabilitation: Principles, Resources, Support Systems and Personnel

Psychiatric Rehabilitation: Principles, Resources, Support Systems and Personnel

Psychiatric Rehabilitation

Psychiatric rehabilitation is a person-centred, recovery-oriented process that helps a person living with mental illness or psychosocial disability develop or regain the skills, confidence, opportunities and environmental supports needed to live, learn, work, relate to others and participate meaningfully in the community.

Core message: Rehabilitation does not wait until every symptom disappears. It begins early, continues across hospital and community care, and combines treatment, skill development, environmental modification, family and peer support, protection of rights and access to real-life opportunities.

Learning Objectives

By the end of this lesson, the learner should be able to define psychiatric rehabilitation; distinguish recovery, treatment, habilitation and rehabilitation; explain its aims and principles; conduct a comprehensive rehabilitation assessment; identify resources and support systems; describe the roles of the multidisciplinary team; formulate an individualized rehabilitation plan; and evaluate outcomes.

Key Concepts

ConceptMeaning and clinical importance
RecoveryA personal process of building a satisfying, hopeful and contributing life, even when some symptoms or limitations remain. Recovery is defined by the service user, not only by symptom scores.
Clinical recoveryReduction or remission of symptoms and improvement in observable functioning. It is important, but is only one part of personal recovery.
RehabilitationRestoring or improving previously developed abilities and roles that were reduced by illness, hospitalization, discrimination or social exclusion.
HabilitationHelping a person acquire skills they may never have developed, such as budgeting, self-care, social or vocational skills.
ReintegrationSupporting return to family, school, employment, worship, recreation and community citizenship without segregation.
AftercarePlanned continuing care after discharge, including appointments, medication support, relapse prevention, home follow-up and social assistance.
Psychosocial disabilityRestrictions in participation arising from the interaction between mental health difficulties and environmental, social or attitudinal barriers.

Why Psychiatric Rehabilitation Is Needed

  • Illness-related limitations: psychosis, depression, bipolar disorder, substance-use disorders and cognitive impairment can disrupt motivation, attention, judgment, communication and daily routines.
  • Effects of long hospitalization: institutional routines may produce dependency, loss of initiative, reduced decision-making and weakening of family and community roles.
  • Social barriers: stigma, discrimination, poverty, homelessness, unemployment, interrupted education and rejection may remain even when symptoms improve.
  • Treatment gaps: medicine can control symptoms but does not by itself teach work skills, rebuild relationships, secure housing or create community acceptance.
  • Relapse prevention: stable routines, supportive relationships, meaningful occupation and early help-seeking reduce avoidable crises and readmissions.

Aims of Psychiatric Rehabilitation

  1. Maximize independence, autonomy and quality of life.
  2. Reduce disability and the practical effects of symptoms.
  3. Strengthen personal, social, educational, vocational and independent-living skills.
  4. Promote hope, identity, dignity, choice and self-efficacy.
  5. Support safe community living and reduce unnecessary institutional care.
  6. Restore valued roles within family, school, work and community.
  7. Improve treatment engagement, physical health and relapse prevention.
  8. Remove environmental and attitudinal barriers and protect human rights.

Principles of Psychiatric Rehabilitation

PrincipleApplication in practice
Person-centred careBegin with the person’s own priorities, culture, strengths and definition of a meaningful life. Avoid imposing goals merely because professionals prefer them.
Hope and recovery orientationCommunicate that improvement and a valued life are possible. Set achievable steps while avoiding false promises.
Choice and self-determinationOffer understandable options, support decision-making and obtain informed consent. Risk alone should not automatically remove a person’s voice.
Strengths-based practiceIdentify abilities, interests, coping methods, relationships and previous successes in addition to symptoms and deficits.
IndividualizationTwo people with the same diagnosis may need very different help. Base the plan on functional assessment and personal goals rather than diagnosis alone.
Holistic careAddress mental and physical health, substance use, self-care, relationships, housing, income, education, work, spirituality and recreation.
Early and continuous interventionStart rehabilitation during acute care and continue across discharge, outpatient and community services; do not postpone it until chronic disability develops.
Least restrictive careUse community-based, rights-respecting support whenever safe and feasible. Restriction must be necessary, proportionate, reviewed and time-limited.
Integration, not segregationPrefer ordinary schools, workplaces, housing and community activities with support over isolated programmes whenever possible.
Family partnershipWith the person’s consent, educate and involve relatives while protecting confidentiality and avoiding overcontrol or blame.
Peer and lived-experience involvementPeer workers provide credible hope, mutual support, role modelling, navigation and advocacy; they complement rather than replace clinical care.
Cultural relevanceUnderstand language, family patterns, spiritual beliefs and local explanatory models. Challenge harmful practices respectfully and collaborate with safe community supports.
Skill development in real settingsTeach and practise skills in the home, market, school or workplace where they will be used, not only in the ward.
Intersectoral teamworkHealth services must collaborate with social welfare, education, labour, housing, justice, community and civil-society resources.
Measurable outcomesReview progress using the person’s goals, functioning, participation, satisfaction, health and safety—not symptom reduction alone.
Human rights and non-discriminationProtect dignity, privacy, legal capacity, freedom from abuse and equal access to services and opportunities.

Major Domains of Rehabilitation

1. Health and symptom self-management

Teach the person to understand the illness, identify triggers and early warning signs, use coping strategies, attend reviews and participate in medicine decisions. Monitor adverse effects, physical health, sleep, nutrition, sexual health and substance use. A written relapse and crisis plan should name preferred help, emergency contacts and actions to take.

2. Activities of daily living

Assess grooming, bathing, dressing, eating, cooking, cleaning, laundry, shopping, transport, medication organization, budgeting and use of communication devices. Break complex tasks into manageable steps; demonstrate, practise, reinforce success and gradually reduce assistance.

3. Social and relationship functioning

Develop conversation, listening, assertiveness, conflict resolution, emotional regulation, parenting and boundary-setting skills. Address loneliness, family strain, exploitation, intimate-partner violence and unsafe relationships.

Advertisements

4. Education and vocational recovery

Clarify interests and strengths, restore study habits, liaise with schools, provide reasonable adjustments, develop job-readiness skills and support return to competitive employment where possible. Work should be meaningful, safe, fairly rewarded and chosen—not forced labour disguised as therapy.

5. Leisure, spirituality and community participation

Meaningful recreation, sport, creative work, worship, volunteering and social groups create routine, identity, pleasure and belonging. Activities must fit the person’s preferences rather than serve only to keep patients occupied.

6. Housing and environmental support

Assess safety, accessibility, privacy, family climate, transport, food security and risk of homelessness. Modify the environment, link to social protection and identify supported accommodation when independent living is not yet safe.

The Psychiatric Rehabilitation Process

StepActionsRationale
1. EngagementBuild trust, listen without judgment, explain rehabilitation and agree how the person wishes to participate.Goals are unlikely to succeed without a respectful therapeutic alliance.
2. Comprehensive assessmentAssess strengths, symptoms, cognition, function, physical health, risk, roles, supports, environment and personal aspirations.Diagnosis alone cannot identify the real barriers to participation.
3. Goal settingConvert priorities into specific, measurable, achievable, relevant and time-bound goals.Clear goals guide action and allow progress to be evaluated.
4. PlanningChoose interventions, responsible persons, resources, time frames and review dates; obtain consent and document the plan.Shared planning prevents fragmented or duplicated care.
5. Skill teachingUse explanation, demonstration, rehearsal, feedback, repetition and graded practice.Many functional skills improve through structured learning.
6. Environmental supportAdapt tasks, negotiate reasonable accommodations and mobilize family, financial, housing, education and work supports.Disability reflects both personal difficulty and environmental barriers.
7. Implementation in real lifePractise at home, school, work and community sites with the least assistance needed.Skills learned only in hospital may not transfer to everyday settings.
8. ReviewMeasure progress, satisfaction, safety and unintended effects; revise goals collaboratively.Needs and preferences change over time.
9. Transition and follow-upReduce support gradually, maintain access to help and prepare for setbacks without treating them as failure.Continuity protects gains and promotes long-term autonomy.

Comprehensive Rehabilitation Assessment

  • The person’s narrative: preferred name, identity, values, hopes, present concerns and desired roles.
  • Mental state: appearance, behaviour, speech, mood, thought, perception, cognition, insight and judgment.
  • Risk and safeguarding: suicide, self-neglect, violence, exploitation, abuse, wandering, substance-related harm and risk to dependants.
  • Function: basic and instrumental activities of daily living, communication, mobility, executive skills and ability to structure time.
  • Illness and treatment: course, relapses, helpful treatments, adherence barriers, adverse effects and coexisting substance use.
  • Physical health: vital signs, weight, nutrition, disability, pain, oral and sexual health, non-communicable disease and medicine monitoring needs.
  • Social context: relationships, caregiving responsibilities, housing, income, debts, legal problems, education, employment and stigma.
  • Strengths and resources: talents, interests, faith, coping skills, supportive people, land, tools, qualifications and community groups.

Functional formulation: State what the person wants to do, what currently prevents it, what strengths can be used, what environmental changes are needed and who will provide each support.

Resources and Support Systems

Health-service resources

  • Psychiatric units, outpatient clinics, primary health-care facilities and referral hospitals.
  • Community mental health outreach, home visits, crisis services and continuity clinics.
  • Occupational therapy, psychological therapy, social work, physiotherapy, pharmacy and general medical services.
  • Medicine supply, laboratory monitoring, assistive products and rehabilitation equipment where indicated.

Family and natural supports

Relatives, friends, neighbours, partners and trusted faith-community members can provide emotional support, practical help, reminders, transport and early recognition of relapse. Staff should assess caregiver burden, provide psychoeducation, discourage blame and agree boundaries. Involvement must follow the service user’s consent except where lawful safeguarding duties apply.

Peer and lived-experience support

Peer-support workers and user-led groups offer mutual understanding, recovery education, self-advocacy, social connection and navigation of services. They require training, supervision, role clarity, confidentiality and fair treatment.

Social, educational and vocational resources

  • Schools, universities, adult literacy programmes, apprenticeships and vocational institutes.
  • Employers, cooperatives, savings groups, supported employment and livelihood programmes.
  • Local government social-development services, disability organizations, legal aid and social-protection schemes.
  • Safe housing, transport, recreation, sport, libraries, places of worship and community centres.

Ugandan community resources

Depending on availability, the team may collaborate with the Village Health Team, Health Centre, district mental health focal persons, community development officers, probation and social welfare officers, disabled persons’ organizations, local councils, schools, employers, cultural and religious leaders and reputable non-governmental organizations. Availability must be verified locally; never promise a benefit or service before confirming eligibility and access.

Personnel and Their Roles

Advertisements

Person or professionalKey contribution
Service userDefines priorities, chooses goals, practises skills, monitors progress and participates in decisions. The person is the central member of the team.
Mental health nurseCoordinates care, assesses function and risk, teaches self-management, administers and monitors medicines, delivers psychosocial nursing interventions, involves family and ensures follow-up.
Psychiatrist or medical officerDiagnoses and treats mental and physical disorders, reviews medicine effectiveness and adverse effects, assesses complex risk and coordinates specialist referral.
Occupational therapistAssesses occupational performance, teaches daily-living and work skills, grades activities, adapts environments and supports participation in meaningful occupations.
Clinical psychologist or counsellorProvides psychological assessment and evidence-based therapies for symptoms, coping, cognition, trauma, motivation and relationships.
Social workerAssesses social needs, safeguards vulnerable people, facilitates family work, housing, benefits, legal help and links with community resources.
Peer-support workerUses lived experience to provide hope, practical guidance, advocacy and mutual support while observing professional boundaries.
PhysiotherapistAddresses mobility, pain, posture, exercise tolerance and physical deconditioning.
PharmacistReconciles medicines, teaches safe use, identifies interactions, supports adherence and helps monitor adverse effects.
Vocational specialist or teacherAssesses educational and employment goals, builds skills, liaises with institutions and supports reasonable accommodation.
Family or chosen supporterProvides agreed practical and emotional support, observes early warning signs and promotes independence without taking over unnecessarily.
VHT and community partnersSupport awareness, follow-up, navigation, inclusion and referral within defined competence and confidentiality safeguards.

Detailed Role of the Mental Health Nurse

  1. Establish a therapeutic relationship: use empathy, consistency, clear limits and respectful communication to support engagement.
  2. Assess and formulate needs: combine mental-state, physical, functional, risk and environmental findings with the person’s own goals.
  3. Develop the care plan: record prioritized nursing problems, measurable outcomes, interventions, responsible persons and review dates.
  4. Promote self-care: teach tasks step by step, praise progress, avoid doing for the person what they can safely do, and reduce assistance gradually.
  5. Support medicine self-management: explain purpose and schedule; monitor response, extrapyramidal effects, metabolic problems, sedation, sexual adverse effects and adherence barriers; promptly escalate serious reactions.
  6. Provide psychoeducation: teach about symptoms, stress, sleep, substance use, physical health, early warning signs and when to seek help.
  7. Deliver psychosocial interventions: use problem solving, behavioural activation, anxiety-management methods, social-skills training and motivational approaches within competence.
  8. Structure therapeutic activity: plan meaningful, age-appropriate activities with a stated goal, graded demand and evaluation—not activity for mere occupation.
  9. Work with families: obtain consent, assess knowledge and burden, correct myths, improve communication and develop a relapse-response plan.
  10. Coordinate referrals: make warm referrals, share necessary information lawfully, confirm appointments and follow whether access actually occurred.
  11. Protect rights and safety: prevent abuse, neglect, exploitation and unnecessary restriction; advocate for privacy, informed choice and inclusion.
  12. Prepare discharge: begin early, reconcile medicines, arrange follow-up, test the plan against realistic barriers and document emergency contacts.
  13. Evaluate outcomes: compare function and participation with baseline, ask the person and family what changed, document results and modify the plan.

Discharge, Aftercare and Relapse Prevention

  • Confirm a safe place to live, a reliable supporter where desired, food, transport and means of obtaining treatment.
  • Provide a clear medicine list: name, purpose, dose, timing, common adverse effects, urgent warning signs and refill plan.
  • Book the next appointment before discharge and give written directions and contact details.
  • List the person’s early warning signs, triggers, coping actions, preferred crisis responses and people to contact.
  • Arrange follow-up for physical health, substance use, occupational goals and social needs—not only psychiatric symptoms.
  • Use telephone contact, outreach or home visits when available for people at high risk of disengagement.
  • Escalate immediately when there is suicidal intent, severe self-neglect, rapidly worsening psychosis or mania, violent risk, delirium, intoxication/withdrawal, serious adverse medicine effects or inability to meet basic needs.

Safety, Ethics and Human Rights

Rehabilitation must never involve punishment, humiliation, forced unpaid labour, exploitation, discrimination or indefinite confinement. Obtain informed consent, protect privacy, use supported decision-making, disclose only information necessary for care, and document the legal and clinical basis of any restrictive intervention. Safeguarding concerns should be reported through appropriate clinical and legal pathways.

Evaluation of Outcomes

Evaluate both clinical and personal outcomes: symptom control; self-care and independent living; school or work participation; social relationships; stable housing; physical health; substance-use reduction; crisis visits and admissions; satisfaction, hope and quality of life; achievement of self-chosen goals; caregiver burden; and experiences of stigma or coercion. Review at agreed intervals and after major transitions or relapse.

Common Barriers and Practical Responses

BarrierResponse
Stigma and discriminationProvide accurate education, promote contact-based anti-stigma work, support disclosure choices and challenge exclusion through advocacy.
Poverty and transport costsCoordinate appointments, use nearby services, explore social protection and livelihood support, and avoid unaffordable plans.
Medicine stock-outs or adverse effectsPlan refills early, communicate with prescribers, monitor carefully and never advise abrupt unsupervised discontinuation.
Family conflict or burnoutAssess safety, provide family intervention, clarify roles, offer respite options where available and involve alternative supporters.
Cognitive or negative symptomsUse simple steps, repetition, written or visual cues, predictable routines, positive reinforcement and graded expectations.
Fragmented servicesName a coordinator, use shared plans, document referrals, communicate at transitions and verify follow-through.
Substance useUse non-judgmental screening, motivational intervention, harm reduction and integrated treatment rather than excluding the person.

Key Examination Points

  • Psychiatric rehabilitation aims at functioning, participation, autonomy and quality of life—not merely symptom removal.
  • The person receiving care is the central decision-maker and an active team member.
  • Effective rehabilitation combines individual skill development with modification of environmental barriers.
  • Assessment must cover strengths, function, risk, physical health, social circumstances and personal goals.
  • Hospital treatment, family care, peer support, vocational opportunity and community resources must be coordinated.
  • The mental health nurse has major roles in assessment, therapeutic engagement, teaching, medicine monitoring, care coordination, rights protection, discharge and evaluation.

Conclusion

Psychiatric rehabilitation is a continuous, collaborative and rights-based process. It helps people move beyond the patient role toward ordinary, self-chosen lives in their families and communities. High-quality practice joins effective clinical care with practical skills, meaningful occupation, social inclusion, peer and family support, environmental change and reliable follow-up.

References and Further Reading

Psychiatric Rehabilitation: Principles, Resources, Support Systems and Personnel Read More »

Respiratory System Assessment 

Respiratory System Assessment 

Respiratory System Assessment & Clinical Examination

1. Introduction & The History

Diseases of the respiratory system account for up to a third of deaths in most countries. The key to successful diagnosis is a clear and carefully recorded history. Symptoms may seem trivial or extremely distressing, but either may indicate serious and life-threatening disease. Most patients will present with breathlessness, cough, excess sputum, haemoptysis, wheeze, or chest pain.

I. Breathlessness (Dyspnoea)

Dyspnoea is breathlessness that is inappropriate to the level of physical exertion, or occurring at rest. The mechanisms are complex and relate to lowered blood oxygen (hypoxia), raised carbon dioxide (hypercapnia), cardiac disease, anaemia, thyrotoxicosis, or metabolic acidosis.

  • Exercise Tolerance: Assess how far the patient can walk at a normal pace on the level. Ask about their daily activities to estimate their mobility accurately.
  • Variability: Ask if symptoms have good and bad days, or specific worsening times. Asthma is often worse at night/early morning. COPD patients often report feeling fine sitting in bed, but become severely distressed upon exertion.

Medical Research Council (MRC) Dyspnoea Scale

GradeDescription of Breathlessness
1Not troubled by breathlessness except on strenuous exercise.
2Short of breath when hurrying or walking up a slight hill.
3Walks slower than contemporaries on the level because of breathlessness, or has to stop for breath when walking at own pace.
4Stops for breath after about 100 m or after a few minutes on the level.
5Too breathless to leave the house, or breathless when dressing or undressing.
Major Causes of Breathlessness:
Acute: Anaphylaxis, Asthma, Pneumothorax, Pulmonary embolus, Metabolic acidosis, Myocardial infarction, Pulmonary oedema.
Subacute: Pneumonia, Exacerbation of COPD, Pleural effusion, Malignancy, Cardiac tamponade.
Chronic: COPD, Interstitial lung disease, Chronic pulmonary emboli, Congestive heart failure, Valvular dysfunction, Severe anaemia, Obesity, Neuromuscular disorders.

II. Cough

Cough is defined chronologically: Acute (lasting less than 3 weeks) or Chronic (lasting more than 8 weeks). Acute coughs are mostly viral/bacterial. Any chronic cough (>8 weeks) requires a baseline CXR and spirometry.

  • Duration: A cough lasting weeks in a middle-aged smoker has major significance (possible malignancy).
  • Timing: A dry nocturnal cough, or one coming in long spasms, may be an early sign of asthma.
  • Triggers: Dust, animals, pollen, cold air, or exercise.
  • Associations: Severe coughing may trigger vomiting. Haemoptysis accompanying any cough requires urgent investigation.

Five Most Common Causes of Chronic Cough (with a normal CXR)

  1. Post-viral upper respiratory tract infection (URTI)
  2. Smoking
  3. Asthma (including cough-variant asthma and non-asthmatic eosinophilic asthma)
  4. Postnasal drip (e.g., from hay fever or sinusitis)
  5. Gastro-oesophageal reflux disease (GORD)

III. Sputum

Children and some adults swallow sputum, but always ask for a description:

  • Appearance: Yellow or green implies purulence/infection. Asthmatics may produce thick, jelly-like casts or yellow sputum heavily laden with eosinophils (even without infection). Clear, sticky sputum indicates chronic bronchitis without active infection. Frothy pink/white sputum is classical for pulmonary oedema. Rusty sputum suggests pneumococcal lobar pneumonia.
  • Amount: Large daily volumes (e.g., a cupful) strongly suggest bronchiectasis (though rarer now). Foul-smelling sputum indicates anaerobic infection or a lung abscess.

IV. Haemoptysis (Coughing up Blood)

This is a critical red-flag symptom that must never be dismissed. Fear often causes patients to hide it.

  • Differentiate if the blood is fresh (bright red) or altered, the volume, and frequency.
  • Ask about epistaxis (nosebleeds) or melaena (dark, tarry stools) to rule out upper airway or gastrointestinal bleeding masquerading as haemoptysis.
  • Major Causes: Lung malignancy/metastasis, TB, bacterial pneumonia, pulmonary emboli, bronchiectasis, severe congestive heart failure, and anticoagulant drugs.

V. Wheezing vs. Stridor

  • Wheeze: A high-pitched, musical sound typically heard in expiration due to small airway narrowing (asthma, COPD). Ask if the patient or their partner hears it at night.
  • Stridor: A harsh, high-pitched inspiratory noise indicating critical narrowing of the larynx, trachea, or main bronchi (upper airway). This is a medical emergency.

VI. Chest Pain

Lung parenchyma itself has no pain receptors; respiratory pain arises from the pleura or chest wall.

  • Pleuritic Pain: Sharp, stabbing, and distinctly worsened by taking a deep breath or coughing. Usually implies pleural inflammation from underlying pneumonia or pulmonary infarction (PE).
  • Constant Aching Pain: May be due to tumor invasion into the chest wall.
  • Aching/Tearing Pain: Seen in spontaneous pneumothorax. A massive pulmonary embolus can cause central, crushing, cardiac-type chest pain due to hemodynamic collapse.

VII. Other Crucial History Components

  1. Upper Airway/ENT: Rhinosinusitis coexists with asthma. Postnasal drip causes chronic cough. A hoarse voice lasting >4 weeks requires laryngoscopy (rule out left recurrent laryngeal nerve invasion by a lung apex tumour, or vocal cord carcinoma).
  2. Smoking & Recreational Drugs: Ask sympathetically. Get the age started/stopped and average consumption. Remember that smoking cannabis or crack cocaine can cause severe, early-onset emphysema.
  3. Occupational History: Take a chronological work history from the time they left school.
    • Asthma triggers: Paint sprayers (isocyanates), bakers (flour dust), hairdressers, laboratory workers (animal dander).
    • Asbestos exposure: Plumbers, shipbuilders, demolition workers, mechanics (brake linings). Exposure causes mesothelioma decades later, often presenting as a pleural effusion.

2. The Clinical Examination of the Respiratory System

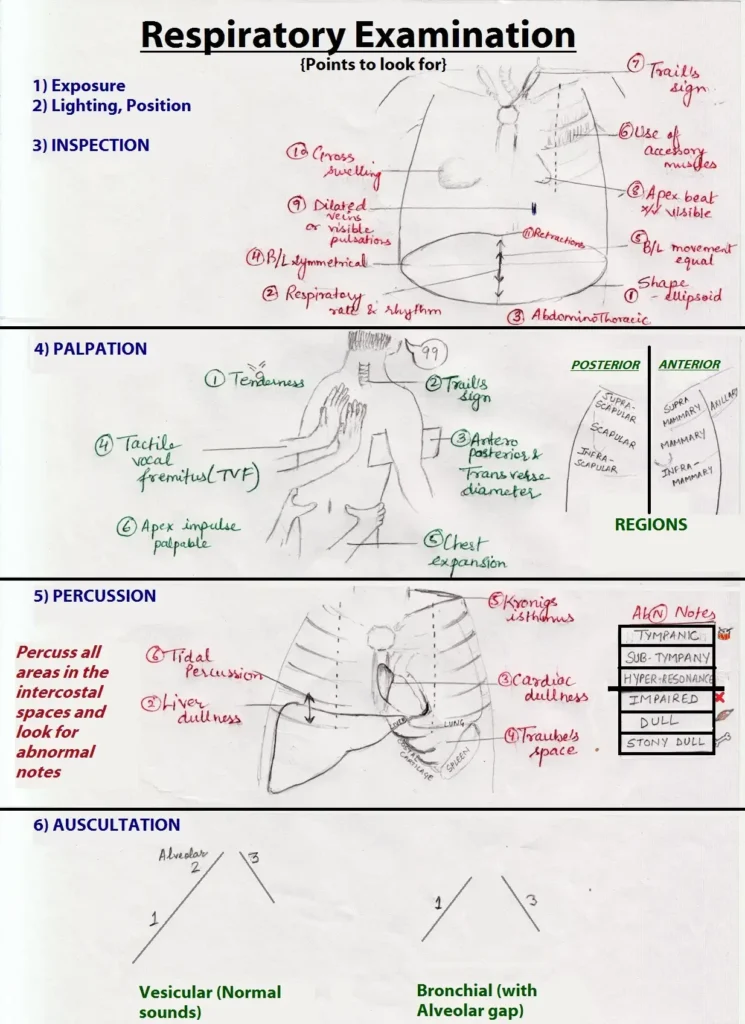
A respiratory examination is incomplete without a simultaneous general physical assessment. Gather maximum information using the classic sequence: Look, Feel, Percuss, Listen.

Step 1: General Assessment (Looking from the End of the Bed)

  • Posture & Effort: Is the patient breathless at rest? Are they using accessory muscles (sternomastoid)? Patients with severe COPD often breathe out through pursed lips to keep airways open.
  • Noises: Listen for an audible wheeze, stridor, or a weak/non-existent cough effort.
  • Bedside Clues: Look for inhalers, peak flow meters, oxygen masks, CPAP machines, or sputum pots.

Examining the Hands & Head

AreaClinical Sign to Look ForPossible Respiratory Cause
HandsClubbing of fingersLung cancer, pulmonary fibrosis, bronchiectasis, lung abscess.
HandsFine tremorSide effect of inhaled Beta-2 agonists (e.g., salbutamol).
HandsCO2 Flap (Asterixis) & Warm palmsHypercapnia (Carbon dioxide retention in Type 2 Respiratory Failure).
HandsTobacco staining (Tar)Heavy, chronic smoking.
NeckRaised Jugular Venous Pressure (JVP)Cor pulmonale (right heart failure due to chronic lung disease). If accompanied by a swollen, red face, suspect Superior Vena Cava Obstruction (SVCO).
Face / EyesCentral cyanosis (blue lips/tongue)Hypoxia / poor blood oxygenation by the lungs.
Face / EyesHorner's syndrome (Ptosis, miosis)Pancoast tumour at the lung apex invading the sympathetic chain.
Respiratory Rate and Rhythm: Normal is 14-16 breaths/min. Tachypnoea is an objectively high rate; Dyspnoea is the subjective feeling of breathlessness. Cheyne-Stokes breathing (cyclical deepening, quickening, then slowing to apnoea) is seen in severe heart failure or neurological damage.

Step 2: Inspecting the Chest (Looking)

Ensure the patient is resting comfortably at a 45-degree angle. Look for:

  • Surgical Scars: Thoracotomy scars (wrap from the scapula to the axilla), VATS scars (small axillary incisions), or midline tracheostomy scars.
  • Chest Shape:
    • Barrel Chest: Overinflated lungs due to severe COPD (increased anteroposterior diameter).
    • Spinal distortion: Kyphosis (forward bending) or Scoliosis (lateral bending) which restrict lung movement.
  • Movement Symmetry: If chest movement is diminished on one side, that is the side of the pathology. Watch for intercostal recession (sucking in of spaces on inspiration) indicating severe upper airway obstruction.

Step 3: Palpating the Chest (Feeling)

  1. Lymph Nodes: Palpate supraclavicular, cervical, and axillary nodes. Enlargement heavily alters cancer staging and treatment.
  2. Trachea Position: Place the 2nd and 4th fingers on the edges of the sternal notch and use the 3rd (middle) finger to feel the tracheal rings.
    • Pushed Away (Contralateral): Tension pneumothorax, large pleural effusion.
    • Pulled Towards (Ipsilateral): Lobar collapse, massive pulmonary fibrosis.
  3. Apex Beat: Displacement without tracheal shift may indicate scoliosis or left ventricular enlargement.
  4. Chest Expansion: Place thumbs in the midline hovering over the spine/sternum and fingers gripping the lateral ribcage. Ask the patient to take a deep breath. Thumbs should move apart equally. Asymmetry means unilateral restriction (e.g., effusion, consolidation).
  5. Tactile Vocal Fremitus: Use the flat of the hand/fingertips while the patient says "ninety-nine". Vibrations are increased over solid consolidation and decreased over fluid/air (effusion/pneumothorax).

Step 4: Percussing the Chest

Press the middle finger of the left hand firmly flat on the chest. Strike the middle phalanx sharply with the tip of the right middle finger, pivoting strictly from the wrist. Always compare side-to-side symmetrically.

  • Resonant: Normal air-filled lung tissue.
  • Dull: Solid tissue replacing air. Seen in lobar consolidation (pneumonia) or collapse.
  • Stony Dull: A flat, hard resistance resembling percussing a solid wall. Extremely characteristic of a pleural effusion.
  • Hyper-resonant: Excess air in the pleural space, classical for a pneumothorax.

Step 5: Auscultation of the Chest (Listening)

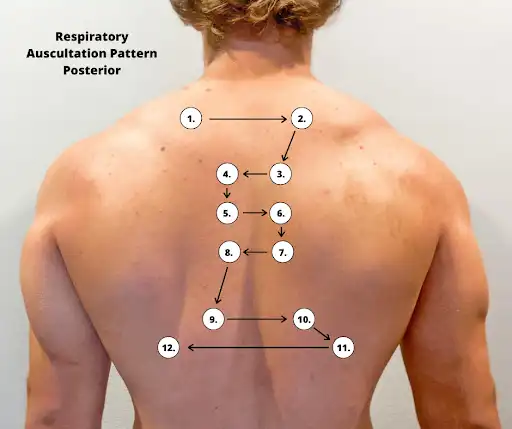
Listen using the diaphragm of the stethoscope. Ask the patient to take deep breaths in and out through their open mouth. Compare side-to-side.

1. Breath Sounds

  • Vesicular (Normal): Quiet, filtered sounds with no distinct pause between inspiration and expiration. Intensity is reduced over effusions or emphysema.
  • Bronchial (Abnormal): Harsh, loud, high-frequency sounds resembling listening over the trachea. The expiratory phase is hissing and prolonged, with a distinct pause between inspiration and expiration. Classical sign of consolidation (e.g., pneumonia) where the solid lung transmits airway sounds perfectly without filtering.

2. Added Sounds

  • Wheezes: Musical sounds due to airway narrowing. Polyphonic (multiple pitches) expiratory wheezes signify widespread obstruction (Asthma, COPD). Monophonic (single pitch) wheezes signify localized blockage (tumor, foreign body).
  • Crackles: Short, explosive, bubbling or clicking sounds from sudden opening of closed small airways. Coarse crackles are heard in bronchiectasis or severe pulmonary oedema. Fine, late-inspiratory crackles (sounding like rolling hair near the ear) are classical for diffuse interstitial pulmonary fibrosis.
  • Pleural Rub: A creaking, crunching sound (like walking on fresh snow) linked to pleuritic pain. Caused by inflamed pleural surfaces grating together.

3. Vocal Resonance

Listen with the stethoscope while the patient says "ninety-nine".

  • Increased Resonance: Over consolidation. The sounds are loud and clear. If they whisper and you hear it perfectly, it is called whispering pectoriloquy.
  • Decreased/Absent: Over fluid (pleural effusion) or air (pneumothorax) which block sound transmission.
  • Aegophony: A nasal, bleating sound heard at the upper margin of a pleural effusion.
🧠 Putting it together: The Diagnostic Triad
Why check Breath Sounds, Vocal Resonance, AND Tactile Fremitus?
Because they all test the same physics: sound transmission.
- Consolidation (Solid): Transmits sound better. ➔ Bronchial breathing, Increased resonance, Increased fremitus.
- Effusion/Pneumothorax (Fluid/Air): Blocks sound. ➔ Decreased breathing, Decreased resonance, Decreased fremitus.

3. Other Respiratory Investigations

I. Lung Function Tests (Spirometry)

Spirometry assesses lung size and airflow efficiency. The patient takes a maximal inspiration and exhales as hard and fast as possible to measure FVC (Forced Vital Capacity) and FEV1 (Forced Expiratory Volume in 1 second).

Defect TypeFEV1FVCFEV1/FVC RatioClassic Conditions
NormalNormalNormal> 70%Healthy lungs
ObstructiveSignificantly ReducedNormal or mildly reduced< 70%Asthma, COPD, Bronchiectasis
RestrictiveReducedSignificantly ReducedNormal (>70%)Pulmonary Fibrosis, Kyphoscoliosis

Peak Expiratory Flow Rate (PEFR): Evaluates the steepest slope of expiration. Easily monitored at home by asthmatics to detect early deterioration (noted by a massive drop in morning readings).

II. Arterial Blood Gases (ABGs)

Assesses the partial pressures of Oxygen (PaO2) and Carbon Dioxide (PaCO2).

TypeTypical ABG Values (On Room Air)Interpretation
Type 1 Resp FailurepH: 7.43 | PaCO2: 3.8 kPa | PaO2: 7.5 kPa | Sats: 91%Hypoxia with low/normal CO2. The lungs are failing to oxygenate, but the patient is hyperventilating, blowing off CO2 successfully.
Type 2 Resp Failure (Decompensated)pH: 7.25 | PaCO2: 9.3 kPa | PaO2: 7.5 kPa | Sats: 92%Hypoxia with HIGH CO2 & Acidosis. The patient's alveolar ventilation has completely failed. They are retaining toxic levels of carbon dioxide.

III. Imaging & Scans

  • Chest X-Ray (CXR): Systematically check the patient identity, alignment (rotation alters mediastinal silhouettes), bony skeleton, trachea position, cardiac outline, diaphragm height, and lung fields (zones). Lobar collapse shows distinct silhouette losses (e.g., middle lobe collapse obscures the right heart border).
  • CT Scan: Cross-sectional slices ideal for staging lung cancer, finding bronchiectasis, or detailing interstitial lung disease (High-Resolution CT).
  • V/Q Scan (Isotope Imaging): Combined Ventilation and Perfusion scan. A "matched defect" (no air, no blood) suggests lung parenchyma disease. An "unmatched defect" (lung gets air, but no blood reaches it) strongly points to a Pulmonary Embolism.
  • PET Scan: Uses a radioactive sugar (FDG) to locate highly metabolic tissues, presenting as 'hot spots'. Crucial for staging lung cancer metastasis.
  • Ultrasound: Excellent bedside tool for identifying and safely guiding drainage of pleural effusions and assessing diaphragmatic paralysis.

IV. Bronchoscopy, Biopsies, and Pleural Analysis

  • Flexible Bronchoscopy: Direct visualization of the bronchial tree to spot tumors, take biopsies, and wash out samples for TB/cytology. Endobronchial Ultrasound (EBUS) allows transbronchial needle aspiration of mediastinal lymph nodes for precise cancer staging.
  • Pleural Aspiration: Drawing fluid from an effusion. Differentiate a transudate from an exudate using Light's Criteria:
    • Exudate if: Pleural fluid protein/Serum protein > 0.5
    • Exudate if: Pleural fluid LDH/Serum LDH > 0.6
    • Exudate if: Pleural fluid LDH > two-thirds the upper limit of normal serum LDH.
    • Note: Pleural pH < 7.2 or very low glucose implies severe infection/empyema requiring urgent chest tube drainage.
  • VATS (Video-Assisted Thoracoscopic Surgery): Minimally invasive surgical approach to visually inspect the pleural cavity, biopsy the lung, perform lobectomies, or strip infected linings (decortication).
  • TB Testing: Use specialized Zeihl-Neelsen or auramine stains to find Acid-Fast Bacilli (AFB). GeneXpert (PCR) rapidly diagnoses active TB and Rifampicin resistance. Mantoux testing and IGRA blood tests check for latent TB exposure.

Quick Quiz

Respiratory Assessment Quiz

FON

Privacy: Your details are used only for quiz tracking and certificates.

Respiratory System Assessment  Read More »

Primary Survey in Trauma

Primary Survey in Trauma

Primary Survey in Trauma

I. Learning Objectives

Before diving into the trauma assessment, it is critical to establish our foundational goals. By the end of this module, you should be able to:

  • Define the Primary Survey: Understand its purpose, scope, and critical timing in emergency trauma care.
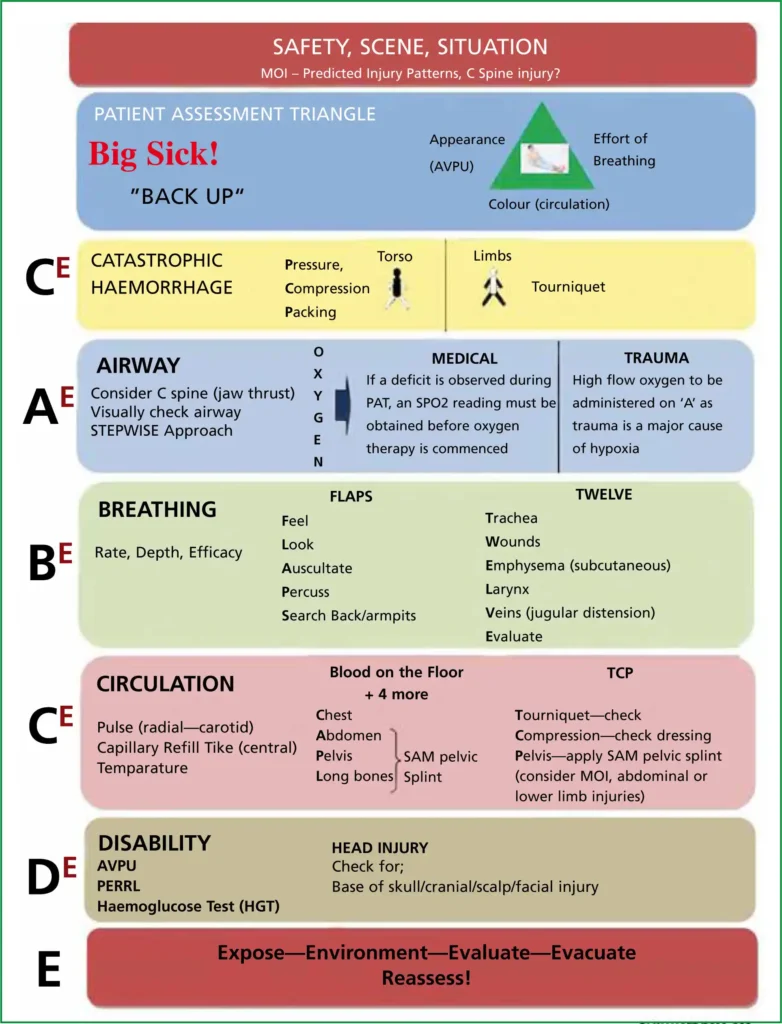
  • Understand ABCDE: Master the systematic, alphabetized approach to life-threatening injuries.
  • Understand AVPU: Rapidly and accurately assess a trauma patient's baseline level of consciousness.

II. What is the Primary Survey?

The primary survey is the absolute foundation of trauma resuscitation. In the chaos of a severe trauma bay, the primary survey provides a strict, unwavering framework to keep the medical team focused on what kills the patient fastest.

  • Initial Assessment: It is the initial assessment specifically designed and performed to detect and treat any immediate, life-threatening injuries.
  • Prioritizes the ABCs: It forces the clinician to treat Airway before Breathing, and Breathing before Circulation. You cannot move to the next letter until the current letter's life-threat is stabilized.
  • Organizes Evaluation: It strictly organizes the way trauma patients are evaluated, ensuring a unified approach whether the patient is in a rural clinic or a Level 1 Trauma Center.
  • The "First Chance": This is the first chance the trauma team has to figure out what happened to the patient (mechanism of injury) and to begin immediate life-saving treatments.

When Does the Trauma Assessment Start?

The trauma assessment is not a single event; it is divided into three distinct phases. The process actually begins the moment the patient comes into your line of sight.

  1. Across the Room Assessment: Before you even touch the patient, you look for massive, uncontrolled external hemorrhage. If you see arterial bleeding, you stop and control it (the "C" before ABC, or the MARCH protocol). You also form a rapid visual impression of their breathing and skin color.
  2. Primary Assessment (The ABCDEs): The structured, hands-on evaluation to identify and intervene on life-threats.
  3. Secondary Assessment (The Head-to-Toe): Only performed after the primary survey is complete and the patient is stabilized. It includes a comprehensive head-to-toe examination, detailed history, and looking for non-life-threatening injuries (like isolated fractures or lacerations).

III. A: Airway and Alertness with Cervical Spine Protection

The "A" step is the most critical. Without an open airway, oxygen cannot reach the lungs, rendering all other interventions useless.

1. Assessing Alertness (The AVPU Scale)

Before physically assessing the airway, quickly assess the patient's level of alertness. Ask a simple question like, "What is your name?" or "What happened to you?" Their response dictates their AVPU score and proves if their airway is currently patent.

  • A (Alert): The patient is awake, eyes open, and tracking you. (If they can speak in full sentences, their airway is patent).
  • V (Alert to Verbal stimuli): The patient is drowsy or eyes are closed but opens them or responds when you call their name loudly.
  • P (Alert to Pain): The patient does not respond to voice but responds (moans, withdraws, or localizes) to a painful stimulus.
  • U (Unresponsive to all stimuli): The patient exhibits absolutely no response to voice or pain. An unresponsive patient cannot protect their own airway and requires immediate intervention.

What is Painful Central Stimuli?

When testing for a response to pain, you must use central stimuli (testing the brain's response) rather than peripheral stimuli (which might just elicit a local spinal reflex). Acceptable methods include:

  1. Supraorbital Pressure: Firmly pressing your thumb into the bony ridge just beneath the eyebrow (avoid the eye itself).
  2. Trapezius Squeeze: Grabbing and firmly squeezing the trapezius muscle at the base of the neck/shoulder.
  3. Sternal Pressure (Sternal Rub): Applying firm, grinding pressure to the center of the patient's sternum with your knuckles. (Note: Use with caution to avoid severe bruising).

2. Cervical Spine (C-Spine) Protection

In trauma, you must assume a cervical spine injury until proven otherwise. Any movement of a fractured neck can sever the spinal cord, causing permanent paralysis or sudden death.

  • Place the patient in a supine position (flat on their back).
  • Perform in-line stabilization manually. One provider's sole job is to hold the patient's head completely still, keeping the nose aligned with the umbilicus.
  • Apply immobilization devices such as a properly sized rigid cervical collar and secure them to a backboard (if indicated by current local protocols).

(Reference Note: Supplemental demonstration videos on C-Spine application were included in the original presentation: https://youtu.be/PqiaHVYaK3c)

3. Airway Assessment & Interventions

Once the C-spine is protected, look inside the mouth. Are there broken teeth? Vomit? Blood? Smashed facial bones?

  • Airway Assessment: Look, listen, and feel. Listen for stridor, snoring, or gurgling (which indicate obstruction).
  • Treatment if Airway is NOT patent:
    • Suction: Use a rigid Yankauer suction catheter to aggressively clear blood, vomit, or secretions.
    • Remove debris: Carefully remove loose teeth or foreign objects using forceps or a gloved finger (only if the object is visible; avoid blind finger sweeps).
    • Insert airway adjunct: Use a nasopharyngeal airway (NPA) in conscious/semi-conscious patients. Use an oropharyngeal airway (OPA) only in completely unresponsive patients without a gag reflex.
    • Prepare for definitive airway: Prepare to assist the MD/Provider in inserting a definitive airway, such as an endotracheal tube (ETT). Gather the laryngoscope, blades, and tubes.

Airway Pitfalls to Avoid

Failure to secure an airway rapidly is the leading cause of preventable trauma death. Watch out for:

  • Delay in recognizing the compromised airway: Waiting too long to intervene when a patient is struggling to breathe.
  • Visual Cues Missed:
    • Comatose Patient: A patient with a Glasgow Coma Score (GCS) of 8 or less. (Remember the trauma adage: "GCS less than 8, Intubate!")
    • Combative / Agitated / Altered Mental Status: Never assume a trauma patient is just "drunk or high." Agitation is the premier sign of Hypoxia (brain screaming for oxygen). It can also be caused by Drugs/Alcohol, or a Traumatic Brain Injury (TBI).
    • Emesis and/or blood in the airway: Can rapidly lead to deadly aspiration pneumonia or total occlusion.

IV. B: Breathing and Ventilation

Once the airway is open, you must ensure the lungs are actually exchanging gas. An open pipe (airway) is useless if the bellows (lungs) are broken.

Breathing Assessment & Treatments

You are assessing to see if the patient is breathing adequately and regularly. Look for symmetrical chest rise, feel for broken ribs (crepitus), and listen to lung sounds bilaterally.

  • Treatment if breathing is present (but inadequate or patient is critical):
    • Administer highly concentrated oxygen via a non-rebreather mask at 15 Liters per minute to maximize oxygen delivery to traumatized tissues.
    • Check breathing using end-tidal CO2 (Capnography) to monitor the actual effectiveness of ventilation.
  • Treatment if breathing is absent (or agonizingly slow/shallow):
    • Open the airway further using a jaw thrust maneuver with a second person (we use jaw thrust instead of head-tilt-chin-lift to protect the C-spine).
    • Insert an airway adjunct (OPA or NPA) to keep the tongue off the back of the throat.
    • Assist ventilation with a bag-mask device (BVM) connected to high-flow oxygen.
    • Prepare to assist the MD in inserting a definitive airway such as an endotracheal tube.

Breathing Pitfalls to Avoid

Missing subtle signs of respiratory failure can lead to sudden cardiac arrest. Ensure attention is paid to visual cues:

  • Pallor: Pale, white skin indicating poor oxygenation and poor perfusion.
  • Cyanosis: Blue or purplish discoloration around the lips, mucous membranes, or fingertips indicating severe hypoxia.
  • Altered mental status: Brain hypoxia causes severe confusion and lethargy.
  • Pulse oximeter reading falling or not tracking: Do not ignore the monitor. If the SpO2 drops below 94% on high-flow oxygen, suspect a massive chest injury (like a tension pneumothorax or massive hemothorax) immediately.

V. C: Circulation and Control of Hemorrhage

Oxygenated blood must be pumped to the organs. Shock is essentially a failure of this circulatory system, most commonly due to massive blood loss (hypovolemic/hemorrhagic shock) in trauma.

Circulation Assessment

  • Palpate for Pulses: Check for the presence of both central (carotid, femoral) and peripheral (radial, pedal) pulses. Note the rate (is it dangerously tachycardic?) and the rhythm.
  • Check the Skin: Assess skin color, temperature, and moisture. Pale, cool, and diaphoretic (moist) skin is a classic, undeniable sign of clinical shock.

Treatment Interventions based on Findings

  1. Treatment if pulses are absent:
    • Initiate basic life-saving CPR immediately.
    • Assess for the underlying cause (e.g., did they bleed to death, or do they have a tension pneumothorax compressing the heart?).
  2. Hemorrhage Assessment:
    • Inspect carefully for any uncontrolled external or internal hemorrhage.
    • Look for skin color changes and massive bruising (ecchymosis) which can indicate gallons of blood pooled under the skin.
  3. Treatment if there is uncontrolled hemorrhage:
    • Use direct manual pressure on the wound.
    • Elevate the bleeding extremity above the level of the heart if possible.
    • Apply commercial tourniquets high and tight on extremities for massive arterial bleeding that pressure cannot stop.
    • Initiate rapid infusion of warmed isotonic crystalloid solution (e.g., Normal Saline or Lactated Ringers) via two large-bore IVs.
    • Prepare for possible blood administration (Massive Transfusion Protocol) and the use of a rapid infuser system to blast warmed blood into the patient under pressure.

Where is the Blood Going? (The 6 major sites of bleeding)

If a trauma patient is in shock but you do not see blood on the floor, they are bleeding into one of these internal compartments:

  • External bleeding: Obvious lacerations, amputations, or open fractures.
  • Intra-thoracic bleeding: Bleeding into the chest cavity (Massive Hemothorax); a single side of the chest can hold up to 3 liters of blood.
  • Intra-abdominal bleeding: Liver or spleen lacerations pouring blood into the belly.
  • Intra-pelvic bleeding: Smashed pelvic bones shredding major blood vessels (can hold massive amounts of blood; requires a pelvic binder).
  • Long bone fractures: A single femur fracture can hide 1 to 1.5 liters of blood in the thigh tissues.
  • Retroperitoneal bleeding: Bleeding behind the abdominal cavity (often from kidneys or severe pelvic trauma).

VI. D: Disability (Neurological Status)

This step involves assessing the patient's neurological baseline and screening for severe Traumatic Brain Injury (TBI).

Assessment & Treatment

  • Inspect Pupils: Check for PERRL (Pupils that are Equal, Round, and Reactive to Light). Unequal or "blown" pupils indicate massive brain swelling and impending brain herniation.
  • Glasgow Coma Scale (GCS): Calculate the score based on Eye, Verbal, and Motor responses.
  • Treatment / Interventions:
    • Obtain blood glucose (Hypoglycemia perfectly mimics severe brain injury and is easily reversible).
    • Obtain ABGs (Arterial Blood Gases) to monitor oxygen, CO2, and acid-base balance.
    • Prepare the patient for an urgent Head CT scan.

The Glasgow Coma Scale (GCS)

Legend: The GCS is obtained by adding the value for each category. Minimal = 3, Maximum = 15.

ScoreEye OpeningVerbal ResponseMotor Response
1NoneNoneNo movements
2Open to painful stimulationIncomprehensible soundsExtends to pain (Decerebrate posturing)
3Open to voiceInappropriate wordsAbnormal flexion to pain (Decorticate)
4Open spontaneouslyConfused, disorientedWithdraws to pain
5-Oriented, conversesLocalizes to painful stimulus
6--Obeys commands

(Reference Note: A supplemental GCS video was noted: https://youtu.be/_BGMQDmwRmA)

VII. E: Exposure and Environmental Control

You cannot treat what you cannot see. The trauma patient must be completely exposed to find hidden injuries, but they must be immediately protected from the environment to prevent deadly heat loss.

Assessment & Treatment

  • Assessment:
    • Remove all clothing. Cut the clothing off with trauma shears rather than manipulating broken limbs.
    • Preserve any clothing evidence: If there is a bullet hole or stab tear, cut around it, not through it, and place items in paper bags for law enforcement.
    • Reassess for any uncontrolled bleeding that was hidden by thick clothing.
    • Note any obvious injuries (lacerations, bruising, deformities) that will need to be addressed in the secondary survey.
  • Treatment: Apply warm blankets to the patient immediately after the exam is complete.
The Pitfall of Hypothermia:
Hypothermia in a trauma patient is a highly preventable complication. Cold blood does not clot properly. A cold trauma patient will continue to bleed internally, leading to the "Trauma Triad of Death" (Hypothermia, Coagulopathy, and Acidosis).

Preventive Measures for Hypothermia:

  • Keeping IV fluids warm in a specialized incubator.
  • Transfusing blood through an in-line fluid warmer.
  • Keeping the resuscitation area/room warm (turn up the thermostat, limit traffic in and out of the room).
  • Using active warming blankets (like a Bair Hugger) and overhead heating lights.
  • Keep the patient covered as soon as the physical exam is done.
  • Cover particularly high heat exchange areas like the scalp. (The head loses massive amounts of body heat).

VIII. F: Full Set of Vitals and Family

Once the ABCDEs are managed and the patient is exposed and warmed, formal vital parameters are documented, and the family is incorporated into the care plan.

1. Full Set of Vitals

Obtain a complete baseline set of vital signs. This includes:

  • Pulse (Heart Rate)
  • Oxygenation (SpO2)
  • Blood pressure (Manual or automated)
  • Temperature (Core temperature if possible)
  • Respirations (Rate and quality)
  • Weight (Crucial for pediatric weight-based drug dosing)
  • Pain score

Always continuously monitor and trend for changes. A steadily dropping blood pressure and rising heart rate is a massive red flag for ongoing internal bleeding.

2. Family Presence

Trauma affects the entire family system. Using an assigned liaison (like a social worker, chaplain, or dedicated nurse), communicate effectively with the family:

  • Explain the current status of the patient in clear, non-jargon terms.
  • Explain the immediate plan of care.
  • Inform them of the next steps: Is the patient going to emergency surgery? Being admitted to MedSurg or ICU? Or being transferred to a higher-level trauma center?

IX. G: Get Resuscitation Adjuncts

The "G" step represents the additional tools, tests, and tubes needed to fine-tune the resuscitation effort.

  • Laboratory Studies: Draw blood for trauma panels (CBC, Comprehensive Metabolic Panel, Lactic acid, Coagulation studies, Type and Crossmatch for blood transfusions).
  • Monitoring: Connect the patient to continuous cardiac rhythm and rate monitoring (Telemetry/ECG).
  • Gastric Tubes: Insertion of a nasogastric (NGT) or orogastric (OGT) tube to decompress the stomach, prevent vomiting, and reduce aspiration risk. (Note: Avoid nasogastric tubes if severe facial/basilar skull fractures are suspected; use orogastric instead).
  • Foley Catheter: Insert a foley catheter if the patient is intubated or if needed due to severe injury, to accurately monitor precise hourly urine output (the best indicator of organ perfusion).
  • Oxygenation/Ventilation tracking: Continually apply and adjust supplemental oxygenation. Monitor ventilatory status precisely with End-Tidal CO2 (Capnography).
  • Pain Assessment and Treatment: Trauma is excruciating. Assess pain formally and administer appropriate pharmacological (IV opioids) and non-pharmacological treatments once the patient is hemodynamically stable.

X. References & Sources

The protocols and structural layout of the primary survey in this presentation are based on established trauma guidelines, notably the Emergency Nurses Association (ENA) Trauma Nursing Core Course (TNCC).

  • http://www.trauma.org/archive/nurse/tertiarysurvey.html
  • http://www.ncbi.nlm.nih.gov/m/pubmed/2352294/
  • http://www.biomedcentral.com/content/pdf/1757-7241-20-77.pdf
  • Additional reference: (2014) TNCC 7th edition p. 39-52

Quick Quiz

Primary Survey Quiz

Health Assessment

Privacy: Your details are used only for quiz tracking and certificates.

Primary Survey in Trauma Read More »

History of nursing

History of Nursing in Uganda

Uganda History of Nursing

1. Introduction

The history of nursing in Uganda describes how nursing developed from traditional community-based care into a professional healthcare service involving formal education, clinical practice, regulation, research, leadership, and specialized nursing care.

Studying the history of nursing is deeply important because it helps explain the origins of current nursing practice, the influence of missionaries and colonial healthcare services, the systemic development of nursing education, and the growing role of Ugandan nurses in improving the health of individuals, families, and communities.

Learning Objectives:

By the end of these notes, a student should be able to:

  1. Define nursing history and its relevance to modern practice.
  2. Describe traditional healthcare and early nursing practices in Uganda.
  3. Explain the monumental contribution of missionaries and colonial medical services.
  4. Discuss the development of formal nursing education and professional regulation.
  5. Explain the evolution of modern nursing in Uganda post-independence.
  6. Identify the ongoing challenges and major achievements of nursing in Uganda.
  7. Relate historical developments to present-day nursing practice and continuous quality improvement.

2. Nursing Care in Uganda Before Formal Nursing Education

Before the establishment of formal nursing schools and modern Western hospitals, communities in Uganda relied largely on family members, traditional healers, herbalists, traditional birth attendants (TBAs), and robust community support systems to care for sick people.

Main Features of Traditional Healthcare

  1. Family-based care:

    Family members cared for sick relatives by providing food, water, shelter, warmth, basic hygiene, comfort, and direct assistance with daily activities.

    Example: A family member cared for a person with severe fever by keeping them comfortable, applying cool sponges, and seeking help from a traditional healer or other available senior caregiver in the village.
  2. Traditional herbal medicine:

    Traditional healers used locally available plants, roots, tree barks, and other traditional remedies to manage certain illnesses and alleviate symptoms.

    Example: A traditional healer might prepare a specific plant-based remedy for a person with severe stomach discomfort or diarrhea. The safety and effectiveness of any remedy depended entirely on the substance and its ancestral knowledge of use.
  3. Traditional birth attendants (TBAs):

    Highly experienced women in communities assisted mothers during pregnancy, childbirth, and the critical period after delivery.

    Example: A TBA might support a woman through prolonged labour with traditional massage and positioning, and help with immediate newborn care like cutting the umbilical cord using traditional tools.
  4. Spiritual and cultural support:

    Communities sometimes interpreted sudden illness through spiritual or cultural beliefs, often attributing sickness to ancestral spirits or curses. They used prayer, rituals, or sought advice from community elders as a core part of holistic care.

  5. Community participation:

    Relatives and neighbours actively supported households affected by illness through the provision of food, physical agricultural labour, childcare, and deep emotional support.

Limitations of Traditional Healthcare

  • Limited access to scientifically tested, evidence-based treatments.
  • Absolute lack of modern diagnostic equipment (x-rays, lab tests).
  • High risk of severe infection when hygiene and sterilization were inadequate (e.g., cutting umbilical cords with unsterilized reeds/blades).
  • Limited ability to manage acute emergencies like severe bleeding, obstructed labour, major traumatic injuries, and surgical cases.
  • Some traditional remedies could be ineffective, highly toxic, or cause dangerous delays in receiving necessary life-saving medical treatment.
Important Distinction: Traditional healthcare should not be dismissed as having no value. Family support, profound cultural understanding, and community solidarity remain vitally important in modern nursing today. However, clinical nursing interventions must always be guided by scientific evidence, strict patient safety, and regulatory professional standards.

3. Introduction of Missionary Healthcare and Formal Nursing

The introduction and development of Western-style hospital services in Uganda during the late nineteenth and early twentieth centuries played a major, foundational role in the growth of formal nursing education. The missionaries essentially laid the groundwork for the modern health system.

Sir Albert Cook

Sir Albert Cook was a dedicated British medical missionary who arrived in Uganda in 1896. In 1897, he established Mengo Hospital, which became a monumental centre for early medical care and later served as the bedrock for nursing and midwifery development in the country.

His massive contributions included:

  • Establishing early, structured hospital services.
  • Actively promoting the formal training of African healthcare workers (ward orderlies and assistants).
  • Supporting the massive development of maternal, medical, and surgical services.
  • Contributing to the foundational development of Mulago's early medical services.

Katharine (Lady) Cook

Katharine Cook was a pioneering missionary nurse who contributed significantly to early nursing and midwifery development. She worked alongside Sir Albert at Mengo Hospital and was instrumental in establishing formal training for indigenous midwives and nurses.

Her key contributions included:

  • Directly supporting the development of specialized maternity services.
  • Promoting and organizing formal midwifery training to combat high maternal/infant mortality.
  • Strictly supervising nursing and maternity services to establish standards of hygiene.
  • Contributing to the establishment of the first organized nursing education curriculums.

Importance of Missionary Healthcare in Nursing History

  1. It helped establish organized, permanent hospitals.
  2. It created a massive demand for trained, specialized nursing personnel.
  3. It introduced much more structured clinical instruction based on Western medical science.
  4. It heavily supported and modernized maternity and newborn services.
  5. It contributed to the gradual development of formal nursing standards and ethics.
Example: Instead of relying only on trial-and-error experience passed from one caregiver to another, a trainee nurse began learning through organized, structured instruction and closely supervised clinical practice in a hospital ward.

Historical perspective: Early nursing education developed within the confines of missionary and colonial healthcare systems. While these systems expanded access to certain formal services and saved many lives, training and professional opportunities for indigenous Africans were initially shaped and restricted by the profound inequalities and limitations of the colonial period.

4. Development of Formal Nursing Education in Uganda

Formal nursing education developed gradually through early maternity training, followed by enrolled nursing courses, registered nursing programmes, and much later, full university-level education.

  • 1919 — Formal midwifery training: Midwifery training was officially initiated at Mengo under the developing medical services. This addressed the desperate need for more organized maternity care and skilled, hygienic assistance during childbirth.
  • 1931–1933 — Nursing school development: The Nurses Training College was established in 1931, and the very first enrolled nurse class successfully qualified in 1933. This was a massive leap forward toward structured, recognized nursing education in Uganda.
  • 1955–1956 — Institutional and regulatory development: Mulago School of Nursing and Midwifery was established by the colonial government in 1955. Shortly after, on 12 April 1956, the Uganda Nurses and Midwives Council (UNMC) was formed, marking a critical step in professional regulation and legal recognition.
  • 1960s — Growth of registered and specialist training: Registered general nursing training officially commenced at Mulago in 1961, while registered midwifery training began in 1967. Mental health nursing training at Butabika also developed rapidly during this period, with sources commonly identifying 1960 as the important starting point for psychiatric nursing.
  • 1970s–1980s — Expansion and specialization: Training opportunities drastically expanded into nursing education, administration, public health, anaesthesia, ophthalmic care, and nurse tutoring. This helped perfectly prepare nurses for broader clinical and educational leadership responsibilities.
  • 1993 — Bachelor of Nursing Science (BNS): The introduction of the Bachelor of Nursing Science programme at Makerere University marked a historic milestone in university-level nursing education in Uganda. It strengthened the academic pathway for nursing leadership, advanced teaching, rigorous research, and advanced professional development.

5. Establishment and Role of the Uganda Nurses and Midwives Council (UNMC)

The Uganda Nurses and Midwives Council (UNMC) is the statutory body legally responsible for regulating nursing and midwifery standards and professional practice in Uganda. Its establishment in 1956 was an incredibly important milestone in the professionalization of nursing. The Nurses and Midwives Act of 1996 provides the modern legal framework for the Council's wide-ranging functions.

Major Functions of the Council

  1. Regulation of nursing practice: Sets, reviews, and strictly regulates professional standards of practice.
  2. Registration and enrolment: Oversees the official registration or enrolment of all eligible nurses and midwives, keeping the national register.
  3. Approval of training: Approves courses of study, inspects training facilities, and supervises nursing and midwifery education within its legal mandate.
  4. Professional conduct: Regulates professional ethical conduct and exercises disciplinary control over malpractice or gross misconduct.
  5. Protection of the public: Helps protect innocent patients from unsafe, unethical, or unqualified "quack" practice.
  6. Professional guidance: Advises the government and Ministry of Health on all matters relating to nursing and midwifery policy.

Why Regulation Matters

Regulation strictly helps ensure that nurses have the required academic qualifications, maintain ongoing professional competence, and practise safely within their legally authorized scope.

Example: A nursing graduate cannot just start working. They must pass exams and meet the applicable registration requirements before practising independently in a role that requires professional registration.

🚨 Remember for examinations: UNMC is the professional regulator; a nursing school or university provides the education, while the Ministry of Health has broader responsibility for health-sector policy and service delivery.

6. Development of Nursing After Uganda's Independence (1962)

Uganda gained independence in 1962. Following independence, the new government continued aggressively developing its health services and expanding nursing education to meet the heavy demands of a rapidly growing population.

Major Developments Post-Independence

  1. Expansion of government health facilities:

    The government continued developing health services across the country, building new hospitals and health centres, vastly increasing the need for trained nurses in rural and community settings.

  2. Growth of nursing training institutions:

    More nursing and midwifery institutions and training opportunities developed over time in various districts, helping massively increase the absolute number of nurses and midwives available to provide care.

  3. Development of specialized nursing:

    Nursing practice rapidly expanded beyond general bedside care to include highly specialized areas such as:

    • Midwifery and reproductive health.
    • Mental health and psychiatric nursing.
    • Community and public health nursing.
    • Anaesthesia and perioperative (theatre) care.
    • Ophthalmic (eye) nursing.
    • Paediatric and neonatal intensive care.
  4. Greater emphasis on preventive healthcare:

    Nurses increasingly contributed to massive national immunization drives, health education, antenatal care, family planning, disease prevention (like HIV/AIDS later on), and community outreach programs.

  5. Development of comprehensive nursing:

    Multipurpose "Comprehensive" nursing roles were promoted to help health workers deliver essential, all-round services at different levels of the healthcare system, especially in understaffed rural health centres.

Practical example: A comprehensive nurse working at a rural HC III may provide antenatal assessment in the morning, childhood immunization at noon, health education in the afternoon, give basic treatment within their scope, handle referrals, and conduct follow-up. This perfectly illustrates how modern nursing combines acute clinical care with prevention and community health.

7. Development of University-Level Nursing Education

University-level nursing education marked a profound shift toward stronger academic preparation, advanced research, leadership, teaching, and evidence-based clinical practice.

A key milestone was the introduction of the Bachelor of Nursing Science (BNS) programme at Makerere University in 1993. Subsequent expansion of nursing programmes created additional pathways for degree and postgraduate education. Research on Uganda's nursing education development identifies postgraduate nursing education as emerging in the early 2000s, including master's-level training starting from around 2003.

Importance of BNS Education

A Bachelor of Nursing Science programme prepares students to develop high-level skills in:

  1. Comprehensive, holistic patient assessment.
  2. Advanced nursing diagnosis and care planning.
  3. Executing evidence-based nursing interventions.
  4. Healthcare leadership, administration, and management.
  5. Teaching patients, families, and mentoring junior colleagues/students.
  6. Academic research and critical appraisal of medical literature.
  7. Public health epidemiology and community nursing.
  8. Complex professional ethics and legal accountability.
Example: A BNS nurse caring for a patient with diabetes should not only blindly administer prescribed treatment. The nurse should also deeply assess the patient, monitor blood glucose as indicated, provide detailed education on medication adherence and diabetic foot care, recognize early complications (like hypoglycaemia), coordinate referrals to dieticians, and continually evaluate the care plan. This beautifully illustrates the movement from simple task-focused care toward comprehensive, evidence-informed professional nursing.

8. Modern Nursing in Uganda

Modern nursing in Uganda includes advanced care in public and private hospitals, health centres, community services, educational institutions, and highly specialist facilities (like the Uganda Heart Institute or Cancer Institute).

Main Roles of Modern Nurses

RoleExplanationExample
Care providerProvides direct, hands-on nursing care.Dressing a wound using strict aseptic technique.
Health educatorTeaches patients, families, and communities.Educating a new mother about exclusive infant feeding.
AdvocateProtects patients' rights, voice, and dignity.Supporting and ensuring true informed consent before a surgery.
CommunicatorShares relevant clinical information clearly.Giving a structured, accurate shift handover to the incoming team.
Care plannerAssesses needs and plans individualized care.Developing a turning-plan for a bedridden patient at risk of pressure injuries.
Leader and managerCoordinates staff, resources, and activities.Organizing ward duties, creating duty rosters, and prioritizing urgent cases.
Research userApplies reliable, modern evidence to practice.Using the most current infection-prevention guidance for outbreak control.
Community health workerSupports primary prevention and population health.Participating in mass immunization and hygiene health education outreach.

Modern Nursing Principles

Today's nursing practice heavily emphasizes:

  • Patient-centred care (treating the person, not just the disease).
  • Evidence-based practice (using data to drive decisions).
  • Strict infection prevention and control (IPC).
  • Ethical conduct and absolute confidentiality.
  • Accurate, legal, and timely documentation.
  • Teamwork and interprofessional collaboration (working with doctors, pharmacists, lab techs).
  • Patient safety and continuous quality improvement.
  • Deep respect for cultural beliefs, spiritual needs, and individual human dignity.

9. Challenges in the Development of Nursing in Uganda

Although nursing has developed substantially since 1897, major challenges remain in the healthcare system.

  1. Shortage and uneven distribution of nurses:

    Some facilities, especially in deep rural and underserved areas, may have far fewer nurses than required.
    Effect: Workload massively increases, causing burnout, and timely life-saving care may become impossible.

  2. Limited resources:

    Facilities frequently face chronic shortages of essential equipment, medicines, sterile supplies, or suitable working space.
    Effect: Nurses severely struggle to provide the expected standard of care, forcing risky improvisations.

  3. Heavy workload:

    Exceptionally high patient numbers and strict staffing constraints can dramatically increase fatigue and reduce the time available for individual patients.
    Effect: Communication, accurate documentation, and vital patient education may heavily suffer.

  4. Continuing professional development (CPD) needs:

    New evidence, modern technology, and updated clinical guidelines require ongoing lifelong learning.
    Effect: Nurses need regular training, funding, and clinical supervision to maintain their competence.

  5. Rural–urban inequalities:

    Access to specialized services, advanced equipment, and professional development opportunities may differ vastly between rural villages and Kampala hospitals.
    Effect: Patients in some communities may experience fatal delays in receiving appropriate care.

  6. Professional recognition and working conditions:

    Workplace support, adequate remuneration (pay), clear career progression, and basic staff welfare (housing/meals) are ongoing struggles.
    These directly influence the recruitment, retention, and overall morale of the nursing workforce.

Measures for Improvement

  • Aggressively recruit and retain adequate nursing staff with better incentives.
  • Improve the equitable distribution of nurses across all health facilities, prioritizing rural hardship areas.
  • Consistently provide adequate medical equipment and essential supplies.
  • Strengthen and fund continuing professional development (CPD).
  • Support nurse educators, researchers, and provide strong clinical mentors for students.
  • Improve ward leadership, clinical supervision, and overall staff welfare.
  • Promote nursing research and enforce evidence-based practice across all levels.
  • Further strengthen nursing regulation and strict quality assurance by the UNMC.

10. Summary Timeline of Nursing History in Uganda

Year / PeriodHistorical DevelopmentSignificance
1896Albert Cook arrived in Uganda.Contributed to the development of pioneering missionary medical services.
1897Mengo Hospital was established.Became an incredibly important centre for early hospital care and medical training.
1919Formal midwifery training developed at Mengo.Promoted more organized, safer maternity care to lower infant mortality.
1931Nurses Training College was established.Advanced formal nursing education structure.
1933First enrolled nurse class officially qualified.Produced the first wave of formally trained African nurses.
1955Mulago School of Nursing and Midwifery was established.Massively expanded public nursing education in the country.
12 April 1956Uganda Nurses and Midwives Council (UNMC) was formed.Advanced strict professional regulation, licensing, and standards.
1961Registered general nursing training commenced at Mulago.Expanded professional nursing education to higher diploma levels.
1967Registered midwifery training commenced at Mulago.Significantly strengthened professional maternity training.
1970s–1980sSpecialist and advanced training opportunities expanded.Supported advanced teaching, administration, public health, and specialist practice.
1993Bachelor of Nursing Science (BNS) was introduced at Makerere University.Strengthened degree-level nursing education, boosting research and leadership.
1996Nurses and Midwives Act enacted.Provided a concrete legal framework for professional regulation and discipline.
2000s onwardDegree and postgraduate (Master's) education and other nursing pathways continued to expand rapidly.Supported high-level research, clinical leadership, teaching, and professional advancement in modern healthcare.
Sources: Uganda Ministry of Health publications, the Uganda Nurses and Midwives Council, Mulago School of Nursing and Midwifery, and extensive research on nursing education in Uganda.

Quick Quiz

History of Nursing in Uganda Quiz

FON

Privacy: Your details are used only for quiz tracking and certificates.

History of Nursing in Uganda Read More »

Musculoskeletal System Assessment

Musculoskeletal System Assessment

Physical Examination of the Musculoskeletal System

1. Introduction & Overview

1.1 Learning Objectives

  • Explain the purpose and principles of musculoskeletal assessment.
  • Obtain a focused and comprehensive musculoskeletal history.
  • Perform systematic inspection and palpation of joints and soft tissues.
  • Assess range of motion (ROM), muscle strength, gait, and functional capacity.
  • Perform selected special tests safely and accurately.
  • Recognize and document common abnormal findings effectively.

1.2 Overview of the Musculoskeletal System

A thorough understanding of anatomy is critical before examining a patient. The musculoskeletal system consists of interconnected structures working in harmony:

  • Bones: Provide structural support, protection of internal organs, and mineral storage (e.g., calcium and phosphorus).
  • Joints: The articulations between bones that permit movement and provide mechanical stability.
  • Skeletal Muscles: Contractile tissues that produce voluntary movement and maintain posture.
  • Tendons: Tough, fibrous connective tissues that connect muscle to bone (e.g., Achilles tendon).
  • Ligaments: Strong, inelastic bands that connect bone to bone, providing crucial joint stabilization (e.g., Anterior Cruciate Ligament).
  • Cartilage, Bursae, and Fascia: Structures that act as shock absorbers, reduce friction between moving parts, and support overall movement.

2. Principles of Case History Taking

A focused musculoskeletal history is the foundation of an accurate diagnosis. Before touching the patient, you must understand exactly why they are seeking help and why now (Pain? Loss of function? Deformity? Preventative reasons?).

2.1 Essential Components of the Case History

  • Presenting complaint and detailed history of the presenting complaint.
  • Family history (e.g., rheumatoid arthritis, osteoarthritis).
  • Previous or current medical conditions (e.g., diabetes, gout).
  • Medications taken (e.g., prolonged steroid use leading to osteoporosis).
  • Previous operations or surgical interventions.
  • History of accidents or trauma.
  • General body systems review.

2.2 Structured History Approach (Pain Assessment)

Always fully characterize the patient's pain and functional limitation. Use a structured approach to evaluate the characteristics of pain:

  1. Site / Location: Exactly where is the problem? Can they point to it with one finger?
  2. Onset & Duration: Was the onset sudden (e.g., acute trauma) or gradual (e.g., chronic osteoarthritis)?
  3. Character / Type of Pain: Is it aching, sharp, burning, or associated with stiffness?
  4. Severity / Intensity: Use a pain score from 0–10 (utilizing different pain scales appropriate for the patient's age and cognition).
  5. Timing / Pattern: Is the pain constant or intermittent? Is it worse in the morning (inflammatory) or at night/after use (mechanical)?
  6. Aggravating Factors: What specific movements or activities make it worse?
  7. Relieving Factors: Does rest, ice, or medication help?
  8. Associated Phenomena: Look for associated swelling, redness, severe weakness, numbness (paraesthesiae), instability, or fever.
🚨 RED FLAGS IN MUSCULOSKELETAL HISTORY
'Red flags' are signs or symptoms which—either on their own or within the context of a case history—may indicate a serious or life-threatening pathology (e.g., malignancy, severe infection, spinal cord compression) and must be investigated immediately.
  • The presence of fever or unexplained night sweats.
  • Unexplained weight loss or lethargy.
  • Constant pain or excruciating night pain (hallmarks of malignancy or bone infection).
  • Per rectal bleeding, abnormal vaginal bleeding, haematuria, or melaena.
  • Disturbed bowel or bladder function / Saddle anaesthesia (Cauda Equina Syndrome).
  • Chest pain related to exertion, persistent cough, or blood-stained sputum.
  • Altered sensation, special sense changes, polyuria, polydipsia, or syncope/dizziness.
  • Morning stiffness lasting more than one hour (indicates severe systemic inflammation like Rheumatoid Arthritis).
  • Swelling of a joint with absolutely no history of injury.
  • Progressive headaches, loss of appetite, or the appearance of any unusual lumps.

2.3 Differentiating Pain by Tissue Type

Listening carefully to how the patient describes their pain can often tell you exactly which anatomical structure is damaged:

Tissue InvolvedPain Characteristics & Clinical Presentation
LigamentsDull ache at rest; sharp, severe pain superimposed during movement that stretches the ligament.
Tendons & Para-tendonsSimilar to ligaments (deep dull ache). If inflamed, sharp pain upon active movement and severe pain upon direct deep pressure.
Bone LesionsDeep, boring, nagging, and constant unremitting pain. Often excruciating, especially at night. (If fractured: deep, severe, sharp, and excruciating pain upon movement).
Peripheral Nerve LesionsSharp, "electric-shock" like pain. Confined strictly to the anatomical territory of the peripheral nerve. Often associated with altered sensation or weakness.
Nerve Root LesionsSharp, electric-shock pain shooting down a limb, conforming precisely to a specific dermatome, with associated neural disturbances (radiculopathy).
Sympathetic NervesSensation of a diffuse, intensely burning or stinging quality.
Capsular PainMovement is severely restricted in most physiological ranges. The restriction may feel soft or hard, accompanied by widespread muscle spasm protecting many different movements (e.g., Adhesive Capsulitis / Frozen Shoulder — characterized by thickening, fibrosis, shrinking, and inflammation of the joint capsule).

Referred Pain (Somatic vs. Visceral)

  • Referred Pain: Pain perceived to be occurring in a part of the body located away from its actual source. While the affected area may be identified by the patient, it is usually not defined by sharp, distinct borders.
  • Somatic Pain Referral: For example, an S1 nerve root compression (from a lumbar disc herniation) refers pain in a well-defined distribution down the back of the leg and into the foot.
  • Visceral Pain Referral: Pain from internal organs is referred diffusely due to shared sympathetic and somatic nerve pathways in the spinal cord. For example, a myocardial infarction (heart attack) refers diffuse pain into the left arm, neck, and jaw.

3. Principles of Physical Examination

3.1 Golden Rules of Examination

  • Explain and Consent: Always explain the procedure to the patient and obtain explicit verbal consent before touching them.
  • Environment: Ensure privacy, adequate exposure of the area to be examined (while maintaining dignity), and excellent lighting.
  • Symmetry is Key: Always compare both sides of the body. Assess the unaffected/normal side first to establish a baseline.
  • Order of Palpation: Examine from less painful areas to more painful areas. Palpate the point of maximum pain last to maintain patient trust and prevent guarding.
  • Systematic Approach: Always begin with visual Inspection before Palpation. (Look, Feel, Move).
  • Safety First: Avoid forceful or sudden passive movements when a fracture or severe acute injury is suspected.
  • Continuous Assessment: Assess the patient's face for signs of pain before, during, and after any movement.
  • Documentation: Document all objective findings clearly and professionally.

3.2 General Survey & Posture

Observe the patient carefully the moment they walk into the room, before formally touching them:

  • Overall posture and whole-body alignment (e.g., stooped, leaning to one side).
  • Symmetry of limbs and joints at a glance.
  • General muscle bulk and any glaringly obvious gross deformities.
  • Ability to easily stand, walk, and transfer from a chair to the examination bed.
  • The use of walking aids or assistive devices (canes, crutches, walkers).
  • Facial expression (are they grimacing with every step?).
  • Overall mobility and activity level.

Assessment of Gait

Ask the patient to walk normally across the room and carefully observe:

  • Speed and rhythm of the walk.
  • Step length and symmetry of stride.
  • Base of support (is it a wide, unsteady stance?).
  • Arm swing (lack of arm swing can indicate Parkinsonism or shoulder pathology).
  • Turning mechanics and overall balance.
  • Common Abnormal Gait Patterns:
    • Antalgic gait: A painful limp where the patient spends as little time as possible bearing weight on the painful leg.
    • Steppage gait: High-stepping walk due to "foot drop" (weakness of ankle dorsiflexors).
    • Ataxic gait: Uncoordinated, staggering, wide-based walk (often cerebellar origin).
    • Spastic gait: Stiff, dragging, circumducting leg (often seen in stroke or cerebral palsy).
    • Trendelenburg gait: The pelvis drops on the opposite, unsupported side during the stance phase, indicating severe weakness of the hip abductor muscles (Gluteus Medius) on the standing leg.

4. The Musculoskeletal Examination Sequence

A complete musculoskeletal examination follows a rigid, systematic flow:
HISTORY ➔ INSPECTION ➔ PALPATION ➔ MOVEMENT ➔ MUSCLE POWER ➔ SPECIAL TESTS ➔ FUNCTION ➔ NEUROVASCULAR ASSESSMENT.

4.1 Close Inspection

Inspect systematically from head to toe, always comparing affected and unaffected sides:

  • Swelling, localized joint enlargement, or edema.
  • Redness (erythema), bruising (ecchymosis), or skin changes (e.g., psoriasis plaques over joints).
  • Deformity or abnormal anatomical alignment (e.g., squaring of the shoulder in anterior dislocation).
  • Muscle wasting (atrophy) or hypertrophy.
  • Surgical scars, traumatic wounds, or discharging sinuses (suggestive of underlying osteomyelitis).
  • Limb length discrepancy and overall symmetry.
  • Venous distention over the area.

4.2 Palpation

Palpate gently and systematically. Evaluate joints, muscles, soft tissues, bony contours, and ligaments:

  • Skin Temperature & Hydration: Use the back of your hand to feel for unnatural warmth (indicating inflammation or acute infection).
  • Tenderness: Pinpoint the exact location of tenderness.
  • Swelling / Effusion: Feel if the swelling is hard (bony), soft (tissue), or fluctuant (fluid inside the joint).
  • Bony Contours: Palpate bony landmarks, joint margins, abnormal shapes, osteophytes (bone spurs), and step-off deformities (fractures).
  • Muscles/Soft Tissues: Assess muscle tone (tonus, flaccidity, rigidity, spasticity), bulk, consistency, fasciculations (twitching), fibrosis, or calcification.
  • Ligaments: Feel for scar tissue, tears, thickening, or nodules.
  • Associated Structures: Palpate local lymph nodes, bursae, and arterial pulses.
  • Crepitus: Feel for a grinding or crackling sensation during movement, indicating degenerative changes (osteoarthritis) or tissue/bone grinding.

4.3 Assessment of Movement (Range of Motion - ROM)

Assess movements to evaluate joint function, coordination, muscle power, and willingness to move. Avoid putting unnecessary stress through damaged tissues.

  1. Active ROM: The patient moves the joint completely independently. This demonstrates their true functional capacity and highlights any unwillingness to move due to pain.
  2. Passive ROM: The examiner gently moves the patient's relaxed joint through its range. This helps differentiate between muscle/tendon problems (which hurt mostly on active movement) and joint/capsule problems (which hurt/restrict both active and passive movement).
  3. Active-Resisted Movements: The patient pushes against the examiner's resistance. This specifically tests muscle and tendon strength and reproduces pain in tendinopathies.

Movements to Assess (Compare bilaterally):

  • Shoulder: Flexion, extension, abduction, adduction, internal/external rotation.
  • Elbow: Flexion and extension.
  • Wrist: Flexion, extension, radial deviation, ulnar deviation.
  • Hip: Flexion, extension, abduction, adduction, internal/external rotation.
  • Knee: Flexion and extension.
  • Ankle: Dorsiflexion, plantarflexion, inversion, eversion.

Evaluation during movement: Note whether movement is full, reduced, or increased (hypermobile). Note the intensity and quality of pain, stiffness, instability, crepitus, paraesthesiae, or weakness. Ensure painful movements are tested last!

4.4 Muscle Tone, Bulk, and Strength Testing

Muscle Tone & Bulk

  • Bulk: Compare symmetry; look closely for unilateral wasting (disuse, nerve lesion) or enlargement.
  • Tone: Assess the muscle's natural resistance to passive movement.
    • Hypotonia: Reduced resistance, limb feels floppy (lower motor neuron lesion).
    • Hypertonia: Increased resistance.
    • Spasticity: Velocity-dependent increase in tone (catches when moved quickly; upper motor neuron lesion).
    • Rigidity: Constant increased tone throughout the entire range of movement (lead-pipe or cogwheel, seen in Parkinson's).

Muscle Strength (The MRC Scale)

Test movement against gravity and uniform resistance. Grade strength meticulously using the Medical Research Council (MRC) 0–5 scale:

MRC GradeDescription of Muscle Strength
Grade 0No visible or palpable muscle contraction whatsoever (complete paralysis).
Grade 1Flicker or trace of contraction visible/palpable, but no actual joint movement occurs.
Grade 2Active movement is possible, but only if gravity is completely eliminated (e.g., sliding arm across a flat table).
Grade 3Active movement against gravity is possible, but not against any added examiner resistance.
Grade 4Active movement against gravity AND against some resistance, but it is weaker than the normal side.
Grade 5Normal, full power against maximal resistance.

4.5 Functional Assessment

Determine exactly how the musculoskeletal problem affects the patient's activities of daily living (ADLs). Mimicking activities that cause pain is highly diagnostic. Assess:

  • Turning over in bed.
  • Moving from sitting to standing; standing on tip-toes; squatting.
  • Walking and climbing stairs.
  • Dressing, bathing, putting on shoes, fastening buttons at the back.
  • Combing the hair; opening door handles; feeding and fine hand function.
  • Ability to perform work and usual hobbies.
  • History of recent falls and the use of assistive devices.

4.6 Neurovascular Assessment (The 6 Ps)

This is particularly critical after trauma, casting, or orthopedic surgery to rule out limb-threatening ischemia or compartment syndrome. Assess the 6 Ps:

  1. Pain: Especially severe, unrelenting pain that is out of proportion to the injury, or extreme pain on passive stretching of the muscles.
  2. Pallor: Pale, white, or mottled skin distal to the injury indicating lack of arterial blood.
  3. Pulselessness: Absent or diminished distal pulses (a very late, dire sign).
  4. Paresthesia: Numbness, tingling, or "pins and needles" indicating nerve ischemia.
  5. Paralysis: Inability to move the digits (another late, severe sign of nerve/muscle death).
  6. Poikilothermia: The limb feels unnaturally cool to the touch compared to the rest of the body.

Action: Also rigorously assess capillary refill (< 2 seconds is normal). Urgent escalation to a doctor is required immediately if acute neurovascular compromise is suspected.

5. Joint Stability and Regional Special Tests

Special tests are provocative maneuvers performed only when clinically indicated by the history and basic exam. They isolate specific ligaments, tendons, or cartilages. Avoid causing injury during these tests.

A. Cervical Spine & Nerve Root Tests

These assess possible cervical nerve-root irritation, spinal cord involvement, and neck muscle function.

Test NameHow It Is PerformedPositive Finding & Clinical Meaning
Spurling TestExaminer positions the neck in extension and rotation (toward affected side) and applies gentle downward axial compression on the head.Reproduction of radiating pain down the arm suggests cervical radiculopathy (nerve root compression). Avoid if instability/acute trauma is suspected.
Cervical Distraction TestApply gentle, steady upward traction to the head and neck.Relief of radiating arm symptoms strongly supports cervical nerve-root involvement.
Upper Limb Tension Test (ULTT)Examiner actively moves the patient's shoulder, elbow, wrist, and neck through a standardized nerve-tension stretching sequence.Reproduction of familiar neurological symptoms indicates neural mechanosensitivity (irritated nerves).
Lhermitte's SignAsk the patient to flex their neck forward. Do not force the movement.An "electric-shock" sensation shooting down the spine or into the limbs. Indicates cervical spinal cord pathology (e.g., Multiple Sclerosis).
Cervical ROM TestAsk the patient to actively flex, extend, rotate, and laterally flex the neck.Pain or restricted movement indicates musculoskeletal dysfunction, though not diagnostic on its own.

B. Shoulder Joint Tests

These assess the rotator cuff muscles, subacromial impingement, biceps tendon, shoulder instability, and the labrum.

Test NameHow It Is PerformedPositive Finding & Clinical Meaning
Neer Impingement TestStabilize the scapula and passively, forcefully elevate the patient's internally rotated arm forward and overhead.Shoulder pain suggests possible subacromial impingement.
Hawkins–Kennedy TestFlex shoulder and elbow to 90°, then gently internally rotate the shoulder (push forearm down).Shoulder pain suggests possible subacromial impingement.
Empty Can / Jobe TestElevate arms ~90° in the scapular plane, thumbs pointing down (like emptying a can). Apply downward resistance.Pain or severe weakness suggests supraspinatus muscle or rotator cuff pathology.
Full Can TestSimilar to empty can, but thumbs point upward. Apply downward resistance.Pain or weakness suggests supraspinatus dysfunction.
Drop-Arm TestPassively abduct the arm to 90° and ask the patient to slowly and smoothly lower it to their side.Inability to lower smoothly, or the arm suddenly dropping, suggests a significant rotator cuff tear.
Painful Arc TestAsk the patient to actively abduct the arm from the side all the way overhead.Pain catching commonly between 60° and 120° of abduction suggests subacromial pain/impingement.
External Rotation ResistanceElbows tucked tightly against the sides and bent to 90°. Ask patient to externally rotate hands outward against your resistance.Pain or weakness indicates infraspinatus or teres minor (rotator cuff) dysfunction.
Lift-off TestPlace the back of the patient's hand against their lower back (lumbar area) and ask them to actively lift it away backward.Inability to lift away or severe weakness suggests subscapularis dysfunction.
Belly-Press TestPatient forcefully presses their palm flat against their abdomen while keeping the elbow pointed forward.Elbow drifting backward or wrist flexion compensation suggests subscapularis weakness.
Speed's TestShoulder flexed forward, elbow extended, forearm supinated (palm up). Resist further upward shoulder flexion.Pain deeply in the bicipital groove suggests long-head biceps tendon pathology.
Yergason's TestElbow flexed 90°. Resist as the patient attempts to supinate the forearm and externally rotate the shoulder.Pain over the bicipital groove suggests biceps tendon pathology.
Apprehension TestWith patient lying down, shoulder abducted to 90° and externally rotated, gently move the arm further into external rotation.Extreme fear of dislocation, facial grimacing, or muscular guarding suggests anterior shoulder instability.
Relocation TestFollowing a positive apprehension position, apply gentle posterior (downward) pressure to the front of the humeral head.Reduced apprehension or relief of pain firmly supports anterior instability.
Sulcus SignGently but firmly pull the relaxed arm downward at the elbow while observing the shoulder.A visible gap/dimple appearing just below the acromion suggests inferior shoulder laxity.
Cross-Body Adduction TestMove the patient's arm horizontally across their chest toward the opposite shoulder.Pain directly localized over the top of the shoulder suggests Acromioclavicular (AC) joint pathology.
O'Brien Active Compression TestFlex arm forward 90°, adduct slightly. Patient resists downward pressure with thumb down, then repeats with thumb up.Deep shoulder pain or clicking (worse thumb down) suggests labral pathology (SLAP tear); pain localized over AC joint indicates AC pathology.

C. Elbow Joint Tests

Test NameHow It Is PerformedPositive Finding & Clinical Meaning
Cozen's TestPatient makes a fist, extends the wrist, and radially deviates against examiner resistance with the elbow flexed.Severe pain localized over the lateral epicondyle confirms lateral epicondylalgia (Tennis Elbow).
Mill's TestExaminer passively pronates the forearm, fully flexes the wrist, and extends the elbow gently.Lateral elbow pain suggests lateral epicondylalgia.
Maudsley's TestResist active extension of the middle finger while the patient's elbow is extended.Lateral epicondylar pain confirms extensor tendon involvement.
Golfer's Elbow TestGently extend the elbow and wrist while supinating the forearm (passive stretching), OR assess resisted wrist flexion.Pain localized over the medial epicondyle suggests medial epicondylalgia (Golfer's Elbow).
Valgus Stress TestApply a gentle valgus (outward) force to the elbow, usually flexed around 20–30°.Medial pain or excessive joint opening suggests Ulnar Collateral Ligament (UCL) injury.
Varus Stress TestApply a gentle varus (inward) force to the flexed elbow.Lateral pain or excessive opening suggests Lateral Collateral Ligament (LCL) injury.
Tinel's Sign at the ElbowGently tap repeatedly over the ulnar nerve resting in the cubital tunnel (funny bone area).Electric tingling shooting into the little finger and half of the ring finger suggests ulnar nerve irritation.
Hook TestWith the elbow flexed 90° and forearm supinated, examiner attempts to hook a finger under the thick distal biceps tendon in the antecubital fossa.Inability to hook the tendon (it feels empty) raises severe concern for a complete distal biceps tendon rupture.

D. Wrist and Hand Tests

Test NameHow It Is PerformedPositive Finding & Clinical Meaning
Phalen's TestHold the wrists in maximum forced flexion, pushing the backs of the hands together, for up to 60 seconds.Tingling or numbness in the thumb, index, middle, and radial half of the ring finger strongly suggests Carpal Tunnel Syndrome (Median nerve compression).
Reverse Phalen's TestHold the wrists in maximum extension with palms pushing together (prayer position) for 60 seconds.Median nerve-distribution symptoms suggest Carpal Tunnel Syndrome.
Tinel's Sign at the WristTap gently and repeatedly over the median nerve precisely at the volar carpal tunnel.Tingling shooting into the median nerve finger distribution suggests nerve irritation.
Durkan's Compression TestApply direct, firm pressure with your thumbs directly over the carpal tunnel for 30 seconds.Reproduction of median nerve symptoms (highly sensitive test for Carpal Tunnel).
Finkelstein TestPatient tucks their thumb inside a closed fist. Examiner gently moves the wrist downward into ulnar deviation.Sharp pain over the radial styloid highly suggests de Quervain's tenosynovitis. (Perform gently to avoid unnecessary agony).
Thumb CMC Grind TestApply gentle axial compression to the first metacarpal bone while grinding/rotating it at the base of the thumb.Pain or harsh crepitus indicates Carpometacarpal (CMC) joint osteoarthritis.
Allen TestCompress both radial and ulnar arteries simultaneously at the wrist. Have patient pump fist until hand is pale. Release *only* the ulnar artery and observe capillary refill perfusion.Delayed or absent return of pink hand colour (>5 secs) suggests impaired collateral blood flow. Mandatory before radial artery blood gas procedures.
Froment's SignAsk the patient to tightly hold a piece of paper between the thumb and side of the index finger while you pull it away.If the thumb forcefully bends at the interphalangeal joint to hold the paper, it indicates ulnar nerve weakness (adductor pollicis paralysis).
Bunnell–Littler TestCompare passive PIP joint flexion while the MCP joint is held extended vs. flexed.Restricted flexion that improves when MCP is flexed = intrinsic muscle tightness. Restricted in both = joint capsule contracture.
Elson TestFlex the PIP joint to 90° over a table edge. Ask the patient to extend the finger against resistance.Weak PIP extension while the DIP joint goes rigidly straight suggests a central slip injury of the extensor mechanism (impending boutonnière deformity).

E. Knee Joint Tests

These tests assess the critical stability provided by the cruciate ligaments (ACL/PCL), collateral ligaments (MCL/LCL), the shock-absorbing menisci, and patellar tracking.

Test NameHow It Is PerformedPositive Finding & Clinical Meaning
Lachman TestPatient supine, knee flexed approx 20–30°. Examiner heavily stabilizes the distal femur and firmly pulls the proximal tibia sharply forward.Excessive forward tibial movement or a "mushy/soft" endpoint strongly diagnoses an Anterior Cruciate Ligament (ACL) tear.
Anterior Drawer TestPatient supine, knee flexed 90°, foot stabilized flat on bed. Pull the proximal tibia forward with both hands.Excessive anterior movement suggests ACL laxity or rupture.
Posterior Drawer TestWith the knee at 90° flexion, push the proximal tibia firmly backward.Excessive posterior sagging or backward movement suggests a Posterior Cruciate Ligament (PCL) injury.
Valgus Stress TestApply an inward (valgus) force to the outside of the knee while pulling the ankle outward, opening the medial joint line. Tested at 0° and 30° flexion.Medial joint opening, gaping, or severe pain diagnoses a Medial Collateral Ligament (MCL) tear.
Varus Stress TestApply an outward (varus) force to the inside of the knee to open the lateral joint line.Lateral joint opening or pain suggests a Lateral Collateral Ligament (LCL) injury.
McMurray TestPatient supine. Fully flex the knee, rotate the tibia internally/externally, and slowly extend the knee while applying appropriate valgus/varus stress to the joint line.Sharp joint-line pain or a palpable/audible "clunk" or click indicates a meniscal tear.
Thessaly TestPatient stands flat-footed on one leg with the knee slightly bent (20°). Patient actively twists their body and knee internally and externally 3 times.Joint-line pain, a feeling of catching, or locking suggests meniscal injury. Avoid if weight-bearing is obviously unsafe.
Apley Compression TestPatient lies prone (face down) with the knee flexed 90°. Examiner pushes down heavily through the heel (axial load) while grinding/rotating the foot.Pain localized precisely at the joint line confirms a meniscal lesion.
Patellar Apprehension TestPatient supine. Examiner gently pushes the kneecap (patella) laterally outward while the knee is slightly flexed.Extreme fear, muscle guarding, or the patient grabbing your hand to stop you suggests severe patellar instability or previous dislocation.
Patellar Tap / BallottementWith the leg completely straight, examiner milks fluid downward from the suprapatellar pouch and sharply taps down on the kneecap.A floating, bouncing, or "clicking" patella that hits the femur beneath suggests a moderate to massive knee joint fluid effusion.
Sweep / Bulge TestSweep fluid upward from the medial side of the knee into the pouch, then press the lateral pouch and watch the medial side.A visible ripple or distinct fluid bulge appearing on the medial side indicates a small knee effusion.
Clarke's Patellar Grind TestApply gentle downward pressure above the superior pole of the patella while the patient actively contracts their quadriceps muscle.Retropatellar pain/grinding suggests patellofemoral irritation (Chondromalacia patellae). Note: Highly non-specific and painful.

F. Hip Joint & Pelvic Tests

These help assess hip flexion contractures, intra-articular hip joint pathology, sacroiliac-region pain, and abductor muscle weakness.

Test NameHow It Is PerformedPositive Finding & Clinical Meaning
Thomas TestPatient lies supine. Ask them to pull one knee tightly to their chest (flattening the lumbar spine) while observing the opposite, relaxed leg.The opposite thigh involuntarily lifting off the bed proves a fixed hip flexion contracture (tight iliopsoas).
Trendelenburg TestAsk the patient to stand entirely on one leg while the examiner observes the horizontal alignment of the pelvis from behind.If the pelvis drops downward on the unsupported/lifted leg side, it diagnoses severe weakness of the stance-side hip abductors (Gluteus Medius).
FABER / Patrick TestFlexion, ABduction, External Rotation. Place the ankle resting above the opposite knee (Figure-4 position). Gently push the bent knee down toward the bed.Deep anterior groin pain = hip joint pathology. Posterior pain localized over the dimples = Sacroiliac (SI) joint pathology.
FADIR TestFlexion, ADduction, Internal Rotation. Flex hip and knee to 90°, adduct across midline, and internally rotate.Groin pain or mechanical pinching suggests Femoroacetabular Impingement (FAI) or a labral tear.
Ober's TestPatient lies on their side. Examiner passively abducts and extends the upper hip, then allows the heavy thigh to drop downward toward the bed.Inability of the leg to drop smoothly (it stays "hanging" in mid-air) proves a severely tight Iliotibial (IT) band.
Ely's TestPatient lies prone. Examiner rapidly flexes the patient's knee toward their buttocks.Spontaneous hip flexion or the pelvis lifting off the table on that side indicates severe rectus femoris muscle tightness.
Log-Roll TestWith the patient completely supine and leg relaxed flat, place hands on mid-thigh and gently roll the entire leg inward and outward.Severe pain, catching, or highly restricted rotation suggests intra-articular hip joint pathology or a femoral neck fracture.
Hip Scour TestFlex the hip 90° and apply gentle downward axial loading while sweeping the hip in a wide circular arc (internal/external rotation).Deep groin pain, catching, or grinding confirms intra-articular hip damage (e.g., osteoarthritis). Avoid entirely if a fracture is suspected.
Leg-Length AssessmentMeasure carefully with a tape measure from the anterior superior iliac spine (ASIS) to the medial malleolus of the ankle. Compare both sides.A difference > 1-2 cm indicates a true anatomical leg-length discrepancy. (Apparent discrepancy arises from pelvic tilt/scoliosis without true bone shortening).
Sacroiliac (SI) Joint Tests (Requires a "Cluster" of positives for diagnosis)
Gaenslen's TestPatient lies near the edge of the bed. One hip is pulled tightly to the chest, while the other leg drops freely off the side of the bed into forced extension.Reproduction of familiar, sharp posterior pelvic pain suggests SI-region pathology.
SI Joint Distraction TestPatient supine. Apply heavy, sustained outward pressure crossed over both anterior superior iliac spines (ASIS), pushing them apart.Familiar deep posterior pelvic pain implies anterior SI ligament sprain/inflammation.
SI Joint Compression TestPatient lies on their side. Apply heavy, steady downward pressure directly over the upper iliac crest toward the bed.Reproduction of familiar pain strongly supports SI-region inflammation.
Thigh Thrust TestPatient supine, hip flexed to 90°. Examiner pushes heavily straight downward through the line of the femur to sheer the SI joint.Sharp posterior pelvic pain suggests SI joint dysfunction.
Sacral Thrust TestPatient lies prone. Apply sudden, firm, springing downward pressure directly over the center of the sacrum.Reproduction of familiar deep pelvic pain suggests SI-region involvement.

G. Ankle and Foot Tests

Test NameHow It Is PerformedPositive Finding & Clinical Meaning
Anterior Drawer Test of the AnkleStabilize the lower leg rigidly with one hand, cup the heel with the other, and gently draw the calcaneus and talus sharply forward.Excessive forward movement or a soft endpoint confirms a tear of the Anterior Talofibular Ligament (ATFL) (the most common ankle sprain).
Talar Tilt TestStabilize the lower leg and firmly tilt the heel inward (inversion) or outward (eversion).Excessive tilt/gaping indicates lateral ligament (CFL) tear or medial deltoid ligament injury, depending on direction.
Thompson TestPatient lies prone with feet hanging freely beyond the bed edge. Examiner violently squeezes the bulky calf muscles.Normally the foot should plantarflex. An absent or markedly reduced plantar flexion response diagnoses a complete Achilles tendon rupture.
Matles TestPatient lies prone and actively flexes both knees to 90°. Observe the natural resting posture of both feet.If the injured foot drops into a more neutral or dorsiflexed position (rather than pointing toes naturally), it indicates an Achilles tendon rupture.
Squeeze Test (Syndesmosis)Firmly compress the tibia and fibula bones together tightly at the mid-calf.Pain referred downward near the distal tibiofibular joint confirms a "High Ankle Sprain" (syndesmotic injury).
External Rotation Stress TestWith the knee flexed 90° and ankle neutral, gently but forcefully externally rotate the foot outward.Sharp pain over the distal tibiofibular area suggests severe syndesmotic injury.
Tinel's Sign at Tarsal TunnelGently tap directly over the posterior tibial nerve curving behind the medial malleolus (inner ankle bone).Electric tingling or shooting pain into the sole of the foot indicates Tarsal Tunnel Syndrome.
Windlass TestActively or passively forcibly extend the great toe upward, while the patient is standing or seated.Reproduction of sharp, tearing pain under the heel or arch strongly supports Plantar Fasciitis.
Mulder's Click TestCompress the metatarsal heads together tightly with one hand, while applying upward pressure between the metatarsal spaces with the thumb.Searing pain or a palpable/audible "click" between the 3rd and 4th toes indicates Morton's Neuroma.

H. Lumbar Spine & Nerve-Root Tests

Test NameHow It Is PerformedPositive Finding & Clinical Meaning
Straight Leg Raise (SLR / Lasègue's)Patient lies completely supine. Passively and slowly raise the straightened symptomatic leg upward by the heel while monitoring the face for pain.Familiar sharp, shooting pain radiating down the back of the leg (sciatica) between 30° and 70° strongly suggests lumbosacral nerve-root compression (herniated disc). (Tight hamstring pain behind the knee is non-specific).
Crossed Straight Leg RaisePerform the SLR test on the unaffected, healthy leg while observing symptoms.Pain shooting down the affected leg while lifting the healthy leg is a highly specific sign of a massive central lumbar disc herniation.
Slump TestPatient sits on edge of bed and slumps forward (curving spine). Passively extend the knee and dorsiflex the ankle; then ask them to lift their chin.Reproduction of shooting neural symptoms that vanish when the neck is extended confirms neural mechanosensitivity (nerve tethering).
Femoral Nerve Stretch (Prone Knee Bend)Patient lies prone. Passively flex the knee entirely to the buttocks and gently lift/extend the hip upward.Sharp, burning pain radiating down the anterior thigh suggests upper lumbar (L2-L4) nerve-root compression.
Schober TestMark the L5 spinous process, and a point 10 cm directly above it. Ask the patient to bend forward touch their toes. Measure the new distance.An increase of less than 5 cm during maximum forward flexion proves severely restricted spinal mobility (classic sign of Ankylosing Spondylitis).
Lumbar Extension TestAsk the patient to stand and lean backward, extending the lumbar spine maximally.Reproduction of central back pain suggests extension-sensitive spinal pathology (e.g., spinal stenosis, facet joint arthritis).
Kemp's / Quadrant TestWith the patient standing, the examiner gently guides them into maximum extension, rotation, and lateral flexion simultaneously.Localized back pain or radiating pain implies severe facet joint disease or narrowing of the intervertebral foramen.
Valsalva ManoeuvreAsk the patient to bear down firmly, as if straining during a difficult bowel movement.Sudden reproduction of radiating pain down the leg suggests a space-occupying lesion inside the spinal canal (like a large herniated disc) reacting to increased intrathecal pressure.
Heel-Walking TestAsk the patient to walk across the room balancing strictly on their heels with toes pointed up.Foot drop or inability to maintain the toes up indicates severe weakness of the ankle dorsiflexors (L4–L5 nerve-root compression).
Toe-Walking TestAsk the patient to walk across the room strictly on their tiptoes.Inability to hold the heel off the ground indicates severe calf/plantar-flexor weakness (S1 nerve-root compression).

6. Common Abnormal Findings & Clinical Safety

6.1 Common Abnormal Findings

  • Joint Swelling: Caused by acute inflammation, trauma (haemarthrosis), or chronic synovial effusion.
  • Crepitus: Grating sound/feel signifying degenerative osteoarthritis cartilage loss, or the horrific grinding of fractured bone ends.
  • Deformity: Visible anatomical distortion due to fracture, joint dislocation, or chronic rheumatoid disease (e.g., swan neck deformity).
  • Muscle Wasting: Loss of muscle bulk due to prolonged disuse, joint immobilization, or severe peripheral nerve lesions.
  • Reduced ROM: Can result from severe pain, joint inflammation, capsular stiffness, bony blocks, or muscle contracture.
  • Weakness: Caused by direct neurological impairment, muscular tears, or systemic weakness.
  • Red, Hot, Very Painful Joint: A massive red flag. Always highly consider septic arthritis (medical emergency) or acute gouty inflammation.

6.2 Clinical Safety and Nursing Considerations

  • Suspect a fracture? Immediately immobilize the limb and strictly avoid unnecessary movement or ROM testing to prevent severing arteries.
  • Severe pain? Conduct a thorough pain assessment before attempting any active or passive ROM. Do not force movement through agonizing pain.
  • Recent surgery? Strictly follow the surgeon’s prescribed weight-bearing and movement restrictions (e.g., hip precautions post-arthroplasty).
  • Suspected spinal injury? Maintain strict spinal precautions (log-rolling, hard collar) until cleared by X-ray/MRI.
  • Acute limb ischemia or compartment syndrome? Escalate to the surgical team immediately to save the limb from amputation.
  • Maintain stringent infection-prevention precautions when handling open wounds, external fixator pins, or invasive devices.
  • Always formally reassess the patient after administering pain interventions to document therapeutic changes.

7. Documentation & OSCE Sequence

7.1 Documentation Standards

Document objectively, completely, and specifically avoiding vague terms. Record:

  • Exact joint or site examined (Left vs Right).
  • Visual inspection findings (erythema, deformity, scars).
  • Palpation findings: pinpoint location of tenderness, presence of swelling, or temperature changes.
  • Measurements of Active and Passive ROM (in degrees if possible).
  • Muscle power documented precisely using the MRC 0-5 grade.
  • Detailed description of Gait and functional ability.
  • Strict neurovascular findings (pulses, sensation, capillary refill).
📝 Excellent Documentation Example:
"Right knee visually swollen, warm to touch, and acutely tender precisely over the medial joint line. Active flexion severely limited to 60° by pain; extension lacks 10°. Patellar tap test is positive for moderate effusion. McMurray's test positive for medial click. Distal sensation intact to light touch. Dorsalis pedis and posterior tibial pulses strong and equal bilaterally. Capillary refill < 2 secs."

7.2 Practical OSCE Sequence (11 Steps to Pass)

If tested in a clinical skills exam, follow this exact fluid sequence without deviation:

  1. Introduce yourself professionally and firmly confirm the patient's identity.
  2. Explain the musculoskeletal procedure plainly and obtain explicit verbal consent.
  3. Perform visible hand hygiene and ensure appropriate exposure of the joint (maintaining dignity).
  4. General inspection of the patient from the end of the bed.
  5. Assess overall posture and observe their gait as they walk.
  6. Inspect closely and systematically palpate the affected area (feeling for temperature, swelling, joint lines).
  7. Assess Active ROM, followed by Passive ROM.
  8. Assess specific muscle power against resistance (using MRC grading).
  9. Perform the relevant special tests (e.g., Anterior Drawer, Phalen's) based on the joint.
  10. Complete a rapid neurovascular and functional assessment.
  11. Thank the patient, ensure they are dressed and comfortable, wash your hands again, and systematically document your findings.

Summary

A complete musculoskeletal examination MUST be systematic:
HISTORY ➔ INSPECTION ➔ PALPATION ➔ MOVEMENT ➔ MUSCLE POWER ➔ SPECIAL TESTS ➔ GAIT/FUNCTION ➔ NEUROVASCULAR ASSESSMENT ➔ DOCUMENTATION
Always relentlessly compare sides and correlate your physical findings with the patient's history.

References & Further Reading:

  • Hutchison's Clinical Methods. (Latest Edition). An Integrated Approach to Clinical Practice. Elsevier.
  • Macleod's Clinical Examination. (Latest Edition). Elsevier.
  • Medical Research Council (MRC) Muscle Scale guidelines for strength assessment.
  • Etonu Archbald (PHD, PGDME, MNS, PDHSM, BNS, DCN). Lecture Notes: Physical Examination of the Musculoskeletal System & Musculoskeletal Assessment.

Quick Quiz

Musculoskeletal System Examination Quiz

Health Assessment

Privacy: Your details are used only for quiz tracking and certificates.

Musculoskeletal System Assessment Read More »

Genitourinary System Examination

Genitourinary System Examination

Physical Examination of the Genitourinary System

A systematic, respectful, evidence-informed approach to clinical assessment. Prepared for clinical teaching and skills practice, incorporating essential nursing rationale and detailed anatomical context.

1. Introduction and Learning Objectives

Learning Objectives

  • Define the scope of a genitourinary (GU) examination and explain its clinical purpose in evaluating renal, urinary, and reproductive health.
  • Prepare the patient, environment, and equipment while strictly protecting the patient's dignity, modesty, and privacy.
  • Take a focused history covering urinary, renal, and reproductive symptoms.
  • Perform a structured examination of the abdomen, flanks, external genitalia, and—when indicated and appropriately trained—the rectum or pelvis.
  • Recognize abnormal findings, document them clearly and legally, and identify urgent Red Flags requiring emergency intervention.

Scope and Principles of GU Examination

The Genitourinary (GU) system comprises two intricately linked systems: the urinary tract (kidneys, ureters, bladder, and urethra) and the reproductive organs (testes, epididymis, prostate, penis in males; vulva, vagina, uterus, ovaries in females).

  • Tailored Assessment: Choose examination components according to the patient's symptoms, age, anatomy, clinical indications, and personal preference. You do not need to examine the genitalia of a patient presenting with simple isolated flank pain unless complications are suspected.
  • Informed Consent: Explain each and every step before you do it. Obtain explicit informed consent.
  • Chaperoning: Always offer and strongly encourage a chaperone for intimate examinations, according to institutional policy. Document the chaperone's name and presence.
  • Trauma-Informed Care: Use a trauma-informed, non-judgmental approach. Be highly sensitive to the fact that many patients may have a history of sexual trauma or abuse. If the patient withdraws consent or experiences significant distress, stop the examination immediately.
  • Holistic Evaluation: A GU examination complements—but does not replace—a thorough clinical history, urinalysis, laboratory testing (renal function), and imaging (ultrasound/CT).
🌍 Ugandan Clinical Context:
In many African settings, discussing genitourinary and sexual health is highly taboo. As a nurse, you must build immense trust. Additionally, keep local endemic diseases in mind: a patient presenting with terminal haematuria (blood at the end of passing urine) in Uganda must be evaluated for Schistosomiasis (Bilharzia), especially if they reside near freshwater lakes.

2. Preparation: Environment, Equipment, and Safety

Intimate examinations provoke severe anxiety in patients. Your preparation sets the tone for a professional, safe encounter.

  1. The Environment: Provide a completely private, warm, and well-lit room. Ensure the door/curtain is securely closed. Only strictly necessary medical staff should be present.
  2. Communication & Consent: Introduce yourself clearly, confirm the patient's identity, explain the purpose and exact sequence of the exam, and obtain verbal consent before any physical contact.
  3. Chaperone: Offer a chaperone (preferably of the same gender as the patient). You must legally document the offer, and whether the patient accepted or declined it.
  4. Standard Precautions: Perform rigorous hand hygiene. Wear non-sterile gloves and other Personal Protective Equipment (PPE) as indicated (e.g., aprons).
  5. Gather Equipment: Ensure you have drapes/gowns, a good light source (goose-neck lamp), a stethoscope, and a measuring tape if needed. For intimate exams, prepare appropriate swabs, lubricating jelly, and a speculum only when clinically indicated and if you are trained to use them.
  6. Patient Comfort: Ask about current pain, mobility issues, allergies (especially to latex gloves or lubricants), and recent surgical procedures. Crucial step: Ask whether the patient needs to empty their bladder before the abdominal exam (a full bladder is incredibly uncomfortable to palpate and can mimic a pelvic mass).

3. Focused Genitourinary History

A. Urinary and Renal Symptoms

A comprehensive history often reveals the diagnosis before you even touch the patient. Use the SOCRATES acronym for pain and explore the following:

Symptom CategorySpecifics to Ask & Clinical Medical Terms
PainOnset, site, severity, and radiation (e.g., classic renal colic pain radiates from the flank/loin down to the groin/testicles). Aggravating or relieving factors.
Voiding (Storage) SymptomsFrequency: Needing to pass urine often.
Urgency: Sudden, compelling need to pass urine.
Nocturia: Waking up multiple times at night to urinate.
Dysuria: Pain or a burning sensation when passing urine (classic UTI sign).
Voiding (Emptying) SymptomsHesitancy: Difficulty starting the urine stream.
Weak stream: Poor flow force.
Intermittency: Flow stops and starts.
Incomplete emptying: Feeling like the bladder is still full. (These are classic signs of Benign Prostatic Hyperplasia - BPH in older men).
Urine ChangesHaematuria: Visible (macroscopic) blood in urine.
Cloudiness or unusual foul odour (infection).
Reduced output (Oliguria: <400ml/day; Anuria: <100ml/day).
Frothiness (indicates heavy proteinuria/nephrotic syndrome).
Incontinence: Unintentional leaking of urine (stress, urge, or overflow).
Associated Systemic SymptomsFever, chills/rigors, nausea/vomiting, severe flank pain, peripheral oedema (swelling of legs/face), severe fatigue, or acute confusion (especially in the elderly with UTIs).
Past Medical HistoryPrevious UTIs, kidney stones, chronic kidney disease (CKD), diabetes, hypertension (major causes of renal failure), recent catheterization, surgery, and a full medication review.

Also ask about: Daily fluid intake, the possibility of pregnancy (when relevant), sexual health, and STI exposure. Handle STI questions sensitively and in strict privacy.

B. Reproductive and Sexual Health History

  • Clarify the concern: Use the patient's own words. Ask permission before diving into sensitive sexual health questions.
  • General genital symptoms: Ask about genital pain, swelling, sores/ulcers, abnormal discharge, intense itching (pruritus), lumps, bleeding, or changes in sexual function.
  • For patients with testes (Male): Enquire about scrotal pain or swelling, history of trauma to the groin, testicular lumps (cancer risk), and abnormal urinary/urethral discharge (STI risk).
  • For patients with a vulva/vagina (Female): Enquire about deep pelvic pain, abnormal vaginal discharge (colour, smell, consistency), vulval symptoms, menstrual history (LMP - Last Menstrual Period, regularity), and abnormal/post-coital bleeding.
  • Sexual History: Ask about sexual practices and partners only as clinically relevant. Use inclusive, non-assumptive language (e.g., "Do you have sex with men, women, or both?").
  • Wider context: Explore prior pregnancies (gravidity/parity), current contraception, menopause status, fertility concerns, past STI history, and importantly, safeguarding needs (signs of intimate partner violence or sexual assault) when appropriate.

4. General Assessment and Vital Signs

Before examining the specific system, step back and perform a general "end-of-bed" inspection.

  1. General Appearance: Assess comfort level, hydration status (dry mucous membranes, sunken eyes), marked pallor (anaemia from chronic kidney disease), signs of fever, distress, and their level of consciousness.
  2. Vital Signs: Measure temperature (fever = infection/pyelonephritis), pulse (tachycardia = pain or sepsis), respiratory rate, blood pressure (hypertension is deeply linked to renal disease), and oxygen saturation when indicated.
  3. Fluid Status & Oedema: Look for peripheral oedema (pitting swelling in the ankles/sacrum) or facial/periorbital oedema (classic in nephrotic syndrome and renal failure). Assess for systemic illness.
  4. Weight and Growth: Assess weight and growth trajectories in children when relevant. Consider blood pressure and strict fluid balance monitoring in patients with known renal disease.
  5. Mobility and Posture: Observe how the patient moves.
    • Colicky pain: A patient with a kidney stone (renal colic) cannot sit still and constantly writhes in agony.
    • Peritonitic pain: A patient with localized peritonitis lies absolutely still, as any movement hurts.
    • Scrotal pathology: May walk with a wide-based, waddling gait to avoid friction.
  6. Urine Output: Record exact urine output when clinically necessary, especially in acutely unwell or hospitalized patients (using a fluid balance chart or urinary catheter bag).

5. Abdominal, Flank, and Kidney Examination

A. Abdominal Examination

  • Positioning: Position the patient supine (lying flat on their back) with arms by their sides and knees slightly flexed to relax the abdominal muscles. Expose only the abdomen (from the xiphisternum to the symphysis pubis) and maintain draping over the chest and legs.
  • Inspection: Look for distension (a hugely swollen bladder can reach the umbilicus), surgical scars (e.g., previous nephrectomy, C-section, appendicectomy), visible masses, hernias (inguinal/umbilical), or abnormal skin changes.
  • Auscultation: While not usually central to a GU assessment, it may be included in a full abdominal exam. You may listen for renal artery bruits (a whooshing sound) just above and lateral to the umbilicus, indicating renal artery stenosis.
  • Palpation: Palpate gently, starting away from the area of reported pain. Feel for tenderness, involuntary guarding (muscle rigidity), abdominal masses, and specifically a distended, firm, globular bladder arising from the pelvis.
  • Percussion: Percuss the suprapubic area. A full, distended bladder will sound dull to percussion. Interpret these physical findings alongside the patient's symptoms and use a bedside bladder ultrasound scanner if available.
  • Documentation: Accurately document the site, severity of tenderness, presence of any masses, guarding, and whether the bladder was palpable.

B. Kidneys and Flank Assessment

  • Inspection: Ask the patient to sit up. Inspect the flanks and lower back for severe bruising (e.g., Grey Turner's sign indicating retroperitoneal haemorrhage), surgical scars, swelling, or obvious asymmetry.
  • Palpation (Ballotting the Kidneys): Attempted by trained clinicians. Place one hand behind the patient's flank (in the renal angle) and the other hand anteriorly on the abdomen. Push your hands together. Normal kidneys are often not palpable in healthy adults, though the lower pole of the right kidney may occasionally be felt in thin individuals. Enlarged kidneys (e.g., polycystic kidney disease, tumours) will be distinctly palpable.
  • Costovertebral Angle (CVA) Tenderness: Assess for CVA tenderness (also known as Murphy's punch sign). Place the palm of your non-dominant hand flat over the angle between the 12th rib and the spine. Strike the back of your hand gently with the ulnar border of your other fist.
🚑 Clinical Alert: CVA Tenderness
Significant CVA tenderness strongly suggests acute pyelonephritis (kidney infection) or renal calculi (stones). However, it is not purely diagnostic on its own. Avoid forceful percussion, particularly if trauma, rib fractures, or severe pain is already suspected. Always correlate CVA tenderness with fever, urinary symptoms, urinalysis, renal function tests, and imaging.

6. External Genital Examination

A. General Approach to Intimate Exams

  1. Strict Indication: Perform only when explicitly indicated by symptoms or clinical need, with explicit consent and a chaperone offered.
  2. Communication: Explain the examination step-by-step. Ask the patient to report any pain immediately and assure them they hold the power to pause or stop the exam at any second.
  3. Inspection: Inspect systematically for skin changes, lesions, ulcers (e.g., syphilis chancre, herpes blisters), swelling, unusual discharge, trauma, scars, or masses.
  4. Infection Control: Wear non-sterile gloves and employ appropriate infection-prevention measures. Avoid unnecessary or prolonged contact and exposure.
  5. Palpation: Should be exceptionally gentle, highly targeted, and clinically justified. Explain what you are about to feel before every single manoeuvre.
  6. Limitations: If the clinical findings are outside your competence level, if the patient declines at any point, or if the pain is severe, stop the examination immediately and arrange for an appropriate specialist review.

B. Examination of the Penis and Urethral Opening

  • Inspection of Shaft and Glans: Inspect the penile shaft, glans penis, and surrounding groin skin for lesions, rashes, sexually transmitted ulcers, swelling, bruising, or anatomical deformity (e.g., Peyronie's disease).
  • Meatus: Inspect the urethral meatus (opening). Note its position (hypospadias if on the underside, epispadias if on top), look for acute inflammation, purulent/watery discharge, or visible blood at the meatus.
  • Foreskin Management: If the patient is uncircumcised, ask them to retract the foreskin, or retract it yourself very gently only if it moves easily. CRITICAL RULE: Always return the foreskin to its normal forward position immediately afterward!
  • History Correlate: Concurrently ask about pain, dysuria, discharge, sores, erectile concerns, or recent pelvic/groin trauma.
  • Specimens: Collect urethral swabs or first-catch urine samples only when indicated for STI screening, according to local laboratory protocols.
🚨 Red Flag: Paraphimosis vs. Phimosis
Phimosis: Inability to retract a tight foreskin over the glans. Do NOT force it, as it will tear and scar.
Paraphimosis: A deeply retracted, tight foreskin becomes trapped behind the glans and cannot be pulled forward. It acts like a tight tourniquet, cutting off venous return. The glans swells massively and becomes painful and necrotic. This requires urgent emergency medical care.

C. Examination of the Scrotum and Testes

  • Inspection: Ask the patient to stand if possible. Inspect the scrotal sac for asymmetry, massive swelling (hydrocele, hernia), erythema (redness/cellulitis), skin lesions, surgical scars, and abnormal testicular position.
  • Palpation: Using warm hands, palpate each testis gently between your thumb and first two fingers. Note the size, consistency (should be firm and smooth), tenderness, and any discrete hard lumps. Palpate the epididymis (soft, nodular structure on the posterior aspect) and trace the spermatic cord up toward the inguinal canal.
  • Lumps: A new, painless, hard, irregular intratesticular lump is highly suspicious for testicular cancer and requires prompt urgent ultrasound assessment.
  • Documentation: Clearly document laterality (left/right), onset of pain, nature of swelling, precise location of tenderness, and any associated systemic symptoms.

D. Examination of the Vulva and Perineum

  • Preparation: Explain the steps and obtain consent. Position the patient comfortably on the examination couch (often in a modified lithotomy or "frog-leg" position) with adequate draping to cover the upper body and thighs. Ensure a chaperone is present.
  • Inspection: Under good lighting, inspect the external genitalia (labia majora, labia minora, clitoris) for skin changes, ulcers, warty lesions, swelling, abnormal discharge, fresh bleeding, or traumatic injury.
  • Urethra and Vagina: Note the urethral opening and vaginal introitus (opening) only as needed to address the patient's presenting clinical concern.
  • Perineum: Assess the perineal skin between the vagina and anus for unhealed episiotomy wounds, scars, signs of pelvic organ prolapse (e.g., cystocele, rectocele visible on straining), or signs of spreading infection.
  • Scope of Practice: Avoid conducting an internal (bimanual pelvic) examination unless explicitly indicated, fully consented to, and performed by a suitably trained and credentialed clinician (e.g., a doctor or specialized midwife).
  • Urgent Pathways: If there is severe acute pelvic pain, heavy uncontrollable bleeding, pregnancy-related complications (e.g., suspected ectopic), or suspected sexual abuse, stop the exam and follow urgent local referral pathways.

7. When Pelvic, Rectal, or Prostate Examination May Be Indicated

These are highly targeted, advanced clinical examinations—they are not routine steps for every general GU assessment.

  • Pelvic/Speculum Examination: May be indicated for selected cases of abnormal vaginal bleeding, taking high vaginal swabs for persistent discharge, investigating deep pelvic pain, performing cervical cancer screening (Pap smear), or assessing suspected pelvic organ prolapse.
  • Digital Rectal Examination (DRE): May be considered for specific anorectal complaints, checking anal sphincter tone in neurological disease (cauda equina), or prostate-related indications.
  • Prostate Assessment: A DRE to feel the posterior surface of the prostate gland requires a detailed explanation, written or clear verbal consent, appropriate chaperoning, and a highly trained examiner. Follow local clinical protocols.
  • Clinical Reasoning: Always consider absolute and relative contraindications, patient comfort, trauma history, and whether a less invasive test (like an ultrasound or urine test) can sufficiently answer the clinical question first.
  • Golden Rule: Refer to a specialist or seek senior supervision when the procedure is outside your legal scope of nursing practice. Never perform any intimate examination without clear, ongoing consent.

8. Common Abnormal Findings and Their Interpretation

Connecting what you find on physical examination to potential underlying pathology is key to clinical reasoning.

Clinical FindingPossible Clinical Significance / Interpretation
Suprapubic fullness / tendernessMay heavily suggest acute urinary retention (distended bladder), severe cystitis (bladder infection), or another space-occupying pelvic condition (like a large fibroid or ovarian cyst).
Flank / CVA tenderness WITH feverRaises high concern for an upper urinary tract infection (Acute Pyelonephritis). Always assess the patient rapidly for signs of systemic sepsis.
Haematuria (Visible Blood)Can arise from severe infection, kidney/bladder stones, blunt trauma, urological malignancy (bladder/renal cancer), Schistosomiasis, or underlying renal disease. Needs comprehensive evaluation.
Urethral or genital discharge / ulcersStrongly consider infection, primarily Sexually Transmitted Infections (STIs) such as Gonorrhoea, Chlamydia, Syphilis, or Herpes. Test according to national public health guidance.
Scrotal swelling or Testicular massPainless mass = High suspicion for Testicular Cancer. Acute, severe pain = Medical emergency (Torsion or Epididymo-orchitis). Requires immediate prompt assessment.
Peripheral Oedema and HypertensionOften accompany chronic renal disease (kidneys failing to excrete sodium/water). Must correlate with renal function blood tests (Creatinine) and urine protein testing.

9. Investigations That May Complement Examination

  • Urinalysis (Dipstick): The most basic, vital test. Check for blood (stones/tumours), protein (kidney damage), leukocytes and nitrites (bacterial UTI), glucose and ketones (Diabetes/DKA), and specific gravity (hydration status) as relevant.
  • Urine Microscopy, Culture, and Sensitivity (MC&S): Send to the lab when a severe or recurrent infection is suspected, or when indicated by local antimicrobial stewardship guidance, to determine exactly which antibiotics will work.
  • Blood Tests: Draw blood for Creatinine/eGFR (to measure exact kidney function), Urea, Electrolytes (Potassium is critical in renal failure), Full Blood Count (FBC for infection/anaemia), and inflammatory markers (CRP) when clinically indicated.
  • Pregnancy Testing (hCG): Perform a urine or blood pregnancy test on women of childbearing age when pregnancy is biologically possible, especially if the result critically affects your assessment (e.g., ectopic pregnancy) or management (e.g., prescribing teratogenic drugs or ordering X-rays).
  • STI Screening: Collect Nucleic Acid Amplification Tests (NAATs) via urine or specific genital swabs based on symptoms, exposure history, and patient consent.
  • Imaging: Utilize a bedside bladder scan (to measure retained urine volume), renal/pelvic ultrasound, or CT KUB (Kidneys, Ureters, Bladder) when indicated. Select imaging tests strictly according to your clinical assessment findings.

10. Red Flags: Urgent Assessment or Emergency Referral

These findings threaten life or limb. Immediate escalation is mandatory to ensure clinical safety.

  1. Sudden severe testicular pain: Strongly points to suspected testicular torsion (twisting of the spermatic cord, cutting off blood supply to the testicle). It is a time-critical surgical emergency.
  2. Acute Urinary Retention: Inability to pass any urine combined with extreme pain and severe bladder distension. Requires urgent catheterization to prevent bladder rupture or kidney damage.
  3. Urosepsis: Fever, rigors (uncontrollable shivering), flank pain, accompanied by hypotension (low BP), confusion, tachycardia, or other systemic signs of sepsis. Requires urgent IV antibiotics and fluids.
  4. Gross Haematuria with Clots: Visible blood containing thick clots, or inability to urinate due to clot blockage. Indicates significant bleeding, potential haemodynamic instability, or severe trauma/cancer.
  5. Trauma & Obstruction: Severe abdominal/flank pain immediately after trauma, a suspected obstructed infected kidney (e.g., a stone blocking a ureter with concurrent infection above it), or rapidly deteriorating renal blood function.
  6. Ectopic Pregnancy Suspicions: A patient who is pregnant (or potentially pregnant) presenting with severe unilateral pelvic pain, sudden collapse, shoulder-tip pain (diaphragmatic irritation from internal bleeding), or heavy vaginal bleeding.
  7. Cauda Equina Syndrome: A massive neuro-surgical emergency. Look for new "saddle numbness" (numbness in the buttocks/perineum where you would sit on a horse saddle), severe leg weakness, or sudden loss of bladder/bowel control. Indicates spinal cord compression.

11. Documentation, Communication, and Checklist

Clinical Practice Standards

  • Comprehensive Records: Record the precise clinical indication for the exam, the relevant focused history, that consent was obtained, the chaperone offer/outcome, and the exact examination components you performed.
  • Objective Terminology: Use completely objective, professional, and respectful language. Describe the exact anatomical site, laterality (left/right), measured size, physical appearance, degree of tenderness, and relevant negatives (e.g., "No palpable lumps, no CVA tenderness").
  • Justify Omissions: Explicitly document what was not examined and the reason why, including patient preference ("patient declined rectal exam") or clinical contraindication.
  • Next Steps: Record all investigations ordered, specimens successfully collected, the findings communicated to the patient, and the clear follow-up or referral plan.
  • Escalation (SBAR): Escalate abnormal or urgent Red Flag findings promptly to a doctor. Use a structured handover tool such as SBAR (Situation, Background, Assessment, Recommendation) for clear, rapid communication.
  • Legal & Ethical: Maintain strict medical confidentiality and rigidly follow your local institutional documentation and safeguarding reporting policies.

Practical Checklist: Systematic GU Examination

  • Hand hygiene, ensuring privacy, step-by-step explanation, obtaining consent, and offering a chaperone.
  • Taking a focused urinary, renal, reproductive, and clinically relevant sexual history.
  • Assessing general appearance, recording vital signs, and evaluating hydration/oedema status.
  • Performing abdominal inspection, palpation, and targeted suprapubic percussion.
  • Performing flank inspection and gentle CVA tenderness assessment when indicated.
  • Conducting a targeted external genital examination only when strictly indicated and consented to.
  • Considering appropriate complementary urine/blood tests, bladder scan, or imaging.
  • Documenting findings accurately, explaining the next steps to the patient, and rapidly escalating any red flags.

12. Clinical Case Discussion

The Scenario: A 24-year-old male presents with sudden, extremely severe right-sided testicular pain and nausea that began exactly one hour ago.

  1. What focused history questions would you ask?
    • What exactly was he doing when the pain started? (e.g., exercising, sleeping, recent trauma).
    • Has he ever had this exact pain before? (Previous intermittent torsion).
    • Does he have any dysuria, frequency, or urethral discharge? (To rule out epididymo-orchitis).
    • Any associated fever? (Points more toward infection than torsion).
  2. Which examination findings might support testicular torsion?
    • A swollen, exquisitely tender, unilaterally enlarged testicle.
    • A high-riding testis (pulled up higher in the scrotum than normal due to the twisted cord shortening).
    • Loss of the normal cremasteric reflex on that side.
    • The epididymis may be palpable in an abnormal, anterior position.
  3. What is the immediate priority, and should investigations delay referral?
    • Immediate Priority: The absolute priority is recognizing this as a time-critical surgical emergency. The testis will die from ischemia (lack of blood flow) within 4 to 6 hours.
    • Should investigations delay referral? NO. Do not wait for urine tests, blood tests, or a scrotal ultrasound if torsion is strongly suspected clinically. Immediate emergency surgical/urological assessment and exploration is required to untwist the cord and save the testicle.

13. Selected References and Learning Resources

  • Hutchison, R. & Glynn, M. Hutchison's Clinical Methods: An Integrated Approach to Clinical Practice. Elsevier. (A core foundation text for systematic clinical examination methodologies).
  • Bickley, L. S. Bates’ Guide to Physical Examination and History Taking. Wolters Kluwer. Use the latest available edition.
  • National Institute for Health and Care Excellence (NICE). Guidance on urinary tract infection, acute kidney injury and suspected cancer. https://www.nice.org.uk/
  • European Association of Urology (EAU). Guidelines on urological infections and acute scrotum/testicular cancer. https://uroweb.org/guidelines
  • Centers for Disease Control and Prevention (CDC). Sexually Transmitted Infections Treatment Guidelines. https://www.cdc.gov/sti/hcp/treatment-guidelines/
  • Note: Local hospital policies, Ugandan Ministry of Health clinical guidelines, and institutional protocols should ultimately guide examination, investigations, chaperoning, and referral pathways.

Quick Quiz

Genitourinary Examination Quiz

Health Assessment

Privacy: Your details are used only for quiz tracking and certificates.

Genitourinary System Examination Read More »

Intergumentary

Intergumentary System Examination

Physical Examination of the Integumentary System

A practical, systematic, and highly detailed guide for nursing students encompassing Health Assessment, Inspection, Palpation, and Clinical Documentation.

1. Learning Outcomes & Introduction

Learning Outcomes

  • Define the integumentary system and powerfully explain its holistic assessment in daily nursing practice.
  • Prepare the patient, environment, and equipment meticulously for a comprehensive examination.
  • Perform a systematic, head-to-toe skin, hair, nail, and pressure-area assessment.
  • Recognize common normal findings and rapidly identify crucial, life-threatening abnormal signs.
  • Document findings clearly, protect patient dignity, and decisively identify exactly when to escalate care.
💡 Clinical Focus:
Always compare your current findings with the patient’s baseline, comprehensive medical history, chronological age, natural skin tone, and current clinical condition. The skin is a window to systemic health!

What is the Integumentary System?

The integumentary system is the largest organ system in the body. It goes far beyond just what we see on the surface. It comprises:

  • Skin Layers:
    • Epidermis: The thin, tough, avascular outer layer. It contains melanocytes (providing skin colour) and keratin (for tough protection).
    • Dermis: The highly vascular, supportive inner layer made of connective tissue (collagen). It houses nerves, sensory receptors, blood vessels, and lymphatics.
    • Subcutaneous Tissue (Hypodermis): The adipose (fat) layer beneath the dermis that provides insulation, energy storage, and a cushioning effect.
  • Appendages: Hair (follicles rooted in the dermis), nails, sweat glands (eccrine and apocrine), and sebaceous (oil) glands.
  • Core Functions: Protection from trauma and microbes, temperature regulation, intense sensory perception (pain, touch, temperature), immune defence, excretion of metabolic wastes, and Vitamin D synthesis.

Systemic Clues: The skin frequently reveals systemic illness. A thorough examination can expose dangerous hydration problems, poor cardiovascular perfusion, overwhelming systemic infection (sepsis), severe allergic reactions (anaphylaxis), liver failure, or chronic nutritional deficiency.

Examine the whole person—not only the visible rash or wound!

2. Preparation, Equipment & Focused History

Preparation and Equipment

  1. Explain and Consent: Explain the examination step-by-step, obtain informed verbal consent, and always ask about current pain or highly sensitive areas before touching the patient.
  2. Environment: Ensure strict privacy (close curtains/doors), brilliant lighting (natural daylight is best for assessing true skin colour), comfortable room temperature, and appropriate draping to avoid exposing the patient unnecessarily.
  3. Hand Hygiene & Safety: Perform rigorous hand hygiene. Use gloves when contact with body fluids, broken skin, mucosa, or undiagnosed open lesions is anticipated. Do not touch infectious lesions unnecessarily or share uncleaned equipment.
  4. Equipment Required:
    • Good examination light / penlight (for tangential lighting to view contours).
    • Clean non-sterile gloves.
    • A flexible, clear ruler or measuring tape (for exact wound/lesion dimensions).
    • Skin marker (if clinically needed to track spreading redness/cellulitis).
    • Documentation chart and specific wound-measurement tools.
  5. Allergies: Crucially ask about allergies to adhesives (plasters/dressings) or latex before using any medical products on their skin.
  6. Positioning: Position safely; inspect areas systematically while preserving the patient's warmth and dignity throughout.

Focused History Before Examination

Before you touch the patient, you must gather the narrative. The history guides your physical assessment.

History ComponentDetailed Clinical Inquiry & Examples
Current ConcernRash, severe itching (pruritus), sharp or dull pain, extreme dryness (xerosis), easy bruising, chronic non-healing wound, sudden hair loss (alopecia), or bizarre nail changes.
ChronologyOnset (when did it exactly start?), duration, progression (is it spreading?), recurrence, triggers (foods/stress/heat), and treatments already tried at home.
Associated SymptomsFever, severe malaise/lethargy, localized swelling, purulent drainage, spontaneous bleeding, or altered sensation (numbness/tingling).
Medical HistoryDiabetes mellitus (huge risk for foot ulcers), vascular/peripheral artery disease, immune suppression (HIV, chemotherapy), allergies, and known skin disorders (psoriasis, eczema).
Medication HistoryNew medicines (antibiotics commonly cause rashes), topical steroid creams, over-the-counter supplements, and recent medication dose changes.
Exposure & ContextExcessive sunlight/UV exposure, hazardous chemicals, occupational risks (farming/construction), recent foreign travel, exposure to infected contacts, prolonged pressure/bedrest, excessive moisture (incontinence), and limited mobility.
Family & Personal HistoryPersonal and family history of skin cancer (Melanoma); lifetime sunburn and tanning bed history where relevant.

3. Systematic Examination: IPPA Adapted for Skin

Unlike examining the lungs or heart, the integumentary examination relies almost entirely on Inspection and Palpation. Percussion and Auscultation are generally not routinely used for the skin.

  • Inspect First: Colour, overall distribution, surface texture, individual lesions, hair distribution, nails, and bilateral symmetry. Look everywhere, including hidden skin folds.
  • Palpate Gently: Assess skin temperature, moisture/diaphoresis, texture, dermal thickness, tenderness, mobility, and skin turgor where appropriate.
  • Assess Lesions: Evaluate deeply by location, morphology (type), size, shape, colour, border irregularity, and overall body distribution (localized vs. generalized).
  • Measure Wounds: Document precise location, then use the strict formula: Length × Width × Depth when clinically appropriate. Use a reliable ruler; avoid "guessing" or "estimating" dimensions when precise measurement matters for healing tracking.
  • Sequence: Use a consistent head-to-toe sequence and always compare the left side with the right side to identify unilateral abnormalities.

4. Inspecting Skin Colour, Perfusion, and Surface

Colour and Perfusion Analysis

Observe overall pigmentation and any new or localized colour change. Clinical presentation varies drastically between light and dark skin tones.

Clinical SignPathophysiology / MeaningAppearance in Darker Skin Tones
Pallor (Paleness)Reduced oxygenated haemoglobin or decreased blood flow (Anaemia, shock, arterial insufficiency).Loss of underlying red tones. Brown skin appears yellow-brown; black skin appears ashen or grey. Best assessed in conjunctivae or mucous membranes.
Cyanosis (Blue)Severe hypoxia, decreased oxygen saturation in the blood (Heart failure, severe asthma/COPD, cold exposure).Skin may appear dark, dull, or lifeless. Best assessed in the oral mucosa, conjunctivae, lips, and nail beds.
Erythema (Redness)Intense vasodilation, local inflammation, fever, or early pressure injury.May appear purple, dark grey, dusky, or simply as a deepening of the usual skin tone. Palpate for increased warmth to confirm inflammation.
Jaundice (Yellowing)Rising serum bilirubin levels due to liver failure, hepatitis, or massive red blood cell destruction (haemolysis).Yellowing is most reliably assessed in the sclera (white of the eyes), the hard palate of the mouth, and the palms/soles.
MottlingPatchy, irregular skin colour caused by severe vasoconstriction and poor systemic perfusion (often seen in end-of-life or severe septic shock).Presents as a dark, irregular, lace-like network, often starting at the knees and moving upwards.
HyperpigmentationExcess melanin production (e.g., Addison's disease, chronic sun exposure, or post-inflammatory changes).Areas become significantly darker than the patient's baseline skin tone.
  • Capillary Refill: Assess capillary refill (normally < 2-3 seconds) in context, alongside skin temperature, peripheral pulses, sensation, and overall systemic perfusion.
  • Clinical Caution: Do not rely on skin colour alone to diagnose anaemia, hypoxia, or jaundice. Poor lighting and natural rich pigmentation can obscure colour changes; rely on multiple assessment cues (like vital signs and palpation).

Inspecting Skin Surface and Texture

  • Integrity & Texture: Note whether the skin is perfectly intact, smooth, rough, excessively dry, oily, scaly, cracked, or macerated (soft and white from prolonged moisture exposure).
  • Moisture & Odour: Observe normal moisture, profound sweating (diaphoresis), unusual foul odour (suggesting anaerobic bacterial infection), and any discharge.
  • Markings: Look actively for surgical scars, striae (stretch marks, notable in Cushing's syndrome or pregnancy), tattoos, natural birthmarks, excoriations (scratch marks), and areas of pathological thickening.
  • Edema (Swelling): Check for interstitial fluid accumulation and compare bilateral sides.
    • Pitting Edema: Leaves a visible indentation when pressed firmly for 5 seconds (graded 1+ to 4+ based on depth and rebound time). Seen in heart failure and kidney failure.
    • Non-Pitting Edema: Skin feels hard and tight; no indentation remains (e.g., severe lymphedema).

5. Understanding Skin Lesions

Describe what you see objectively using precise medical terminology, rather than jumping to an unsupported clinical diagnosis.

Primary Skin Lesions (Develop on previously unaltered skin)

Lesion TypeDefinition & CharacteristicsClassic Clinical Examples
Macule / PatchFlat, non-palpable colour change. Macule: < 1 cm. Patch: > 1 cm.Freckles, flat moles (nevi), petechiae, measles, vitiligo (patch).
Papule / PlaqueRaised, solid, palpable lesion. Papule: < 1 cm. Plaque: > 1 cm (broader or plateau-like).Elevated moles, warts (papules); Psoriasis, eczema (plaques).
Nodule / TumourSolid, elevated, deeper into the dermis. Nodule: 1-2 cm. Tumour: > 2 cm.Lipomas, large fibromas, enlarged lymph nodes, carcinomas.
Vesicle / BullaElevated cavity containing clear, free fluid (blister). Vesicle: < 1 cm. Bulla: > 1 cm.Herpes simplex, early chickenpox (vesicles); Severe burns, contact dermatitis (bullae).
PustuleElevated lesion filled with turbid purulent fluid (pus).Severe acne, impetigo, staphylococcal infections.
WhealTransient, superficial, raised, erythematous swelling caused by dermal edema.Mosquito bites, allergic urticaria (hives), severe allergic reactions.
CystEncapsulated fluid-filled or semi-solid mass in the deep dermis or subcutaneous layer.Sebaceous cyst, ganglion cyst.

Secondary Lesions (Change over time due to disease progression, scratching, or infection)

  • Scale: Compact, desiccated flakes of skin, dry or greasy, from shedding dead excess keratin cells (e.g., dandruff, psoriasis).
  • Crust: Thickened, dried-out exudate (serum, blood, or pus) left when vesicles or pustules burst and dry up (e.g., the honey-coloured crust of Impetigo).
  • Erosion: Superficial loss of the epidermis; scooped out but shallow. Moist but bleeds minimally; heals without a deep scar.
  • Ulcer: Deeper tissue loss extending into the dermis or subcutaneous fat. Irregular shape, may bleed heavily, and leaves a permanent scar (e.g., pressure ulcers, venous stasis ulcers).
  • Fissure: Linear crack with abrupt edges extending into the dermis; can be dry or moist (e.g., severe athlete's foot, cracks at the corners of the mouth).
  • Excoriation: Self-inflicted abrasion; superficial scratch-related injury (e.g., intense scratching from scabies or insect bites).
  • Lichenification: Tightly packed set of papules causing profoundly thickened skin with accentuated markings from prolonged, chronic intense rubbing/scratching.
  • Atrophy: Thinning of the skin surface with loss of normal skin markings; skin looks paper-thin, translucent, and fragile (e.g., aging skin, long-term topical steroid use).
  • Scar (Cicatrix): Normal tissue is replaced with fibrous connective tissue following an injury, closing a wound. (Keloids are hypertrophic, elevated scars growing beyond original wound boundaries).
⚠️ Note Signs of Infection:
When assessing any lesion or breakdown, immediately escalate if you see: rapidly increasing redness or discolouration, intense radiating warmth, massive swelling, severe unremitting pain, foul-smelling pus/odour, or systemic symptoms like fever and chills.

Assessing a Lesion: The ABCDE Warning Signs for Melanoma

Arrange prompt clinical/dermatological review for suspicious or rapidly changing pigmented lesions. The ABCDE criteria is a powerful screening aid for skin cancer, not a definitive diagnosis.

  • A — Asymmetry: The two halves of the lesion look completely different; they do not match.
  • B — Border: Irregular, notched, scalloped, or poorly defined, blurred edges.
  • C — Colour: Varied or changing colours within one single lesion (shades of brown, tan, black, and sometimes red, blue, or white).
  • D — Diameter: Larger lesions may be highly concerning (usually > 6 mm, the size of a pencil eraser), but note that dangerous melanomas can sometimes be smaller than 6 mm when first discovered.
  • E — Evolving: A critical red flag. Any recent change in size, shape, colour, elevation, or new symptoms (such as spontaneous bleeding, intense itching, or crusting).

The "Ugly Duckling" Sign: Also note any new or unusual lesion that looks entirely different from the person’s other surrounding lesions.

6. Palpation: Temperature, Moisture, and Turgor

  1. Temperature: Use the backs (dorsa) of your fingers to assess and compare skin temperature at corresponding bilateral sites. The skin should be uniformly warm, indicating normal circulatory perfusion. (Palpate gently for intense localized warmth [inflammation/infection] or extreme coolness [shock/arterial block]).
  2. Moisture & Texture: Assess with your fingertips. Note excessive, flaking dryness (dehydration/hypothyroidism), profound sweating (diaphoresis from fever/pain/heart attack), or an unnatural clamminess.
  3. Thickness, Tenderness & Mobility: The skin should move easily. Note any induration (hardened, thickened areas), severe tenderness upon palpation, fluctuance (a wave-like feeling indicating a fluid/pus pocket underneath), or crepitus (crackling feeling under the skin, indicating dangerous subcutaneous emphysema/trapped air).
  4. Turgor & Elasticity:
    • Skin turgor reflects hydration and elasticity. Gently pinch a large fold of skin (typically on the anterior chest under the clavicle, or the forearm). It should snap back immediately.
    • A delayed return ("tenting") after pinching may suggest severe clinical dehydration or massively reduced elasticity.
    • Older Adults: In the elderly, always assess turgor over the sternum/clavicle rather than relying on the back of the hand, because natural aging drastically destroys hand skin elasticity, leading to false-positive "tenting".
Avoid Over-Interpretation:
Skin turgor can be heavily affected by extreme age, anatomical site, chronic sun damage, and chronic wasting illnesses. No single skin sign reliably establishes hydration status on its own. You MUST combine turgor findings with precise intake/output charts, mucous membrane moisture, vital signs (blood pressure, heart rate), and overall clinical history.

7. Appendages: Hair, Scalp, and Nail Examination

Hair and Scalp Examination

  • Inspect: Hair distribution, density, texture, natural shine, breakage, and specific patterns of hair loss.
  • Scalp Assessment: Part the hair in several different places to meticulously inspect the underlying scalp for dense scales (dandruff/psoriasis), hidden lesions, biting parasites (head lice/pediculosis), extreme inflammation, or scarring.
  • History Integration: Ask about intense itching, extreme tenderness, recent severe illness, major life stress, extreme diets, harsh chemical hair practices, and new shampoos/products.
  • Hair Loss (Alopecia): Carefully distinguish diffuse shedding (thinning all over, often from systemic illness or stress) from patchy, localized loss (like alopecia areata or fungal tinea capitis). Document exact location and pattern.
  • Body Hair: Inspect eyebrows, eyelashes, and general body hair when relevant to the history (e.g., absent leg hair indicates severe peripheral artery disease; excessive facial hair in women [hirsutism] indicates hormonal imbalance).
  • Cultural Respect: Use culturally respectful, sensitive language and completely avoid making prejudiced assumptions about a patient's personal hair-care practices or styling choices.

Nail Examination

Nail findings are profound clues to systemic illness, not just stand-alone diagnostic tests. Consider physical trauma, specific occupations, harsh nail cosmetic products, and underlying chronic diseases before interpreting changes.

  • Inspect: Nail colour, overall shape, structural thickness, natural curvature, surface smoothness, cleanliness, and the integrity of surrounding skin (cuticles).
  • Nail Folds: Inspect thoroughly for aggressive redness, swelling, exquisite tenderness, or purulent drainage (Paronychia).
  • Specific Pathological Signs to check for:
    • Clubbing: The nail bed angle becomes greater than 180 degrees, and the nail base feels spongy. A massive sign of chronic, long-term systemic hypoxia (e.g., severe COPD, lung cancer, congenital heart defects).
    • Spoon-shaped nails (Koilonychia): Concave, thin, and dipping nails. A classic sign of severe chronic iron-deficiency anaemia.
    • Pitting: Tiny, deep "ice-pick" holes in the nail plate. Strongly associated with Psoriasis.
    • Ridges & Splitting: Transverse grooves (Beau's lines) indicate a severe past systemic illness that temporarily halted nail growth. Vertical splitting can occur with aging or severe malnutrition.
    • Onycholysis: Painless separation of the nail plate from the underlying nail bed, starting at the tip.
    • Splinter Haemorrhages: Tiny red/brown linear blood streaks. Highly suspicious for Infective Endocarditis or severe localized trauma.
  • Capillary Refill: Assess when clinically indicated, ensuring adequate room warmth and appropriate pressure technique to test cardiovascular perfusion.

8. Pressure Injury Risk and Wound Documentation

Pressure Injury Risk and Bony Prominences

A pressure injury (bedsore/decubitus ulcer) is localized damage to the skin and underlying tissue, usually over a bony prominence, resulting from prolonged pressure or pressure combined with shear.

  1. Key Risk Areas to Inspect: The Sacrum/coccyx (most common), heels, hips (trochanters), ankles (malleoli), elbows, occiput (back of head, especially in children/infants), and other pressure points determined by the patient's specific resting position.
  2. Intact Skin Assessment (Stage 1 Warning): Assess intact skin for a persistent, non-blanching colour change (erythema that does not turn white when pressed), significant temperature differences (warmer or cooler), firmness/boggy feel, swelling, or localized pain.
  3. Assessment in Darker Skin Tones: Non-blanching erythema may be totally invisible in dark skin. You MUST heavily rely on comparing the area with surrounding healthy skin and assessing for localized warmth, unusual tissue firmness (induration), and patient-reported tenderness.
  4. Holistic Review: Always review the patient's independent mobility, sensory perception (can they feel pain?), nutritional status (protein is vital for skin integrity), excessive moisture/incontinence (maceration destroys skin), overall systemic perfusion, and tight medical devices (oxygen masks, catheters, casts).
  5. Action: Use a validated local risk tool (e.g., Braden Scale or Waterlow Score) strictly alongside your clinical judgement. A mathematical score does absolutely not replace an actual physical skin inspection!
  6. Escalation: Offload the pressure immediately (turn the patient, use specialized mattresses) and escalate any suspected pressure injury promptly to the wound care team.

Wound Assessment and Exact Documentation

  • Anatomy & Aetiology: Record the exact anatomical location, the specific wound type if known (e.g., surgical, venous ulcer, arterial ulcer, pressure injury), onset date, and the likely causative mechanism when established.
  • Measurement: Measure Length × Width × Depth (in centimetres) strictly using the facility’s standard method (e.g., clock-face method). Describe any undermining (destruction hidden under intact skin edges) or deep tunnelling if present.
  • Wound Bed & Edges: Describe the tissue inside the wound bed (red healthy granulation tissue, yellow slough, or black dead necrotic eschar), the exact condition of the wound edges, and the surrounding peri-wound skin.
  • Exudate & Odour: Document the amount and type of exudate (serous/clear, sanguineous/bloody, purulent/pus), and note any specific odour only after thoroughly cleansing the wound.
  • Pain & Infection: Record patient-reported pain scores and obvious infection signs.
  • Interventions: Document the specific dressing applied, mechanical pressure-relief measures taken, and the patient’s clinical response.
  • Objective Language: Use highly consistent measurement techniques and approved clinical photography procedures (always with explicit consent and secure digital storage). Avoid vague labels such as “clean” or “bad” without providing a detailed objective description.
🚨 ESCALATE IMMEDIATELY:
Rapidly spreading redness (streaking), disproportionate agonizing pain, sudden tissue necrosis (blackening), new systemic illness (fever, hypotension, confusion), or suspected deep space infection demands urgent, immediate medical and surgical assessment.

9. Common Findings Needing Clinical Attention & Adaptation

Red Flags for Immediate Clinical Attention

  • A rapidly changing, spontaneously bleeding, chronically non-healing, or highly suspicious pigmented lesion (violating the ABCDE rules).
  • A new, widespread generalized rash combined with high fever, facial swelling, severe breathing difficulty, or mucosal involvement (mouth/eyes) — massive red flag for Anaphylaxis or Stevens-Johnson Syndrome / Toxic Epidermal Necrolysis.
  • Signs of severe cellulitis or deep wound infection, especially when accompanied by fever, chills, or exceptionally rapid physical progression up a limb.
  • Sudden, terrifying widespread blistering, sheets of skin peeling off, or a severely painful rash developing immediately after starting a new medication.
  • Unexplained, spontaneous severe bruising or petechiae (tiny pinpoint bleeds), particularly when associated with systemic symptoms or active bleeding from gums (suspect severe thrombocytopenia or leukaemia).
  • Acute cyanosis, severe mottling with catastrophic poor perfusion, or a completely cold, pulseless, agonizingly painful limb (acute arterial occlusion).
  • A newly discovered pressure injury, deteriorating non-healing ulcer, or rapid skin breakdown in a frail, high-risk patient.

Emergency Response: Airway symptoms, severe allergic reactions, extensive full-thickness skin detachment, or any signs of systemic shock absolutely require emergency rapid-response escalation.

Adapting Assessment for Different Patients

GroupSpecific Assessment Considerations
Infants & ChildrenInspect diaper/nappy areas diligently for fungal rashes. Check deep skin folds, the scalp, and hydration cues (sunken fontanelles). Involve the parent/caregiver appropriately to calm the child.
Older AdultsConsider profoundly fragile skin, drastically reduced elasticity (loss of collagen), easy bruising (senile purpura), extreme dryness (xerosis), and a massively elevated risk for rapid pressure injuries. Handle with extreme care to prevent skin tears.
Immobility or Sensory ImpairmentMeticulously inspect entirely beneath heavy medical devices, braces, oxygen tubing, and deeply hidden areas the patient physically cannot see or feel (due to paralysis or neuropathy).
Diabetes or Vascular DiseasePay extraordinary, close attention to the feet (between the toes and on the soles), looking for hidden painless wounds, profound lack of peripheral perfusion, and complete loss of protective sensation.
Cultural & PrivacyRespect absolute privacy, deep cultural preferences, gender considerations, and always respect the patient’s fundamental right to decline parts of the exam. Use a professional interpreter when needed and explicitly explain each step before touching.

10. Practical Checklist, Documentation & Summary

A Practical Head-to-Toe Checklist

  1. Prepare: Explain, gain consent, perform hand hygiene, ensure strict privacy, and execute safe positioning.
  2. General Survey: Assess visible overall skin colour changes, obvious signs of distress, foul odours, and overt signs of systemic illness from the doorway.
  3. Head & Upper Body: Inspect and palpate head/scalp and face; move to ears and neck; thoroughly examine the trunk (chest/abdomen) and deep skin folds (under breasts, groin).
  4. Limbs & Extremities: Assess upper limbs, hands, and nails; proceed to lower limbs, feet, between toes, and strictly assess all lower pressure areas (heels/ankles).
  5. Hidden Areas: Inspect relevant hidden areas (perineum, sacrum) with explicit consent and an appropriate clinical chaperone/support present.
  6. Palpation & Measurement: Palpate selected areas for temperature/turgor and precisely measure any lesions, wounds, or rashes found.
  7. Conclude: Summarize findings verbally to the patient, address their physical comfort, safely reposition them, thoroughly document everything, and urgently report/escalate any critical abnormalities to the medical team.

Exam Technique Tip: Tell the patient exactly what you are doing before you do it, always compare both sides simultaneously, and avoid leaving the patient fully exposed (uncover only the area being examined).

Sample Documentation: Objective and Concise

  • Normal Example: "Skin warm, dry, and appropriate colour for ethnicity; intact over all examined bony prominences. No visible rash, lesions, or open wounds noted. Skin turgor prompt."
  • Lesion Example: "Left anterior forearm: 8 mm round, flat, dark brown macule, with a regular smooth border, uniform colour throughout; patient reports no change in size or shape over 5 years."
  • Wound Example: "Right heel: 2.0 × 1.5 cm area of distinct, non-blanching dark red colour change; epidermis remains fully intact; local area feels significantly warmer and firmer than adjacent surrounding tissue; patient reports mild localized tenderness upon palpation."

Documentation Rules: Always include the exact site, size, objective appearance, patient symptoms, relevant negatives (e.g., "no purulent discharge"), the specific action taken, and whom you officially notified. Use approved medical terminology and never document an assessment parameter that was not actually performed.

Clinical Case Discussion

Scenario: A 68-year-old patient with poorly controlled diabetes and reduced bed mobility is found to have a dusky, dark purple area over their sacrum.

Assessment: The area is distinctly warmer and physically firmer (indurated) than the nearby healthy skin; the patient reports dull discomfort when pressed.

  • Further assessments required: Evaluate capillary refill around the area, check for any skin breakdown/blistering, assess overall nutritional status, incontinence issues, and blood glucose levels. Determine their Braden/Waterlow score.
  • Actions & Escalation: Key point: Assess the area promptly, immediately offload all pressure by turning the patient to a 30-degree lateral tilt, follow strict local wound care protocols, document objectively, and escalate to the wound specialist. NEVER massage a suspected pressure injury (massaging destroys the fragile underlying ischemic tissue and worsens the necrosis).

Knowledge Check Review

  1. Name the three main layers of the skin. (Epidermis, Dermis, Subcutaneous/Hypodermis).
  2. What does the "E" in ABCDE stand for? (Evolving - any change in size, shape, colour, or new symptoms).
  3. Why may erythema be harder to identify in darker skin tones? (Because the natural rich melanin masks the red colour. It may appear dark grey, purple, or dusky. You must rely heavily on palpating for heat and tissue firmness/induration).
  4. List four pressure areas to inspect in a bedbound patient. (Sacrum/coccyx, heels, elbows, occiput/back of head, hips/trochanters, shoulder blades/scapulae).
  5. What information should be included when documenting a wound? (Exact anatomical location, mechanism/cause, Length x Width x Depth measurements, description of the wound bed tissue, exudate type/amount, odour, pain, infection signs, and the specific dressing applied).
  6. Give three skin findings that require urgent escalation. (Rapidly spreading cellulitis with systemic fever, an evolving bleeding ABCDE lesion, sudden widespread blistering/peeling rash [SJS/TEN], signs of deep tissue necrosis, or anaphylaxis accompanied by hives and airway distress).

11. Summary & References

Perform a highly systematic, culturally respectful, and holistic assessment of the skin, hair, nails, and pressure areas. Always inspect first, then palpate selected areas, and meticulously measure when needed. Describe lesions with clinical objectivity; avoid jumping to an unsupported diagnosis from a fleeting appearance alone. Interpret all findings in context, actively integrating skin tone, baseline status, chronological age, medical history, and specific risk factors. Document accurately, protect patient privacy relentlessly, and escalate concerning life-threatening findings promptly without delay. Follow institutional protocols and actively seek senior review when you are uncertain.

Suggested Clinical References

  • Hutchison's Clinical Methods – An internationally integrated approach to clinical skills and holistic patient examination.
  • Jarvis, Physical Examination & Health Assessment – Comprehensive guide to nursing assessment.
  • Bates’ Guide to Physical Examination and History Taking – Essential foundations for physical assessment.
  • Current local, national, and international wound care and pressure-injury prevention guidelines (e.g., NPIAP/EPUAP).

Quick Quiz

Integumentary Examination Quiz

Health Assessment

Privacy: Your details are used only for quiz tracking and certificates.

Intergumentary System Examination Read More »

Standards of Care

History of Nursing in Africa

History of Nursing in Africa

The history of nursing in Africa is a rich, complex tapestry that weaves together ancient traditional caregiving practices, the influence of early civilizations, the impact of missionary and colonial healthcare systems, and the dynamic growth of the profession in the post-independence era. Understanding this history is crucial for modern African nurses to appreciate their roots and provide culturally sensitive care.

Learning Objectives

By the end of this comprehensive lesson, the nursing student should be able to:

  • Define the history of nursing within the African context.
  • Describe traditional caregiving practices in precolonial African societies.
  • Explain the vital role of indigenous healthcare systems in the foundation of nursing.
  • Discuss the dual influence of missionary healthcare institutions on nursing development.
  • Explain the profound impact of colonialism on African nursing education, practice, and social structures.
  • Describe the rapid development of nursing after African nations gained independence.
  • Discuss the immense contributions of African nurses to contemporary healthcare delivery.
  • Explain the progression of nursing education and professional regulation across the continent.
  • Identify the historical and current challenges affecting the development of nursing in Africa.
  • Discuss the evolving role of nurses in contemporary African healthcare systems.

1. General Historical Development

1.1 Precolonial Caregiving

Africa boasts a long, rich history of traditional healthcare and caregiving that long predates European arrival. Before the introduction of modern, Western-style professional nursing (often associated with Florence Nightingale), African communities had robust, deeply rooted systems of caring for their vulnerable members.

These organized community systems specifically catered to:

  • Mothers and Newborns: Ensuring safe childbirth and postpartum recovery through specialized community women.
  • Children: Managing childhood illnesses, nutrition, and early development.
  • Older people: Providing palliative and supportive care within the extended family structure.
  • People with injuries: Managing fractures (traditional bone-setters) and treating battle or hunting wounds.
  • People with illnesses: Treating endemic diseases like malaria and digestive issues using herbal remedies and spiritual care.

1.2 Providers of Traditional Care

Care in precolonial Africa was holistic and often communal. It was primarily provided by:

  • Families: The first line of healthcare. The extended family system ensured no sick person was left unattended.
  • Traditional Birth Attendants (TBAs): Highly respected older women in the community who possessed immense practical knowledge of midwifery.
  • Herbalists: Specialists in the medicinal properties of local flora (roots, leaves, bark).
  • Traditional Healers: Practitioners who addressed both the physical and spiritual/psychological aspects of illness (holistic care).
  • Community Elders: Guardians of public health norms, sanitation rules, and dietary taboos.

Crucial Aspect: This profound medical and caregiving knowledge was largely oral. It was meticulously passed from one generation to another through apprenticeships, songs, and cultural initiations.

📝 Example: The Role of TBAs
Traditional birth attendants provided critical, continuous support to pregnant women through the entire maternity cycle: Pregnancy, Labour, Delivery, and the Postpartum period.
Nursing Implication: Although this differs from modern, scientifically regulated professional nursing, it represents the exact historical foundation of what we now call community-based care and maternal support systems.

1.3 A Diverse Tapestry of Development

Nursing in Africa did not develop in a single straight line. It evolved through the merging of:

  1. Diverse indigenous caregiving practices.
  2. Community health traditions (herbalism, bone setting).
  3. Religious and missionary healthcare institutions (bringing Western medicine paired with religion).
  4. Colonial-era health systems (often segregated and military-focused initially).
  5. Post-independence professional education and national regulation.

Important Note: African nursing history is not identical across countries. A country colonized by the British (e.g., Uganda, Kenya) has a different nursing trajectory than one colonized by the French (e.g., Senegal) or Portuguese (e.g., Mozambique). This lesson provides a broad overview of common continental themes.

2. Traditional African Healthcare Systems

2.1 Definition of Precolonial Africa

The term precolonial Africa refers broadly to African societies before the establishment of European colonial rule in particular territories. The exact period differs heavily from region to region. It is vital to recognize that African societies had highly complex political, economic, cultural, and healthcare systems long before European expansion.

2.2 Definition of Traditional Healthcare

Traditional healthcare refers to the knowledge, beliefs, practices, and resources developed internally within communities for maintaining health, preventing illness, diagnosing health problems, and treating disease. Before modern nursing schools were established, these communities successfully sustained life and managed public health using these indigenous systems.

Examples of Indigenous Caregiving:

  • Family-based nursing and emotional support (the psychological bedrock of healing).
  • Traditional birth assistance (managing normal labour and recognizing basic complications).
  • The extensive use of medicinal plants (pharmacognosy), many of which form the basis of modern pharmacology today.
  • Community support networks for older, frail people.
  • Care of injured persons (e.g., using splints made of bamboo or reeds for fractures).
  • Consultations with specialized traditional health practitioners.

2.3 Contributions to Modern Nursing History

Traditional healthcare systems did not simply disappear; they laid a permanent foundation for modern African nursing. Contributions include:

  • Community participation: The concept that health is a community issue, not just an individual one (the basis of Primary Health Care).
  • Knowledge of local resources: Understanding locally available medicinal plants and nutrition.
  • Maternal and newborn support: The strong cultural emphasis on protecting the mother and child.
  • Family involvement in patient care: In African hospitals today, the "patient attendant" (family member) remains a crucial part of the care team, a direct carryover from precolonial times.
  • Cultural competence: Recognition of the absolute importance of cultural beliefs, spirituality, and psychology in healthcare and healing.

3. Healthcare in Ancient African Civilizations

Africa is the cradle of human civilization, and it possessed highly organized systems of medical knowledge millennia before the colonial period.

3.1 Ancient Egypt

Ancient Egypt developed deeply documented medical knowledge, complex medicinal preparations, and structured approaches to treating various illnesses and injuries.

  • The Ebers Papyrus (c. 1550 BC): One of the oldest preserved medical documents in the world. It contains vast medical information, herbal remedies, magical spells, and detailed descriptions of treatments for asthma, digestive disorders, and wound care.
  • Contributions: Development of medical texts, use of medicinal substances, advanced treatment of wounds/injuries, strict medical observation, practical surgical knowledge, and the development of specialized healing roles (physicians, priests, and caregivers).
Clarification for Nursing Students:
Ancient Egyptian medicine should not be described as "modern professional nursing" (as there was no formal nursing registry or Nightingale-style training). However, its historical development contributes significantly to the broader understanding of patient assessment, treatment, wound care, and healthcare organization. It was a massive contribution to the global development of healthcare knowledge.

3.2 Other African Healthcare Traditions

Beyond Egypt, other historically significant African societies developed their own sophisticated healing practices:

  • Ancient Nubia and Kush: Known for their advanced use of medicinal herbs and surgical techniques.
  • Ethiopian Christian Traditions: Early monastic caregiving and scriptural-based healing practices.
  • Islamic Healthcare: Found in parts of North and West Africa (e.g., Timbuktu), integrating scholarly medical texts, hospitals (Bimaristans), and advanced hygiene practices driven by Islamic teachings.
  • Indigenous Systems: Complex herbal and spiritual healing systems spreading across Central, Eastern, Southern, and Western Africa.

4. Missionary and Colonial Healthcare Systems

4.1 The Influence of Christianity & Missionaries

Christianity heavily contributed to the establishment of formal healthcare institutions in Africa, primarily through missionary organizations and churches arriving in the 19th and early 20th centuries. The nature and extent of this influence varied greatly by country and historical period.

Activities of Missionary Healthcare Institutions:

  • Providing treatment for sick people in newly built dispensaries.
  • Establishing rural hospitals and clinics (often in very remote areas where colonial governments refused to go).
  • Offering Maternal and Child Health (MCH) services, drastically reducing infant mortality in some areas.
  • Training healthcare workers: Missionaries opened the very first rudimentary nursing and midwifery training schools in Africa.
  • Providing health education and hygiene classes.
  • Supporting care for vulnerable populations (e.g., leprosy colonies, orphanages).
  • Conducting medical outreach into deep rural communities.

The Role of Missionary Nurses

European missionary nurses worked in diverse settings, often facing severe tropical diseases themselves. Their responsibilities included caring for hospitalized patients, providing MCH, teaching hygiene, assisting with surgeries, and participating in community outreach.

⚠️ Historical Considerations (The Dual Reality):
While missionary healthcare expanded access to medical services and introduced formal nursing education, it operated firmly within colonial and religious structures.
When discussing this history in an exam, you must include both the positive healthcare contributions AND the negative aspects: unequal power relationships, the forceful suppression of valid traditional cultural practices, and the limitations placed on African nurses (who were often treated as subordinate "helpers" rather than equals).

4.2 Colonialism and the Development of Nursing

Definition of Colonialism: The political and economic control of one territory or people by another power. European colonial rule profoundly affected much of Africa, shaping its healthcare infrastructure.

  • Colonial healthcare systems directly influenced the development of formal nursing education, the architecture of hospitals, the delivery of medical services, and the creation of professional nursing structures (Councils/Boards).
  • Initial Focus: Early colonial medical services were not built for the African population. They were established primarily to protect the health of colonial officials, European settlers, and the military. Only later did these expand to the selected local workforce to keep the labor pool healthy.

Important Distinction

Formal nursing education in Africa was not created entirely from nothing during colonialism. African communities already had established caregiving and healing practices. Colonial institutions merely introduced, expanded, or reorganized particular forms of Western-style professional training within these pre-existing societies.

4.3 Development of Nursing Training Schools

To staff their growing network of hospitals, colonial and missionary powers began opening formal nursing schools at different times across the continent.

Features of early formal training:

  • Classroom theoretical instruction based on European curricula.
  • Heavy practical hospital experience (often utilizing students as free labor).
  • Strict focus on nursing procedures, hygiene, and sanitation.
  • Maternal and child health training (midwifery was highly prioritized).
  • Discipline and professional conduct: Modeled after the strict, almost military-like discipline of Florence Nightingale's era (uniforms, rigid hierarchies).
  • Formal assessment and examinations leading to certification.

Limitations in Colonial Settings (Exam Focus)

The colonial nursing system was fundamentally flawed by systemic inequalities:

  • Unequal access to training: Education was limited to a privileged few.
  • Racial and social discrimination: African nurses were often paid a fraction of what European nurses earned and were barred from treating European patients.
  • Differences in training opportunities: Africans were often trained at a lower "enrolled" or "assistant" level rather than the "registered" level.
  • Limited career advancement: African nurses were systematically blocked from leadership, matron, or tutor positions.
  • Inadequate resources: Schools for Africans were heavily underfunded compared to those for settlers.
  • Prioritized populations: Healthcare systems ignored rural African communities in favor of urban colonial centers.

Example: In many colonial healthcare systems, African nurses were heavily trained to provide the grueling day-to-day clinical bedside services but faced hard legal and social restrictions preventing them from ever becoming nursing administrators.

5. Development of Nursing in East Africa

East Africa (including countries such as Uganda, Kenya, Tanzania, Rwanda, Burundi, and South Sudan) offers an excellent case study of how nursing developed regionally.

  • The Foundation: Missionary hospitals (e.g., Mengo Hospital in Uganda, established by Dr. Albert Cook) and government facilities worked simultaneously to expand formal medical and nursing services.
  • Contributions: They built dispensary networks, pioneered indigenous nursing and midwifery training (to combat devastating infant mortality and maternal death rates), and laid the groundwork for public health and disease control (battling sleeping sickness, smallpox, etc.).

Nursing Education Evolution in East Africa

Nursing education in this region developed through a steady combination of hospital-based apprentice training, dedicated nursing schools, standardized professional examinations, and eventually, the massive expansion into higher education.

Historical EraEducational Focus in East Africa
PrecolonialApprenticeship to TBAs, family-based herbal knowledge.
Early Missionary (Late 1800s - 1920s)Informal on-the-job "ward helpers" and basic midwifery skills to save mothers.
Late Colonial (1930s - 1950s)Formal Enrolled Nursing/Midwifery certificates. Strict rules, uniforms, and basic science.
Post-Independence (1960s onward)Registered Nursing diplomas, establishment of National Nursing Councils to set independent standards.
Modern EraUniversity Degrees (BSN), Masters, and PhDs. Focus on research and leadership.

6. Post-Independence Nursing Development

Following independence in the 1960s, African nations rapidly moved to dismantle the discriminatory colonial health structures. They worked aggressively to expand healthcare systems, making them accessible to the rural majority, and developed sovereign national approaches to nursing education and regulation.

Major Post-Independence Developments

  • Establishment of Nursing Councils: Creation of independent regulatory bodies (e.g., the Uganda Nurses and Midwives Council) to govern licensure, ethics, and practice standards without colonial oversight.
  • Expansion of Training Schools: Massive government investment in building regional nursing schools to address severe staff shortages.
  • Development of Higher Education: Transitioning from purely hospital-based certificates to robust Diploma and eventually University Degree (BSN) programs.
  • Growth of Public Health Nursing: Shifting focus toward preventative community health rather than just curative hospital care.
  • Specialization: Expansion into specialized services (psychiatric nursing, pediatric nursing, intensive care).
  • Maternal and Child Health (MCH): A massively increased national emphasis on reducing maternal and infant mortality rates.
  • Nursing Associations: Development of powerful labor and professional associations to advocate for nurses' rights, better pay, and working conditions.
  • Leadership: African nurses finally taking over Matron, Principal Tutor, and Chief Nursing Officer roles previously reserved for expatriates, leading to increased involvement in research and healthcare policy.

Modern Education Pathways

Today, depending on the specific African country and its regulatory framework, modern nurses may undertake a highly structured academic path:

  1. Certificate-level training (Being phased out in many countries in favor of diplomas).
  2. Diploma in Nursing / Midwifery (The backbone of the current workforce).
  3. Bachelor of Science in Nursing (BSN).
  4. Postgraduate Diplomas (For clinical specializations).
  5. Master's Degrees (MSN) (Focusing on advanced clinical practice, education, or administration).
  6. Doctoral Education (PhD / DNP) (Focusing on original nursing research and top-tier leadership).

Note: Specific entry requirements, qualifications, and licensing standards differ among countries and continue to evolve over time.

7. Factors That Influenced the Development of Nursing

The rapid growth and evolution of nursing in Africa has been continually shaped by multiple interconnected societal forces.

Social Factors Driving Healthcare Demand

  • Population growth: Explosive demographic growth requires a proportionally larger nursing workforce.
  • Urbanization: Mass migration to cities created crowded slums, sparking new public health crises (cholera, TB) requiring specialized community nursing.
  • Increased life expectancy: People are living longer, leading to a rise in chronic non-communicable diseases (diabetes, hypertension) that require long-term nursing management.
  • Changing family structures: The gradual breakdown of the traditional extended family means the elderly and sick can no longer rely solely on home care, increasing the demand for professional hospital and hospice care.
  • Greater demand for professional healthcare: As education levels rise, communities expect higher quality, scientifically backed medical care.
Nursing Implication:
Because of these dynamic social changes, the role of the modern African nurse has expanded far beyond the hospital bedside. Today, nurses provide critical care across hospitals, homes, schools, community centers, industrial workplaces, and mobile clinics.

8. Clinical Application: Cultural Competence in Modern Nursing

Understanding the history of traditional African medicine is not just an academic exercise; it is a critical clinical skill.

A nurse working in an African community MUST demonstrate cultural sensitivity. They must assess traditional health practices respectfully, identify potential physiological risks, provide appropriate and gentle health education, and support timely referrals without causing the patient to feel alienated.

🩺 Example Scenario (Applying History to Practice):
A patient arrives at your clinic for abdominal pain and admits they have been drinking a traditional herbal preparation given by an elder.

Poor Nursing Practice: Scolding the patient, mocking their "backward" beliefs, and throwing the herbs away. (This causes the patient to hide information in the future and destroys trust).

Excellent Nursing Practice: The nurse respectfully asks about the specific preparation, assesses the patient's current physical condition, identifies potential pharmacological interactions or organ toxicity, and provides appropriate medical care without dismissing the patient disrespectfully. The nurse acknowledges the historical importance of herbalism while gently educating the patient on the benefits of standardized modern treatment for their specific condition.

Quick Quiz

History of Nursing in Africa Quiz

FON

Privacy: Your details are used only for quiz tracking and certificates.

History of Nursing in Africa Read More »

Standards of Care

Nursing Care Procedures and Standards of Care

Nursing Care Procedures and Standards of Care

This comprehensive guide covers the foundational principles of nursing care, the standards that govern clinical practice, the nursing process, and the step-by-step procedures required to deliver safe, effective, and ethical patient-centered care.

1. Fundamentals of Nursing Care

Definition of Nursing Care

Nursing care is the systematic provision of safe, evidence-based, individualized care to patients to promote health, prevent illness, restore health, relieve suffering, and support patients and families. It goes beyond mere task completion; it is a holistic approach treating the physical, emotional, and psychosocial needs of the patient.

Main Aims of Nursing Care

  • Promote health and wellbeing: Encouraging healthy lifestyle choices, nutrition, and exercise.
  • Prevent disease and complications: Implementing infection control, administering immunizations, and turning bedridden patients to prevent pressure sores.
  • Restore health: Administering medications, providing wound care, and assisting in rehabilitation therapies after an illness or surgery.
  • Relieve pain and suffering: Offering both pharmacological (painkillers) and non-pharmacological (positioning, reassurance) interventions.
  • Maintain dignity and independence: Respecting patient privacy and encouraging them to do as much for themselves as their condition allows.
  • Provide psychological and social support: Listening to the patient's concerns, counseling families, and involving social workers when needed.
  • Educate patients and families: Teaching patients about their diagnosis, medications, and self-care at home.
  • Promote safe discharge and continuity of care: Ensuring a smooth transition from the hospital to the home or a lower-level care facility, accompanied by proper referral notes.

2. Standard of Care

Definition

A standard of care is the level of care that a reasonably competent healthcare professional is expected to provide under similar circumstances. It is the legal and ethical benchmark used to evaluate whether a nurse has performed their duties correctly.

In nursing, standards guide nurses in providing safe, competent, ethical, evidence-based, and patient-centred care.

💡 Important Principle:
A nursing procedure is not merely a series of technical steps; it must be performed safely, ethically, competently, and strictly according to the patient's individual needs. Treating the patient as a unique human being is always superior to just "completing a task."

Sources of Nursing Standards

A nurse should never guess how to perform a procedure. Practice must be based on:

  • Professional nursing standards: Set by national and international nursing bodies.
  • National laws and regulations: The legal framework governing healthcare in the country.
  • Nursing and Midwifery Council requirements: The regulatory body's scope of practice.
  • Hospital/institutional policies: Local facility guidelines (e.g., the specific hospital's policy on blood transfusions).
  • Evidence-based guidelines: Current scientific research and clinical trials.
  • Standard Operating Procedures (SOPs): Step-by-step instructions for routine tasks.
  • Manufacturer instructions for equipment: Essential for operating ventilators, IV pumps, or monitors safely.
  • Patient-specific prescriptions and care plans: The individualized plan written by the healthcare team.
  • Professional code of ethics: Guiding moral behavior, confidentiality, and patient advocacy.
  • Current infection-prevention standards: Guidelines from WHO or local ministries of health.

3. The Nursing Process (ADPIE)

The nursing process provides the absolute foundation and scientific method for delivering nursing care. It ensures care is structured, logical, and continuously evaluated.

  1. A — Assessment: Collect comprehensive information about the patient. This involves taking a history, performing a physical examination, and reviewing lab results.
  2. D — Diagnosis: Identify actual or potential nursing problems based on the assessment data (e.g., "Acute pain related to surgical incision," or "Risk of infection").
  3. P — Planning: Set measurable, achievable goals and select appropriate nursing interventions to solve the identified problems.
  4. I — Implementation: Carry out the planned nursing interventions safely and timely.
  5. E — Evaluation: Determine whether the goals set during the planning phase have been achieved, and observe the patient's response.
  6. Reassessment: The cycle continues. If the goal was not met, the nurse must reassess the patient and modify the care plan.

4. General Standard for Performing a Nursing Procedure

Most nursing procedures, regardless of complexity, can be organized into a standard workflow to ensure safety and efficiency.

A. Preparation (Before touching the patient)

  • Review the patient's condition: Are they stable enough for the procedure?
  • Review the medical/nursing orders: Confirm the procedure is actually prescribed.
  • Check relevant history: e.g., bleeding disorders before an injection.
  • Identify contraindications: Is there a reason this procedure should not be done right now?
  • Gather equipment: Bring everything to the bedside to avoid leaving the patient midway.
  • Check that equipment is clean and functional: Test devices before attaching them to the patient.
  • Perform hand hygiene: The single most important step to prevent infection.
  • Ensure privacy: Close doors, draw curtains.
  • Determine whether assistance is required: Do you need a second nurse to help turn a heavy patient?

B. Patient Identification

Administering care to the wrong patient is a catastrophic clinical error. Always use the facility's approved identification process.

  • Usually verify at least two appropriate patient identifiers according to institutional policy.
  • Examples of valid identifiers: Full name, Date of birth, Hospital/medical record number.
🚨 Critical Safety Warning:
Do not use bed number alone as patient identification! Patients frequently switch beds or rooms. Always ask the patient to state their name, or check their official wristband.

C. Explaining the Procedure & Obtaining Consent

Before performing any procedure, no matter how routine, you must:

  • Introduce yourself: State your name and your role (e.g., "Hello, I am Nurse Sarah").
  • Explain what you are going to do: Break it down simply.
  • Explain why it is necessary: Give the clinical rationale.
  • Explain what the patient may feel: Prepare them for potential discomfort (e.g., "You will feel a sharp pinch").
  • Allow the patient to ask questions: Ensure they fully understand.
  • Obtain consent: Secure verbal or written consent according to applicable policy.

Example: "I am going to check your blood pressure. The procedure will take only a few minutes. You may feel the cuff tighten around your arm."
Benefit: Good communication significantly reduces patient anxiety and promotes their active cooperation.

D. Privacy and Dignity

The hospital environment strips away much of a person's privacy. The nurse must actively protect it:

  • Close curtains or doors securely before starting.
  • Expose only the specific area being examined or treated; keep the rest of the body covered.
  • Cover the patient appropriately using sheets or blankets.
  • Maintain respectful, professional communication at all times.
  • Avoid unnecessary exposure to passing staff or other patients.
  • Explain exactly what you are doing before touching the patient.
  • Respect cultural, religious, and personal preferences regarding touch and modesty.

Remember: Treat the patient as a person, not as a procedure.

5. Infection Prevention and Control

Every single nursing procedure must incorporate strict infection-prevention principles to stop the spread of Healthcare-Associated Infections (HAIs).

Standard Precautions Include:

  • Hand hygiene.
  • Appropriate Personal Protective Equipment (PPE) - gloves, masks, aprons, eye protection.
  • Safe injection practices (never recapping needles).
  • Respiratory hygiene and cough etiquette.
  • Appropriate handling of contaminated equipment.
  • Safe disposal of sharps in approved puncture-proof containers.
  • Appropriate cleaning, disinfection, or sterilization of reusable instruments.
🖐️ WHO's Five Moments for Hand Hygiene:
This is a major global framework for infection prevention in healthcare. Memorize these five moments:
  1. Before touching a patient.
  2. Before a clean/aseptic procedure.
  3. After body-fluid exposure/risk.
  4. After touching a patient.
  5. After touching the patient's surroundings.

Aseptic Technique

Aseptic technique refers to strict practices used to prevent contamination by microorganisms during procedures where the infection risk is highly significant.

  • Examples include: Wound dressing, urinary catheterization, insertion of invasive devices (like central lines), IV procedures, and operating theatre sterile procedures.

Principles of Aseptic Technique:

  • Perform thorough hand hygiene.
  • Prepare a clean/sterile field as required.
  • Do not touch sterile items with contaminated (or bare) hands.
  • Keep sterile equipment strictly sterile (sterile only touches sterile).
  • Avoid reaching over sterile fields unnecessarily, as dust/bacteria can drop from your arm onto the field.
  • Replace contaminated equipment instantly if sterility is broken.
  • Follow institutional aseptic technique policy strictly.

6. General Procedure Format (The 12 Steps)

For examinations, clinical practice, and OSCEs, use this universally adaptable 12-step sequence for most nursing procedures:

  1. Assess: Review patient status and need for the procedure.
  2. Prepare: Gather equipment, ensure a clean environment.
  3. Explain: Introduce yourself and detail the procedure to the patient.
  4. Identify: Verify the patient using two identifiers.
  5. Obtain consent: Get permission to proceed.
  6. Position: Ensure the patient is in the correct, safe, and comfortable posture for the specific task.
  7. Perform: Execute the technical steps of the procedure competently and aseptically.
  8. Observe: Watch the patient's reactions, pain levels, and vital signs during the task.
  9. Reassess: Check if the procedure was effective immediately afterward.
  10. Dispose/clean: Segregate waste, dispose of sharps safely, and clean reusable equipment.
  11. Document: Write down everything that was done and the patient's response.
  12. Report: Verbally escalate any abnormal findings to the charge nurse or physician.

7. Patient Safety During Procedures (ABCDE)

Before and during any procedure, constantly monitor the patient's fundamental life signs using the ABCDE approach:

  • A — Airway: Is the airway patent (open and clear)? Ensure positioning does not choke the patient.
  • B — Breathing: Is the patient breathing adequately? Observe respiratory rate and effort.
  • C — Circulation: Assess pulse, blood pressure, tissue perfusion (skin color/warmth), and watch for any bleeding where relevant.
  • D — Disability: Consider consciousness levels (AVPU scale), neurological status, and pain levels.
  • E — Exposure/Environment: Check the patient and the surrounding environment while strictly maintaining their dignity and preventing hypothermia (keeping them warm).

8. Common Nursing Care Procedures

A. Vital Signs

Includes: Temperature, Pulse, Respiratory rate, Blood pressure, Oxygen saturation, and Pain assessment (often called the 6th vital sign).

  • Standard principles: Explain the procedure, position the patient appropriately (e.g., resting for 5 mins before BP), use functioning calibrated equipment, use correct technique, record results accurately, compare with previous measurements, and report abnormal findings immediately.
💡 Example of Clinical Thinking vs. Just Recording:
If a patient's respiratory rate suddenly increases from their baseline, do not simply record the number and walk away.
Assess the patient further and look for: Shortness of breath, oxygen saturation changes, chest pain, fever, severe anxiety, or other signs of deterioration. Then, escalate appropriately to the medical team.

B. Oral Care

Purpose: Maintain oral cleanliness, promote comfort, prevent oral infections (like thrush or ventilator-associated pneumonia), improve appetite and taste, reduce accumulation of thick secretions, and support general oral health.

  • Basic procedure: Explain, perform hand hygiene, position patient safely (often semi-Fowler's or side-lying to prevent choking), protect clothing/bed with a towel, inspect the mouth with a penlight, brush teeth/gums/tongue appropriately, rinse where safe, provide oral moisturizing care (lip balm) if required, clean equipment, and document/report abnormalities (bleeding gums, sores).
  • Special caution: Patients with reduced consciousness, stroke, or swallowing difficulties require special aspiration precautions. Keep them on their side and use suction to prevent fluid from entering the lungs.

C. Bed Bath / Personal Hygiene

Objectives: Maintain cleanliness, promote comfort, prevent skin complications, promote circulation (through warm water and friction), and allow for full-body skin assessment.

  • Nursing responsibilities (Skin Inspection): During bathing, actively inspect for redness, pressure injuries (bedsores), rash, wounds, bruising, swelling, skin breakdown, and changes in temperature or skin colour.
  • Standard: Maintain absolute privacy, warmth, dignity, and encourage patient participation (let them wash their own face/hands if able) throughout the procedure.

D. Patient Positioning

Correct positioning should actively promote: Comfort, proper body alignment, optimal respiratory function, adequate circulation, skin integrity, and patient safety.

  • Examples of Positions:
    • Supine: Lying flat on the back.
    • Fowler's / Semi-Fowler's: Head of bed elevated (improves breathing and feeding).
    • Lateral: Side-lying (relieves pressure on the sacrum).
    • Prone: Lying face down (used in acute respiratory distress).
    • Sims': Semi-prone side position (used for enemas or rectal exams).
    • Orthopneic: Sitting up and leaning over a table (maximizes chest expansion for severe asthma/COPD).
    • Lithotomy: Supine with legs in stirrups (gynecological exams).
  • Safety checks during positioning: Always assess pressure areas (heels, elbows, sacrum), body alignment, ensure tubes/drains are not pulled or kinked, assess pain levels, check distal circulation, and monitor respiratory status after moving them.

E. Medication Administration

Medication administration requires incredibly strict adherence to the medical order and institutional policy to prevent fatal errors.

Common Medication Safety Checks (The "Rights"):
Use the facility's approved medication rights, commonly including:

  1. Right patient: Check two identifiers.
  2. Right medication: Read the label three times.
  3. Right dose: Check calculations and units.
  4. Right route: Oral, IV, IM, Subcut?
  5. Right time: Give at the scheduled interval.
  6. Right documentation: Sign immediately after giving the drug, never before.
  7. Right reason/indication: Does it make clinical sense for this patient?
  8. Right response/evaluation: Did the blood pressure drop after the antihypertensive was given?
  9. Right education: Inform the patient what the drug is and its side effects.

The exact "rights" framework varies between institutions, but patient identification and medication verification must always be performed carefully.

Timeline of Checks:

  • Before administration Check: Medication order, patient allergies, patient identity, medication name, dose, route, time, expiry date/condition of the drug, and relevant baseline observations/laboratory information when required (e.g., checking pulse before giving Digoxin).
  • After administration: Monitor response, monitor for adverse effects, document appropriately, and escalate any adverse reactions promptly to the doctor.

F. Injections

  • Common routes: Intradermal (into the dermis, e.g., BCG vaccine), Subcutaneous (into the fat layer, e.g., Insulin), Intramuscular (deep into muscle, e.g., Ceftriaxone), Intravenous (directly into a vein).
  • The technique varies according to: The medication properties, the route, the patient's body size/muscle mass, the specific injection site chosen, the needle size/device, and institutional policy.
  • Universal safety principles: Verify medication, check allergies, perform hand hygiene, use appropriate PPE, use a new sterile needle/syringe for each injection, never reuse needles or syringes, and dispose of sharps immediately in an approved, puncture-proof sharps container.

G. Wound Care

Objectives: Promote optimal healing environment, prevent infection, remove excess exudate (pus/fluid) when indicated, protect the wound from trauma, and continuously assess the healing progress.

  • Assess the following parameters: Location, exact size (length, width, depth), appearance of the wound bed (red/granulating, yellow/slough, black/necrotic), wound edges, exudate (type and amount), odour, condition of the surrounding skin, and patient pain levels.
  • Signs requiring immediate medical attention (Infection): Increasing redness spreading outward, massive swelling, unnatural heat radiating from the wound, increasing intense pain, purulent (thick yellow/green) discharge, foul rotting odour, systemic fever, and sudden wound deterioration.

H. Urinary Catheter Care

Purposes of catheterization: Urinary retention management, accurate hourly urine output monitoring in critically ill selected patients, certain prolonged surgical procedures, and specific clinical indications (e.g., end-of-life comfort or healing of severe perineal wounds).

  • Nursing care principles: Maintain a strictly closed drainage system where applicable to prevent bacterial entry, always keep the drainage bag below the level of the bladder (to prevent infected urine flowing back into the bladder), avoid unnecessary disconnection of tubes, prevent tubing kinks or blockages, maintain appropriate daily meatal hygiene, monitor urine characteristics (color, clarity) and output volume, and review daily whether the catheter remains absolutely necessary (remove ASAP to prevent CAUTI - Catheter-Associated Urinary Tract Infections).

I. Oxygen Administration

Oxygen is a medication/therapy and should be administered strictly according to clinical indication and medical prescription/protocol.

  • Nursing responsibilities: Assess baseline respiratory status, check oxygen saturation (SpO2) when indicated, select the appropriate delivery device (e.g., nasal cannula vs. non-rebreather mask), apply the prescribed flow rate/concentration, monitor the patient's physiological response, ensure equipment is actually functioning (humidifier bubbling, oxygen flowing), and maintain oxygen safety.
  • Oxygen safety: No smoking or open flames near oxygen (it heavily supports combustion and causes explosions). Keep oxygen equipment far away from ignition sources and follow facility oxygen-storage policies strictly.

J. Pressure Injury Prevention

Pressure injuries (bedsores) are largely preventable through diligent nursing care.

  • Assess risk factors (e.g., using the Braden Scale): Consider the patient's mobility, sensory perception (can they feel pain?), skin moisture (incontinence), nutrition, perfusion, age/general condition, and any existing skin damage.
  • Prevention Strategies: Reposition the patient appropriately (usually every 2 hours), use pressure-redistributing surfaces (air mattresses), explicitly protect the vulnerable heels (elevate them off the bed), keep skin meticulously clean and dry, manage moisture from sweat/urine, minimize friction and shear (use slide sheets to move patients, do not drag them), and actively support good nutrition and hydration to keep skin resilient.

K. Pain Management

  • Assess pain: Use an appropriate validated pain scale (e.g., 0-10 numerical scale, or FACES scale for children). Assess: Location, Intensity, Character (stabbing, burning, aching), Duration, Onset, Aggravating factors (what makes it worse?), Relieving factors (what makes it better?), and its effect on daily function.
  • Management may include: Prescribed analgesics, optimal positioning, relaxation techniques, heat/cold application where appropriate, reassurance, psychological support, and other non-pharmacological interventions.
  • Always reassess: The cycle must be: Assess ➔ Treat ➔ Reassess ➔ Document. If you give a painkiller, you must return in 30-60 minutes to check if the pain has actually decreased.

L. Patient Transfer and Mobility

  • Before moving a patient, assess: Patient strength, balance, level of consciousness, weight-bearing ability, pain levels, dizziness, general falls risk, presence of IV lines/drains that could be pulled out, and the need for staff assistance or lifting equipment.
  • Use appropriate equipment: Examples include transfer belts, slide sheets, transfer boards, wheelchairs, and mechanical hoists/lifts.
  • Safety Rule: Avoid manually lifting heavy patients who require mechanical assistance when appropriate equipment is available. Protect your own back!

M. Fall Prevention

  • Nursing interventions: Actively assess falls risk upon admission, keep the call bell accessible and in the patient's hand, ensure adequate room lighting, keep the floor totally dry and mop spills instantly, remove obstacles/clutter, use appropriate non-slip footwear, assist the patient with mobility to the bathroom, keep frequently used items (water, glasses) within easy reach on the bedside table, and follow individualized safety measures (like lowering the bed or using bed rails if appropriate).
  • Never assume: "The patient can walk because they walked yesterday." A patient's mobility can change rapidly within hours because of acute illness, new medications (like sedatives or blood pressure drugs), pain, weakness, or dizziness.

9. Patient Education

Patient education is an absolutely essential nursing responsibility, vital for empowering patients to manage their own health post-discharge.

Principles of Effective Education:

  • Assess the patient's existing knowledge first.
  • Identify their specific learning needs.
  • Use understandable, simple language.
  • Avoid unnecessary medical jargon.
  • Demonstrate physical tasks where appropriate (e.g., insulin injection technique).
  • Ask the patient to explain or demonstrate the task back to you (the "Teach-Back" method) to confirm learning.
  • Provide written information or pamphlets where appropriate.
  • Continually evaluate their understanding.
❌ Poor Practice (Too much Jargon)✅ Better Practice (Clear and Simple)
"You have hypertension and require antihypertensive therapy.""Your blood pressure is higher than it should be. This medicine helps lower it safely."

10. Documentation

Definition: Documentation is the accurate, legal recording of patient assessment, the specific care provided, the patient's clinical response, and relevant clinical communication between healthcare teams.

Remember the golden rule of nursing: "If it is not documented, it was not done."

Good documentation should always be:

  • Accurate: True to the facts, without exaggeration.
  • Objective: Based on observable facts (e.g., "Patient is crying"), not subjective judgments (e.g., "Patient is acting like a baby").
  • Timely: Written as soon as possible after the event.
  • Complete: Covering all aspects of care.
  • Legible/appropriately electronic: Clear handwriting or proper EMR typing.
  • Confidential: Protected from unauthorized viewing.
  • Relevant: Focused on clinical facts.

What to Document:

  • Assessment findings (vital signs, physical exam results).
  • Specific nursing interventions performed.
  • Medication administration (time, dose, route).
  • Patient response to treatments (e.g., "Pain reduced from 8/10 to 3/10 after paracetamol").
  • Education provided to the patient.
  • Any changes in the patient's condition.
  • Communication/escalation of deteriorating signs to the doctor.
  • Referrals made to other departments where relevant.
📝 Example of Documentation Quality:

❌ Poor: "Patient doing well." (This is vague, subjective, and gives no clinical data).

✅ Better: "Patient reports pain 3/10 at the surgical site. Wound dressing dry and intact. Vital signs stable. Assisted patient to Fowler's position. Patient reports improved comfort." (This provides objective data, specific interventions, and the patient's evaluation).

11. Ethical Principles

Nurses face complex moral decisions daily. These core ethical principles must guide every action and decision you make regarding patient care:

  • Autonomy: Respect the patient's right to make informed decisions about their own body and care, even if you disagree with their choice.
  • Beneficence: Actively do good. Always act in the patient's absolute best interests to promote their wellbeing.
  • Non-maleficence: "Do no harm." Avoid causing harm, whether intentionally or through reckless negligence.
  • Justice: Provide fair, equal, and equitable care to all patients, regardless of their race, financial status, or background. Allocate resources fairly.
  • Confidentiality: Protect private patient medical information strictly. Never share details with unauthorized individuals or family members without the patient's explicit consent.
  • Veracity: Communicate honestly. Always tell the truth to your patients regarding their diagnosis and treatment to build trust.

12. Standard of Care During Any Procedure (SAFE CARE)

To ensure you meet all clinical and ethical standards when performing any nursing task, memorize and apply the SAFE CARE mnemonic:

SAFE CARE Mnemonic

  • S — Safety first: Prioritize the physical safety of the patient, yourself, and the environment.
  • A — Assess the patient: Gather baseline data before starting.
  • F — Follow approved procedure/policy: Stick to the institutional guidelines and evidence-based SOPs.
  • E — Explain and obtain appropriate consent: Ensure the patient understands and agrees.
  • C — Control infection: Perform hand hygiene, use PPE, and maintain aseptic technique.
  • A — Act competently: Perform the skill precisely as trained.
  • R — Reassess response: Check how the patient handled the procedure and if the outcome was achieved.
  • E — Enter/document findings: Accurately chart the procedure, the time, and the patient's response in the medical record.

Quick Quiz

Nursing Care Procedures Quiz

FON

Privacy: Your details are used only for quiz tracking and certificates.

Nursing Care Procedures and Standards of Care Read More »

Want notes in PDF? Join our classes!!

Send us a message on WhatsApp
0726113908

Scroll to Top
Enable Notifications OK No thanks