

Before memorizing the steps of a dressing or a bandage, you must understand the underlying physiology of tissue repair and vascular dynamics. Nursing is not just completing tasks; it is applied physiology. If you understand why a wound heals or how a bone dies from lack of blood, the procedures will make perfect logical sense.
Every wound, from a tiny paper cut to a massive surgical incision, heals through four distinct, overlapping phases. Aseptic dressing techniques are designed to protect these fragile stages:
- Hemostasis (Minutes): Blood vessels constrict, and platelets aggregate to form a fibrin clot to stop bleeding.
- Inflammation (Days 1-4): White blood cells (neutrophils and macrophages) flood the area to eat dead tissue and kill bacteria. The wound is red, warm, and swollen.
- Proliferation (Days 4-21): New blood vessels form (angiogenesis), and fibroblasts lay down collagen. Bright red, bumpy Granulation Tissue fills the wound bed. (Rough bandaging or peeling off a dry dressing rips this new, fragile tissue away!)
- Maturation/Remodeling (Months to Years): Collagen cross-links and strengthens, forming a scar.
Veins have one-way valves to push blood back to the heart against gravity. When you bandage a limb, you must always bandage from below, upwards (distal to proximal). This physically squeezes the blood back toward the heart. If you bandage downwards, you trap blood in the extremity, causing massive, painful swelling.
The skin is heavily colonized with normal flora (like Staphylococcus epidermidis). When the skin breaks, these bacteria become deadly pathogens. Aseptic technique utilizes a strict clean-to-dirty workflow to ensure that zero bacteria are pushed from the outside skin into the sterile wound bed.
- A Dressing is a sterile pad or compress applied directly to a wound to promote healing, protect it, and/or absorb exudate (fluids).
- Wound Dressing is the systematic, aseptic procedure of cleaning a wound and applying a sterile covering using strict sterile technique and sterile equipment.
Why do we dress wounds? As a nurse, you must know these indications for your OSCEs:
- To protect the wound from further mechanical injury or external bacterial infection.
- To absorb exudates such as pus, blood, or serum (preventing the skin from macerating).
- To immobilise and support the injured part, reducing pain.
- To apply pressure on the wound to control bleeding (hemostasis) or to approximate (bring together) the wound edges.
- To provide psychological and physical comfort for the patient (hiding a severe, traumatic wound drastically reduces patient anxiety).
- To keep the wound environment moist for optimal healing (dry cells die!) and to allow for regular inspection/monitoring of the wound bed.
- Surgical wounds: Sutured incisions directly from the operating theatre. These are usually clean, primary-intention wounds.
- Traumatic wounds: Abrasions, lacerations, and deep punctures from accidents (high risk for tetanus and gross contamination).
- Infected wounds: Wounds actively discharging foul-smelling fluids or pus ("dirty wounds").
- Burn wounds: Requiring highly specialized, sterile, non-adherent care to prevent peeling off massive sheets of skin.
- Chronic wounds: Pressure sores (bedsores from ischemia), diabetic foot ulcers (neuropathy), and venous leg ulcers.

| Type of Dressing | Clinical Description & Specific Use |
|---|---|
| Dry sterile dressings (Gauze) | Basic sterile woven/non-woven gauze. Used primarily for covering clean, dry, sutured surgical wounds. |
| Non-adherent dressings | Dressings treated with petroleum jelly (e.g., Paraffin gauze / Jelonet). They do not stick to the raw, weeping wound surface, making removal completely painless. Ideal for burns, grazes, and fragile skin grafts. |
| Wet-to-dry dressings | Saline-moistened gauze is packed deep into a dirty wound. As the gauze dries, it physically binds to dead, necrotic tissue. When pulled out, it mechanically debrides (rips out) the dead tissue. Used exclusively for dirty/sloughy wounds. |
| Occlusive / Semi-permeable films | Clear, waterproof polyurethane films (e.g., Tegaderm). They keep the wound moist while allowing oxygen/carbon dioxide gas exchange. Perfect for protecting IV insertion sites and superficial minor burns. |
| Hydrocolloid / Alginate / Foam | Advanced modern dressings. Alginates (derived from seaweed) can absorb up to 20x their weight in extremely heavy exudate. Hydrocolloids turn into a soothing gel to promote rapid granulation tissue growth. |
Aseptic technique is the absolute foundation of wound care. The core principles are to:
- Prevent cross-infection (spreading nosocomial germs like MRSA from one patient to another) and wound sepsis.
- Protect both the patient and the nurse by following Universal Precautions (treating all blood/body fluids as potentially infectious for HIV, Hepatitis B, and C).
- Ensure that ONLY sterile articles touch the wound bed.
- Maintain a strict clean-to-dirty workflow, performing rigorous hand hygiene before and after the procedure.
Before you clean a wound, you must scientifically observe and document its status:
- Anatomy: Site, exact size (length x width), depth, and shape of the wound.
- Exudate: Type and amount of discharge: Serous (clear fluid), Sanguineous (fresh blood), Serosanguineous (pinkish), or Purulent (thick, foul-smelling pus).
- Wound Edges: Are they approximated (closed nicely) or gaping open? Check the integrity of any stitches, clips, or surgical drains.
- Signs of Infection: Redness (erythema), heat, localized swelling, severe pain out of proportion, fever, or dangerous red streaks tracking up the limb (lymphangitis).
- Periwound: The condition of the surrounding skin (is it macerated/soggy?) and the patient's general systemic vital signs.
If a nurse is sloppy with asepsis or aggressive with cleaning, it leads to severe wound sepsis, system-wide bacteremia, drastically delayed healing, wound dehiscence (a horrific complication where a surgical wound bursts completely open), excessive bleeding, or the destruction of fragile new granulation tissue from rough handling. Always respect the sterile field!
Examiner Objectives:
1. Mention the indications for wound dressing.
2. Mention the general rules of wound dressing.
3. Identify requirements for wound dressing.
4. Prepare requirements for wound dressing.
5. Perform the wound dressing flawlessly.
| No. | Clinical Rule | Physiological Rationale |
|---|---|---|
| 1. | All bed making, mopping of the floor and dusting must be finished at least one hour before the dressing round is started. | To prevent the spread of infections (allows airborne dust and aerosolized bacteria to settle completely). |
| 2. | Before the dressing round, wash the trolley thoroughly with soap and water and dry it. | Mechanical removal of gross organic matter. |
| 3. | Before each individual dressing, wipe the trolley shelves with a potent disinfectant using a moppar. | Chemical destruction of remaining pathogens. |
| 4. | Sterile articles are placed strictly on the TOP shelf; un-sterile articles on the BOTTOM shelf. | Prevents accidental contamination from unsterile items dropping onto sterile ones. |
| 5. | Clean, uninfected wounds are ALWAYS dressed first. | Prevents tracking deadly bacteria from dirty wounds into clean surgical wounds. |
| 6. | Limit movements in the ward; windows/fans near the patient being dressed must be closed. | To prevent drafts from blowing cross-infectious pathogens onto the sterile field. |
| 7. | Do not carry out dressing when having a focal wound or droplet infection (e.g., a cold/flu). | Protects the highly vulnerable patient from the nurse's pathogens. |
| 8. | If possible, 2 nurses should be available to carry out the dressing. | One "clean" nurse handles the patient; one "sterile" nurse handles the instruments. Prevents contamination and saves time. |
| 9. | Apply universal infection prevention and control before and after each procedure. | Standard protocol to prevent the spread of bloodborne infections. |
| 10. | Nails must be cut short; watches and rings MUST be removed. | Jewelry harbors immense colonies of bacteria and tears sterile gloves. |
| 11. | Masks are worn if required. Once in position, they must not be touched. • When removing, handle only the tapes and dispose immediately. • NEVER put a used mask in a uniform pocket. | The front of the mask acts as a filter and is heavily contaminated with bacteria. |
| 12. | Lotions: The dressing assistant should pour only enough lotion for one single dressing. Unused lotion must be disposed of. | To avoid wastage and eliminate the risk of cross-infection from contaminated bottles. |
| 13. | The trolley MUST be reset for each individual dressing. | Maintains strict single-patient use standards. |
| 14. | All used equipment must be decontaminated in chlorine, washed with soapy water, brushed, dried, and sterilised (Autoclaved). | To ensure absolute sterility ready for the next dressing. |
| 15. | The trolley is cleaned with disinfectant post-procedure. | Leaves the environment safe. |
You must memorize this exact layout for your practical exams to avoid failing on safety protocols:
| Top Shelf (Strictly Sterile) | Bottom Shelf (Unsterile / Clean) | Bed Side / Environment |
|---|---|---|
|
Sterile Dressing Pack containing: - 2 dressing towels (drapes). - 2 non-toothed dissecting forceps. - 2 dressing forceps. - 3 gallipots: • 1 for sterile swabs. • 1 for the cleaning lotion (e.g., Normal Saline). • 1 for gauze dressing. - A pair of stitch scissors or a clip remover (if specifically required). |
- A dressing mackintosh (waterproof sheet) and towel. - Receiver for soiled/dirty dressings. - Receiver for used/dirty instruments. - A bottle of approved antiseptic lotions. - A drum for extra sterile dressings. - A drum for extra sterile swabs. - A tray with bandages, scissors, safety pins, strapping/tape. - A container of Cheatle forceps (for transferring sterile items). - A pair of sterile gloves and a pair of clean exam gloves. - A bowl. | - Hand washing equipment (Soap, water, sterile towels, or alcohol hand rub). |
If the examiner verbally tells you or the scenario dictates that the wound is dirty, necrotic, or infected, you MUST dynamically add these specific items to your trolley setup:
- Probe: To assess the depth of sinuses/fistulas.
- Hydrogen peroxide (H2O2): For effervescent lifting of dead slough and necrotic debris.
- Pedal bin: For immediate disposal of highly infectious waste.
- Sinus forceps: For packing deep cavities.
- Pus swab + Laboratory form: For collecting a vital microbiology Culture & Sensitivity (C&S) sample before giving antibiotics.
- Hypotonic/Hypertonic saline: Based on osmotic requirements for the slough.
| Step | Nursing Action | Rationale |
|---|---|---|
| 1. | Refer to general rules. Introduce yourself, identify the patient, and explain the procedure. | To maintain sterility, ensure the correct patient, and reduce anxiety. |
| 2. | Dressing assistant positions the patient appropriately. | Ensures optimal lighting and access to the wound. |
| 3. | Place the mackintosh and towel directly under the part to be dressed. | Provides physical comfort and prevents potentially infectious fluids from soiling the bed linen. |
| 4. | Dressing assistant puts on clean gloves, removes the outer bandage, and loosens the strapping. | For easy and painless removal of the old dressing. |
| 5. | Dressing assistant removes gloves, washes hands, opens the sterile dressing pack, and adds any additional sterile equipment using Cheatle forceps. | To arrange the materials logically for easy use while maintaining an unbroken sterile field. |
| 6. | Add the sterile cleaning solution required into the gallipot. | Preparation for wound irrigation. |
| 7. | Dressing assistant puts on new clean gloves, carefully removes the inner dressing, and discards it directly in the receiver. | To prevent the spread of infections from the saturated old dressing. |
| 8. | Dressing nurse washes hands thoroughly with soap and water and dries with a sterile towel (or uses surgical rub). | To absolutely reduce the transient flora on the hands. |
| 9. | Put on sterile gloves using proper surgical technique. | To maintain strict surgical asepsis. |
| 10. | Drape the wound meticulously with the sterile dressing towels. | To create and provide an isolated sterile environment around the wound. |
| 11. | Using forceps, swab the wound in the following specific way, discarding EACH swab after a single use: • First, wipe the exact centre of the wound. • Then wipe each side of the wound, always working from the middle outwards. | Minimizes the spread of infection. Swabbing from clean (centre) to dirty (periphery) ensures you never drag skin bacteria into the raw wound bed. |
| 12. | For a dirty wound, perform the necessary toilet as prescribed. This may involve the removal of stitches/clips, probing the wound depth, or packing the wound with ribbon gauze. | Removes barriers to healing (slough) and promotes granulation from the base up. |
| 13. | Apply a sterile primary dressing to cover the wound. Add a secondary absorbent pad if oozing or heavy discharge is anticipated. | To protect the wound from trauma and prevent strike-through soiling of the linen. |
| 14. | Place all used, sharp, or contaminated instruments immediately into a dedicated receiver. | To avoid sharps injuries and cross-infections. |
| 15. | Remove gloves, apply strapping (tape) or a supportive bandage over the dressing as required. | To secure the dressing while maintaining hygiene and comfort. |
| 16. | Wash your hands, clear away the trolley, and leave the patient comfortable. | Standard infection control protocol. |
| 17. | Document the procedure (wound appearance, exudate, patient tolerance) and report any abnormalities immediately. | For legal continuity of care and surgical follow-up. |
- Use surgical spirit or alcohol for easy, painless removal of sticky adhesive marks from previous strapping.
- If the inner strapping/gauze is stuck and adherent to the raw skin, do not rip it! Soften it by soaking it with warm normal saline or antiseptic lotion.
- For a dirty wound, Hydrogen Peroxide is used specifically to bubble out hidden debris from deep crevices.
- Avoid excessive, aggressive surgical toilet. Scrubbing too hard destroys the delicate, new angiogenesis (blood vessels) required for wound healing and causes unnecessary bleeding.

Always clean in ONE direction only, from the cleanest part to the dirtiest part.
- 1st swab: Straight down the centre of the surgical incision. (Discard)
- 2nd swab: Down one side of the wound, moving slightly outward. (Discard)
- 3rd swab: Down the other side of the wound, moving slightly outward. (Discard)
Physiological Rule: Each swab is discarded after a single continuous stroke. Never return a used swab to the wound bed; doing so carries the patient's own skin flora (bacteria) back into the open tissues, causing iatrogenic infection.
Objectives:
1. Identify the exact requirements for the safe removal of sutures/clips.
2. Demonstrate the correct removal of sutures/clips without causing dehiscence.
Requirements: Same trolley setup as standard wound dressing, plus stitch scissors or a specialized clip remover.
| Step | Nursing Action | Rationale |
|---|---|---|
| 1. | Refer to general rules. Review the patient's surgical chart and doctor's orders. | To confirm the correct patient, the correct procedure, and ensure it is the correct postoperative day for removal. |
| 2. | Follow the standard procedure for opening a surgical wound dressing. | To promote strict infection prevention and control. |
| STITCH (SUTURE) REMOVAL | ||
| 1. | Grasp the knot of the stitch using a pair of non-toothed dissecting forceps and pull gently upward. Cut the suture wire as close to the skin as possible on the side beneath the knot, and pull the stitch out smoothly. | Crucial: This ensures that the dirty, exposed part of the stitch resting on the outside skin is NOT dragged through the clean internal wound tract, preventing deep infection. |
| 2. | Use antiseptic lotion for dirty wounds after the removal of stitches. If the skin is completely healed, clean, and dry, do not over-clean. | Maintains normal skin integrity. |
| CLIP (STAPLE) REMOVAL | ||
| 4. | Insert the lower jaw of the sterile clip remover completely under the centre of the metallic clip; squeeze the handles firmly until the clip bends completely in the middle and the edges lift out. | The clip remover mechanically bends the staple, allowing the prongs to back out of the skin safely without tearing tissue. |
| 5. | When the wound has healed perfectly with no discharge, a new heavy dressing is not necessary. A simple light covering or exposing to air is sufficient. | Exposure to air promotes drying and ultimate epidermization (quick healing). |
| 6. | Strictly COUNT the stitches or clips removed. | To compare against the surgical operation notes and ensure absolutely none are left embedded inside to cause a foreign body reaction or abscess. |
| 7. | Document the procedure, the number of sutures removed, and the status of the wound line. | For legal records and surgical follow-up. |
- Stitches or clips are normally removed between the 5th and 10th day post-operatively, depending on the tissue vascularity (face/neck heal fast in 5 days; joints/abdomens take 10-14 days).
- Sometimes the stitches or clips are removed alternatively (every other stitch) on day 7, and the rest on day 9. This prevents the nightmare complication of the wound bursting open (dehiscence) prematurely if it hasn't gained enough tensile strength.
- On some occasions, absorbable sutures (like Vicryl or Monocryl) may be used internally or subcuticularly, in which case they dissolve and are not removed.
For advanced exams, know the difference:
- Non-absorbable: Silk, nylon, polypropylene, stainless steel clips. The body cannot digest these; they retain strength indefinitely and must be physically cut and removed.
- Absorbable: Catgut, Vicryl, Dexon. Broken down via enzymatic digestion or hydrolysis naturally inside the body. Used for deep tissues.
- First Intention: Clean, neatly sutured edges that heal quickly with minimal scar tissue.
- Second Intention: A dirty, infected, or gaping wound that is intentionally left open. It heals slowly by massive granulation tissue filling the defect from the base upwards. Leaves a prominent, large scar.
- A Bandage is a continuous strip of material used to bind, support, cover, or immobilise a specific part of the body.
- Bandaging is the clinical technique of applying these bandages firmly, evenly, and safely to hold dressings in place, support muscular injuries, or apply hemostatic pressure.
- To keep a sterile dressing securely in position on a wound without using skin-damaging adhesive tape.
- To apply direct mechanical pressure and control severe bleeding (e.g., a pressure bandage for arterial hemorrhage).
- To support and immobilise an injured musculoskeletal part (sprains, strains, or undisplaced fractures).
- To prevent or rapidly reduce swelling (using compression combined with elevation).
- To secure rigid splints firmly in place against a broken limb.
- To correct or prevent physical deformity (e.g., clubfoot strapping) and to provide thermal warmth to a joint.
- To mechanically assist in venous blood return and reduce dependent oedema in the lower limbs.

- Roller bandages: Long strips rolled tightly on themselves. Made of Cotton (breathable), Crepe (highly elastic for compression), Domette, or Flannel.
- Triangular bandages: Extremely versatile First Aid staples! Made by cutting a large square of cloth diagonally. Used for arm slings, tourniquets, and securing massive dressings.
- Tubular bandages: E.g., stockinet, tube gauze, or elastic tubing. Slipped seamlessly over fingers, arms, and legs.
- Adhesive strapping (plaster): Sticky tape for exact fixation of dressings or strapping joints (e.g., sports taping).
- Plaster of Paris (POP) bandage: Gauze infused with dry calcium sulfate dihydrate. When soaked in water, it undergoes an exothermic reaction and hardens into rigid splints/casts for broken bones.
| Turn / Pattern Name | Clinical Description & Specific Use |
|---|---|
| Fixing (anchor) turn | 2 overlapping circular turns applied to firmly anchor the bandage to the limb before the real directional bandaging starts. |
| Circular turns | Each turn goes directly over the exact previous one. Used at the start/end of bandaging, or on perfectly cylindrical parts like fingers and toes. |
| Spiral turns | Each turn overlaps the previous by ½ to ⅔ of the width, ascending the limb smoothly and evenly. |
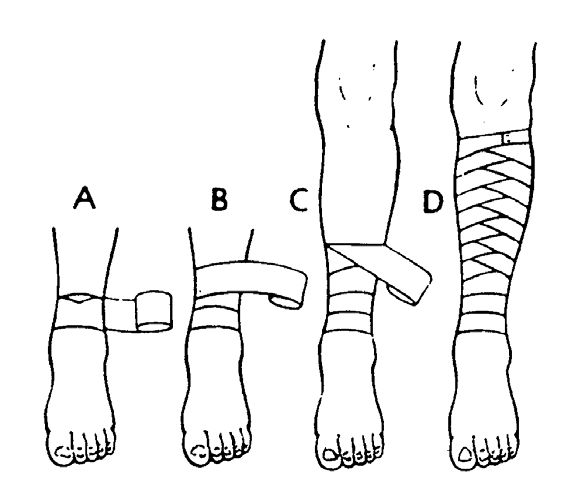
| Spiral-reverse turns | Required for limbs that rapidly change width or taper (like the muscular forearm or calf). You must fold/reverse the bandage 180 degrees at each turn to make it lie flat against the conical shape. |
| Figure-of-eight turns | The classic pattern used specifically for hinge joints (ankle, wrist, knee, elbow). It allows for movement while providing immense structural support. |
| Spica (basket-weave) turns | Crossing turns over a fixed joint or specific anatomical area (shoulder, hip, thumb). A Divergent spica is used for joints bent at an angle with fixed dressings (knee/elbow/heel). |
| Recurrent turns | Folding the bandage forwards and backwards over a blind stump/end (e.g., finger tip, severe amputation stump, or the dome of the head). |
- Too tight (The Ischemic Threat): Obstructs arterial blood flow and venous return, causing severe distal swelling, excruciating throbbing pain, numbness, a cold/blue (cyanotic) limb, and eventual tissue death (gangrene) requiring amputation.
- Too loose: Slips off instantly as the patient moves, completely failing to support the injury or apply life-saving pressure to bleeding.
- Too much tension on fragile skin: Causes severe friction blisters, shear tears, and pressure sores over bony prominences.
- THE GOLDEN RULE - ALWAYS CHECK CSM: After applying ANY bandage, immediately check the Circulation (capillary refill < 2 secs), Sensation (can they feel you touching?), and Movement (can they wiggle their toes/fingers?) of the part beyond the bandage. Recheck rigorously after 15–30 minutes!
Objectives:
1. Mention the general physiological principles of bandaging.
2. Outline indications for bandaging.
3. Identify requirements for bandaging.
4. Prepare materials for bandaging.
5. Perform bandaging of various body parts flawlessly.
| No. | Rule | Rationale |
|---|---|---|
| 1. | Use a tightly rolled bandage of suitable width (narrow for fingers, wide for thighs) and appropriate material. | To promote neatness, prevent wrinkling, and ensure efficiency. |
| 2. | Always face the patient when bandaging limbs. | To constantly observe the patient's facial expression for wincing/signs of sudden pain indicating the bandage is too tight. |
| 3. | Hold the head (roll) of the bandage uppermost (facing you). | Allows the bandage to unroll naturally, applying even tension and pressure without dropping it. |
| 4. | Bandage the limb well aligned in its natural anatomical position. | To prevent long-term joint deformity, contractures, and extreme discomfort. |
| 5. | Hold the bandage in the right hand when bandaging a left limb and vice versa. | To promote ergonomic, correct bandaging technique. |
| 6. | Bandage the limb from inside outwards and from BELOW upwards, keeping the bandage even throughout. | Absolutely vital: Wrapping distal-to-proximal mechanically supports venous return and lymphatic drainage back to the heart, preventing distal pooling and severe oedema. |
| 7. | Ensure that the bandage is neither too tight nor too loose. | To prevent catastrophic interference with arterial circulation, while avoiding useless slippage. |
| 8. | Finish off the bandage with a straight circular turn, fold in the raw end, and secure it. Always avoid placing the pin over joints, bony prominences, or the actual site of injury. | To prevent localized pressure necrosis, irritation, and extreme discomfort when the patient rests. |
| 9. | Fasten with safety pins or with the provided elastic metal fastener. | To prevent unravelling and loosening of the compression. |
| 10. | Apply medical tape in psychiatric, mentally handicapped, or paediatric patients instead of metal pins or sharp clips. | Safety protocol to prevent severe injury (e.g., children swallowing pins or psychiatric patients using pins for self-harm). |
| Material Type | Clinical Description / Use |
|---|---|
| Cotton | Heavy weaves are strong and used for slings. Thin, porous ones form "open weave" bandages which are cheap, light, highly breathable, and disposable. Firmer cotton can be washed and autoclaved repeatedly. |
| Domette | This woven material with a slightly fluffed, soft surface makes a firm supporting bandage. It has mild resilience but provides robust, comfortable support for splints. |
| Flannel | Soft, warm strips. Historically used for dressing and padding rigid splints like the heavy metal Thomas splint. |
| Crepe | These bandages are highly elastic. The degree to which they are stretched when applied dictates the exact amount of hydrostatic pressure they exert. Widely used for compressing massive sprains and treating varicose veins. |
| Plaster (POP) | Plaster muslin is the fabric basis for making plaster of Paris (POP) rigid bandages. |
| Stockinet | A soft, seamless tubular cotton material. Applied directly to the skin beneath harsh fiberglass or plaster casts to protect the skin from friction and plaster burns. |
| Proprietary Tubular | Such as TubeGauze or Helodast. Applied with a special metal applicator for fast, seamless, perfectly even coverage over fingers and toes. |

| Step | Nursing Action | Rationale |
|---|---|---|
| 1. | Observe general rules of all nursing procedures (Hand hygiene, patient ID, explanation). | To maintain clinical standards. |
| 2. | Put patient in a comfortable position, fully exposing the affected joint. | To promote comfort, assess baseline circulation, and prevent deformity. |
| 3. | Hold bandage with the roll (drum) facing upwards in your hand. | Allows smooth unrolling and application of even tension/pressure. |
| 4. | Wrap the bandage around the limb twice (fixing turns) distally (below) the joint. | To securely anchor and stabilize the bandage and provide a firm starting base. |
| 5. | Use alternating ascending and descending diagonal turns across the joint to form a continuous "figure of eight". Overlap each turn of the bandage by one-half to two-thirds the width of the strip. | Provides dynamic, flexible support that allows joint mobility while maintaining strict compression. Overlapping promotes firmness and aesthetic neatness. |
| 6. | Wrap the bandage around the limb twice, proximally (above) the joint to anchor the final tail and secure with a clip, tape, or safety pin. | Locks the entire structural weave in place. |
| 7. | Elevate the newly bandaged extremity for 15 to 30 minutes after application. | Gravity assists venous return, working with the compression to rapidly reduce oedema and throbbing pain. |
| 8. | Assess the skin beyond the bandage for colour, integrity, pain, and temperature (CSM Check). | To detect deadly complications (like blocked arterial circulation or nerve compression) extremely early. |
| 9. | Leave the patient comfortable, clean away the trolley, and document. | Maintain standards and legal records. |
Used when simple circular turns would leave gaping gaps due to anatomy.
- Make a fixing (anchor) turn firmly around the forehead/head.
- Bring the bandage diagonally under the affected ear, pulling it straight over the head and down the back, deliberately leaving the normal, healthy ear un-bandaged for hearing and comfort.
- Repeat these diagonal turns three or four times, overlapping each by 2/3, until the thick dressing on the affected ear is gradually and completely covered.
- Finish with a final circular fixing turn and secure the bandage at the centre of the forehead (where the patient isn't resting their head) using a safety pin, clip, or medical tape.

This pattern weaves away from the centre, accommodating extreme angles.
- Make two locking anchor turns directly over the exact centre (apex) of the bent joint (e.g., right over the point of the elbow or kneecap). (Rationale: To instantly stabilize the dressing at the point of highest tension).
- Now make alternate figure-of-8 turns spreading outwards: one turn above the joint, then the next turn below the joint, diverging further outward each time. This forms a perfect, snug basket-weave pattern at each side of the joint without bunching up in the crease.
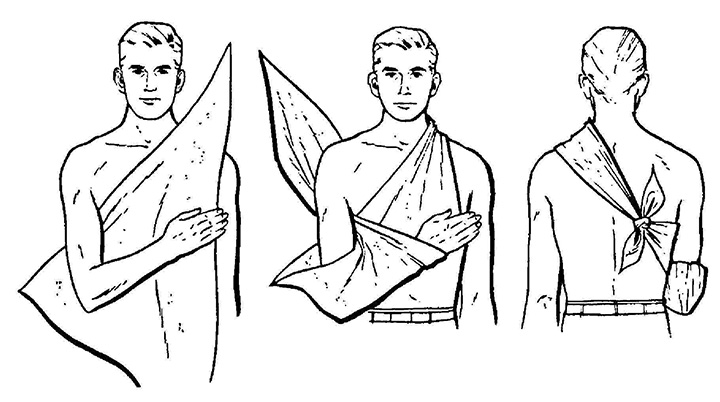
The ultimate first-aid tool for stabilizing upper extremity fractures.
- Place the injured arm gently across the patient's chest so that the fingers are elevated and almost touching the opposite (healthy) shoulder. (Rationale: To physically mobilise the fracture, reduce muscle spasm, and relieve severe pain).
- Slide the unfolded triangular bandage between the chest and the injured arm. Place one upper corner over the uninjured shoulder, letting the right-angled corner (the point) stick out just beyond the elbow on the injured side.
- Bring the bottom corner up over the injured forearm, carrying it over the injured shoulder.
- Carry both corner ends around the back of the neck and tie the ends securely with a reef knot (square knot). The knot MUST lie in the fleshy hollow just above the clavicle on the UNINJURED side. (Rationale: Never tie a knot directly on the cervical spine/neck bone; the weight of the arm will cause excruciating pressure and nerve damage).
- The protruding right-angle point at the elbow is neatly folded forward and pinned securely to the front of the sling to enclose the elbow tightly in a pocket. (Rationale: To prevent the elbow from sliding out and prevent raw edge skin irritation).
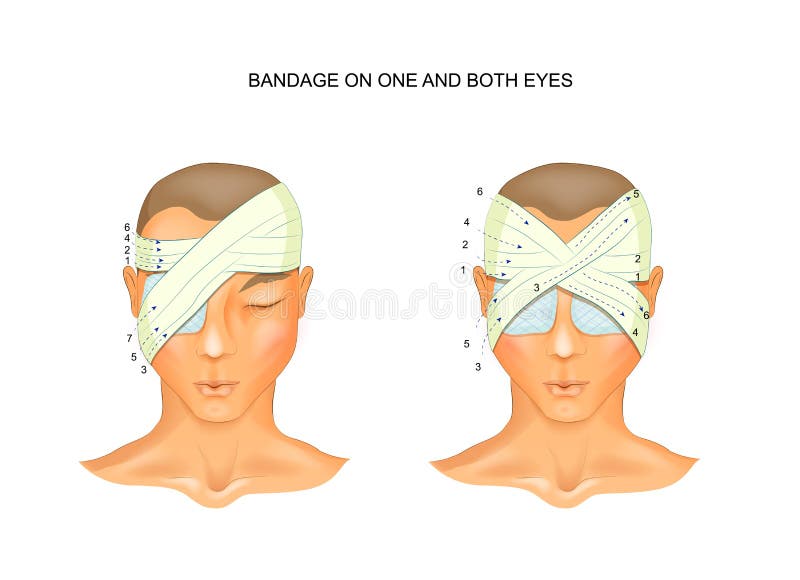
- Facing the patient, hold the sterile eye pad firmly in position over the affected eye until the first turn of the bandage locks it. (Rationale: To secure the dressing and maintain gentle pressure).
- Begin from the affected side, pulling toward the normal side. Go across the forehead and round the head in a circular fixing turn.
- From the back of the head, bring the bandage under the ear on the affected side, diagonally up across the cheek, covering the lower (nasal) side of the eye pad, and pull it straight over the top of the head and down the back.
- The next turn repeats this, but comes slightly higher, overlapping the first eye turn by 2/3. It crosses the fixing turn at the exact same point above the ear, covers the rest of the pad, and comes round to the front.
- Fix a safety pin or tape safely in the centre of the forehead.

- Position the patient comfortably in a sitting up position and stand directly behind them.
- Place the centre of the outer surface of the bandage precisely in the centre of the forehead/head.
- Bring both heads of the bandage round the sides, over the temples, and strictly above the ears to the nape of the neck where the ends cross over each other. (Rationale: Ensure that the delicate cartilage of the ear is not caught or folded over).
- Bring one bandage horizontally around the head (the locking band), while the other bandage is pulled vertically over the centre of the top of the scalp (the dome) down to the root of the nose.
- Bring the horizontal locking bandage over the forehead, pinning down the vertical bandage. The vertical bandage is then flipped back over the head to the nape of the neck.
- Ensure that each vertical turn across the scalp overlaps 2/3 of the previous turn. (Rationale: Ensures the bandage adheres snugly to the spherical shape of the skull without slipping).
- Cross it again at the back, lock it with the horizontal bandage, and bring it forward over the scalp to the opposite side of the midline.
- Repeat these alternating backward and forward turns to the left and right of the centre until the entire scalp is completely woven and covered.
- Take two final, tight circular turns entirely around the head with the horizontal bandage to lock all the pleats, and secure with a safety pin or tape.

- Apply longitudinal strips back and forth over the end of the stump. Overlap each layer by half to two-thirds the width. Wrap firmly to shape the stump, but not tightly enough to cause ischemia. Ask the patient frequently if they feel any numbness, tingling, loose skin rubbing, tightening, aching, or throbbing pain.
- Stand directly facing the patient and take a circular fixing turn around the base of the stump. (Rationale: To constantly observe their facial expression for signs of hidden pain).
- Fold the bandage forward across the front of the stump at a 45° angle, fold it over the blind end, and bring it backwards. Lock it in place by crossing the first circular turn at a right angle.
- Repeat these recurrent, folding turns—locking each one with a circular turn—until the stump is fully enclosed and protected.
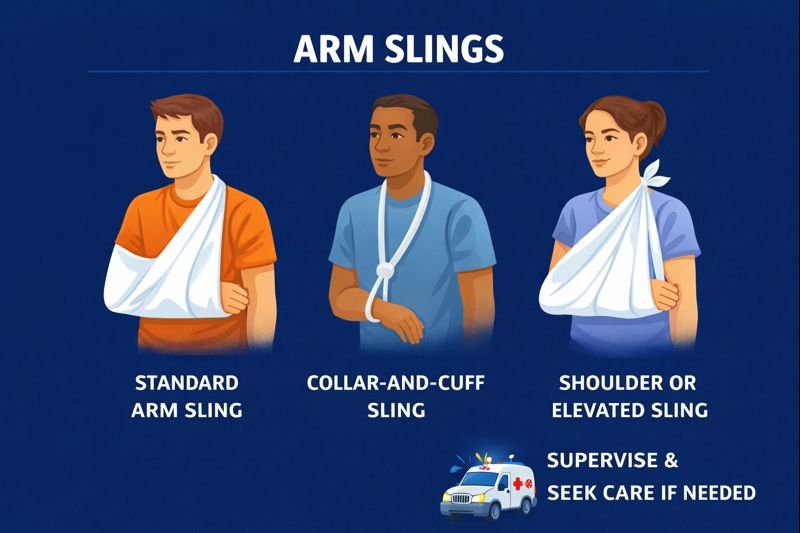
You must know the specific indications for each sling type for clinical scenarios:
- Triangular arm sling (Broad Arm Sling): Supports the entire weight of the forearm and the wrist horizontally. Used primarily for fractures of the radius/ulna (forearm) or wrist sprains.
- High arm (Elevation) sling: The arm is folded tightly and elevated high against the opposite chest wall, with the fingers pointing to the collarbone. Used to drastically reduce severe swelling of the hand/wrist post-injury, and to use gravity to control severe arterial bleeding from the arm.
- Collar-and-cuff sling: A simple loop of material forming a clove hitch around the wrist, suspended from the neck. It supports ONLY the wrist. Used specifically for fractures of the upper arm (humerus), shoulder, or clavicle. Rationale: It allows the heavy humerus bone to hang vertically by gravity, pulling the broken bone ends into perfect, natural alignment without needing a heavy cast.
- A Splint is any rigid or flexible device used to immobilise, structurally support, and protect an injured part of the musculoskeletal system (such as a bone fracture, joint dislocation, or severe tendon/ligament sprain) or to forcefully maintain a body part in correct anatomical alignment during the long healing process.
- Splinting is the precise clinical act of applying this device safely.
Why is splinting a life-saving first aid skill?
- To strictly immobilise unstable fractures and dislocations. Rationale: Broken bone ends are as sharp as razor blades. If they move, they will slice through nearby major nerves and deadly arteries (converting a closed fracture into a massive internal hemorrhage).
- To drastically relieve excruciating pain and instantly reduce severe, damaging muscle spasms around the break.
- To prevent or mechanically correct severe deformity, maintaining proper alignment during bone healing (callus formation).
- To support massively injured soft tissues (severe Grade III sprains and muscle tears).
- To secure and protect life-saving dressings and IV lines inserted on agitated patients' limbs.
- To allow the safe, pain-free, and shock-preventing transport of the injured casualty from the field to the hospital.

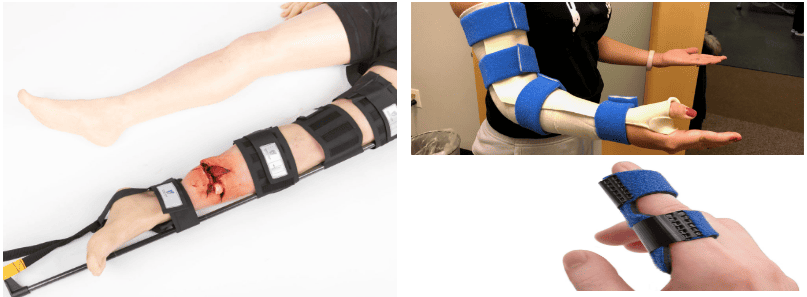
- Rigid splints: Made of wood, solid metal, hard plastic, or stiff cardboard. Rule: They must be physically long enough to completely immobilise the joint ABOVE and the joint BELOW the fracture.
- Soft splints: Using a thick pillow wrapped around an ankle, a heavy blanket roll, or a simple arm sling tied to the torso. Used for minor/stable injuries.
- Traction splints (e.g., The Thomas Splint): Used specifically and exclusively for mid-shaft Femur (thigh) fractures. The thigh muscles are massive; when the femur breaks, the muscles spasm and pull the bone ends over each other, causing massive internal bleeding (up to 1.5 Liters!). The traction splint applies continuous, powerful mechanical pulling (traction) to realign the massive bone, stopping the spasm and saving the leg.
- Plaster of Paris (POP) casts / slabs: Used definitively in hospitals for long-term (6-8 weeks) rigid immobilisation while the bone fuses.
- Air (pneumatic) splints: Inflatable, clear plastic sleeves commonly used in modern ambulance/field rescue. They provide uniform 360-degree compression to stop bleeding and immobilize simultaneously.
If you fail to follow these golden rules in the field, you can cause permanent paralysis, massive bleeding, or forced amputation:
- Always assess the casualty's ABCs first (DRABC) and definitively control severe, spurting arterial bleeding before attempting to apply a splint.
- Splint the limb in the EXACT position it was found. NEVER, ever attempt to forcefully straighten or realign a severe fracture or dislocation in the field. You will sever the artery. Let the ER doctors do it under X-ray.
- Always immobilise the joint strictly above and the joint strictly below the fracture site. (e.g., For a shin/tibia fracture, you must lock both the knee and the ankle).
- Pad the rigid splint extremely well with cotton or clothing, especially around bony prominences (ankles, knees). Secure it with bandages tightly above and below the fracture site — never tie a constricting knot directly over the broken bone.
- Always expose the tips of the fingers or toes. Check CSM (Circulation, Sensation, Movement) before applying the splint, AND immediately after tying it. Recheck every 15 minutes!
- The splint must be mechanically snug, but never tight enough to act as a tourniquet and cut off blood flow.
- Elevate the shattered limb after splinting, treat the patient for systemic hemorrhagic shock (keep them warm, lie them flat), and arrange urgent surgical referral.
This is an absolute orthopaedic emergency. It occurs when a bone breaks, causing massive internal bleeding and swelling inside a rigid, non-expanding muscle compartment (or inside a tight POP cast/bandage). The pressure builds until it crushes and collapses the arteries and veins. Muscle tissue and nerves begin to die (necrosis) within 4-6 hours, leading to irreversible paralysis and amputation.
You must continuously check the "6 Ps" of arterial ischemia:
- 1. Pain: Severe, relentless, out of proportion to the injury, and agonizingly worse on passive stretching of the toes/fingers.
- 2. Pallor: The skin becomes pale, white, and completely drained of blood.
- 3. Paresthesia: Numbness, tingling, or "pins and needles" (the nerves are screaming as they die).
- 4. Paralysis: The patient is completely unable to move the fingers/toes.
- 5. Pulselessness: No palpable pulse beyond the cast (a very late, ominous sign).
- 6. Poikilothermia: The limb feels ice cold to the touch compared to the rest of the body.
Action: This is a massive EMERGENCY. The cast or tight bandage must be split down the middle (bivalved) or removed entirely immediately! If pressure doesn't drop, the surgeon must perform an emergency fasciotomy (slicing the leg open to relieve pressure).
- While the plaster dries (The critical first 24–48 hours): A wet cast is fragile. Handle it using the flat palms of your hands only! Using your fingertips will create inward dents in the wet plaster; when it dries hard as rock, these dents will press into the patient's skin, cutting off blood supply and causing deep, rotting pressure sores. Support the wet cast on soft, plastic-covered pillows. Keep it completely uncovered and exposed to room air to facilitate rapid drying. Use a bed cradle (a metal cage) to keep the heavy weight of bedclothes off a wet leg plaster.
- After drying: Keep the plaster strictly clean and dry. (Cover it with a plastic bag when washing/sponging the patient, but do not leave the plastic enclosed long-term, or the trapped sweat will macerate the skin). Keep the hard edges of the cast smooth and heavily padded with adhesive tape (petaling) to prevent it from slicing into the skin.
- Neurovascular observations (CSM): As the nurse, you must constantly, obsessively check the colour, warmth, capillary refill, pulses, sensation, and movement of the exposed fingers/toes. Always compare them directly with the uninjured, normal limb. Report coldness, blueness (cyanosis), massive swelling, numbness, or severe unremitting pain immediately!
- Elevate: Keep the casted limb elevated high on pillows above the level of the heart for the first 24–48 hours. Gravity is your best friend to drastically reduce massive inflammatory swelling.
- Exercises: Forcefully encourage the patient to actively and frequently move their fingers/toes and the joints that are NOT locked inside the cast. Rationale: This prevents severe joint stiffness, muscle atrophy, and promotes venous return, preventing deadly Deep Vein Thrombosis (DVT) blood clots.
- The "Itch" Warning: Warn the patient to never, ever insert foreign objects (like rulers, knitting needles, or pens) deep inside a cast to scratch a maddening itch. It breaks the fragile, unseen skin, introduces bacteria, and causes horrific hidden, rotting staph infections under the plaster.
Objectives:
1. Identify the exact clinical requirements used for preparing and applying orthopaedic POP splints.
2. Demonstrate the application of an orthopaedic splint correctly and safely.
| Top Shelf (Application Tools) | Bottom Shelf (Heavy/Cutting Tools) | At the Bed Side (Cleanup) |
|---|---|---|
|
• Basin of warm water (Speeds up the exothermic hardening reaction). • A tray of dry plaster (POP) bandages of various widths. • Skin marking pencil, bandage scissors, and thick orthopaedic cotton wool (Webril) for padding. • Stockinet (tubular cotton to protect the skin). • Tape measure (to accurately measure the slab length). |
• Long protective mackintoshes (for the bed). • Plastic mackintosh (for the nurse). • Heavy-duty Plaster Shears (for cutting or modifying hardened casts). • Crepe rolled bandages (to secure the wet slab to the limb). • Used/dirty dressing container. |
• A separate basin of warm water. • Flannel washcloth, towel, and mild soap. (Crucial Rationale: This must be kept purely for scrubbing and cleaning pieces of wet plaster splashes off the patient's delicate skin immediately after application, before it sets like concrete into their arm hair). |
- Understand the chemistry: Plaster sets (hardens) in just a few minutes due to an exothermic chemical reaction (it gets very warm), but it takes several hours to up to 48 hours to dry completely and reach maximum structural strength.
- To assist the splint in maintaining the exact correct anatomical position, allow absolutely nothing hard to press against a wet plaster (e.g., resting it on the metal bed frame, a chair edge, or a cradle). Keep the rest of the patient's body warm with blankets to prevent systemic chilling from the wet, evaporating cast.
- Leave the new plaster completely exposed to the circulating room air, supported gently on soft, yielding pillows if necessary.
- For a massive leg plaster, a bed cradle should be used to suspend the heavy, warm bed clothes off the wet cast, allowing air flow and preventing deformation.
- The patient should receive a thorough, soapy bath of the limb before the plaster is applied to remove oils and dead skin; fingernails should also be cut very short to prevent the patient from blindly scratching inside the cast and causing infection.
- The fingernails must be completely clean, and absolutely no plaster splash should be left dried on them. (Rationale: Plaster stuck on nails makes it physically impossible for nurses to accurately check capillary refill and assess life-saving circulation).
- The fingers and toes should feel subjectively warm to the patient and be completely free to move voluntarily.
- REPORT IMMEDIATELY to the surgeon if the fingers become ice cold, pale, or blue (cyanotic) in colour! This is an active compartment syndrome.
- The patient should be able to move their fingers and toes freely without agony, and neurological sensation (sharp vs dull touch) should be tested regularly to ascertain that the neurovascular circulation is perfectly satisfactory and the cast is not crushing a major nerve (like the radial or peroneal nerve).
- Note: Content required for references was not provided in the source text.