Nurses Revision

nursesrevision@gmail.com

ANTIFUNGAL AGENTS

ANTIFUNGAL AGENTS

ANTIFUNGAL AGENTS

SECTION 1: INTRODUCTION TO FUNGI & FUNGAL INFECTIONS

1.1 What Are Fungi?

Fungi are living organisms that are different from bacteria and viruses. Think of them as tiny plants that cannot make their own food (they are not green like plants because they lack chlorophyll).

Key Characteristics of Fungi:

  • They have a cell wall made of chitin (a tough material, like the shell of a crab).
  • Their cell membrane contains ergosterol (this is VERY important — most antifungal drugs target this!).
  • They can be yeasts (single-celled, like Candida) or molds (multicellular, like Aspergillus).
  • They reproduce by making spores that float in the air.
💡 EXAM TIP & PHYSIOLOGY EXPANSION
Fungi are eukaryotes (just like human cells), which makes them much harder to kill than bacteria (which are prokaryotes) without accidentally hurting human cells. Because fungal cells and human cells share similar biological machinery, finding "selective toxicity" is difficult. This is exactly why antifungal drugs often have more severe side effects than standard antibiotics!

1.2 What Is a Mycosis?

A mycosis is simply the medical word for a fungal infection. "Myco" means fungus, and "-osis" means disease or condition.

Types of Mycoses:

  • Superficial mycoses: Affect only the outer layers of skin, hair, or nails. Examples: ringworm (tinea), athlete's foot, jock itch.
  • Cutaneous mycoses: Deeper into the skin. Examples: tinea capitis (scalp ringworm), tinea corporis (body ringworm).
  • Subcutaneous mycoses: Under the skin, often after injury. Example: mycetoma (Madura foot — commonly seen in Africa!).
  • Systemic mycoses: Spread throughout the body via the bloodstream, affecting internal organs. Examples: cryptococcal meningitis, histoplasmosis, invasive aspergillosis.
  • Opportunistic mycoses: Occur strictly when the immune system is weak. Examples: oral thrush, esophageal candidiasis, Pneumocystis pneumonia.

1.3 Why Are Fungal Infections Common in Uganda?

According to recent research, approximately 9% of Ugandans (about 4 million people) are affected by serious fungal diseases annually.

Major Risk Factors in Ugandan Communities:

  • HIV/AIDS: Weakens the immune system (depletes CD4 T-cells), allowing opportunistic fungi to grow unchecked.
  • Tuberculosis (TB): Especially after TB treatment, the residual lung cavities are perfect breeding grounds for Chronic pulmonary aspergillosis (Aspergillomas or "fungus balls").
  • Malnutrition: Poor nutrition fundamentally weakens cellular immunity.
  • Diabetes mellitus: High blood sugar feeds fungi (especially Candida, which thrives in glucose-rich environments).
  • Cancer and chemotherapy: Treatment destroys white blood cells (neutropenia), severely weakening the immune system.
  • Overcrowding: Spreads fungal skin infections like tinea capitis rapidly in schools.
  • Poor sanitation: Increases exposure to environmental fungal spores in soil and decaying organic matter.
  • Limited access to diagnostics: Many fungal infections go undiagnosed or are misdiagnosed as bacterial infections.
Common InfectionAffected PopulationEstimated Annual Cases (Uganda)
Tinea capitis (scalp ringworm)School children~3 million
Oral candidiasis (thrush)HIV-positive adults~29,000
Esophageal candidiasisHIV-positive adults~75,000
Cryptococcal meningitisHIV-positive adults~5,500
Pneumocystis pneumoniaHIV-positive adults & children~6,700
Chronic pulmonary aspergillosisPost-TB patients~63,000
Recurrent vaginal candidiasisWomen of reproductive age~656,000

SECTION 2: OVERVIEW OF ANTIFUNGAL AGENTS

2.1 What Are Antifungal Agents?

Antifungal agents are medicines that kill fungi or stop them from growing. They are a specific type of antimicrobial (like antibiotics, but designed exclusively for fungi instead of bacteria).

2.2 How Are They Different from Antibiotics?

FeatureAntibiotics (for bacteria)Antifungals (for fungi)
Target cell wallPeptidoglycanChitin and glucan
Target cell membraneNo sterol targetErgosterol
Selective toxicityEasier (bacteria are very different from human cells)Harder (fungi are eukaryotes just like human cells)
Side effectsGenerally fewerMore common and often much more severe
Duration of treatmentUsually days to weeksOften weeks to months or even years!

2.3 Routes of Administration

  • Topical: Applied to the skin, nails, or mucous membranes (Creams, ointments, gels, powders, sprays, shampoos, vaginal suppositories, troches/lozenges).
  • Oral: Swallowed as pills, capsules, or liquids.
  • Intravenous (IV): Given directly into the vein. Used for serious, life-threatening systemic infections.
  • Intrathecal: Injected directly into the spinal fluid (rare, reserved for severe refractory meningitis).

2.4 Fungistatic vs. Fungicidal

  • Fungistatic: Stops the fungus from growing and reproducing, but does NOT kill it. The body's immune system must finish the job. (Examples: azoles, flucytosine).
  • Fungicidal: Actually KILLS the fungus directly. (Examples: amphotericin B, echinocandins, allylamines).
💡 EXAM TIP
In severely immunocompromised patients (like those with advanced HIV/AIDS or neutropenia), fungicidal drugs are strongly preferred because their immune system is simply too weak to clear an infection that is only suppressed by a fungistatic drug.
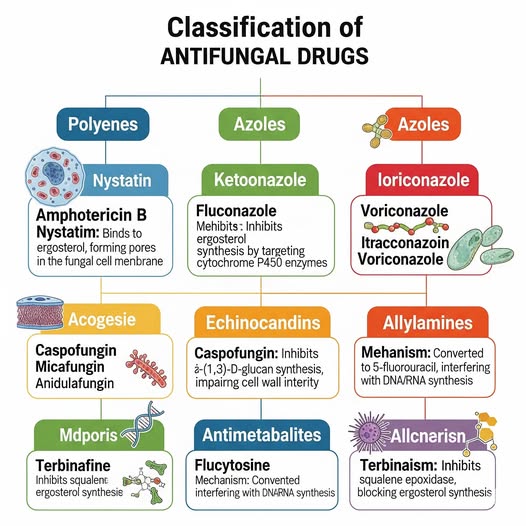
SECTION 3: CLASSIFICATION OF ANTIFUNGAL AGENTS

THE BIG FIVE CLASSES:

  1. AZOLES (The "-conazoles")
    • Systemic: Fluconazole, Itraconazole, Ketoconazole, Voriconazole, Posaconazole, Isavuconazole.
    • Topical: Clotrimazole, Miconazole, Econazole, Oxiconazole, Tioconazole, Sertaconazole, Butoconazole, Terconazole.
  2. POLYENES (The "-tatin" and "-ricin" group)
    • Amphotericin B, Nystatin.
  3. ECHINOCANDINS (The "-fungin" group)
    • Caspofungin, Micafungin, Anidulafungin.
  4. ALLYLAMINES (The "-fine" group)
    • Terbinafine, Naftifine.
  5. MISCELLANEOUS AGENTS
    • Flucytosine (5-FC), Griseofulvin, Ciclopirox, Tolnaftate, Undecylenic acid, Gentian violet.

SECTION 4: DETAILED DRUG CLASS PROFILES

CLASS 1: AZOLE ANTIFUNGALS

4.1.1 Overview

Azoles are the most commonly used antifungal drugs. They work by interfering with the fungal cell membrane. They can be used for both superficial (skin, nails, vagina) and systemic (blood, organs, brain) infections.

4.1.2 Mechanism of Action (MOA) — DETAILED

  • Normal Fungal Cell Membrane: The fungal cell membrane is like a flexible bag that holds the cell together. It is made of phospholipids and ergosterol. Ergosterol is like the "reinforcement bars" that keep the membrane strong and flexible.
  • The Enzyme Target: Fungi make ergosterol using an enzyme called 14α-demethylase. This enzyme belongs to the cytochrome P450 (CYP450) family — specifically CYP51A1.
  • What Azoles Do: Azoles have a nitrogen atom in their chemical structure. This nitrogen binds directly to the heme iron in the CYP450 enzyme, effectively blocking it.
  • The Result:
    • Ergosterol cannot be made → the fungal cell membrane becomes weak and leaky.
    • Toxic sterol precursors build up inside the fungus → these are poisonous to the fungus.
    • The membrane loses its shape and function. Essential molecules leak out of the cell.
    • The fungus cannot grow or reproduce (fungistatic effect).
🧠 MNEMONIC: "AZOLES BLOCK THE HOLES"
Azoles
Zap the enzyme (14α-demethylase)
Obstruct ergosterol synthesis
Leak the membrane
Eradicate the fungus
Stop reproduction

(Note: Azoles are fungistatic, meaning they stop growth rather than kill. However, at very high concentrations, some azoles can become fungicidal).

4.1.3 Subclasses of Azoles

  • A. Imidazoles (older, more side effects): Ketoconazole (rarely used systemically now due to severe liver toxicity), Miconazole (topical), Clotrimazole (topical), Econazole (topical).
  • B. Triazoles (newer, safer, better tolerated): Fluconazole (great for Candida/Cryptococcus, crosses BBB), Itraconazole (broad, aspergillosis), Voriconazole (first-line for invasive aspergillosis), Posaconazole (broadest, prophylaxis), Isavuconazole (mucormycosis).

4.1.4 Individual Azole Profiles

FLUCONAZOLE (Diflucan)

  • Category: Triazole — Systemic and topical
  • Spectrum of Activity: Excellent against Candida species; Good against Cryptococcus neoformans (meningitis); Some activity against dermatophytes.
  • Clinical Uses:
    • Vaginal candidiasis — single 150mg oral dose or topical cream.
    • Oropharyngeal / Esophageal candidiasis — common in HIV patients.
    • Cryptococcal meningitis — induction and maintenance therapy (with amphotericin B).
    • Prophylaxis — prevents fungal infections in transplant/neutropenic patients.
  • Pharmacokinetics: Well absorbed orally (90%); Widely distributed, crosses blood-brain barrier (crucial for meningitis!); Long half-life (30 hours) allowing once-daily dosing. Excreted via Kidneys (urine).
  • Exam Tip: Because fluconazole is heavily excreted by the kidneys, the dose MUST be reduced in patients with kidney disease!
  • Adverse Effects: Nausea, vomiting, diarrhea; Headache; Hepatotoxicity (liver damage - monitor AST/ALT); Rash; QT prolongation (heart rhythm problem).
  • Drug Interactions (VERY IMPORTANT!): Fluconazole inhibits CYP2C9.
    • Warfarin: INCREASES bleeding risk!
    • Phenytoin: Increases phenytoin levels (toxicity).
    • Oral hypoglycemics: Can cause dangerous low blood sugar.
    • Statins: Increases risk of muscle damage (rhabdomyolysis).

ITRACONAZOLE (Sporanox)

  • Category: Triazole — Systemic
  • Spectrum/Uses: Broad spectrum. Used for Onychomycosis (nail fungus), severe Tinea infections, Aspergillosis, and endemic fungi (Histoplasmosis, Blastomycosis).
  • Pharmacokinetics (Crucial Nursing Point): Absorption is variable and poor—it REQUIRES an acidic stomach for absorption. Take with food or an acidic drink (like Coca-Cola!). Do NOT give with antacids, H2 blockers, or PPIs (omeprazole).
  • Adverse Effects: Hepatotoxicity; Congestive Heart Failure (can worsen heart function - ABSOLUTELY check for CHF history before giving!); Hypokalemia; Peripheral edema.

KETOCONAZOLE (Nizoral)

  • Category: Imidazole (Mostly Topical now).
  • WARNING: Systemic ketoconazole has been largely replaced by safer azoles due to high risk of severe liver toxicity and adrenal suppression.
  • Clinical Uses: Seborrheic dermatitis, Tinea infections, Dandruff (shampoo form).
  • Systemic Adverse Effects (If used): Severe hepatotoxicity, Adrenal suppression (reduces cortisol), Gynecomastia (breast enlargement in men due to anti-androgen effects), impotence.

VORICONAZOLE (Vfend)

  • Category: Triazole — Systemic (IV and oral).
  • Clinical Uses: FIRST-LINE treatment for Invasive Aspergillosis. Also used for serious Candida infections resistant to fluconazole.
  • Adverse Effects:
    • Visual disturbances: VERY COMMON! Blurred vision, altered color perception, photophobia. (Exam Tip: "Vfend affects your Vision!")
    • Hepatotoxicity; Skin reactions (photosensitivity); Hallucinations; QT prolongation.
  • Nursing Considerations: Advise patient to avoid bright sunlight, wear sunglasses and sunscreen. Monitor vision and liver function.

POSACONAZOLE (Noxafil)

  • Category: Triazole — Systemic.
  • Spectrum: Broadest spectrum. Active against Mucorales (causes mucormycosis — the "black fungus").
  • Pharmacokinetics: Absorption is highly variable — MUST be taken with a high-fat meal (increases absorption 4-fold!).

CLOTRIMAZOLE & MICONAZOLE

  • Category: Imidazole — TOPICAL / VAGINAL.
  • Uses: Tinea infections (athlete's foot), Vaginal candidiasis, Oral thrush (troches/lozenges).
  • Nursing Considerations: For vaginal use, advise patient to remain lying down for 10-15 minutes after insertion. For oral troches, dissolve slowly in mouth (do not chew) and do not eat/drink for 30 minutes after. Complete full course!

4.1.5 Azole Adverse Effects — Summary Table

Adverse EffectWhich Azoles?Nursing Action
HepatotoxicityALL, especially ketoconazoleMonitor LFTs (AST, ALT, bilirubin)
GI upsetALLGive with food, small frequent meals
QT prolongationFluconazole, voriconazole, posaconazole, itraconazoleMonitor ECG, electrolytes
Visual disturbancesVoriconazoleWarn patient, advise sunglasses
Adrenal suppression / Hormone effectsKetoconazoleMonitor cortisol levels. Watch for gynecomastia, menstrual changes
Drug interactionsALL (CYP450 inhibition)Complete medication review

Azoles: Common Drugs, Indications, Dosages, Contraindications, and Side Effects

DrugCommon IndicationsTypical Dosages (Adult)ContraindicationsMajor Side Effects
FluconazoleVulvovaginal candidiasis, Oropharyngeal candidiasis, Cryptococcal meningitis150 mg PO (single dose for vaginal); 200-400 mg/day PO/IV for systemicPregnancy (systemic use), Co-administration with drugs known to prolong QT intervalHepatotoxicity, QT prolongation, GI upset, Rash
ItraconazoleOnychomycosis, Histoplasmosis, Aspergillosis200 mg PO daily or BID (Take with food/acidic drink)History of Heart Failure (CHF), Ventricular dysfunctionCHF exacerbation, Hepatotoxicity, Hypokalemia, Edema
VoriconazoleInvasive Aspergillosis, Severe Candidiasis6 mg/kg IV q12h (loading), then 4 mg/kg IV q12hCo-administration with potent CYP3A4 substrates, PregnancyVisual disturbances, Photosensitivity, Hepatotoxicity, Hallucinations
ClotrimazoleTinea pedis, Vaginal candidiasis, Oral thrushTopical: apply BID; Troche: 10 mg 5 times/dayHypersensitivityLocal skin irritation, erythema, mild burning

CLASS 2: POLYENE ANTIFUNGALS

4.2.1 Overview

Polyenes are older but extremely powerful antifungal drugs. They work by binding directly to ergosterol in the fungal cell membrane and creating holes (pores) that leak the cell contents. They are rapidly fungicidal.

4.2.2 Mechanism of Action (MOA) — DETAILED

  • Structure: Amphotericin B is a large molecule shaped like a rod with a hydrophilic (water-loving) end and a hydrophobic (fat-loving) end.
  • Binding to Ergosterol: The hydrophobic end inserts directly into the fungal cell membrane and binds to ergosterol molecules.
  • Pore Formation: Multiple amphotericin B molecules join together end-to-end to form a channel or pore right through the membrane.
  • Cell Death: This pore allows massive amounts of potassium, magnesium, and other essential ions to leak out of the fungal cell. The cell loses its internal balance and dies instantly.
💡 PHYSIOLOGY EXPANSION: Why is it so toxic to humans?
Polyenes target ergosterol in fungi. However, human cell membranes contain a very similar molecule called cholesterol. While Amphotericin B prefers ergosterol, it *also* binds to human cholesterol (especially in the kidneys), tearing similar holes in human cells. This is the physiological basis for its severe toxicity!
🧠 MNEMONIC: "POLYENES PUNCH HOLES"
Polyenes
Open pores in membrane
Leak potassium out
Yeast and molds die
Ergosterol is the target
No resistance develops easily
Effective but toxic
Serious infections only

4.2.3 Individual Polyene Profiles

AMPHOTERICIN B (Fungizone, AmBisome)

  • Category: Polyene — Systemic (IV only)
  • ⚠️ NICKNAME: "Ampho-Terrible" because of its severe, guaranteed side effects!
  • Spectrum: Broadest spectrum of all antifungals. Used for severe, life-threatening systemic infections (Cryptococcal meningitis induction, severe systemic candidiasis, mucormycosis).
  • Formulations:
    • Deoxycholate (Fungizone): Original, most nephrotoxic, least expensive.
    • Liposomal (AmBisome): Encapsulated in lipids, targets the fungus better while sparing human kidneys. Least nephrotoxic, but highly expensive. Preferred if patient already has kidney failure.
Adverse Effects — THE BIG ONES:
  1. NEPHROTOXICITY (Kidney Damage) — MOST IMPORTANT!
    • Occurs in up to 80% of patients. It causes renal vasoconstriction and direct tubular toxicity, leading to Electrolyte wasting (losing Potassium and Magnesium).
    • NURSING MANAGEMENT:
      • Obtain baseline renal function (Creatinine, BUN) and monitor daily.
      • SODIUM LOADING: Give 500-1000 mL of Normal Saline IV before each dose to flush and protect the kidneys!
      • Monitor and aggressively replace Potassium and Magnesium. Avoid other nephrotoxic drugs (gentamicin, NSAIDs).
  2. INFUSION-RELATED REACTIONS ("Shake and Bake")
    • Fever, chills, rigors (severe shaking), hypotension, bronchospasm occurring 1-3 hours into infusion.
    • NURSING MANAGEMENT:
      • Premedicate 30-60 mins before infusion with Acetaminophen (fever), Diphenhydramine (allergic symptoms), and Hydrocortisone (inflammation).
      • Meperidine (pethidine) can be used to stop the rigors.
      • Infuse SLOWLY over 4-6 hours.
  3. ANEMIA & THROMBOPHLEBITIS
    • Suppresses erythropoietin production (monitor hemoglobin/hematocrit).
    • Highly irritating to veins. Use a central line if possible, or rotate peripheral IV sites frequently.

NYSTATIN (Mycostatin)

  • Category: Polyene — TOPICAL and ORAL (but it is NOT absorbed systemically!)
  • Spectrum: Active against Candida species only.
  • Clinical Uses: Oral candidiasis (thrush) via oral suspension; Intestinal/Vaginal candidiasis.
  • Nursing Considerations:
    • Because it is not absorbed into the blood, it acts strictly locally.
    • For oral suspension: Instruct patient to swish for as long as possible before swallowing (to coat the esophagus) or spitting.
    • Continue for 48 hours AFTER symptoms resolve to prevent recurrence.
🧠 MNEMONIC: "NYSTATIN STAYS IN"
Nystatin
Yeast in mouth or gut
Swish and swallow (or spit)
Topical only (not systemic)
Active against Candida
Treat thrush effectively
Inexpensive and safe
No absorption into blood
❓ APPLIED KNOWLEDGE CHECK
Question: A patient with systemic, blood-borne Candida albicans is prescribed Nystatin oral suspension. What is the critical error here?
Answer: Nystatin is absolutely NOT absorbed from the GI tract. If the patient swallows it, it will travel through the gut and exit in the feces without a single drop ever entering the bloodstream. Systemic candidemia requires IV Amphotericin B, IV Echinocandins, or systemic Azoles (like Fluconazole).

Polyenes: Common Drugs, Indications, Dosages, Contraindications, and Side Effects

DrugCommon IndicationsTypical Dosages (Adult)ContraindicationsMajor Side Effects
Amphotericin BSevere systemic fungal infections (Cryptococcal meningitis, mucormycosis)0.5-1.5 mg/kg/day IV (Deoxycholate formulation); 3-5 mg/kg/day IV (Liposomal formulation)Severe HypersensitivityNephrotoxicity, Severe hypokalemia/hypomagnesemia, Infusion reactions ("Shake and Bake"), Anemia, Phlebitis
NystatinOral thrush, cutaneous and vaginal candidiasis400,000-600,000 units oral suspension QID (swish and swallow)HypersensitivityGI upset (nausea, vomiting, diarrhea if swallowed), local skin irritation

CLASS 3: ECHINOCANDIN ANTIFUNGALS

4.3.1 Overview

Echinocandins are the newest class of antifungal drugs. They are uniquely safe with very few drug interactions and extremely low toxicity. They are fungicidal against Candida and fungistatic against Aspergillus.

4.3.2 Mechanism of Action (MOA) — DETAILED

  • Fungal Cell Wall: Fungi have a rigid outer cell wall made of glucan, chitin, and mannoproteins. This wall gives the fungus its shape and protects it from bursting.
  • β-(1,3)-D-Glucan: This is a long chain of sugar molecules that forms the structural backbone of the fungal cell wall.
  • The Enzyme Target: Fungi make β-(1,3)-D-glucan using an enzyme called β-(1,3)-D-glucan synthase.
  • What Echinocandins Do: Echinocandins noncompetitively inhibit β-(1,3)-D-glucan synthase. (This means they bind to a different site on the enzyme than the normal substrate, permanently locking it).
  • The Result:
    • Glucan cannot be synthesized.
    • The cell wall becomes weak, fragile, and unable to withstand environmental stress.
    • Osmotic pressure inside the cell causes it to swell and burst (osmotic lysis). Cell death occurs rapidly.
💡 PHYSIOLOGY EXPANSION: The Secret to Their Safety
Why are Echinocandins so incredibly safe compared to Amphotericin B? Because they target the CELL WALL (glucan), not the cell membrane. Human cells DO NOT HAVE cell walls! We only have cell membranes. Therefore, the drug circulates in the human body completely ignoring human cells because its specific target (glucan synthase) simply does not exist in human biology. This is the ultimate example of selective toxicity.
🧠 MNEMONIC: "ECHINOCANDINS CRUSH THE WALL"
Echinocandins
Cell wall target (glucan)
Halt glucan synthesis
Inhibit glucan synthase
No glucan made
Osmotic lysis occurs
Candida dies
Aspergillus weakened
No human toxicity (no glucan in humans!)
Drug interactions minimal
IV only
New and safe
Serious infections

4.3.3 Individual Echinocandin Profiles

CASPOFUNGIN (Cancidas)

  • Category: Echinocandin — Systemic (IV only).
  • Spectrum: Excellent for Candida (even fluconazole-resistant strains) and Aspergillus. NOT active against Cryptococcus.
  • Clinical Uses: Invasive candidiasis, Esophageal candidiasis (when fluconazole fails), Invasive aspergillosis, Prophylaxis in stem cell transplants.
  • Pharmacokinetics: Highly protein bound (97%). Slowly degraded by hydrolysis in liver (NOT CYP450 — hence, very few drug interactions!).
  • Adverse Effects: Extremely well tolerated! May cause mild fever, phlebitis at IV site, mild liver enzyme elevation, or histamine-mediated reactions (rash, flushing).
  • Nursing Considerations:
    • Administer by slow IV infusion over 1 hour.
    • CRITICAL: Do NOT mix with dextrose! Use normal saline only.
    • Loading dose is given on day 1, then maintenance dose daily.

MICAFUNGIN & ANIDULAFUNGIN

  • Micafungin (Mycamine):
    • Similar to Caspofungin. Used for Candidemia and prophylaxis.
    • Nursing Note: Can be mixed with normal saline OR lactated Ringer's. No loading dose needed.
  • Anidulafungin (Eraxis):
    • Longest half-life (40-50 hours).
    • Pharmacokinetic Magic: It is NOT metabolized by the liver or kidneys. It slowly degrades spontaneously in the blood via chemical degradation.
    • Nursing Note: No dosage adjustment is needed for any level of renal or hepatic impairment — very convenient for critically ill ICU patients with failing organs!

Echinocandins: Common Drugs, Indications, Dosages, Contraindications, and Side Effects

DrugCommon IndicationsTypical Dosages (Adult)ContraindicationsMajor Side Effects
CaspofunginInvasive candidiasis, Esophageal candidiasis, Invasive aspergillosis70 mg IV loading dose on Day 1, then 50 mg IV dailyHypersensitivityMild fever, Phlebitis, Mild LFT elevation, Histamine reactions (rash, flushing)
MicafunginCandidemia, Prophylaxis in stem cell transplant100-150 mg IV dailyHypersensitivityRash, Pruritus, Mild LFT elevation
AnidulafunginCandidemia, Invasive candidiasis200 mg IV loading dose on Day 1, then 100 mg IV dailyHypersensitivityHypokalemia, Diarrhea, Mild infusion reactions

CLASS 4: ALLYLAMINE ANTIFUNGALS

4.4.1 Overview & Mechanism of Action (MOA)

  • Allylamines are mainly used for superficial fungal infections of the skin, hair, and nails. They are highly fungicidal against dermatophytes.
  • How they work: To make ergosterol, fungi must convert a chemical called squalene into squalene epoxide using the enzyme squalene epoxidase. Allylamines block this exact enzyme early in the pathway.
  • The Result (Double-Hit mechanism):
    1. Squalene accumulates inside the cell, which is highly TOXIC to the fungus.
    2. Ergosterol is depleted, so the cell membrane collapses.
🧠 MNEMONIC: "ALLYLAMINES STOP THE START"
Allylamines
Lock squalene epoxidase
Leave squalene building up
Yeast and molds poisoned
Loss of ergosterol

TERBINAFINE (Lamisil)

  • Category: Allylamine — Oral and topical.
  • Clinical Uses: Onychomycosis (fungal nail infection), Tinea capitis (scalp), Tinea pedis (athlete's foot), Tinea cruris (jock itch).
  • Pharmacokinetics: Highly lipophilic — it accumulates massively in skin, nails, and fat. While its half-life in plasma is 16 hours, its half-life in nails is 200-400 hours! This is why it cures nail infections so well.
  • Adverse Effects & Nursing Considerations:
    • Taste disturbance (loss of taste or altered taste, which can occasionally be permanent). Warn the patient!
    • Hepatotoxicity — monitor LFTs before and during therapy.
    • Treatments are long: 6-12 weeks for fingernails, 12-24 weeks for toenails.

Allylamines: Common Drugs, Indications, Dosages, Contraindications, and Side Effects

DrugCommon IndicationsTypical Dosages (Adult)ContraindicationsMajor Side Effects
TerbinafineOnychomycosis, Tinea capitis, Tinea pedis, Tinea cruris250 mg PO daily (duration depends on site: up to 12-24 weeks for nails)Chronic or active liver disease, HypersensitivityTaste disturbances (dysgeusia), Hepatotoxicity, GI upset, Headache

CLASS 5: MISCELLANEOUS ANTIFUNGAL AGENTS

4.5.1 FLUCYTOSINE (5-FC, Ancobon)

  • Mechanism of Action (The "Trojan Horse"):
    • Flucytosine is taken up by fungal cells through a permease enzyme. Once inside, the fungus's own enzymes (cytosine deaminase) convert it into 5-fluorouracil (5-FU).
    • 5-FU is a potent chemotherapy agent that halts DNA and RNA synthesis, stopping cell division.
  • Clinical Uses: Cryptococcal meningitis and Severe Candida infections.
  • CRITICAL NURSING RULE: ALWAYS used in combination (usually with Amphotericin B). It is NEVER used alone because the fungi will rapidly mutate and develop total resistance.
  • Adverse Effects: Bone marrow suppression (leukopenia, thrombocytopenia, severe anemia). Monitor CBC regularly! Toxicity occurs at blood levels >100 mcg/mL.
🧠 MNEMONIC: "FLUCYTOSINE NEEDS A FRIEND"
Flucytosine
Looks like cytosine (harmless Trojan horse)
Unleashes 5-FU inside fungus
Combination therapy only!
Yeast and Cryptococcus targeted
Toxic to bone marrow

4.5.2 GRISEOFULVIN

  • Mechanism: Deposits heavily into keratin precursor cells (cells that make skin/hair/nails). As these cells mature, the embedded drug acts as a barrier, making the new skin resistant to fungal invasion. It also stops fungal mitosis.
  • Uses: Severe Tinea capitis (scalp ringworm), especially in children.
  • Nursing Considerations: Absorption is highly variable. MUST be given with a fatty meal (like peanut butter, milk, or avocado) to drastically increase GI absorption. Advise patients to avoid sunlight (causes photosensitivity). Contraindicated in pregnancy.

4.5.3 TOPICAL AGENTS

  • Ciclopirox (Penlac): Topical only. Chelates metal ions (iron) that fungi need. Applied like nail polish for Onychomycosis (removed with alcohol every 7 days).
  • Tolnaftate (Tinactin): OTC topical for Tinea pedis/cruris. Inhibits squalene epoxidase like terbinafine.
  • Gentian Violet: Dye antiseptic. Highly effective for oral thrush in resource-limited settings. Nursing Note: Warn the mother it will stain the baby's mouth, skin, and clothing bright purple!

Miscellaneous Agents: Common Drugs, Indications, Dosages, Contraindications, and Side Effects

DrugCommon IndicationsTypical Dosages (Adult)ContraindicationsMajor Side Effects
Flucytosine (5-FC)Cryptococcal meningitis (adjunct to Amphotericin B)25 mg/kg PO q6h (100 mg/kg/day total)Severe renal impairment (requires strict dose adjustment), Avoid monotherapyBone marrow suppression (leukopenia, thrombocytopenia), GI intolerance, Hepatotoxicity
GriseofulvinTinea capitis, severe dermatophytosis500-1000 mg PO daily (microsize formulation); take with fatty mealPregnancy, Severe liver disease, PorphyriaPhotosensitivity, Headache, GI upset, Peripheral neuropathy

SECTION 5: COMPARATIVE TABLE OF SYSTEMIC ANTIFUNGALS

DrugClassRouteSpectrumKey ToxicityMonitoring
FluconazoleTriazoleOral, IVCandida, CryptococcusHepatotoxicity, QT prolongationLFTs, ECG
ItraconazoleTriazoleOral, IVBroad (Aspergillus, dimorphic)Hepatotoxicity, CHFLFTs, heart function
VoriconazoleTriazoleOral, IVAspergillus, CandidaVisual disturbances, hepatotoxicityLFTs, vision checks
Amphotericin BPolyeneIVBroadestNephrotoxicity, infusion rxns, hypokalemiaRenal panel, K+, Mg2+, CBC
CaspofunginEchinocandinIVCandida, AspergillusMild — very well toleratedLFTs
FlucytosinePyrimidineOral, IVCandida, CryptococcusBone marrow suppressionCBC, LFTs, drug levels
TerbinafineAllylamineOral, topicalDermatophytesTaste disturbance, HepatotoxicityLFTs

SECTION 6: NURSING PROCESS FOR ANTIFUNGAL THERAPY

6.1 ASSESSMENT

  • A. Health History: Check allergies. Screen for Liver disease, Kidney disease, Heart disease (critical for itraconazole), HIV/AIDS status, Diabetes (high glucose feeds fungi). Complete medication history is CRITICAL for azoles due to massive CYP450 drug interactions.
  • B. Physical Assessment: Inspect skin, hair, nails. Check mouth/throat for white patches. Laboratory tests: Baseline CBC, LFTs (AST, ALT, bilirubin), Renal (Creatinine, BUN), and Electrolytes (K+, Mg2+).
  • C. Diagnostic Tests: KOH preparation (skin scrapings), fungal cultures, blood cultures, or Lumbar puncture (for meningitis).

6.2 NURSING DIAGNOSES & 6.3 PLANNING

  • Nursing Diagnoses: Risk for Infection related to incomplete treatment; Impaired Skin Integrity; Acute Pain; Risk for Imbalanced Fluid Volume / Electrolyte Imbalance (Amphotericin B).
  • Goals: Patient will complete full course of therapy, remain free of serious adverse effects, and maintain adequate renal/hepatic function.

6.4 IMPLEMENTATION (Drug-Class Specific Interventions)

  • AZOLES: Monitor LFTs. Check interactions. Give Voriconazole patients sunglasses. Give Itraconazole with food/acid. Give Posaconazole with a high-fat meal.
  • AMPHOTERICIN B: Pre-hydrate with normal saline. Premedicate (acetaminophen, diphenhydramine, hydrocortisone). Infuse slowly (4-6 hrs). Monitor K+ and Mg2+ daily. Replace aggressively.
  • ECHINOCANDINS: Administer IV over 1 hour. Do NOT use dextrose for caspofungin.
  • FLUCYTOSINE: Monitor CBC for bone marrow suppression. Ensure hydration.
  • TOPICALS: Clean and dry area first. For vaginal, insert high and remain recumbent for 10-15 mins. For troches, dissolve slowly, do not chew.

SECTION 7: PATIENT & FAMILY EDUCATION

  • General Points: Complete the FULL course—fungal infections come back stronger if not fully treated (resistance). Do not skip doses.
  • Report Immediately: Yellowing of skin/eyes (jaundice), dark urine, severe rash, difficulty breathing, or vision changes.
  • Hygiene Measures: Fungi love moisture! Keep skin dry. Do not share towels/combs. Wear sandals in communal showers.

7.2 Community Education for Ugandan Settings

  • HIV/AIDS patients: Take antiretroviral therapy (ART) consistently to maintain immune function. Report oral sores immediately.
  • Diabetic patients: Control blood sugar. Inspect feet daily. Keep space between toes bone dry.
  • School children: Do not share combs, hats, or hair accessories (prevents Tinea capitis).
  • Farmers (Subcutaneous Mycoses): Wear protective footwear (gumboots) to prevent soil-borne fungi (mycetoma) entering cuts.

SECTION 8: CLINICAL SCENARIOS FOR UGANDAN COMMUNITIES

SCENARIO 1: Oral Thrush in an HIV-Positive Patient

  • Patient: Maria, 32, HIV+, not on ART. White patches in mouth, painful swallowing, low CD4 count.
  • Diagnosis & Treatment: Oropharyngeal candidiasis. Treat with Nystatin oral suspension or Fluconazole tablets.
  • Nursing Interventions: Instruct to "swish and swallow" Nystatin. Counsel heavily on restarting ART to rebuild her immune system so the thrush stops returning. Advise a soft, bland diet. Continue for 48 hours after white patches disappear.

SCENARIO 2: Cryptococcal Meningitis

  • Patient: John, 28, HIV+, severe headache, neck stiffness, photophobia. Lumbar puncture shows high pressure cloudy CSF.
  • Treatment Protocol: Amphotericin B IV + Flucytosine oral (2 weeks induction) → Fluconazole oral (8 weeks consolidation) → Fluconazole maintenance (for life, or until CD4 recovers).
  • Nursing Priorities: Protect the kidneys! Pre-hydrate with 1L normal saline before Amphotericin. Monitor CBC twice weekly for Flucytosine bone marrow toxicity. Keep head of bed elevated 30 degrees.

SCENARIO 3: Tinea Capitis in a School Child

  • Patient: Peter, 7, patchy hair loss, scaly scalp, black dots where hair broke. Classmates have similar symptoms.
  • Treatment: Oral Griseofulvin (or Terbinafine) for 6-8 weeks + antifungal shampoo.
  • Nursing Interventions: Give Griseofulvin with a fatty meal (peanut butter/milk) to maximize absorption. Educate family NOT to share combs/hats. Treatment takes 6-8 weeks, do not stop early even if hair starts growing back.

SCENARIO 4: Vaginal Candidiasis in a Pregnant Woman

  • Patient: Sarah, 24, 28 weeks pregnant. Thick white cottage-cheese discharge, intense itching.
  • CRITICAL Nursing Rule: DO NOT give oral Fluconazole! Oral azoles are contraindicated in pregnancy (risk of birth defects).
  • Treatment: Topical azole cream or vaginal suppository (Clotrimazole) for 7 days. Advise loose cotton underwear. Screen for gestational diabetes if recurrent.

SCENARIO 5: Invasive Aspergillosis in a Cancer Patient

  • Patient: Grace, 45, neutropenic from leukemia chemotherapy. Fever, dry cough, chest CT shows "halo sign".
  • Treatment: Voriconazole IV (First-line).
  • Nursing Education: "You may notice changes in your vision or colors—tell us immediately. Wear sunglasses and sunscreen when you go outside. We will check your liver function regularly."

SECTION 10: EXAM TIPS

10.1 High-Yield Facts for Exams

💡 Fact 1: Azoles and CYP450
Question: Why do azoles cause so many drug interactions?
Answer: They inhibit cytochrome P450 enzymes (especially CYP3A4, CYP2C9, CYP2C19). This slows down the metabolism of many other drugs, causing their levels to rise to toxic levels.
High-yield pairs:
• Fluconazole + Warfarin = INCREASED bleeding risk
• Fluconazole + Oral hypoglycemics = SEVERE hypoglycemia
• Itraconazole + Statins = Rhabdomyolysis (muscle breakdown)
💡 Fact 2: Amphotericin B and Nephrotoxicity
Question: What is the nurse's PRIORITY intervention when administering amphotericin B?
Answer: Pre-hydration with normal saline to protect the kidneys. Never forget: Amphotericin B causes hypokalemia and hypomagnesemia due to renal tubular damage. Replace these electrolytes!
💡 Fact 3: Echinocandins Are the Safest
Question: Which antifungal class has the FEWEST drug interactions and is preferred in patients with liver problems?
Answer: Echinocandins (caspofungin, micafungin, anidulafungin) — they are NOT metabolized by CYP450 enzymes in the liver.
💡 Fact 4: Flucytosine Is Never Alone
Question: Why is flucytosine always given in combination with amphotericin B or fluconazole?
Answer: Because severe resistance develops rapidly when used alone. It is a Trojan horse drug that fungi can easily learn to resist.
  • Fact 5: Voriconazole and Vision. If a patient reports seeing colors differently and bright lights hurting their eyes, this is an expected adverse effect. Reassure the patient, advise sunglasses, and monitor. Reversible when stopped.
  • Fact 6: Nystatin Is Not Systemic. Nystatin is NOT absorbed from the GI tract. It only works locally. Do NOT use it for systemic bloodstream infections.
  • Fact 7: Terbinafine for Nails. Why take medicine for 12 weeks? Terbinafine accumulates in keratin, but nails grow very slowly. Fingernails take 6-12 weeks, toenails take 12-24 weeks to grow out completely.
  • Fact 8: Pregnancy and Antifungals. Oral fluconazole is CONTRAINDICATED (causes birth defects). Topical azoles (clotrimazole) are safe and preferred.
  • Fact 9: Griseofulvin and Fat. Administer with a fatty meal (peanut butter, milk) to maximize GI absorption.
  • Fact 10: Cryptococcal Meningitis. Standard induction treatment for HIV patients: Amphotericin B + Flucytosine for 2 weeks.

10.2 Sample UHPAB-Style Questions with Rationales

Question 1

A patient receiving amphotericin B develops shaking chills and a temperature of 39.5°C during the infusion. What is the nurse's FIRST action?

  • A. Stop the infusion immediately
  • B. Administer meperidine and continue the infusion
  • C. Slow the infusion rate and notify the prescriber
  • D. Give acetaminophen and diphenhydramine as ordered

Rationale: Fever and chills are COMMON infusion reactions to amphotericin B. The nurse should administer premedications as ordered. Stopping the infusion is not necessary unless the patient develops severe hypotension, bronchospasm, or anaphylaxis.

Question 2

A nurse is teaching a patient about fluconazole. Which statement by the patient indicates understanding?

  • A. "I can stop taking this medication when my symptoms improve."
  • B. "I should avoid grapefruit juice while taking this medication."
  • C. "This medication can cause liver damage, so I need blood tests."
  • D. "I need to take this medication on an empty stomach."

Rationale: Fluconazole can cause hepatotoxicity, and LFTs must be monitored. Patients must complete the FULL course. It can be taken with or without food.

Question 3

A patient with invasive candidiasis is prescribed caspofungin. The nurse prepares to administer the medication. Which solution is appropriate for reconstitution?

  • A. Dextrose 5% in water (D5W)
  • B. Normal saline (0.9% NaCl)
  • C. Lactated Ringer's solution
  • D. Sterile water for injection

Rationale: Caspofungin MUST be reconstituted and diluted with normal saline. It is INCOMPATIBLE with dextrose-containing solutions.

Question 4

A pregnant woman at 32 weeks gestation has vulvovaginal candidiasis. Which treatment is MOST appropriate?

  • A. Oral fluconazole 150 mg single dose
  • B. Oral itraconazole 200 mg daily for 3 days
  • C. Topical clotrimazole vaginal cream for 7 days
  • D. Oral griseofulvin 500 mg daily for 4 weeks

Rationale: Oral azoles are contraindicated in pregnancy due to risk of birth defects. Topical azoles are safe and the treatment of choice.

Question 5

A patient is receiving itraconazole for histoplasmosis. The nurse notes the patient is also taking omeprazole for GERD. What is the nurse's concern?

  • A. Omeprazole increases itraconazole absorption
  • B. Omeprazole decreases itraconazole absorption by reducing stomach acid
  • C. The combination causes severe hypotension
  • D. The combination increases the risk of tendon rupture

Rationale: Itraconazole capsules require an acidic gastric pH for absorption. PPIs reduce stomach acid, significantly decreasing absorption. Give with an acidic beverage (like Coca-Cola) or use oral solution.

SECTION 11: SUMMARY & QUICK REFERENCE TABLES

11.1 Mechanism of Action Summary

Drug ClassTargetMechanismResultFungicidal/Fungistatic?
AzolesCell membraneInhibit 14α-demethylase → ↓ ergosterolWeak, leaky membraneFungistatic
PolyenesCell membraneBind ergosterol → pore formationLeakage of K+, cell deathFungicidal
EchinocandinsCell wallInhibit β-(1,3)-D-glucan synthaseWeak cell wall, osmotic lysisFungicidal (Candida)
AllylaminesCell membraneInhibit squalene epoxidase↓ ergosterol, ↑ toxic squaleneFungicidal
FlucytosineDNA/RNAConverted to 5-FU → inhibits thymidylate synthaseDisrupted DNA/RNA synthesisFungistatic

11.2 Spectrum of Activity Quick Reference

InfectionFirst-Line TreatmentNotes
Vulvovaginal candidiasisFluconazole 150 mg PO once OR topical azole x7 daysAvoid oral azoles in pregnancy
Oropharyngeal candidiasisNystatin suspension OR clotrimazole trochesHIV patients often need fluconazole
Invasive candidiasisEchinocandin (caspofungin, micafungin)Echinocandins preferred in critically ill
Cryptococcal meningitisAmphotericin B + Flucytosine (2 weeks)Flucytosine levels must be monitored
Invasive aspergillosisVoriconazoleFirst-line standard of care
MucormycosisLiposomal amphotericin B + surgical debridementSurgical removal is ESSENTIAL
Tinea capitis (scalp)Griseofulvin OR terbinafine POTreat for 6-8 weeks

11.3 Adverse Effects by Body System

Body SystemAmphotericin BAzolesFlucytosine
RenalNephrotoxicity (major!)RareRare
HepaticMildHepatotoxicity (common)Hepatotoxicity
HematologicAnemiaRareBone marrow suppression
CardiacArrhythmias (from K+/Mg2+ loss)QT prolongationNone
NeurologicHeadacheVoriconazole: visual changesConfusion, seizures
MetabolicHypokalemia, hypomagnesemiaHypokalemiaNone specific

11.4 Drug Interaction Cheat Sheet

If Patient Takes...And Receives...RiskNursing Action
WarfarinAzolesBleedingMonitor INR closely; reduce warfarin dose
Oral hypoglycemicsFluconazoleSevere hypoglycemiaMonitor blood glucose
StatinsItraconazole, VoriconazoleRhabdomyolysisStop statin during therapy
CyclosporineAzoles, Amphotericin BToxicity of immunosuppressantMonitor drug levels; reduce dose
RifampinAzoles, FlucytosineTreatment failureRifampin rapidly clears antifungals from blood

SECTION 12: SPECIAL CONSIDERATIONS FOR UGANDAN NURSING PRACTICE

  • A. Resource-Limited Settings:
    • If Liposomal Amphotericin B is unavailable, conventional amphotericin must be used. Sodium loading is CRITICAL—even if you only have 250 mL of normal saline, give it!
    • If Meperidine is unavailable for rigors, use IV paracetamol and warm blankets.
  • B. Managing Tinea Capitis in Schools:
    • Extremely common in Ugandan schools. Oral griseofulvin is often the most affordable. Train parents to check children's scalps and emphasize NOT sharing combs/hats.
  • C. Agricultural Workers:
    • Subcutaneous fungal infections (mycetoma/Madura foot) occur when soil fungi enter wounds. Teach farmers to wear gumboots and immediately clean/cover any cuts.
  • D. Medication Adherence Challenges:
    • Long courses (months for nails, years for cryptococcal maintenance) lead to fatigue. Use community health workers for refills, and simplify regimens to once-daily dosing when possible.

SECTION 13: CLINICAL CASE STUDY (Test Your Knowledge!)

Case: A 35-Year-Old Farmer from Gulu

Mr. Ojok presents with a 3-week history of painful white patches in his mouth, difficulty swallowing, and 5 kg weight loss. Diagnosed with HIV 2 years ago but stopped taking ART 6 months ago.
Assessment: BMI 17.5. Extensive white plaques on tongue and palate that bleed when scraped. CD4 count: 45 cells/μL (severe immunocompromise).

📝 Case Study Questions & Detailed Answers

  1. What is the MOST likely diagnosis for the oral lesions?
    Answer: Oropharyngeal candidiasis (Oral Thrush), likely extending into esophageal candidiasis due to his difficulty swallowing.
  2. What is the appropriate FIRST-LINE treatment?
    Answer: Systemic oral Fluconazole. Nystatin swish-and-swallow is fine for mild thrush, but because he has swallowing difficulty (esophageal involvement) and a severely low CD4 count, systemic therapy is required.
  3. What additional fungal infection should you be concerned about given the CD4 count < 50?
    Answer: Cryptococcal meningitis and Pneumocystis pneumonia (PCP). He should undergo Cryptococcal antigen screening (CrAg) immediately.
  4. If the patient develops headache and neck stiffness 2 weeks later, what complication has occurred?
    Answer: Cryptococcal Meningitis (a deadly systemic mycosis).
  5. What is the standard treatment for this complication?
    Answer: IV Amphotericin B combined with oral Flucytosine for 2 weeks (Induction), followed by high-dose Fluconazole.
  6. What are the nursing priorities when administering amphotericin B in this setting?
    Answer: Pre-hydration with normal saline to prevent nephrotoxicity. Pre-medicating for infusion reactions. Monitoring daily renal function and replacing lost Potassium and Magnesium.

SECTION 14 & 15: GLOSSARY AND REFERENCES

TermSimple Definition
Chitin / ErgosterolChitin forms the fungal cell wall; Ergosterol is the fat in the cell membrane (drug targets).
Fungicidal / FungistaticFungicidal directly KILLS the fungus. Fungistatic halts growth, relying on the immune system to finish the job.
Opportunistic infectionAn infection that strictly takes advantage of a weak immune system (e.g., Candida in HIV).

References & Further Reading:

  • Uganda Fungal Disease Burden — Bongomin F, et al. "The burden and impact of fungal diseases in Uganda." Journal of Fungi. 2026.
  • Antifungal Pharmacology — Nett JE, Andes DR. "Antifungal Agents: Spectrum of Activity." Infectious Disease Clinics of North America. 2016.
  • WHO Guidelines for Cryptococcal Meningitis (2022) & Uganda Ministry of Health Guidelines (2024).
Quick Quiz

Antifungal Agents Quiz

Pharmacology

Privacy: Your details are used only for quiz tracking and certificates.

ANTIFUNGAL AGENTS Read More »

ANTIRETROVIRAL DRUGS (ARVs)

ANTIRETROVIRAL DRUGS (ARVs) Pharmacology

ANTIRETROVIRAL DRUGS (ARVs)

MODULE 1: UNDERSTANDING HIV AND WHY WE NEED ARVs

1.1 What is HIV?

HIV (Human Immunodeficiency Virus) is a tiny germ (virus) that attacks the body's defense system. Think of your body like a house, and your immune system is the security guard. HIV specifically attacks the CD4 cells (also called T-helper cells) — these are like the "commander soldiers" of your immune system.

Key Points:

  • HIV stands for Human Immunodeficiency Virus.
  • It is NOT the same as AIDS (AIDS is the advanced stage when the immune system is very weak).
  • HIV cannot survive outside the human body for long.
  • It spreads through: unprotected sex, from mother to baby (vertical transmission), sharing sharp objects, and blood transfusions.

Physiological Expansion: Why CD4 cells?

HIV has a specific glycoprotein on its surface called gp120. This protein fits perfectly like a lock-and-key into the CD4 receptor found on T-helper cells, macrophages, and dendritic cells. Without CD4 cells, the immune system cannot signal B-cells to make antibodies or Cytotoxic T-cells to kill infections. That is why HIV is so destructive—it takes out the generals of the immune army.

🧠 MNEMONIC: "HIV Hides In Villages"

  • Hides in the body for years without symptoms (clinical latency period).
  • Immune system is the target.
  • Very sneaky — can be passed on before you know you have it.

1.2 What Happens Without Treatment?

If a person with HIV does NOT take ARVs:

  • The virus keeps making copies of itself inside CD4 cells.
  • CD4 cell count drops (normal is 500–1,500 cells/mm³).
  • The body cannot fight infections anymore.
  • Opportunistic Infections (OIs) attack — like TB, pneumonia, diarrhea, skin diseases.
  • Eventually, the person develops AIDS (Acquired Immunodeficiency Syndrome).

❓ Clinical Scenario: Disease Progression
Case: A 32-year-old woman from a village in Uganda comes to the clinic with a cough that has lasted 3 months, weight loss, and night sweats. Her CD4 count is 180 cells/mm³. She has HIV that has progressed to AIDS because she never took ARVs.

Nursing Action: As a nurse, you must start her on ART immediately after ruling out or treating Opportunistic Infections (like TB and cryptococcal meningitis). Why? Starting ART while a severe OI is active can cause IRIS (Immune Reconstitution Inflammatory Syndrome), a dangerous overreaction of the newly "woken up" immune system!

1.3 What is ART?

ART (Antiretroviral Therapy) is the combination of ARV drugs used to treat HIV. It is NOT a cure, but it helps people live long, healthy lives.

The Goal of ART:

  • To reduce the amount of virus in the blood to undetectable levels.
  • To increase CD4 cell count (immune reconstitution).
  • To prevent transmission of HIV to others (U=U: Undetectable = Untransmittable).
  • To prevent AIDS and death.

🧠 MNEMONIC: "ART Always Restores Tomorrow"

  • Always take it daily.
  • Restores the immune system.
  • Tomorrow will be healthier.

MODULE 2: HOW ARVs WORK (MECHANISMS OF ACTION)

Think of HIV like a factory that makes copies of itself. ARVs are like "factory workers" who go inside and break different machines in the factory so the virus cannot make new copies.

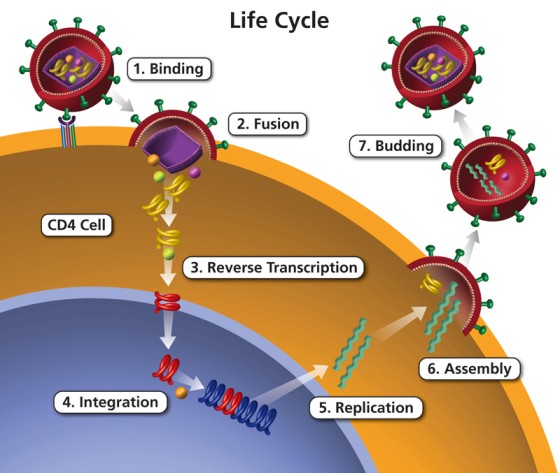
2.1 The HIV Life Cycle (Simplified & Expanded)

To understand ARVs, you must first understand how HIV reproduces:

  1. Attachment: HIV attaches to a CD4 cell (gp120 binds to the CD4 receptor and a co-receptor like CCR5).
  2. Fusion: HIV's viral envelope merges with the CD4 cell membrane, emptying its contents into the cell.
  3. Reverse Transcription: HIV is a retrovirus, meaning it carries RNA. It uses the enzyme Reverse Transcriptase to change its viral RNA (genetic material) into viral DNA.
  4. Integration: HIV DNA enters the cell's nucleus and uses the enzyme Integrase to mix (splice) itself permanently into the human DNA.
  5. Replication: The human cell is hijacked! It reads the viral DNA and starts making new HIV proteins and viral RNA.
  6. Assembly: New HIV parts come together near the cell surface.
  7. Budding: New HIV viruses push out (leave) the cell, wrapping themselves in the human cell's membrane to infect other cells. Protease enzyme cuts the proteins to mature the virus.

🧠 MNEMONIC: "A Fat Rabbit Is Really (bad)At Basketball"
Attachment → Fusion → Reverse transcription → Integration → Replication → Assembly→Budding

2.2 The Six Major Classes of ARVs

Each class of ARV attacks a different step in the HIV life cycle:

ClassWhat It DoesStep Attacked
NRTIsFake building blocks that stop DNA buildingReverse Transcription
NNRTIsBlock the reverse transcriptase enzyme directlyReverse Transcription
PIsBlock the protease enzyme (stops virus maturation)Assembly / Maturation
INSTIsBlock the integrase enzyme (stops HIV DNA mixing)Integration
Entry InhibitorsBlock HIV from entering the CD4 cellAttachment/Fusion
PK BoostersMake other ARVs work better and longerNot an ARV itself

MODULE 3: DETAILED STUDY OF EACH ARV CLASS

3.1 NRTIs (Nucleoside/Nucleotide Reverse Transcriptase Inhibitors)

Pronounced: "En-Ar-Tee-Eyes"

What They Do:

NRTIs are "fake DNA building blocks." HIV needs real building blocks (nucleotides) to make its DNA. NRTIs pretend to be real building blocks, but when HIV tries to use them, the DNA chain stops growing. It's like giving a builder fake bricks — the wall cannot be completed.

How They Work (Detailed Pharmacology):

  • HIV has an enzyme called reverse transcriptase.
  • This enzyme reads HIV's RNA and builds a complementary DNA strand.
  • NRTIs look like the natural nucleosides that reverse transcriptase needs. However, they lack a crucial 3'-OH group needed to attach the next nucleotide.
  • Reverse transcriptase picks up the NRTI instead of the real building block.
  • Once the fake building block is added, no more blocks can be added. The DNA chain is terminated (Chain Termination).
  • Result: HIV cannot make copies of itself.
Generic NameAbbreviationBrand NameKey Notes
TenofovirTDF or TAFViread (TDF), Vemlidy (TAF)Backbone of most regimens. TAF is safer for bones/kidneys.
Lamivudine3TCEpivirVery well tolerated. Also treats Hep B.
EmtricitabineFTCEmtrivaSimilar to 3TC. Can cause hyperpigmentation of palms/soles.
ZidovudineAZT or ZDVRetrovirCan cause severe anemia and bone marrow suppression.
AbacavirABCZiagenMust test for HLA-B*5701 gene to prevent fatal hypersensitivity.
Stavudined4TZeritNO LONGER RECOMMENDED — causes severe lipoatrophy & neuropathy.

NRTI Clinical Summary: Drugs, Indications, Dosages, Contraindications & Side Effects

Common DrugsIndicationsStandard Adult DosagesContraindicationsMajor Side Effects
Tenofovir (TDF)HIV-1, Chronic Hepatitis B300 mg once dailySevere renal impairment (CrCl < 30 mL/min)Nephrotoxicity, decreased bone mineral density.
Lamivudine (3TC)HIV-1, Chronic Hepatitis B300 mg once daily OR 150 mg twice dailyHypersensitivityMinimal; mild nausea, headache.
Zidovudine (AZT)HIV-1, PMTCT, Post-exposure prophylaxis300 mg twice dailySevere anemia, bone marrow suppression, neutropeniaMacrocytic anemia, neutropenia, myopathy, hyperpigmentation.
Abacavir (ABC)HIV-1 (often when TDF is contraindicated)600 mg once daily OR 300 mg twice dailyHLA-B*5701 positive (high risk of fatal hypersensitivity), severe hepatic impairmentHypersensitivity reaction (fever, rash, respiratory symptoms), possible increased CV risk.

Common Side Effects of NRTIs:

  • Nausea, vomiting, headache, and fatigue.
  • Diarrhea.
  • Lactic acidosis: Rare but serious. Occurs because NRTIs can mistakenly inhibit mitochondrial DNA polymerase gamma, starving human cells of ATP and causing lactic acid buildup.
  • Lipodystrophy: Fat changes in body (especially with old drugs like d4T).
  • Bone problems & Kidney problems: Specifically with Tenofovir Disoproxil Fumarate (TDF). It can cause Fanconi syndrome (kidney wasting) and osteoporosis.

🚨 NURSING ALERT: Lactic Acidosis
Symptoms: Deep, rapid breathing (Kussmaul breathing), muscle pain, weakness, stomach pain, feeling cold.
This is a medical emergency! If a patient on NRTIs presents with these, STOP the drug and call the doctor immediately. Check ABGs and lactate levels.

❓ Clinical Scenario: TDF Toxicity
Case: A 45-year-old man on TDF+3TC+DTG comes to the clinic complaining of severe bone pain and difficulty walking.
Nursing Action: As a nurse, you check his kidney function (creatinine) and bone density. You know that TDF can cause renal toxicity (which leaks phosphate) leading to bone weakening. The doctor may switch him to TAF (tenofovir alafenamide), which targets the HIV cell much more efficiently, meaning less drug floats in the blood to damage bones and kidneys.

🧠 MNEMONIC for NRTIs: "Tenofovir And Lamivudine Can Always Zap HIV"

  • Tenofovir
  • And (Abacavir)
  • Lamivudine
  • Can (EmtriCitabine - FTC)
  • Always
  • Zidovudine
  • HIV

3.2 NNRTIs (Non-Nucleoside Reverse Transcriptase Inhibitors)

Pronounced: "En-En-Ar-Tee-Eyes"

What They Do:

NNRTIs also attack the reverse transcriptase enzyme, but they work differently from NRTIs. They bind directly to the enzyme and change its shape, so it cannot work anymore. Think of it like putting a wrong key in a lock — the lock changes shape and the real key cannot fit anymore.

How They Work (Detailed Pharmacology):

  • Reverse transcriptase has an active pocket where it binds to nucleosides (where NRTIs work).
  • NNRTIs do NOT act as fake building blocks. Instead, they fit into a different, allosteric pocket on the enzyme.
  • When the NNRTI binds to this pocket, it forces a conformational (shape) change in the active site of the enzyme.
  • The enzyme becomes "deformed" and paralyzed. It cannot build DNA anymore. HIV replication stops. (This is non-competitive inhibition).
Generic NameAbbreviationBrand NameKey Notes
EfavirenzEFVSustiva, StocrinCrosses blood-brain barrier. Causes vivid dreams, dizziness. Avoid in 1st trimester pregnancy.
NevirapineNVPViramuneHigh risk for severe liver rash (Stevens-Johnson syndrome). Requires 2-week dose lead-in.
EtravirineETRIntelenceSecond-line use. Works even against some NNRTI-resistant HIV.
RilpivirineRPVEdurantMust take with full meal. Absolutely AVOID proton pump inhibitors (omeprazole).
DoravirineDORPifeltroNewer drug, fewer CNS side effects than Efavirenz.

NNRTI Clinical Summary: Drugs, Indications, Dosages, Contraindications & Side Effects

Common DrugsIndicationsStandard Adult DosagesContraindicationsMajor Side Effects
Efavirenz (EFV)HIV-1 (First-line alternative)400 mg or 600 mg once daily (at bedtime)Severe psychiatric disorders, 1st trimester pregnancy (historical caution)CNS effects (vivid dreams, dizziness, depression), rash, hepatotoxicity.
Nevirapine (NVP)HIV-1, PMTCT (neonatal prophylaxis)200 mg once daily for 14 days, then 200 mg twice dailyHigh CD4 count in women (>250) or men (>400) due to fatal hepatotoxicity riskSevere hepatotoxicity, Stevens-Johnson syndrome (severe rash).
Rilpivirine (RPV)HIV-1 (Viral load < 100,000)25 mg once daily (with a full meal)Use with Proton Pump Inhibitors (PPIs) completely contraindicatedDepression, insomnia, rash, QTc prolongation.

Common Side Effects of NNRTIs:

  • Rash (skin reaction — very common and potentially fatal with Nevirapine).
  • Liver problems (hepatotoxicity — especially with Nevirapine in patients with high CD4 counts).
  • Central Nervous System (CNS) effects: (with Efavirenz): vivid dreams, dizziness, confusion, mood changes, "hangover" feeling in the morning.
  • Lipid changes: Total cholesterol and triglycerides go up.

🚨 NURSING ALERT: Nevirapine Rash
NVP rash can be mild or progress to a life-threatening skin peeling condition (Stevens-Johnson syndrome or TEN). If rash appears with a fever, blistering, or mouth sores → STOP THE DRUG IMMEDIATELY. Always start NVP at a lower dose for the first 2 weeks to let the liver adjust, then increase to normal dose.

❓ Clinical Scenario: Efavirenz & Pregnancy/CNS
Case: A 28-year-old woman on an EFV-based regimen tells you she is 8 weeks pregnant.
Nursing Action: EFV is known to be teratogenic (can cause neural tube birth defects) in the first trimester. Furthermore, it can cause severe psychiatric problems (depression, suicidal thoughts). As a nurse, you urgently inform the doctor to switch her to a DTG-based regimen (TDF+3TC+DTG), which is safe in pregnancy and lacks the CNS toxicity.

🧠 MNEMONIC for NNRTIs: "Every Nurse Eats Red Delicious Oranges"

  • Efavirenz
  • Nevirapine
  • Etravirine
  • Rilpivirine
  • Doravirine
  • Oranges (just for the "O" sound to finish the sentence!)

3.3 PIs (Protease Inhibitors)

Pronounced: "Pee-Eyes"

What They Do:

PIs block the protease enzyme. After HIV makes new proteins inside the cell, protease is needed to cut these proteins into the right sizes so new viruses can be assembled. PIs stop this cutting process. Think of it like a pair of scissors — PIs take away the scissors, so the virus parts cannot be put together properly.

How They Work (Detailed Pharmacology):

  • HIV translates its genetic code into long, inactive "polyproteins" (like a long, uncut string of sausages).
  • The viral protease enzyme specifically cleaves (cuts) these polyproteins into smaller, functional structural proteins and enzymes.
  • These pieces are needed to build the core of new, mature HIV viruses.
  • PIs bind directly to the active site of the protease enzyme.
  • Because protease cannot cut the protein chains, the new HIV viruses that bud from the cell are immature, defective, and non-infectious. Result: HIV cannot spread to other cells.
Generic NameAbbreviationBrand NameKey Notes
Lopinavir/RitonavirLPV/rKaletraCommonly used in children (available as liquid/pellets). Causes severe diarrhea.
Atazanavir/RitonavirATV/rReyataz + NorvirCan cause harmless but visible jaundice (yellow eyes) and kidney stones.
Darunavir/RitonavirDRV/rPrezista + NorvirPreferred PI in 2026 WHO guidelines due to high barrier to resistance.
RitonavirRTVNorvirUsed strictly as a "booster," not alone for its antiviral effect.

PI Clinical Summary: Drugs, Indications, Dosages, Contraindications & Side Effects

Common DrugsIndicationsStandard Adult DosagesContraindicationsMajor Side Effects
Lopinavir/Ritonavir (LPV/r)HIV-1 (Second-line, Pediatric first-line)400/100 mg twice dailyCo-administration with amiodarone, simvastatin, rifampicin (without dose adjustment)Severe diarrhea, hyperlipidemia, insulin resistance, PR/QT prolongation.
Atazanavir/Ritonavir (ATV/r)HIV-1 (Second-line alternative)300/100 mg once dailyCo-administration with PPIs (requires stomach acid for absorption)Indirect hyperbilirubinemia (jaundice), nephrolithiasis (kidney stones), cholelithiasis.
Darunavir/Ritonavir (DRV/r)HIV-1 (Second/Third-line preference 2026)800/100 mg once dailySevere hepatic impairment, sulfa allergy (caution)Hepatotoxicity, skin rash, hyperlipidemia.

Common Side Effects of PIs (Think "Metabolic Syndrome"):

  • Diarrhea (very common with LPV/r).
  • Nausea and vomiting.
  • Lipid abnormalities: High cholesterol, high triglycerides. PIs interfere with lipid metabolism in the liver.
  • Insulin resistance: Can lead to hyperglycemia and clinical diabetes.
  • Fat redistribution (Lipodystrophy): Buffalo hump on the back, big belly (visceral fat), but thin arms/legs and sunken cheeks.
  • Kidney stones and Jaundice (specifically with Atazanavir).

🚨 NURSING ALERT: PI and Drug Interactions
PIs interact with MANY other drugs because they drastically affect the CYP3A4 enzyme system in the liver. Always check for drug interactions before prescribing! Common dangerous interactions include statins (cholesterol drugs - can cause severe muscle breakdown), erectile dysfunction drugs, and some TB drugs (rifampicin drops PI levels to zero!).

❓ Clinical Scenario: PI Side Effects
Case: A 50-year-old man on LPV/r comes to the clinic with severe diarrhea (5–6 watery stools per day) and high cholesterol.
Nursing Action: As a nurse, you educate him about taking his medication WITH food to significantly reduce stomach upset. You also advise him to reduce fatty foods and increase dietary fiber. The doctor may add a cholesterol-lowering drug (statin), but you must strictly check for interactions first (e.g., Atorvastatin dose must be lowered; Simvastatin is totally contraindicated!).

🧠 MNEMONIC for PIs: "Lions And Dragons Roar"

  • Lopinavir
  • And (Atazanavir)
  • Darunavir
  • Ritonavir (the booster)

3.4 INSTIs (Integrase Strand Transfer Inhibitors)

Pronounced: "In-Stees"

What They Do:

INSTIs are the newest and best class of ARVs. They block the integrase enzyme, which HIV uses to insert its DNA into the human cell's DNA. Think of it like a thief trying to break into a house — INSTIs lock the door so the thief cannot get inside.

How They Work (Detailed Pharmacology):

  • After reverse transcription, a double-stranded HIV DNA is formed in the cytoplasm.
  • The integrase enzyme grabs this HIV DNA and carries it into the cell nucleus.
  • Integrase then performs "strand transfer"—it cuts the human DNA and pastes the HIV DNA permanently into the host chromosome. Once integrated, the cell becomes a permanent HIV factory.
  • INSTIs bind to the active site of the integrase enzyme, paralyzing it. HIV DNA stays outside the nucleus and eventually degrades. The human cell is saved from being hijacked!
Generic NameAbbreviationBrand NameKey Notes
DolutegravirDTGTivicayPreferred first-line anchor drug in Uganda and globally.
BictegravirBICBiktarvyVery effective, minimal side effects (co-formulated).
RaltegravirRALIsentressFirst INSTI approved. Dosed twice daily (less convenient).
CabotegravirCABVocabriaLong-acting injectable (given every 2 months!).

INSTI Clinical Summary: Drugs, Indications, Dosages, Contraindications & Side Effects

Common DrugsIndicationsStandard Adult DosagesContraindicationsMajor Side Effects
Dolutegravir (DTG)HIV-1 (First-line preferred)50 mg once dailyCo-administration with dofetilide (antiarrhythmic)Insomnia, weight gain, headache, rare hepatic toxicity.
Bictegravir (BIC)HIV-1 (Used in fixed-dose combo)50 mg once dailyCo-administration with dofetilide or rifampicinWeight gain, nausea, headache, diarrhea.
Raltegravir (RAL)HIV-1 (Alternative/PEP)400 mg twice daily OR 1200 mg once dailyHypersensitivityMyopathy, rhabdomyolysis, insomnia, rash.

Why DTG is the BEST Choice (Uganda & WHO 2026):

  • High barrier to resistance: HIV finds it very hard to mutate and become resistant to DTG.
  • Rapid viral suppression: Viral load drops significantly faster than with EFV or PIs.
  • Fewer side effects: Much better tolerated than EFV (no nightmares/depression).
  • Once-daily dosing: Easy for patients to remember, promoting adherence.
  • Low drug interactions: Safer to use with other medications.
  • Safe in pregnancy: Fully approved for pregnant and breastfeeding women.
  • Low cost: Affordable for massive public health programs like Uganda's.

Common Side Effects of INSTIs:

  • Insomnia (difficulty sleeping - usually passes after a few weeks).
  • Headache, mild nausea, dizziness.
  • Weight gain: Especially pronounced in women and when combined with TAF.
  • Liver enzyme elevation (rare).

🚨 NURSING ALERT: Weight Gain with DTG
Some patients gain significant weight (5-10 kg) on DTG. Monitor weight and BMI at every visit. Encourage a healthy diet and aerobic exercise. Do NOT stop the drug — this weight gain is manageable and is partly due to a "return to health" phenomenon as the virus stops burning the body's calories.

❓ Clinical Scenario: DTG Side Effects
Case: A 35-year-old woman starts TDF+3TC+DTG (TLD). After 3 months, her viral load is completely undetectable, but she has gained 5 kg. She is very worried about her body image.
Nursing Action: As a nurse, you enthusiastically celebrate her undetectable viral load! Reassure her that weight gain is a known side effect of DTG and shows the medicine is working. You counsel her on portion control, reducing sugary drinks, and walking 30 minutes daily. You schedule her for weight monitoring every month.

🧠 MNEMONIC for INSTIs: "Doctor Bic Rides Cars"

  • Dolutegravir
  • Bictegravir
  • Raltegravir
  • Cabotegravir

3.5 Entry Inhibitors

What They Do: These drugs stop HIV from entering the CD4 cell in the first place. They are like guards at the gate who refuse to let HIV inside.

Types of Entry Inhibitors:

  • Fusion Inhibitor (Enfuvirtide / T-20): Blocks the viral envelope from fusing with the CD4 cell membrane. Given by subcutaneous injection twice daily. Side effects include severe injection site reactions (pain, redness, nodules).
  • CCR5 Antagonist (Maraviroc): Blocks the human CCR5 co-receptor on CD4 cells. HIV cannot latch on. Pharmacological catch: Requires a "tropism test" first to ensure the patient's specific HIV strain actually uses CCR5 (and not CXCR4). Side effects include liver toxicity.

Usage: These are NOT first-line drugs. They are used only in special salvage cases (third-line or heavy resistance).

Entry Inhibitors Clinical Summary: Drugs, Indications, Dosages, Contraindications & Side Effects

Common DrugsIndicationsStandard Adult DosagesContraindicationsMajor Side Effects
Maraviroc (MVC)CCR5-tropic HIV-1 (Salvage therapy)150, 300, or 600 mg twice daily (depends on interacting drugs)CXCR4-tropic HIV, severe renal impairmentHepatotoxicity (severe), upper respiratory infections, rash.
Enfuvirtide (T-20)HIV-1 Treatment-experienced (Salvage)90 mg subcutaneously twice dailyHypersensitivityInjection site reactions (98% of patients), bacterial pneumonia, hypersensitivity.

3.6 Pharmacokinetic Boosters

What They Are: These are NOT ARVs themselves. They are drugs that slow down the breakdown of other ARVs (especially PIs) in the liver, making them work longer and better.

How They Work: The liver uses the CYP3A4 enzyme to destroy drugs. Boosters forcefully inhibit (block) this enzyme. As a result, the main ARV stays in the blood at high concentrations for 24 hours. This allows for lower doses of the main ARV and once-daily dosing!

Drugs in this Class:

  • Ritonavir (Norvir): The original booster.
  • Cobicistat (Tybost): A newer booster used for PIs and INSTIs.

PK Boosters Clinical Summary: Drugs, Indications, Dosages, Contraindications & Side Effects

Common DrugsIndicationsStandard Adult DosagesContraindicationsMajor Side Effects
Ritonavir (RTV)Boosting agent for PIs (LPV, ATV, DRV)100-200 mg per day alongside the primary PICo-administration with amiodarone, simvastatin, rifampicin (massive CYP3A4 interactions)GI intolerance (nausea/diarrhea), lipid abnormalities, circumoral paresthesia (tingling around mouth).
Cobicistat (COBI)Boosting agent for INSTIs (Elvitegravir) or PIs (DRV, ATV)150 mg once daily alongside primary drugCo-administration with highly dependent CYP3A4 drugsSlight increase in serum creatinine (without actual renal failure), GI upset.

🚨 NURSING ALERT: Ritonavir and Drug Interactions
Because Ritonavir intentionally breaks the liver's drug-clearing enzyme, it interacts with ALMOST EVERYTHING. Always ask patients about ALL medications they take, including herbal remedies. Common dangerous interactions: TB drugs (rifampicin), hormonal contraceptives (makes them fail!), and statin cholesterol drugs.

MODULE 4: ARV REGIMENS USED IN UGANDA

4.1 First-Line ART Regimens

What is First-Line? First-line regimens are the FIRST combination of drugs given to a person newly diagnosed with HIV. Uganda follows WHO guidelines.

PREFERRED FIRST-LINE REGIMEN (Adults & Adolescents ≥30 kg):

TLD = TDF + 3TC + DTG

  • TDF = Tenofovir Disoproxil Fumarate (NRTI Backbone)
  • 3TC = Lamivudine (NRTI Backbone)
  • DTG = Dolutegravir (INSTI Anchor)

Why TLD is Preferred:

  • One pill, once daily (Fixed Dose Combination).
  • High effectiveness & high barrier to resistance.
  • Fewer side effects than EFV (Efavirenz).
  • Safe in pregnancy and breastfeeding.
  • Affordable for Uganda's national program.

Dosing Instructions: One tablet once daily, with or without food. Take at the SAME TIME every day.

Alternative RegimenWhen to Use It (Clinical Rationale)
TAF + FTC + DTGIf the patient develops severe kidney disease or bone osteoporosis from TDF.
TDF + 3TC + EFV 400mgIf DTG is totally out of stock or specifically contraindicated.
ABC + 3TC + DTGIf TDF is contraindicated (e.g., existing kidney disease with GFR < 60 mL/min).

When to Use EFV Instead of DTG:

  • Severe depression or active psychosis (DTG rarely can worsen mood).
  • Neurological disease where DTG side effects cannot be assessed.
  • Concurrent use of benzodiazepines or carbamazepine (seizure drugs that interact heavily).
  • Severe liver disease.
  • HIV/TB co-infection using bedaquiline (MDR-TB drug).
  • When hormonal contraception is the only family planning method available (though guidelines on this are constantly evolving).

When to Use ABC (Abacavir) Instead of TDF:

  • Kidney disease (GFR < 60 mL/min). TDF destroys tubules; ABC is safely metabolized by the liver.
  • Adolescents below 35 kg.

Crucial Clinical Rule: You MUST test for the HLA-B*5701 gene first! If the patient is positive, NEVER give ABC. It will trigger a massive Type IV Hypersensitivity reaction (fever, rash, respiratory failure) that is frequently fatal upon rechallenge!

4.2 First-Line for Special Populations

Pregnant and Breastfeeding Women:

  • Preferred: TDF + 3TC + DTG (Exactly the same as adults).
  • Start ART on the SAME DAY as diagnosis to protect the baby!
  • Viral load is checked at 3 months after starting, then every 3 months until the end of breastfeeding.
  • If already on TLE (TDF+3TC+EFV) and viral load is perfectly suppressed, stay on it until 6–9 months postpartum, then seamlessly switch to TLD.

Children Under 3 Years:

  • Preferred: ABC + 3TC + LPV/r
  • LPV/r is preferred because it comes in a liquid/pellet formulation (easier to swallow) and has a very high barrier to resistance for babies who spit up medicine.

Children 3–10 Years:

  • Preferred: ABC + 3TC + EFV (or DTG if available in pediatric dosing).
  • Use NVP only if EFV is strictly contraindicated.

4.3 Second-Line ART Regimens

When Do We Switch to Second-Line?

  • When viral load is NOT suppressed after intensive adherence counseling.
  • When there is confirmed treatment failure (defined as two consecutive viral loads > 1,000 copies/mL).
  • When there is severe drug toxicity that cannot be medically managed.

Principle of Switching:

  • Change the anchor drug (the "third drug") — usually stepping up from an NNRTI/INSTI (EFV/DTG) to a powerful boosted Protease Inhibitor (PI).
  • Keep or swap the NRTI backbone (If they were on TDF, switch to AZT. If they were on AZT, switch to TDF).
If First-Line Was:Second-Line Becomes:
TDF + 3TC + DTG/EFVAZT + 3TC + ATV/r or LPV/r
AZT + 3TC + DTG/EFVTDF + 3TC + ATV/r or LPV/r

Note: DRV/r (Darunavir/Ritonavir) is the preferred PI in the 2026 WHO updates! Always use boosted PIs to ensure 24-hour coverage.

4.4 Third-Line ART Regimens

When Do We Use Third-Line?

  • When a patient clinically and virologically fails second-line therapy.
  • When there is extensive multi-drug resistance.

Third-Line Options:

  • Rule: Use drugs from NEW classes the patient has never seen before.
  • Requires genotypic resistance testing (mapping the exact mutations in the patient's HIV).
  • May include: DRV/r + RAL (Integrase) + ETR (Etravirine), or Entry inhibitors depending on the resistance profile.

❓ Clinical Scenario: Treatment Failure & 3rd Line
Case: A 42-year-old man has been on second-line AZT+3TC+LPV/r for 2 years. His viral load is 45,000 copies/mL. He swears he takes his medication daily.
Nursing Action: As a nurse, you know this is definitive treatment failure. The doctor orders a resistance test. The results show massive resistance to both NRTIs and PIs. The patient is switched to a highly complex third-line regimen with new drugs (e.g., DRV/r + RAL + ETR). You must provide intensive, empathetic adherence counseling because third-line options are limited—if this fails, he has no backup options left!

MODULE 5: NURSING MANAGEMENT OF ARVs

5.1 Before Starting ART (Pre-ART Assessment)

As a nurse, you must meticulously assess the patient BEFORE giving the first dose to prevent fatal complications (like IRIS - Immune Reconstitution Inflammatory Syndrome).

  1. Clinical Assessment:
    • Check for opportunistic infections (TB, cryptococcal meningitis, pneumonia).
    • Crucial Rule: If TB or cryptococcal meningitis is present, START treatment for the OI first, then begin ART after 2–8 weeks. (Starting ART immediately wakes up the immune system too fast, causing massive inflammation that can kill the patient).
    • Check WHO clinical stage.
    • Check CD4 count and viral load.
  2. Laboratory Tests (and WHY we do them):
    • HIV test: Confirm diagnosis before starting lifelong therapy.
    • CD4 count & Viral load: Baseline to measure future success.
    • Hemoglobin: Check for baseline anemia, especially before prescribing AZT (which causes bone marrow suppression).
    • Creatinine and eGFR: Check kidney function before prescribing TDF (which clears through and can damage renal tubules).
    • Liver function tests (LFTs): Before prescribing NVP or EFV (hepatotoxic).
    • Hepatitis B and C screening: Determines if TDF/3TC should be prioritized (they treat both!).
    • HLA-B*5701 test: Before ABC to prevent fatal hypersensitivity.
    • Pregnancy test: For women of childbearing age (guides regimen choice/counseling).
    • TB screening: (Cough, fever, weight loss, night sweats).
  3. Psychosocial Assessment:
    • Assess readiness to start ART (it is a lifelong commitment).
    • Check for depression, anxiety, substance use.
    • Assess social support (family, friends, partner).
    • Assess disclosure status (who knows their status?).
    • Assess food security (do they have food to take with drugs like LPV/r?).
  4. Adherence Preparation:
    • Use the ART readiness checklist.
    • Explain that ART is LIFELONG.
    • Explain the absolute importance of taking drugs at the SAME TIME every day to prevent viral mutation and resistance.
    • Discuss possible side effects and how to manage them. Provide a treatment buddy.

5.2 Patient Education (Counseling Points)

As a nurse, teach EVERY patient the following:

  1. How to Take ARVs:
    • Take at the SAME TIME every day. Do NOT miss doses. Do NOT share drugs with anyone.
    • Do NOT stop taking drugs, even if you feel better. (Feeling better means the drugs are working!).
    • If you miss a dose, take it as soon as you remember, unless it is almost time for the next dose (do not double dose).
  2. Food and ARVs:
    • DTG, TDF, 3TC (TLD): Can take with or without food.
    • EFV: Take on an EMPTY stomach (best at bedtime to sleep through the dizziness/CNS effects).
    • LPV/r, ATV/r: Take WITH food (increases absorption and reduces diarrhea).
    • RPV (Rilpivirine): MUST take WITH food (needs acidic environment).
  3. Side Effects to Report Immediately:
    • Severe rash with fever or blistering (SJS).
    • Yellow eyes or skin (jaundice/liver failure).
    • Severe stomach pain with vomiting (pancreatitis/lactic acidosis).
    • Shortness of breath. Severe muscle pain or weakness.
    • Signs of depression or suicidal thoughts (EFV toxicity).
  4. Drug Interactions:
    • Do NOT take herbal remedies without asking the doctor. Tell the nurse/doctor about ALL other medications.
    • Some ARVs interact with TB drugs, contraceptives, and traditional medicines.
  5. Pregnancy and Breastfeeding:
    • DTG is SAFE in pregnancy. Do NOT stop ART during pregnancy.
    • Breastfeeding is SAFE while on ART (if viral load is undetectable). The baby will also receive prophylaxis.
  6. U=U (Undetectable = Untransmittable):
    • If viral load is undetectable for 6+ months, you CANNOT transmit HIV through sex. This is a powerful message for reducing stigma!

5.3 Monitoring Patients on ART

Clinical Monitoring (At Every Visit): Weight, Blood pressure, General health and well-being, Signs of opportunistic infections, Side effects of ARVs, Adherence assessment.

Laboratory TestFrequency & Rationale
Viral loadAt 3 months after starting, then every 6–12 months. (The absolute gold standard for measuring treatment success).
CD4 countAt baseline, then every 6–12 months (if available). (Measures immune recovery).
Creatinine/eGFREvery 6 months (if on TDF).
Liver functionEvery 6 months (if on NVP or EFV).
Lipid profileEvery 6–12 months (if on Protease Inhibitors).
HemoglobinEvery 6 months (if on AZT).

🧠 MNEMONIC for Monitoring: "Viral Counts Create Liver Laughter"

  • Viral load
  • Counts (CD4 count)
  • Create (Creatinine)
  • Liver (Liver function)
  • Laughter (Lipid profile)

5.4 Managing Common Side Effects

Side EffectDrug(s) Causing ItNursing Management
Nausea/vomitingMost ARVsTake with food, small frequent meals, ginger tea.
DiarrheaLPV/r, most ARVsOral rehydration salts (ORS), increase fluids, low-fat diet.
Headache & InsomniaEFV, DTGParacetamol, rest, hydration. Take EFV at bedtime, avoid caffeine.
RashNVP, EFVMild: antihistamines; Severe: stop drug, refer immediately.
Weight gainDTG, TAFDiet counseling, exercise, monitor weight.
Lipodystrophyd4T (old), PIsSwitch drug if possible, exercise.
Kidney & Bone problemsTDFMonitor creatinine, calcium, vitamin D. Switch to TAF.
Liver problemsNVP, EFV, PIsMonitor LFTs, stop if severe.

5.5 Adherence Support

Why Adherence is CRITICAL: Missing even a few doses drops the drug concentration in the blood. HIV rapidly mutates to survive this low drug level, leading to drug resistance. Once resistance develops, the drug may NEVER work again. Uganda has limited and expensive third-line options.

Strategies to Improve Adherence:

  1. Education: Explain WHY adherence matters. Use visual aids/diagrams. Involve family members or treatment buddies.
  2. Practical Support: Pillboxes with days of the week, phone alarms, community health worker linkage.
  3. Address Barriers: Transport (Provide multi-month drugs), Stigma (Counsel on disclosure, provide privacy), Side effects (Manage early), Mental health (Screen for depression).
  4. Differentiated Service Delivery (DSD): Stable patients (viral load suppressed > 1 year) can get:
    • Longer drug refills (3–6 months)
    • Community drug distribution / Fast-track refill lines
    • Reduced clinic visits and Peer support groups.

MODULE 6: PHARMACOVIGILANCE (DRUG SAFETY MONITORING)

What is Pharmacovigilance? It means "watching over drugs" — monitoring and reporting side effects to keep patients safe. In Uganda, ARVs are given to millions of people. New drugs (like DTG) need ongoing safety monitoring because rare side effects may only appear after long-term population use. Reporting via the "Yellow Card System" helps improve national guidelines.

6.2 Common Drug Toxicities (High Yield!)

ToxicitySigns/SymptomsCommon CausesNursing Action
AnemiaPale skin, fatigue, shortness of breathAZTCheck hemoglobin, switch drug if severe.
Liver toxicityYellow eyes/skin, dark urine, abdominal painNVP, EFV, PIs, TB drugsStop drug, check LFTs.
Kidney toxicitySwelling, reduced urine, fatigueTDFCheck creatinine, switch to TAF.
Lactic acidosisDeep breathing, muscle pain, weaknessd4T, AZTEMERGENCY — stop NRTIs, refer.
HypersensitivityFever, rash, muscle pain, flu-likeABC (if HLA-B*5701 positive)STOP immediately, never rechallenge!
Psychiatric effectsDepression, suicidal thoughts, vivid dreamsEFVSwitch to DTG.

How to Report: Recognize → Document → Report (Yellow card) → Manage → Follow up.

MODULE 7: SPECIAL CONSIDERATIONS FOR UGANDAN COMMUNITIES

7.1 HIV and TB Co-Infection:

  • Why It Matters: TB is the leading cause of death among people with HIV in Uganda (~40% co-infection rate).
  • Management: Screen ALL HIV patients for TB at every visit. If TB is diagnosed, start TB treatment FIRST. Start ART 2–8 weeks after starting TB treatment.
  • Drug Interactions: Rifampicin (TB drug) heavily induces CYP3A4, destroying ARV levels. Use rifabutin instead if available. If not, and patient needs a PI, use double-dose LPV/r.

7.2 HIV and Hepatitis B Co-Infection:

  • Management: Screen ALL HIV patients for Hepatitis B. If positive, specifically use TDF + 3TC (or FTC) in their regimen because these drugs treat BOTH viruses.
  • Physiological Danger: NEVER stop TDF or 3TC suddenly in Hep B patients! The Hepatitis B virus will rebound massively, causing a severe, potentially fatal "hepatic flare" (liver failure).

7.3 Prevention of Mother-to-Child Transmission (eMTCT):

  • The Four Approaches: 1. Primary prevention, 2. Prevent unintended pregnancies, 3. Prevent transmission (ART), 4. Treatment and support.
  • For the Baby: All HIV-exposed babies get NVP (Nevirapine) prophylaxis for 6 weeks (low risk) or 12 weeks (high risk). High-risk babies get triple drug prophylaxis (ABC + 3TC + LPV/r).
  • Testing the Baby: DNA PCR testing at 4–6 weeks, 9 months, and 6 weeks after stopping breastfeeding. Rapid antibody test at 18 months.

7.4 Adolescents and Young People:

  • Challenges: Stigma, difficulty disclosing status, peer pressure, substance use, transitioning to adult care.
  • Nursing Strategies: Adolescent-friendly clinic hours, peer support groups, comprehensive sexuality education, tech reminders (SMS).

MODULE 8: EXAM TIPS AND QUICK REVIEW

Key FactExam Answer
Preferred first-line in Uganda (adults)TDF + 3TC + DTG (TLD)
Preferred first-line in pregnancyTDF + 3TC + DTG
Preferred first-line in children <3 yearsABC + 3TC + LPV/r
When to start ARTSAME DAY as diagnosis (if no TB/crypto)
Goal of ARTUndetectable viral load
What does U=U mean?Undetectable = Untransmittable
Test before giving ABCHLA-B*5701
Most common side effect of LPV/rDiarrhea
Most common side effect of EFVVivid dreams, dizziness
Drug to avoid in first trimesterEFV

MODULE 9: CLINICAL SCENARIOS FOR PRACTICE

🩺 Scenario 1: Newly Diagnosed Adult

Case: John, 28 years old, is newly diagnosed with HIV. His CD4 is 320, viral load is 45,000. He has no TB symptoms. He is not pregnant.

Answer: Start TLD (TDF + 3TC + DTG) same day. Counsel on adherence and side effects (insomnia, weight gain). Schedule viral load at 3 months. Provide condoms.

🩺 Scenario 2: Pregnant Woman with TB symptoms

Case: Mary, 24 years old, is 16 weeks pregnant and newly diagnosed with HIV. She has a cough and fever.

Answer: Screen for TB immediately. If NO TB: Start TLD same day. If TB is found: Start TB treatment first, start ART after 2 weeks. Counsel on exclusive breastfeeding for 6 months and ensure baby gets NVP prophylaxis at birth.

🩺 Scenario 3: Suspected Treatment Failure

Case: Peter has been on TLD for 2 years. His viral load is 8,500 copies/mL. He says he takes his drugs every day.

Answer: Do NOT switch immediately! Provide Intensive Adherence Counseling (IAC) for 3 months. Repeat viral load. If still not suppressed → switch to second-line (AZT + 3TC + ATV/r or LPV/r). Since he is on DTG, true resistance is rare — poor adherence is highly likely the real cause.

🩺 Scenario 4: Side Effect Management

Case: Grace, 35, on TLD for 6 months, complains she cannot sleep and has gained 7 kg. She wants to stop the drugs.

Answer: Reassure her — do NOT stop ART. For Insomnia: Take DTG in the morning instead of evening. For Weight gain: Counsel on diet and brisk walking. Monitor weight monthly.

MODULE 10: THE NURSE'S ROLE IN ARV THERAPY

10.1 Core Nursing Responsibilities:

  • Screening & Testing: Offer tests, link to care.
  • Initiation & Counseling: Use readiness checklist, offer same-day start.
  • Monitoring & Adherence Support: Track viral load, use pillboxes, manage side effects early.
  • Psychosocial & Prevention: Screen for depression, promote U=U, offer family planning.

📋 The 5 Rights of Medication Administration (Applied to ARVs)

  • Right Patient: Confirm HIV status, check identity.
  • Right Drug: Verify the regimen (TLD vs. TLE).
  • Right Dose: One tablet once daily (for most fixed-dose combos).
  • Right Route: Oral (swallow with water).
  • Right Time: Same time every day! (Crucial for ARVs).
  • PLUS the 6th Right: Right Documentation: Record every drug, side effect, and counseling session.

🏆 FINAL EXAM TIP for Pharmacology:
When answering pharmacology questions about ARVs, always structure your thought process:

  • Mechanism: Which step of HIV life cycle does it block?
  • Side effects: What should the nurse monitor for? (e.g., Creatinine for TDF).
  • Interactions: What other drugs affect it? (e.g., Rifampicin vs. PIs).
  • Nursing implications: What must the nurse teach, assess, and document?

REFERENCES

  • World Health Organization (WHO) Consolidated Guidelines on HIV Prevention, Testing, Treatment, Service Delivery and Monitoring (2021/2026 updates).
  • Ministry of Health Uganda: Consolidated Guidelines for the Prevention and Treatment of HIV and AIDS.
  • Standard Nursing Pharmacology Textbooks on Antiretroviral Mechanisms and Patient Management.

Quick Quiz

ARV\'s Quiz

Pharmacology

Privacy: Your details are used only for quiz tracking and certificates.

ANTIRETROVIRAL DRUGS (ARVs) Pharmacology Read More »

Anti-Helminths

Anti-Helminths Agents

Anti-Helminths

📌 SECTION 1: INTRODUCTION TO HELMINTH INFECTIONS

1.1 What Are Helminths?

Helminths are parasitic worms that infect humans. The word "helminth" comes from Greek meaning "worm." These worms live inside the human body (intestines, blood, tissues, skin) and cause disease called helminthiasis.

1.2 Why This Matters for Ugandan Communities

  • Uganda has a high burden of helminth infections, especially in rural areas with poor sanitation and limited access to clean water.
  • School-age children are the most affected group.
  • These infections cause malnutrition, anemia, stunted growth, and poor school performance.
  • Nurses are on the front line — you will be giving these drugs during mass deworming campaigns!

1.3 Types of Helminths (The "Big Three" Groups)

GroupCommon NameExamplesWhere They Live
NematodesRoundwormsAscaris lumbricoides (roundworm), Ancylostoma/Necator (hookworm), Trichuris trichiura (whipworm), Enterobius vermicularis (pinworm), Strongyloides stercoralis, Wuchereria bancrofti (causes elephantiasis)Intestines, blood, lymph
TrematodesFlukesSchistosoma mansoni (intestinal), Schistosoma haematobium (urinary/blood)Blood vessels, liver, bladder
CestodesTapewormsTaenia solium (pork tapeworm), Taenia saginata (beef tapeworm), Hymenolepis nana (dwarf tapeworm)Intestines, tissues (cysts)

1.4 How Do People Get Infected?

  • Soil-transmitted helminths (STH): Walking barefoot on contaminated soil (hookworm), eating unwashed vegetables (roundworm), poor hand hygiene (pinworm).
  • Water contact: Swimming or washing in infected water (Schistosoma — bilharzia).
  • Undercooked meat: Eating pork or beef with larvae (tapeworms).
  • Blackfly bites: Near fast-flowing rivers (Onchocerca volvulus — river blindness).

1.5 Why Treat Helminth Infections?

Untreated infections cause:

  • Malnutrition (worms steal nutrients)
  • Iron-deficiency anemia (hookworms suck blood)
  • Cognitive impairment in children
  • Blindness (onchocerciasis)
  • Liver fibrosis and bladder cancer (schistosomiasis)
  • Death in severe cases

📌 SECTION 2: OVERVIEW OF ANTIHELMINTIC DRUGS

2.1 What Are Anthelmintic Drugs?

These are medicines that kill (vermicide) or paralyze and expel (vermifuge) parasitic worms from the human body.

2.2 Key Principle: Selective Toxicity

Anthelmintic drugs are designed to harm the worm but NOT the human. They target processes that exist in the worm but are different or absent in humans.

2.3 Two Main Actions

TermMeaningExample
VermicideKills the wormAlbendazole, Praziquantel
VermifugeParalyzes the worm so it is expelled in stoolPiperazine, Pyrantel pamoate

2.4 Classification of Anthelmintic Drugs

We will study them by the type of worm they treat (Nematodes, Trematodes, Cestodes, Filarial).

📌 SECTION 3: DRUGS FOR NEMATODES (ROUNDWORMS)

Summary Table of Nematode Drugs (as requested):

Common DrugsIndicationsDosages (Common)ContraindicationsSide Effects
AlbendazoleAscariasis, Hookworm, Whipworm, Pinworm, Strongyloidiasis, Neurocysticercosis, Hydatid disease400 mg once (STH); 400 mg BID for systemicPregnancy, hypersensitivity, children < 2 yrs (caution)Stomach pain, nausea, dizziness, bone marrow suppression, liver damage, seizures (in CNS cysts)
MebendazoleRoundworm, hookworm, whipworm, pinworm100 mg BID x 3 days OR 500 mg single dosePregnancy (1st trimester), children < 2 yrsStomach pain, diarrhea. Rare: Liver issues, Stevens-Johnson syndrome
IvermectinOnchocerciasis, Strongyloidiasis, Scabies, Head lice150 mcg/kg single oral dose (repeated 6-12 months)Pregnancy, breastfeeding (caution), < 5 yrs or < 15 kg, Loa loa co-infectionMazzotti reaction (fever, rash, headache, muscle pain)
Pyrantel PamoateAscariasis, Enterobiasis (pinworm), Hookworm11 mg/kg (max 1 g) single doseMinimal contraindications (very safe)Stomach upset (give with food)
LevamisoleAscariasis, hookwormVariesSevere kidney disease, pregnancyAgranulocytosis (dangerous drop in WBCs)
Piperazine CitrateAscariasis, EnterobiasisVariesEpilepsy (neurotoxicity)Neurotoxicity at high doses

3.1 ALBENDAZOLE ⭐ (First-Line for Most STH)

  • A. Basic Information: Generic name: Albendazole. Brand names: Zentel, Albenza. Class: Benzimidazole. Route: Oral (by mouth).
  • B. Mechanism of Action (How It Works):
    • Albendazole enters the worm's body.
    • It blocks glucose (sugar) uptake — the worm cannot eat!
    • The worm runs out of energy (ATP).
    • The worm becomes paralyzed, dies, and is passed out in stool.
  • C. Uses (Indications): Ascariasis (roundworm), Hookworm infection, Trichuriasis (whipworm), Enterobiasis (pinworm), Strongyloidiasis, Neurocysticercosis (tapeworm cysts in the brain), Hydatid disease (Echinococcus cysts in liver/lungs), Filariasis (in combination with other drugs).

D. Dosage (Adults and Children):

InfectionDoseDuration
Roundworm, hookworm, whipworm400 mg onceSingle dose
Pinworm400 mg onceSingle dose; repeat in 2 weeks
Neurocysticercosis400 mg twice daily8–30 days
Hydatid disease400 mg twice daily28-day cycles with 14-day breaks
  • E. Side Effects (Adverse Effects):
    • Common: Stomach pain, nausea, vomiting, headache, dizziness.
    • Serious (rare): Bone marrow suppression (low blood counts), Liver damage (yellow eyes/skin), Hair loss (alopecia), Seizures (if treating brain cysts — due to inflammation from dying parasites), Allergic reactions.
  • F. Contraindications (When NOT to Give): Pregnancy — can harm the baby (teratogenic), Hypersensitivity to benzimidazoles, Children under 2 years (use with caution).
  • G. Drug Interactions: Praziquantel increases albendazole's effect (often given together). Cimetidine, ketoconazole increase albendazole levels. Phenytoin, carbamazepine, rifampicin decrease albendazole levels.
  • H. Nursing Implications & Patient Teaching:
    • Take with fatty meal — fat increases absorption!
    • Crush tablets for children who cannot swallow.
    • Wash hands before and after giving medication.
    • Repeat stool exam 2 weeks after treatment to confirm cure.
    • Treat the whole family for pinworm — it spreads easily!
    • Pregnancy test before giving to women of childbearing age.

💡 Clinical Scenario

Scenario: A 6-year-old boy in a rural village comes to the health center with a bloated belly and worms visible in his stool. The mother says he walks barefoot to the garden. You give albendazole 400 mg.

Your teaching to the mother:
"Give this medicine once. The worms will die and come out in the stool."
"Make him wear shoes to the garden."
"Wash all fruits and vegetables with clean water."
"Bring him back in 2 weeks for a stool check."

3.2 MEBENDAZOLE ⭐ (Alternative First-Line)

  • A. Basic Information: Generic name: Mebendazole. Brand names: Vermox, Emverm. Class: Benzimidazole. Route: Oral.
  • B. Mechanism of Action: Same as albendazole: inhibits microtubule formation and blocks glucose uptake. Leads to worm death and expulsion.
  • C. Uses: Roundworm, hookworm, whipworm, pinworm. Less effective than albendazole for tissue infections (like hydatid disease).

D. Dosage:

InfectionDoseDuration
Roundworm, hookworm100 mg twice daily OR 500 mg3 days OR single dose
Whipworm100 mg twice daily3 days
Pinworm100 mg onceSingle dose; repeat in 2 weeks
  • E. Side Effects: Stomach pain, diarrhea, headache. Rare but serious: Liver problems, bone marrow suppression, Stevens-Johnson syndrome (severe skin rash).
  • F. Contraindications: Pregnancy — avoid in first trimester. Children under 2 years. Hypersensitivity to benzimidazoles.
  • G. Nursing Implications: Can be chewed, swallowed whole, or crushed and mixed with food. No special diet needed — unlike albendazole, fat does not affect absorption much. Monitor for signs of bone marrow suppression: unusual bleeding, bruising, fatigue, fever.

3.3 IVERMECTIN ⭐ (For River Blindness & Strongyloidiasis)

  • A. Basic Information: Generic name: Ivermectin. Brand name: Mectizan® (donated free by Merck for onchocerciasis). Class: Macrocyclic lactone (avermectin). Route: Oral.
  • B. Mechanism of Action:
    • Ivermectin binds to glutamate-gated chloride channels in the worm's nerve and muscle cells.
    • This is a channel found ONLY in invertebrates (worms, insects) — NOT in humans!
    • Chloride enters the cell ➔ hyperpolarization ➔ paralysis ➔ worm dies.
  • C. Uses: Onchocerciasis (river blindness) — drug of choice. Strongyloidiasis — drug of choice. Scabies (topical or oral). Head lice. Ascariasis (some effect). Filariasis (in combination).
  • D. Dosage for Onchocerciasis: 150 micrograms per kg body weight — single oral dose. Given once every 6–12 months for 10–15 years (to cover the adult worm lifespan). In some high-transmission areas, given twice per year.
  • E. Side Effects (Crucial!): Mazzotti reaction: This happens when microfilariae die. Symptoms include: Fever, headache, muscle pain, itching, rash, swollen lymph nodes, eye inflammation, low blood pressure (rare). Usually mild and self-limiting. Treat with antihistamines or steroids if severe.
  • F. Contraindications: Pregnancy — safety not established. Breastfeeding — use with caution. Children under 5 years or under 15 kg. Loa loa co-infection — can cause severe brain inflammation (encephalopathy)! Always check for Loa loa in co-endemic areas before giving ivermectin.
  • G. Nursing Implications:
    • Weigh the patient accurately — dose is based on body weight!
    • Give on an empty stomach with water.
    • Observe for Mazzotti reaction — especially in first 3 days.
    • Community-Directed Treatment (CDTI): In Uganda, community health workers distribute ivermectin. Nurses train and supervise them.
    • Do NOT give to someone with severe eye disease without ophthalmology consultation.

💡 Clinical Scenario (Uganda Context)

Scenario: A 45-year-old man from a village near the Nile River presents with severe itching, skin nodules on his hips, and failing vision. He has been scratching himself with stones because the itch is unbearable. This is classic onchocerciasis.

Nursing action:
Weigh him: 60 kg ➔ dose = 60 × 150 mcg = 9,000 mcg = 9 mg.
Give ivermectin orally.
Warn him: "You may feel more itchy and have a fever for 2–3 days — this means the medicine is working!"
Arrange follow-up in 6–12 months.
Teach the community about blackfly breeding near rivers.

3.4 PYRANTEL PAMOATE

  • Mechanism: Acts as a depolarizing neuromuscular blocker. Mimics acetylcholine at the worm's muscle receptors causing spastic paralysis. Worm is expelled alive in stool.
  • Uses: Ascariasis, Enterobiasis (pinworm), Hookworm.
  • Dosage: 11 mg/kg (max 1 g) — single dose. For pinworm: repeat in 2 weeks.
  • Nursing: Give with food to reduce stomach upset. No fasting or purging needed. Stool may contain live worms — reassure the patient this is normal! Very safe due to minimal absorption.

3.5 LEVAMISOLE

  • Mechanism: Acts as an agonist at nicotinic acetylcholine receptors causing spastic paralysis. Worm is expelled.
  • Uses: Ascariasis, hookworm. (Also used as an immunostimulant in some cancers).
  • Side Effects: Agranulocytosis (dangerous drop in WBCs) — rare but serious. Contraindicated in severe kidney disease and pregnancy.

3.6 PIPERAZINE CITRATE

  • Mechanism: Acts as a weak GABA-mimetic. Causes flaccid paralysis (relaxed, floppy paralysis) of the worm.
  • Uses: Ascariasis, Enterobiasis.
  • Drug Interaction: Do NOT give with pyrantel — they have opposite effects (antagonistic).
  • Contraindication: Neurotoxicity at high doses. Contraindicated in epilepsy!

📌 SECTION 4: DRUGS FOR TREMATODES (FLUKES / SCHISTOSOMES)

Summary Table of Trematode Drugs (as requested):

Common DrugsIndicationsDosages (Common)ContraindicationsSide Effects
PraziquantelSchistosomiasis (all types), Tapeworms, Neurocysticercosis40 mg/kg single oral dose (divided); 60 mg/kg for heavy infectionOcular cysticercosis (cysts in eye)Stomach pain, nausea, fever/itching (from dying worms), seizures in CNS infection

4.1 PRAZIQUANTEL ⭐ (Drug of Choice for All Schistosomiasis & Tapeworms)

  • A. Basic Information: Generic name: Praziquantel. Brand names: Biltricide, Cysticide. Class: Pyrazinoisoquinoline derivative. Route: Oral.
  • B. Mechanism of Action:
    • Praziquantel enters the worm.
    • It increases calcium permeability in the worm's muscles.
    • The worm has violent muscle contractions (tetanic paralysis).
    • The worm's tegument (outer covering) is damaged. The worm is attacked by the host's immune system and dies.
    • Worms dislodge from blood vessels and are carried to the liver, where they are destroyed.
  • C. Uses: All types of schistosomiasis (S. mansoni, S. haematobium). All tapeworm infections (Pork, Beef, Dwarf, Fish tapeworms). Neurocysticercosis (with albendazole).
  • D. Dosage for Schistosomiasis: 40 mg/kg — single oral dose (divided into 2 doses, 4 hours apart). For heavy infections: 60 mg/kg divided over 1 day.
  • E. Side Effects:
    • Common: Stomach pain, nausea, drowsiness.
    • Due to dying parasites: Fever, itching, increased eosinophils.
    • Neurocysticercosis: Headache, seizures, increased intracranial pressure. Give steroids (dexamethasone) and anticonvulsants alongside!
  • F. Contraindications: Ocular cysticercosis (cysts in the eye) — can cause blindness if cysts burst.
  • H. Nursing Implications:
    • Give after meals — food increases absorption.
    • Tablets should be swallowed whole — do NOT chew (very bitter taste causes vomiting).
    • Mass treatment in Uganda: The Ministry of Health gives praziquantel to schoolchildren in endemic areas (e.g., Masindi District).

💡 Clinical Scenario (Uganda Context)

Scenario: A 12-year-old girl from a fishing village on Lake Victoria has blood in her urine and lower abdominal pain. Stool exam shows S. haematobium eggs. This is urinary schistosomiasis (bilharzia).

Nursing action: Give praziquantel 40 mg/kg. Divide into 2 doses, 4 hours apart. Tell her: "Take this medicine with food. Do not chew the tablet. You may feel a little sick or itchy — this is the worms dying." Teach the family to stop washing in the lake and use pit latrines.

📌 SECTION 5: DRUGS FOR CESTODES (TAPEWORMS)

Summary Table of Cestode Drugs (as requested):

Common DrugsIndicationsDosages (Common)ContraindicationsSide Effects
NiclosamideBeef, Fish, and Dwarf tapeworm; Pork tapeworm (adults only)2 g single doseNot effective for cysts (cysticerci)Abdominal pain, GI upset

5.1 NICLOSAMIDE

  • Mechanism: Inhibits oxidative phosphorylation in the worm's mitochondria. Blocks ATP production. Worm runs out of energy and dies.
  • Uses: Beef, Fish, and Dwarf tapeworm. Pork tapeworm (but does NOT kill larvae/cysticerci, so praziquantel is preferred).
  • Dosage & Administration: 2 g single dose. Must be CHEWED thoroughly before swallowing.
  • Nursing: Give on an empty stomach. Stool will contain dead worm segments — reassure patient.

📌 SECTION 6: DRUGS FOR FILARIAL WORMS (LYMPHATIC FILARIASIS)

Summary Table of Filarial Drugs (as requested):

Common DrugsIndicationsDosages (Common)ContraindicationsSide Effects
Diethylcarbamazine (DEC)Lymphatic filariasis (elephantiasis), Loiasis (eye worm)Varies depending on weight/protocolOnchocerciasis (causes severe eye damage)Mazzotti-like reaction, Encephalopathy in heavy Loa loa

6.1 DIETHYLCARBAMAZINE (DEC)

  • Mechanism: Alters microfilarial membrane — makes them more susceptible to host immune attack. Does NOT kill adult worms directly.
  • Uses: Lymphatic filariasis (elephantiasis), Loiasis (eye worm).
  • Side Effects: Mazzotti-like reaction. Encephalopathy in heavy Loa loa infection — very dangerous!
  • Contraindications: Onchocerciasis — can cause severe eye damage! Always rule out onchocerciasis and loiasis before giving DEC!

📌 SECTION 7: COMPARISON TABLE OF ALL MAJOR ANTIHELMINTICS

DrugWorms TreatedMechanismKey Side EffectSpecial Nursing Note
AlbendazoleRoundworm, hookworm, whipworm, pinworm, cystsBlocks glucose uptakeBone marrow suppression, liver damageTake with fatty food; avoid in pregnancy
MebendazoleRoundworm, hookworm, whipworm, pinwormBlocks glucose uptakeLiver damageCan chew or crush tablets
IvermectinOnchocerciasis, strongyloidiasis, scabiesOpens chloride channels ➔ paralysisMazzotti reactionDose by weight; avoid in Loa loa
PraziquantelAll schistosomes, all tapewormsIncreases calcium ➔ violent paralysisSeizures (in neurocysticercosis)Swallow whole; give with food
Pyrantel pamoateRoundworm, pinworm, hookwormSpastic paralysisNausea, vomitingMinimal absorption; very safe
NiclosamideTapeworms (intestinal only)Blocks ATP productionAbdominal painChew thoroughly; does NOT treat cysts
DECFilarial worms (lymphatic filariasis, loiasis)Alters microfilarial membraneMazzotti reaction, encephalopathyRule out onchocerciasis first!

📌 SECTION 8: NURSING MANAGEMENT & PATIENT EDUCATION

  • General Assessment: Confirm diagnosis. Check pregnancy status. Weigh patient (for ivermectin). Assess nutritional status.
  • During Administration: Give correct dose (underdosing leads to resistance!). Observe for anaphylaxis. Keep accurate records during Mass Drug Administration (MDA).
  • After Administration: Monitor for Mazzotti reaction, seizures, or liver problems. Repeat stool/urine exam 2–4 weeks after treatment.

Patient Education (WASH Strategy):

  1. Wash hands with soap.
  2. Wear shoes to prevent hookworm.
  3. Wash fruits/vegetables with clean, boiled water.
  4. Cook meat thoroughly (no pink pork/beef).
  5. Use pit latrines; do not defecate in open areas.
  6. Treat the whole family for pinworm!

📌 SECTION 9: MASS DRUG ADMINISTRATION (MDA) IN UGANDA

  • What is MDA? Giving anthelmintic drugs to entire communities/schools without individual diagnosis. Done for STH, Schistosomiasis, Onchocerciasis, and Lymphatic Filariasis.
  • Uganda's Deworming Program: Biannual distribution to school-age children using Albendazole 400 mg or Mebendazole 500 mg. Approx 17 million tablets needed for 2025.
  • CDTI (Community-Directed Treatment with Ivermectin): Community health workers (CHWs) go house-to-house. Nurses provide training and supervise adverse events.

📌 SECTION 10: MNEMONICS & MEMORY AIDS

🧠 Mnemonic for Benzimidazoles (Albendazole, Mebendazole)

"A & M BLOCK SUGAR"

  • Albendazole & Mebendazole
  • BLOCK glucose uptake
  • SUGAR = the worm starves to death!

🧠 Mnemonic for Ivermectin Mechanism

"Ivermectin CLAMPS the worm"

  • Chloride enters
  • Locks the channel
  • Acts on glutamate receptors
  • Makes the worm paralyzed
  • Permanent paralysis ➔ death
  • Selective for invertebrates only!

🧠 Mnemonic for Praziquantel

"PRAZI = CRAZY CALCIUM"

  • PRAZIquantel causes CRAZY muscle spasms because CALCIUM floods into the worm. Worm goes crazy and dies!

🧠 Mnemonic for Side Effects to Watch

"The 3 M's of Anthelmintics"

  • 1. Mazzotti reaction (ivermectin, DEC)
  • 2. Marrow suppression (albendazole, mebendazole)
  • 3. Metabolic upset / Liver (all benzimidazoles)

📌 SECTION 11: EXAM TIPS & COMMON QUESTIONS

  • Q: What is the drug of choice for onchocerciasis (river blindness)?
    A: Ivermectin. Given as 150 mcg/kg orally, once every 6–12 months for 10–15 years.
  • Q: What is the drug of choice for all types of schistosomiasis?
    A: Praziquantel. 40 mg/kg single oral dose.
  • Q: A patient develops fever, itching, and swollen lymph nodes 2 days after ivermectin. What is this?
    A: Mazzotti reaction — caused by dying microfilariae. Treat with antihistamines or steroids.
  • Q: Why must you check for Loa loa before giving ivermectin?
    A: Ivermectin can cause severe encephalopathy (brain inflammation) in patients with heavy Loa loa infection.
  • Q: Which anthelmintic should be taken with a fatty meal?
    A: Albendazole — fat increases its absorption.
  • Q: Why is praziquantel NOT used for ocular cysticercosis?
    A: Dying cysts in the eye can cause severe inflammation and blindness. Surgical removal is preferred.

📌 SECTION 12: QUICK REFERENCE FOR CLINICAL PRACTICE

When You See This SymptomThink This WormGive This Drug
Itchy anus at night (children)PinwormAlbendazole / Mebendazole / Pyrantel
Worms in stool, bloated bellyRoundwormAlbendazole / Mebendazole
Blood in urine, lower abdominal painS. haematobium (urinary schisto)Praziquantel
Blood in stool, liver enlargementS. mansoni (intestinal schisto)Praziquantel
Severe itching, skin nodules, vision lossOnchocerca volvulus (river blindness)Ivermectin
Cough, wheezing, larvae in sputumStrongyloidesIvermectin
Seizures, brain cysts on CT scanTaenia solium cysticerciAlbendazole + Praziquantel + Steroids
Massive leg swelling (elephantiasis)Wuchereria bancroftiDEC + Albendazole

📌 SECTION 13: ADVERSE REACTIONS MANAGEMENT

ReactionDrug(s)Management
Mazzotti reactionIvermectin, DECAntihistamines, steroids, rest, fluids
Severe allergic reactionAny anthelminticStop drug, adrenaline, oxygen, IV fluids, call doctor
SeizuresAlbendazole/Praziquantel (for neurocysticercosis)Give anticonvulsants (phenytoin), steroids, monitor airway
Liver damageAlbendazole, MebendazoleStop drug, check LFTs, supportive care
Bone marrow suppressionAlbendazole, MebendazoleStop drug, CBC, blood transfusion if severe

📌 SECTION 15: GLOSSARY OF TERMS

TermSimple Meaning
AnthelminticDrug that kills or expels worms
Vermicide / VermifugeKills the worm / Expels the worm (paralyzes it)
Microfilariae / MacrofilariaeBaby worms in the blood/skin / Adult worms
TegumentOuter skin/covering of the worm
HyperpolarizationMaking the cell too negative to fire — causes paralysis
Preventive chemotherapy (PC)Giving drugs to whole populations to prevent disease

✅ SECTION 16: SUMMARY CHECKLIST FOR NURSES

Before giving ANY anthelmintic, ask yourself:

  • Is the diagnosis confirmed?
  • Is the patient pregnant? (If yes, consult doctor first!)
  • Is the dose correct for body weight?
  • Are there any drug interactions?
  • Is there a risk of Mazzotti reaction? (ivermectin, DEC)
  • Do I need to give steroids alongside? (neurocysticercosis)
  • Have I educated the patient on prevention (WASH)?
  • Is follow-up scheduled for stool/urine re-check?

📚 REFERENCES & FURTHER READING

  • World Health Organization (WHO). (2017). Preventive chemotherapy to control soil-transmitted helminth infections in at-risk population groups. WHO Guidelines.
  • Katzung, B. G., & Trevor, A. J. (2020). Basic & Clinical Pharmacology (15th ed.). McGraw-Hill Education.
  • Ministry of Health Uganda. (2024). National Guidelines for Mass Drug Administration for Neglected Tropical Diseases.
  • Brunton, L. L., Hilal-Dandan, R., & Knollmann, B. C. (2017). Goodman and Gilman's The Pharmacological Basis of Therapeutics (13th ed.). McGraw-Hill Education.

Quick Quiz

Anti-Helminths Quiz

Pharmacology

Privacy: Your details are used only for quiz tracking and certificates.

Anti-Helminths Agents Read More »

Anti-Tuberculous Agents

Anti-Tuberculous Agents

Anti-Tuberculous Agents

SECTION 1: INTRODUCTION TO TUBERCULOSIS (TB)

1.1 What is Tuberculosis?

Tuberculosis (TB) is a contagious (spreadable) bacterial infection caused by Mycobacterium tuberculosis (also called the "tubercle bacillus"). It mainly attacks the lungs (pulmonary TB) but can also affect other parts of the body like the brain, spine, kidneys, and bones (extrapulmonary TB).

Key Points for Nurses:

  • Airborne Transmission: TB spreads when an infected person coughs, sneezes, or talks, releasing droplet nuclei into the air.
  • Latent vs. Active: Not everyone who gets infected becomes sick. Some people have latent TB (sleeping TB) where the bacteria are walled off by the immune system (granulomas) but are not causing symptoms. Active TB means the person is sick, symptomatic, and can spread the disease to others.
  • TB is one of the top 10 causes of death worldwide and remains a major public health problem in Uganda.

1.2 TB in Uganda – The Local Picture

Uganda is classified as a high-burden TB country. This means:

  • Many people in Uganda get TB every year.
  • TB and HIV often occur together (co-infection), as HIV depletes the CD4 T-cells needed to keep TB dormant.
  • The government, through the National Tuberculosis and Leprosy Program (NTLP), manages TB care.
  • Community health workers, nurses, and village health teams (VHTs) play a critical role in finding TB cases and supporting treatment.

Why Nurses Matter in TB Control:

  • Nurses are often the first point of contact for patients.
  • Nurses give Directly Observed Therapy (DOT) – physically watching patients take their medicine to ensure compliance.
  • Nurses educate families and communities about TB prevention and infection control.
  • Nurses monitor for severe adverse side effects and ensure patients complete the long treatment course.

1.3 Why Combination Therapy?

TB treatment always uses multiple drugs together, never just one drug. This is because:

  • Different mechanisms: Different drugs attack the bacteria in different ways – some kill quickly (bactericidal), some kill slowly (bacteriostatic).
  • Prevents drug resistance: Mycobacteria mutate rapidly. If you use only one drug, the bacteria will naturally mutate and survive it.
  • Improves cure rates: Using 4 drugs in the intensive beginning phase gives the best chance of killing all the rapidly dividing bacteria and penetrating the thick granulomas.
💡 Nursing Pearl: Think of it like using different weapons to fight a highly adaptable enemy. One weapon alone is not enough – you need an army of drugs! If a patient only takes 1 or 2 of their pills, they are actively creating Multidrug-Resistant TB (MDR-TB).

SECTION 2: CLASSIFICATION OF ANTI-TUBERCULOUS DRUGS

Anti-TB drugs are divided into groups based on how effective they are and when they are used.

2.1 First-Line Drugs (The "Main Team")

These are the most effective, best-tolerated drugs used for drug-susceptible TB (TB that responds to standard treatment).

DrugAbbreviationWhat It Does (Primary Action)
IsoniazidH (INH)Kills rapidly dividing bacteria
RifampicinR (RIF)Kills both active and "sleeping" bacteria
PyrazinamideZ (PZA)Kills bacteria in acidic environments (like inside macrophages)
EthambutolE (EMB)Stops bacteria from building their cell walls (bacteriostatic)
StreptomycinSInjectable; kills extracellular bacteria
🧠 Mnemonic for First-Line Drugs: "RIPE" for Success! R = Rifampicin, I = Isoniazid, P = Pyrazinamide, E = Ethambutol

2.2 Second-Line Drugs (The "Backup Team")

Used when first-line drugs fail or when the bacteria are resistant. These drugs are: Less effective, more toxic (more side effects), more expensive, and often given for longer periods (up to 18-24 months).

  • Group A (Fluoroquinolones) – Most effective second-line drugs: Levofloxacin, Moxifloxacin.
  • Group B (Injectable agents) – Given by injection: Amikacin, Kanamycin, Capreomycin.
  • Group C (Other core second-line agents) – Cycloserine, Ethionamide / Prothionamide, Para-aminosalicylic acid (PAS).
  • Group D (Add-on agents)
    • D1: Pyrazinamide, Ethambutol, High-dose Isoniazid.
    • D2: Bedaquiline, Linezolid, Delamanid, Clofazimine.
    • D3: Amoxicillin-clavulanate, Imipenem, Meropenem, Clarithromycin.

2.3 Newer Drugs (The "New Generation")

These are recently developed drugs for drug-resistant TB:

  • Bedaquiline (Bdq): First new anti-TB drug in 50 years!
  • Pretomanid (Pa): Used in combination with bedaquiline and linezolid (BPaL regimen).
  • Delamanid (Dlm): Another new oral drug.

SECTION 3: FIRST-LINE ANTI-TUBERCULOUS DRUGS (DETAILED)

3.1 ISONIAZID (INH, H)

Isoniazid is the most important first-line anti-TB drug. It is highly effective at killing rapidly growing TB bacteria.

  • Mechanism of Action: Prevents the bacteria from making mycolic acid – a special fatty acid that forms the unique, waxy outer wall of TB bacteria. Without mycolic acid, the bacteria cannot build their protective coat and they die. (Think of it like removing the bricks from a house – the house collapses!)
  • Pharmacokinetics:
    • Absorption: Well absorbed from the stomach when taken on an empty stomach.
    • Distribution: Goes everywhere in the body, including the brain (crosses the blood-brain barrier).
    • Metabolism: Broken down in the liver by enzymes (via acetylation).
    • Excretion: Removed from the body mainly through the kidneys in urine.
  • Dosing in Uganda: Adults = 10 mg/kg (max 300 mg/day). Children = 10 mg/kg (range 7-15 mg/kg).
  • Side Effects (Adverse Effects):
    • Peripheral Neuropathy: Numbness, tingling, or burning sensation in hands and feet. Why: Isoniazid uses up and promotes the excretion of vitamin B6 (pyridoxine). Prevention: Give pyridoxine 25-50 mg daily.
    • Hepatotoxicity (Liver Damage): Jaundice, dark urine, abdominal pain, nausea. Nursing action: Monitor LFTs. Stop drug if jaundice appears.
    • Other: Nausea, vomiting, rash, fever, joint pains.
  • Contraindications: Active liver disease, known allergy, severe liver damage.
  • Drug Interactions: Phenytoin (increases phenytoin levels ➔ toxicity), Warfarin (effect reduced by Rifampicin), Carbamazepine (levels increased).
  • Nursing Implications: Always give pyridoxine. Take on an empty stomach (1 hr before or 2 hrs after food). Monitor for signs of liver damage. Educate patient to report numbness/tingling immediately.
🧠 Mnemonic: "INH Needs Help (pyridoxine)"

3.2 RIFAMPICIN (RIF, R)

Rifampicin is a broad-spectrum antibiotic that kills both actively growing and "sleeping" TB bacteria. It is one of the most powerful anti-TB drugs.

  • Mechanism of Action: Blocks DNA-dependent RNA polymerase – the enzyme the bacteria need to transcribe DNA into mRNA to make proteins. Without RNA polymerase, the bacteria cannot communicate or reproduce (like cutting the phone line).
  • Pharmacokinetics:
    • Absorption: Well absorbed, but food reduces absorption.
    • Distribution: Reaches all tissues (brain, bones, lungs).
    • Metabolism & Excretion: Broken down in liver, removed mainly through bile (into stool) and some in urine.
  • Dosing in Uganda: Adults = 10 mg/kg (max 600 mg/day). Children = 15 mg/kg.
  • Side Effects:
    • Hepatotoxicity: Liver damage (especially when combined with INH and PZA).
    • Orange/Red Discoloration: Urine, sweat, tears, and saliva turn orange-red. Harmless, but patients MUST be warned to avoid panic. Contact lenses may be permanently stained.
    • Flu-like Syndrome: Fever, chills, muscle aches (usually with intermittent dosing).
    • GI Upset & Thrombocytopenia: Low platelet count (rare but serious).
  • Drug Interactions (VERY IMPORTANT!): Rifampicin is a strong CYP450 enzyme inducer – it speeds up the breakdown of many other drugs.
    • Oral contraceptives: Reduced effectiveness ➔ unplanned pregnancy (Use condoms/IUD).
    • Warfarin: Reduced anticoagulant effect (Monitor INR).
    • Nevirapine/Dolutegravir (HIV drugs): Reduced HIV treatment levels.
⚠️ Critical Nursing Point & Mnemonic: Always ask female patients about contraception before starting rifampicin! Mnemonic: "Rifampicin Rifles Through the Liver" – it speeds up the metabolism of many drugs, clearing them out of the body too fast!

3.3 PYRAZINAMIDE (PZA, Z)

Pyrazinamide is a unique drug that kills TB bacteria in acidic environments – like inside human macrophages where TB bacteria hide.

  • Mechanism of Action: Converted inside the bacteria into pyrazinoic acid. This disrupts the bacteria's ability to make energy and build cell walls. It is a special key that opens a locked door inside cells to kill dormant bacteria.
  • Dosing in Uganda: Adults = 30-40 mg/kg (max 2500 mg/day). Children = 35 mg/kg.
  • Side Effects:
    • Hyperuricemia (High Uric Acid): Causes gout-like joint pains. Why: PZA prevents the kidneys from removing uric acid. Manage with paracetamol/ibuprofen.
    • Hepatotoxicity: High risk when combined with INH and RIF.
    • Photosensitivity & Rash: Skin sensitive to sunlight.
🧠 Mnemonic: "Pyrazinamide Zaps bacteria in Zones (acidic zones inside cells)"

3.4 ETHAMBUTOL (EMB, E)

Ethambutol is a bacteriostatic drug – it stops bacteria from growing rather than killing them directly. Used to prevent resistance.

  • Mechanism of Action: Blocks arabinosyl transferase, stopping arabinogalactan synthesis (needed to build the bacterial cell wall). Like stopping the delivery of building materials.
  • Dosing in Uganda: Adults = 15 mg/kg. Children = 20 mg/kg.
  • Side Effects:
    • Optic Neuritis (Eye Nerve Damage): The most serious side effect! Symptoms: Blurred vision, reduced color vision (especially red-green), visual field defects. Action: Stop drug immediately. Reversible if caught early.
  • Contraindications: Pre-existing optic neuritis. Children under 5 years (because it is too difficult for a toddler to communicate that they are losing their color vision!).
🧠 Mnemonic: "Ethambutol Eats your Eyes – watch your vision!"

3.5 STREPTOMYCIN (S)

  • Mechanism of Action: An injectable aminoglycoside. Binds to the 30S bacterial ribosome (protein-making factory) and prevents protein synthesis.
  • Side Effects: Ototoxicity (Inner ear damage causing permanent hearing loss, ringing/tinnitus, vertigo) and Nephrotoxicity (Kidney damage).
  • Contraindications: Pregnancy (can cause congenital deafness in the baby).
🧠 Mnemonic: "Streptomycin Strikes the Ears and Kidneys"

Summary Table: First-Line Anti-Tuberculous Drugs

DrugIndicationsDosage (Uganda NTLP)ContraindicationsKey Side Effects
Isoniazid (INH)Active TB, Latent TB (TPT)Adult: 10 mg/kg (max 300mg/d)
Child: 10 mg/kg
Active liver disease, severe hepatic damagePeripheral neuropathy, Hepatotoxicity
Rifampicin (RIF)Active TB, LeprosyAdult: 10 mg/kg (max 600mg/d)
Child: 15 mg/kg
Hypersensitivity, concurrent protease inhibitorsOrange/red body fluids, Hepatotoxicity, CYP450 Inducer (decreases ART/contraceptive efficacy)
Pyrazinamide (PZA)Active TB (Intensive phase)Adult: 30-40 mg/kg
Child: 35 mg/kg
Severe liver disease, acute goutHyperuricemia (joint pains), Hepatotoxicity
Ethambutol (EMB)Active TB (Combination therapy)Adult: 15 mg/kg
Child: 20 mg/kg
Pre-existing optic neuritis, Children < 5 yrsOptic neuritis (blurred vision, red-green color blindness)
Streptomycin (S)Severe/Extra-pulmonary TB, Resistance15 mg/kg IM injectionPregnancy, Myasthenia GravisOtotoxicity (hearing loss/vertigo), Nephrotoxicity

SECTION 4: SECOND-LINE ANTI-TUBERCULOUS DRUGS (DETAILED)

4.1 Fluoroquinolones (Group A)

  • Levofloxacin and Moxifloxacin: Most effective second-line drugs.
  • Mechanism: Inhibit DNA gyrase (prevents bacteria from copying their DNA).
  • Side Effects: Tendon damage/rupture (rare), QT prolongation (heart rhythm problems), photosensitivity. Monitor ECGs.

4.2 Injectable Agents (Group B) & Other Core Drugs (Group C)

  • Amikacin, Kanamycin, Capreomycin: Can cause severe Ototoxicity and Nephrotoxicity. Monitor electrolytes (low K+ and Mg2+).
  • Cycloserine: Causes severe psychiatric problems (depression, psychosis, seizures). Give pyridoxine.
  • Ethionamide / Prothionamide: Causes severe metallic taste, severe nausea, and hypothyroidism.
  • Para-aminosalicylic Acid (PAS): Inhibits folate synthesis. Severe GI upset.

4.3 Newer Drugs (Group D2)

  • Bedaquiline: Inhibits ATP synthase (cuts off the bacteria's energy supply). Watch for QT prolongation.
  • Pretomanid: Used in the BPaL regimen. Inhibits cell wall synthesis.
  • Linezolid: Inhibits protein synthesis. Watch for bone marrow suppression (low blood counts) and lactic acidosis.

Summary Table: Second-Line & Newer Anti-Tuberculous Drugs

Drug Class / NameIndicationsDosage (Standard Adult)ContraindicationsKey Side Effects
Fluoroquinolones
(Levofloxacin, Moxifloxacin)
DR-TB, MDR-TBLfx: 750-1000 mg/day
Mfx: 400 mg/day
History of QT prolongation, severe hypersensitivityTendon rupture, QT prolongation, photosensitivity
Injectables
(Amikacin, Kanamycin)
DR-TB (where oral regimens are not viable)15 mg/kg/day IM/IVPregnancy, severe renal impairmentOtotoxicity, Nephrotoxicity, Electrolyte wasting
Bedaquiline (Bdq)MDR-TB, XDR-TB400 mg daily (2 wks), then 200 mg 3x/weekSevere arrhythmiasQT prolongation, hepatic toxicity
Linezolid (Lzd)MDR-TB (BPaL/BPaLM regimens)600 mg dailyConcurrent MAOI useBone marrow suppression, lactic acidosis, peripheral neuropathy
CycloserineMDR-TB250-500 mg twice dailySevere psychiatric disease, epilepsyDepression, psychosis, seizures (give Pyridoxine)

SECTION 5: UGANDA'S TB TREATMENT REGIMENS (UPDATED GUIDELINES)

5.1 Standard Regimen for Drug-Susceptible TB in Uganda

For Adults and Adolescents (>15 years): 2RHZE / 4RH

  • Initial Phase (2 months): Rifampicin + Isoniazid + Pyrazinamide + Ethambutol
  • Continuation Phase (4 months): Rifampicin + Isoniazid
  • Total Duration: 6 months (Given as Fixed-Dose Combination tablets based on weight bands: 33-39kg = 1 tab, 40-54kg = 2 tabs, 55-70kg = 3 tabs, >70kg = 4 tabs).

For Children:

  • All forms (except meningitis/bone): 2RHZE / 4RH
  • TB Meningitis / Bone TB (Osteoarticular): 2RHZE / 10RH (Requires a full 12 months because these tissues are very hard for drugs to penetrate).
  • Note: Weigh the child at EVERY visit and adjust doses!

5.2 New 4-Month Regimen (2HPZM/2HPM)

The WHO and Uganda are introducing a shorter 4-month regimen for eligible adults/adolescents:

  • Intensive Phase (2 mos): Isoniazid + Rifapentine + Pyrazinamide + Moxifloxacin
  • Continuation Phase (2 mos): Isoniazid + Rifapentine + Moxifloxacin
  • Eligibility: >12 years, >40 kg, drug-susceptible, HIV+ with CD4 >100 on compatible ART (efavirenz/dolutegravir).
  • NOT Eligible: Pregnant/breastfeeding, <12 years, severe extrapulmonary TB.

5.3 New 4-Month Regimen for Children (2HRZE / 2HR)

Children aged 3 months to 16 years with Non-Severe TB (e.g., uncomplicated peripheral lymph node TB) can be treated for just 4 months. Do NOT use for severe TB (miliary, meningitis, cavitary).

5.4 Drug-Resistant TB (DR-TB) Regimens in Uganda

  • MDR-TB (Resistant to Rifampicin and Isoniazid): Requires individualized steps using Groups A, B, C, D for 18-24 months.
  • New 6-Month All-Oral Regimens:
    • BPaLM: Bedaquiline, Pretomanid, Linezolid, Moxifloxacin (for fluoroquinolone-susceptible MDR-TB).
    • BPaL: Bedaquiline, Pretomanid, Linezolid (for fluoroquinolone-resistant MDR-TB).

SECTION 6: DRUG RESISTANCE IN TB

6.1 Types of Drug Resistance

  • Mono-Resistance: Resistance to ONE first-line drug only (e.g., INH mono-resistance).
  • Poly-Resistance: Resistance to more than one first-line drug (but NOT both RIF and INH).
  • Multidrug-Resistant TB (MDR-TB): Resistance to BOTH Rifampicin and Isoniazid. Highly dangerous.
  • Extensively Drug-Resistant TB (XDR-TB): MDR-TB PLUS resistance to any fluoroquinolone AND at least one injectable second-line drug. Extremely high death rate.
  • Rifampicin-Resistant TB (RR-TB): Treated exactly the same as MDR-TB.

6.2 Causes & Prevention of Drug Resistance

Causes: Incomplete treatment, poor adherence, wrong prescribing, substandard drugs, or catching a mutated strain from someone else.

🧠 Mnemonic: Prevention "DOT Prevents DR-TB"
Directly observed therapy (Watch them swallow it!)
Ongoing education (Explain why finishing the 6 months is life or death)
Testing (Drug Susceptibility Testing - DST to know what works)

SECTION 7: ADVERSE EFFECTS & NURSING MANAGEMENT

7.2 Managing Hepatotoxicity (Liver Damage)

  • Signs to Watch For: Jaundice (yellow eyes/skin), dark urine, pale stools, severe nausea/vomiting, abdominal pain (especially Right Upper Quadrant).
  • What to Do: Stop ALL hepatotoxic drugs immediately (INH, RIF, PZA). Keep ethambutol/streptomycin if needed to cover the patient. Monitor Liver Function Tests (LFTs) until they return to normal. Reintroduce drugs one by one starting with the least hepatotoxic.

7.3 Managing Severe Skin Reactions (Stevens-Johnson Syndrome)

  • Signs: Severe rash with blisters, peeling skin, sores in mouth/eyes/genitals, severe fever.
  • What to Do: This is a medical emergency. Stop ALL anti-TB drugs immediately. Admit to hospital for fluids/pain relief. Do NOT reintroduce drugs without specialist help.

SECTION 8: DRUG INTERACTIONS

8.3 HIV-TB Co-Treatment Interactions

TB and HIV are a deadly duo. When treating both, timing and drug choices are critical:

  • Preferred ART in Uganda: TDF + 3TC (or FTC) + DTG (Dolutegravir). Alternative: TDF + 3TC + EFV (Efavirenz).
  • Important Timing Notes:
    • Rifampicin reduces Dolutegravir (DTG) levels. You MUST separate timing or double the DTG dose to ensure the HIV is controlled.
    • Rifampicin severely reduces Lopinavir/Ritonavir.
    • Efavirenz is the most compatible with Rifampicin.
⚠️ Nursing Action: Always check what ART the patient is on before starting TB treatment! If they are on Nevirapine, it MUST be switched before starting Rifampicin.

SECTION 9: NURSING CARE & COMMUNITY HEALTH

9.1 Directly Observed Therapy (DOT)

DOT means a healthcare worker, VHT, or trained family member watches the patient physically swallow every dose. This is the gold standard because it ensures correct dosing, prevents resistance, and allows daily monitoring of side effects.

9.2 Patient Education (What to Teach Every TB Patient)

  • About Infection Control: "Cover your mouth when coughing. Sleep in a separate room for the first 2 weeks. Open windows for fresh air."
  • About Treatment: "Do NOT stop taking medicine even if you feel better after a month. Missing doses creates super-bacteria."
  • About Side Effects: "Orange urine is normal (Rifampicin). Report yellow eyes, severe nausea, or numbness immediately."

9.3 Contact Screening and Preventive Therapy

  • Children Under 5: Screen for symptoms. If NO symptoms, they must receive Isoniazid Preventive Therapy (IPT) for 6 months (10 mg/kg + pyridoxine daily).
  • PLHIV (People Living with HIV): Screen at every visit (Cough, Fever, Weight loss, Night sweats). If no symptoms, give TPT (Tuberculosis Preventive Treatment).
  • Uganda TPT Regimens: 6H (Isoniazid for 6 mos), 3HP (Rifapentine+INH for 3 mos), 1HP (for 1 month).
  • Note: For PLHIV starting dolutegravir-based ART, delay TPT for 3 months to avoid drug interactions.

SECTION 10: MNEMONICS & EXAM TIPS

🧠 Pyridoxine Indications: "PHADEM"
Give Pyridoxine (Vit B6) with Isoniazid to high-risk groups to prevent neuropathy:
Pregnant women
HIV-positive patients
Alcoholics
Diabetics
Elderly patients
Malnourished patients

Exam Traps to Avoid:

  • Orange urine? ➔ Rifampicin (It's NOT blood!)
  • Requires pyridoxine? ➔ Isoniazid.
  • Eye problems? ➔ Ethambutol.
  • NOT for children under 5? ➔ Streptomycin (hearing) AND Ethambutol (can't test vision).
  • Enzyme inducer? ➔ Rifampicin.

SECTION 11: CLINICAL SCENARIOS FOR UGANDAN COMMUNITIES

🏥 Scenario 1: A 28-Year-Old Woman with TB

  • Patient: Diagnosed with pulmonary TB. On oral contraceptives (Lo-femenal). Has a 3-year-old child.
  • Nursing Actions: Start 2RHZE/4RH. Change contraception immediately (Rifampicin destroys estrogen pill efficacy; recommend IUD or condoms). Screen the 3-year-old child; if asymptomatic, start the child on 6 months of IPT (Isoniazid + Pyridoxine). Warn her about orange urine.

🏥 Scenario 2: A 45-Year-Old Man with HIV and TB

  • Patient: CD4 150. On TDF/3TC/NVP (nevirapine-based ART).
  • Nursing Actions: Start 2RHZE/4RH. The Nevirapine MUST be switched because Rifampicin will cause it to fail. Switch to an Efavirenz or Dolutegravir-based regimen. Give Pyridoxine (HIV is a risk for neuropathy). Monitor for Immune Reconstitution Inflammatory Syndrome (IRIS).

🏥 Scenario 5: A Pregnant Woman with TB

  • Patient: 24-year-old pregnant woman (second trimester).
  • Nursing Actions: Do NOT delay treatment. Start standard 2RHZE/4RH. Avoid Streptomycin completely (causes fetal deafness). Give pyridoxine (essential in pregnancy). TB drugs are safe for breastfeeding, but the baby should get BCG and pyridoxine if nursing.

SECTION 12: QUICK REVIEW & CONCLUSION

Standard Regimens at a Glance:

  • New drug-susceptible TB (adults): 2RHZE/4RH (6 months)
  • New drug-susceptible TB (children, non-severe): 2HRZE/2HR (4 months)
  • TB meningitis / Bone TB: 2RHZE/10RH (12 months)
  • MDR-TB (new shorter oral): BPaLM or BPaL (6 months)

REFERENCES

  • Ministry of Health Uganda (MoH). National Tuberculosis and Leprosy Programme (NTLP) Manual for Management and Control of Tuberculosis.
  • World Health Organization (WHO). WHO consolidated guidelines on tuberculosis: Module 4: Treatment - Drug-susceptible tuberculosis treatment.
  • World Health Organization (WHO). WHO consolidated guidelines on tuberculosis: Module 4: Treatment - Drug-resistant tuberculosis treatment.
  • Uganda Clinical Guidelines (UCG). National Guidelines on Management of Common Conditions.

Quick Quiz

Anti-TB Quiz

Pharmacology

Privacy: Your details are used only for quiz tracking and certificates.

Anti-Tuberculous Agents Read More »

Quinolones (Fluoroquinolones)

Quinolones (Fluoroquinolones)

Quinolones (Fluoroquinolones)

1. INTRODUCTION & DEFINITION

What Are Quinolones?

Quinolones (also called Fluoroquinolones) are a group of synthetic (man-made) antibiotics that are used to treat many different types of bacterial infections. They are called "broad-spectrum" because they can kill a wide variety of bacteria — both Gram-positive and Gram-negative bacteria.

Simple Definition: Quinolones are powerful man-made antibiotics that stop bacteria from copying their DNA, which kills the bacteria.

💡 Why Are They Important for Nurses in Uganda?

In Uganda and other community settings, quinolones are commonly prescribed for:

  • Typhoid fever (caused by Salmonella typhi)
  • Urinary tract infections (UTIs)
  • Dysentery (bloody diarrhea, often caused by Shigella)
  • Pneumonia
  • Gonorrhea (a sexually transmitted infection)
  • Wound infections

Because these infections are common in our communities, nurses must understand how to safely administer these drugs and teach patients properly.

2. CLASSIFICATION & GENERATIONS

Quinolones are divided into four generations based on when they were developed and how broad their bacterial coverage is.

GenerationExamplesKey Features
First GenerationNalidixic acid, CinoxacinNarrow spectrum; mainly Gram-negative; not commonly used today
Second GenerationCiprofloxacin, Norfloxacin, OfloxacinBroader spectrum; good against Gram-negative bacteria; first "fluoroquinolones"
Third GenerationLevofloxacinImproved Gram-positive coverage; better for respiratory infections
Fourth GenerationMoxifloxacin, GemifloxacinBroadest spectrum; covers anaerobes, Gram-positive, and some Gram-negative

🧠 Memory Tip:
Think of generations like upgrading a phone — each new generation gets better and can do more!

Most Commonly Used Quinolones in Clinical Practice:

  • Ciprofloxacin — the most widely used; excellent for UTIs and typhoid
  • Levofloxacin — good for pneumonia and respiratory infections
  • Moxifloxacin — broad spectrum; good for complicated infections
  • Norfloxacin — used for UTIs and gastrointestinal infections
  • Ofloxacin — used for eye and ear infections (topical)

3. MECHANISM OF ACTION (HOW THE DRUG WORKS)

The "DNA Story" — Simplified

Bacteria are living cells that need to make copies of themselves to survive and spread. To do this, they must copy their DNA (their genetic material). This process involves special enzymes (proteins that speed up chemical reactions). Quinolones work by blocking two important bacterial enzymes:

A. DNA Gyrase (also called Topoisomerase II)

  • This enzyme helps bacteria untangle their DNA so it can be copied.
  • Without this enzyme, the DNA gets tangled up like a knotted rope.
  • Mechanism: Quinolones block DNA gyrase ➔ DNA cannot untangle ➔ bacteria cannot copy themselves ➔ bacteria die.

B. Topoisomerase IV

  • This enzyme helps separate the new DNA copies so they can be distributed into new bacterial cells.
  • Mechanism: Quinolones block Topoisomerase IV ➔ new DNA copies cannot separate ➔ bacteria cannot divide ➔ bacteria die.

Key Points to Remember:

FeatureExplanation
BactericidalQuinolones KILL bacteria directly (they don't just stop them from growing)
TargetOnly bacterial enzymes — NOT human enzymes (this is why they are safe for humans)
Gram-negative bacteriaQuinolones mainly target DNA gyrase
Gram-positive bacteriaQuinolones mainly target Topoisomerase IV

💡 Analogy:
Imagine a photocopier (the bacteria) trying to make copies of a document (DNA). Quinolones are like someone who jams the photocopier — no more copies can be made, and the "business" (bacteria) shuts down!

4. SPECTRUM OF ACTIVITY (WHICH BACTERIA THEY KILL)

Quinolones are broad-spectrum antibiotics, meaning they can kill many different types of bacteria.

Gram-Negative Bacteria (These are commonly found in Uganda):

BacteriaDisease Caused
Escherichia coli (E. coli)UTIs, diarrhea
Salmonella typhiTyphoid fever
Shigella speciesDysentery (bloody diarrhea)
Pseudomonas aeruginosaHospital-acquired infections, wound infections
Neisseria gonorrhoeaeGonorrhea (STI)
Haemophilus influenzaeRespiratory infections
Legionella speciesAtypical pneumonia
Campylobacter speciesGastroenteritis
Klebsiella speciesPneumonia, UTIs

Gram-Positive Bacteria:

BacteriaDisease Caused
Streptococcus pneumoniaePneumonia, meningitis
Staphylococcus aureusSkin infections, boils
Enterococcus speciesUTIs, abdominal infections

Atypical Organisms:

  • Mycoplasma pneumoniae
  • Chlamydia species
  • Mycobacterium tuberculosis (some quinolones are used in TB treatment)

Important Note: Quinolones are NOT effective against viruses, fungi, or parasites. They only kill bacteria!

5. COMMON DRUGS & THEIR NAMES

All quinolones end with the suffix "-floxacin". This makes them easy to identify!

Generic NameCommon Brand NamesMain Uses
CiprofloxacinCipro, Ciprotab, CiprobayTyphoid, UTIs, diarrhea, anthrax
LevofloxacinLevaquin, TavanicPneumonia, sinusitis, complicated infections
MoxifloxacinAveloxRespiratory infections, some skin infections
NorfloxacinNoroxin, NorbactinUTIs, prostatitis, gastroenteritis
OfloxacinFloxinEye infections (drops), ear infections
GemifloxacinFactiveCommunity-acquired pneumonia

🧠 Memory Tip:
If the drug name ends in "-floxacin", it is a quinolone!

COMPREHENSIVE QUINOLONE MASTER TABLE

This table breaks down the specific indications, standard dosages, and unique contraindications for the most commonly prescribed fluoroquinolones. (Note the differences in dosing frequency—some are twice daily, while the newer generations are once daily due to longer half-lives).

Drug NameCommonest IndicationsStandard DosageMain Side EffectsContraindications
Ciprofloxacin
(2nd Generation)
  • Typhoid fever
  • Complicated & uncomplicated UTIs
  • Bacterial diarrhea / dysentery
  • Prostatitis
  • Skin & soft tissue infections
  • Bone & joint infections (osteomyelitis)
  • Anthrax (post-exposure)
  • Gonorrhea (where sensitive)
  • Pseudomonal infections
Oral/IV:
  • Uncomplicated UTI: 250 mg every 12 hours for 3 days
  • Complicated UTI / Typhoid: 500 mg every 12 hours for 7–14 days
  • Severe infection / Anthrax: 750 mg every 12 hours
  • Prostatitis: 500 mg every 12 hours for 28 days
  • Eye/Ear drops: 1–2 drops every 2–4 hours
  • Nausea, vomiting, diarrhea
  • Abdominal pain, dyspepsia
  • Headache, dizziness, insomnia
  • Photosensitivity (severe sunburn)
  • Tendonitis / tendon rupture (Achilles)
  • Peripheral neuropathy
  • QT prolongation
  • Crystalluria
  • C. difficile superinfection
  • Hypersensitivity reactions
  • Hypersensitivity to quinolones
  • Pregnancy & breastfeeding
  • Children < 18 years (growing cartilage)
  • History of tendon rupture with quinolones
  • Myasthenia gravis
  • Concurrent tizanidine use
  • Known QT prolongation or uncorrected hypokalemia
Levofloxacin
(3rd Generation)
  • Community-acquired pneumonia
  • Acute bacterial sinusitis
  • Acute exacerbation of chronic bronchitis
  • Complicated & uncomplicated UTIs
  • Pyelonephritis
  • Skin & soft tissue infections
  • Prostatitis
Oral/IV:
  • Uncomplicated UTI: 250 mg once daily for 3 days
  • Complicated UTI / Pyelonephritis: 250–500 mg once daily for 7–10 days
  • Pneumonia / Sinusitis: 500–750 mg once daily for 7–14 days
  • Prostatitis: 500 mg once daily for 28 days
  • Nausea, diarrhea, constipation
  • Headache, dizziness
  • Insomnia, restlessness
  • Photosensitivity
  • Tendonitis / tendon rupture
  • Peripheral neuropathy
  • QT prolongation
  • Dysglycemia (hypo-/hyperglycemia)
  • Hepatotoxicity
  • C. difficile colitis
  • Hypersensitivity to quinolones
  • Pregnancy & breastfeeding
  • Children < 18 years
  • History of tendon rupture
  • Myasthenia gravis
  • Known QT prolongation
  • Concurrent use with other QT-prolonging drugs (e.g., amiodarone, sotalol)
Moxifloxacin
(4th Generation)
  • Community-acquired pneumonia
  • Acute bacterial sinusitis
  • Acute exacerbation of chronic bronchitis
  • Complicated intra-abdominal infections
  • Complicated skin & soft tissue infections
  • Plague (Yersinia pestis)
Oral/IV:
  • Standard adult dose: 400 mg once daily
  • Acute sinusitis / Bronchitis: 400 mg once daily for 10 days
  • Pneumonia / Complicated infections: 400 mg once daily for 7–14 days
  • Intra-abdominal: 400 mg once daily for 5–14 days
  • Nausea, vomiting, diarrhea
  • Dizziness, headache
  • Higher risk of QT prolongation
  • Tendon rupture
  • Peripheral neuropathy
  • Hepatotoxicity (elevated LFTs)
  • Photosensitivity (less than ciprofloxacin)
  • Dysglycemia
  • C. difficile colitis
  • Hypersensitivity to quinolones
  • Pregnancy & breastfeeding
  • Children < 18 years
  • History of tendon rupture
  • Myasthenia gravis
  • Baseline QT prolongation (highest risk in class)
  • Concurrent antiarrhythmics (Class IA & III)
  • Severe hepatic impairment
Norfloxacin
(2nd Generation)
  • Uncomplicated & complicated UTIs
  • Prostatitis
  • Gastroenteritis / traveler's diarrhea
  • Gonococcal urethritis (where sensitive)
Oral:
  • Uncomplicated UTI: 400 mg every 12 hours for 3 days
  • Complicated UTI: 400 mg every 12 hours for 7–21 days
  • Prostatitis: 400 mg every 12 hours for 28 days
  • Gastroenteritis: 400 mg every 12 hours for 1–3 days
  • Nausea, vomiting, diarrhea, abdominal cramps
  • Headache, dizziness
  • Photosensitivity
  • Tendonitis / tendon rupture
  • Crystalluria (ensure high fluid intake)
  • Peripheral neuropathy
  • C. difficile colitis
  • Hypersensitivity to quinolones
  • Pregnancy & breastfeeding
  • Children < 18 years
  • History of tendon rupture
  • Myasthenia gravis
  • QT prolongation
  • Concurrent theophylline (increased toxicity risk)
Ofloxacin
(2nd Generation)
  • Lower respiratory tract infections
  • UTIs & pyelonephritis
  • Prostatitis
  • Skin & soft tissue infections
  • Gonorrhea
  • Bacterial conjunctivitis (eye drops)
  • Otitis externa (ear drops)
Oral/IV:
  • Uncomplicated UTI: 200–400 mg every 12 hours for 3–7 days
  • Lower respiratory / Skin: 400 mg every 12 hours for 10 days
  • Prostatitis: 300 mg every 12 hours for 6 weeks
  • Gonorrhea: 400 mg single dose
  • Eye drops: 1–2 drops every 2–4 hours, then taper
  • Ear drops: 10 drops into affected ear twice daily for 10–14 days
  • Nausea, diarrhea
  • Insomnia, headache, dizziness
  • Photosensitivity
  • Tendonitis / tendon rupture
  • Peripheral neuropathy
  • QT prolongation
  • Dysglycemia
  • Local irritation (with eye/ear drops)
  • C. difficile colitis
  • Hypersensitivity to quinolones
  • Pregnancy & breastfeeding
  • Children < 18 years
  • History of tendon rupture
  • Myasthenia gravis
  • QT prolongation
  • Concurrent antiarrhythmics
Gemifloxacin
(4th Generation)
  • Community-acquired pneumonia (CAP)
  • Acute bacterial exacerbation of chronic bronchitis
  • Acute bacterial sinusitis
Oral:
  • Standard adult dose: 320 mg once daily
  • Bronchitis / Sinusitis: 320 mg once daily for 5 days
  • Pneumonia: 320 mg once daily for 5–7 days
  • Nausea, diarrhea
  • Headache, dizziness
  • Rash (including severe rash in women < 40 years)
  • Photosensitivity
  • Tendon rupture
  • Peripheral neuropathy
  • QT prolongation
  • Dysglycemia
  • C. difficile colitis
  • Hypersensitivity to quinolones
  • Pregnancy & breastfeeding
  • Children < 18 years
  • History of tendon rupture
  • Myasthenia gravis
  • Known QT prolongation
  • History of rash with other quinolones
  • Concurrent Class IA/III antiarrhythmics

💡 High-Yield Clinical Distinctions (Why choose one over the other?)

  • UTIs: Ciprofloxacin, Levofloxacin, and Norfloxacin are great for UTIs because they are heavily excreted unchanged in the urine. Moxifloxacin is NOT used for UTIs because it is metabolized in the liver and does not concentrate in the urine!
  • Respiratory Infections: Levofloxacin, Moxifloxacin, and Gemifloxacin are dubbed the "Respiratory Fluoroquinolones" because they have excellent coverage against Streptococcus pneumoniae (the most common cause of community-acquired pneumonia). Ciprofloxacin is poor against Strep and should not be used as monotherapy for routine pneumonia.
  • Pseudomonas: If you suspect Pseudomonas aeruginosa (hospital-acquired infections), Ciprofloxacin is the most potent quinolone.

❓ Applied Clinical Question: The Wrong Drug

Case: A 45-year-old female presents to the clinic with dysuria, frequency, and suprapubic pain. Urinalysis confirms an uncomplicated UTI. The pharmacy is out of Ciprofloxacin. A junior doctor writes a prescription for Moxifloxacin 400mg daily. As the nurse reviewing the chart, why should you question this order?

Answer: You must question this order because Moxifloxacin is primarily metabolized by the liver and excreted in feces/bile. It does not reach high enough concentrations in the urine to effectively treat a urinary tract infection. The doctor should switch to Levofloxacin or Norfloxacin instead!

🧠 Mnemonic: "My Lungs Grow"

To remember the Respiratory Fluoroquinolones (the ones that effectively kill Streptococcus pneumoniae):

  • My = Moxifloxacin
  • Lungs = Levofloxacin
  • Grow = Gemifloxacin

6. CLINICAL USES & INDICATIONS

Common Infections Treated with Quinolones:

  • Urinary Tract Infections (UTIs): Very common in women. Symptoms: burning when passing urine, frequent urination, lower abdominal pain. Ciprofloxacin and Norfloxacin are commonly used.
  • Typhoid Fever: Caused by Salmonella typhi. Common in areas with poor sanitation. Symptoms: prolonged fever, headache, abdominal pain, rose spots on skin. Ciprofloxacin is the drug of choice in many cases.
  • Dysentery (Bloody Diarrhea): Caused by Shigella species. Symptoms: bloody stools, abdominal cramps, fever. Ciprofloxacin is effective.
  • Pneumonia: Infection of the lungs. Symptoms: cough, fever, difficulty breathing, chest pain. Levofloxacin and Moxifloxacin are used.
  • Gonorrhea: Sexually transmitted infection. Ciprofloxacin was previously used, but resistance is increasing.
  • Skin and Soft Tissue Infections: Wounds, abscesses, cellulitis. Ciprofloxacin may be used.
  • Bone and Joint Infections: Osteomyelitis (bone infection). Ciprofloxacin is used for chronic cases.
  • Eye and Ear Infections: Bacterial conjunctivitis (pink eye) and Otitis externa (swimmer's ear). Ofloxacin eye drops and ear drops.
  • Anthrax: A serious bacterial infection that can be used as a biological weapon. Ciprofloxacin is the drug of choice for post-exposure prophylaxis.

7. ROUTES OF ADMINISTRATION

Quinolones can be given in several ways:

RouteExamplesNursing Notes
Oral (by mouth)Tablets, capsules, suspensionsMost common; absorbed well from the gut
Intravenous (IV)Infusions in hospital settingsUsed for serious infections; infuse slowly
TopicalEye drops, ear dropsFor eye/ear infections only
Otic (ear)Ofloxacin ear dropsFor ear infections

Oral Absorption: Quinolones are well absorbed when taken by mouth. Food may slow absorption slightly, but they can generally be taken with or without food.
EXCEPTION: Avoid taking with dairy products, antacids, or iron supplements (see Drug Interactions).

8. PHARMACOKINETICS (HOW THE BODY HANDLES THE DRUG)

  • A. Absorption: Oral bioavailability is excellent (70–90%). This means most of the drug gets into the bloodstream when taken by mouth. Peak levels in blood occur 1–2 hours after oral administration.
  • B. Distribution: Quinolones are widely distributed throughout the body. They penetrate well into: Urine (good for UTIs), Lungs (good for pneumonia), Bones and joints, Prostate gland, Cerebrospinal fluid (to some extent).
  • C. Metabolism: Most quinolones are metabolized in the liver. Some are excreted unchanged by the kidneys.
  • D. Excretion: Mainly excreted through the kidneys in urine. This is why they are so effective for UTIs — the drug concentrates in the urine! Some are also excreted in bile/feces.
  • E. Half-Life: Varies by drug: Ciprofloxacin (~4 hours), Levofloxacin (~6–8 hours), Moxifloxacin (~12 hours). Dosing is usually twice daily for most quinolones.

9. ADVERSE EFFECTS & SIDE EFFECTS

Quinolones can cause many side effects. Nurses must monitor patients carefully.

A. Gastrointestinal (GI) Effects — MOST COMMON

Side EffectWhat to Watch For
NauseaPatient feels like vomiting
VomitingActual throwing up
DiarrheaLoose, watery stools
Abdominal painStomach cramps
DyspepsiaIndigestion, heartburn
C. difficile infectionSevere watery diarrhea, fever, abdominal pain

💡 Nursing Action: Monitor bowel movements. If patient develops severe diarrhea, notify the doctor immediately — this could be C. difficile, a serious superinfection!

B. Central Nervous System (CNS) Effects

Side EffectWhat to Watch For
HeadachePersistent head pain
DizzinessFeeling lightheaded
InsomniaDifficulty sleeping
RestlessnessUnable to sit still
ConfusionDisorientation, especially in elderly
SeizuresConvulsions (rare but serious)
DepressionLow mood
NightmaresBad dreams

💡 Nursing Action: Monitor mental status. Report any confusion or seizures immediately.

C. Musculoskeletal Effects — VERY IMPORTANT!

Side EffectWhat to Watch For
TendonitisPain, swelling, tenderness in tendons (especially Achilles tendon)
Tendon ruptureSudden "snap" feeling, inability to move foot, severe pain
ArthralgiaJoint pain
Muscle weaknessEspecially dangerous in myasthenia gravis patients

Risk Factors for Tendon Problems: Age over 60 years, taking corticosteroids (like prednisone), kidney disease, diabetes, history of tendon problems.

💡 Nursing Action: Teach patients to STOP the medication and report immediately if they feel tendon pain, swelling, or hear a "pop" sound!

D. Cardiovascular Effects

Side EffectWhat to Watch For
QT prolongationAbnormal heart rhythm on ECG
Torsades de PointesLife-threatening irregular heartbeat
PalpitationsFeeling heart racing
HypotensionLow blood pressure

💡 Nursing Action: Monitor heart rate and rhythm. Be extra careful if patient is also taking other QT-prolonging drugs (like amiodarone).

E. Dermatological (Skin) Effects

Side EffectWhat to Watch For
PhotosensitivitySevere sunburn even with brief sun exposure
RashSkin redness, itching
Urticaria (hives)Raised, itchy welts
Stevens-Johnson syndromeSevere blistering rash (medical emergency!)
Toxic epidermal necrolysisSkin peeling off (medical emergency!)

💡 Nursing Action: Teach patients to avoid sun exposure and use protective clothing and sunscreen!

F. Hepatic (Liver) Effects

  • Elevated liver enzymes (ALT, AST)
  • Hepatotoxicity (liver damage)
  • Jaundice (yellowing of skin and eyes)

💡 Nursing Action: Monitor liver function tests. Watch for jaundice.

G. Other Effects

Side EffectExplanation
CrystalluriaCrystals forming in urine (can block kidneys)
HypoglycemiaLow blood sugar (especially in diabetics)
Peripheral neuropathyNumbness, tingling, burning in hands/feet
Aortic aneurysmBulging of the main artery (rare but serious)

10. BLACK BOX WARNINGS (MOST SERIOUS WARNINGS)

The FDA (U.S. Food and Drug Administration) has issued the strongest possible warning for quinolones called a "Black Box Warning."

  1. Tendinitis and Tendon Rupture: Can happen during treatment or up to several months after. Most commonly affects the Achilles tendon. Risk increased in patients over 60, those on corticosteroids, and those with kidney disease.
  2. Peripheral Neuropathy: Nerve damage causing pain, burning, tingling, numbness. Can be permanent!
  3. Central Nervous System Effects: Seizures, psychosis, increased intracranial pressure.
  4. Exacerbation of Myasthenia Gravis: Can cause life-threatening muscle weakness.

💡 Nursing Action: If a patient experiences ANY of these serious adverse reactions, DISCONTINUE THE MEDICATION IMMEDIATELY and notify the healthcare provider!

11. DRUG INTERACTIONS

Quinolones interact with many other drugs. Nurses must check medication lists carefully!

A. Drugs That Reduce Quinolone Absorption

These contain cations (positive ions) that bind to quinolones in the gut:

Drug/FoodExamplesAction
AntacidsMaalox, Mylanta, TumsSeparate by at least 2 hours
Iron supplementsFerrous sulfateSeparate by at least 2 hours
Calcium supplementsCalcium carbonateSeparate by at least 2 hours
Zinc supplementsZinc tabletsSeparate by at least 2 hours
Magnesium supplementsMagnesium oxideSeparate by at least 2 hours
Dairy productsMilk, cheese, yogurtDo not take together

Rule: Give quinolones 2 hours BEFORE or 6 hours AFTER these products!

B. Drugs That Increase Quinolone Side Effects

DrugInteraction
Corticosteroids (prednisone)Increased risk of tendon rupture
WarfarinIncreased bleeding risk
TheophyllineIncreased theophylline toxicity (nervousness, seizures)
CaffeineIncreased caffeine effects (jitteriness, palpitations)
PhenytoinAltered phenytoin levels
AmiodaroneIncreased QT prolongation risk
SucralfateDecreased quinolone absorption

C. Drugs That Affect Blood Sugar

Quinolones can cause hypoglycemia (low blood sugar) or hyperglycemia (high blood sugar). Monitor blood sugar closely in diabetic patients.

12. CONTRAINDICATIONS & PRECAUTIONS

Absolute Contraindications (NEVER Give):

SituationReason
Known allergy to quinolonesRisk of anaphylaxis
History of tendon rupture with quinolonesHigh risk of recurrence
Myasthenia gravisCan worsen muscle weakness

Relative Contraindications (Use with Caution):

SituationReason
PregnancyRisk of cartilage damage to fetus
BreastfeedingDrug passes into breast milk
Children under 18Risk of cartilage damage in growing bones
Elderly (>60 years)Increased risk of tendon rupture
Seizure disordersCan lower seizure threshold
Renal impairmentDrug accumulation; dose adjustment needed
Hepatic impairmentAltered drug metabolism
QT prolongationRisk of dangerous heart rhythms
DiabetesRisk of blood sugar changes

13. NURSING CONSIDERATIONS & INTERVENTIONS

Before Administration:

  • Check allergies — Ask about previous reactions to quinolones
  • Obtain culture and sensitivity — Before starting antibiotic (if possible)
  • Review medication list — Check for drug interactions
  • Assess baseline vital signs and check renal and liver function tests

During Administration:

  • Oral: Give with a full glass of water. Can give with food if stomach upset occurs. NEVER give with dairy, antacids, or iron supplements. Ensure patient drinks plenty of fluids (2 liters/day).
  • IV Administration: Infuse slowly over 60 minutes (for 500mg) or 90 minutes (for 750mg). Monitor for infusion reactions. Do not mix with other medications in the same IV line.

After Administration:

  • Monitor for effectiveness: Decreasing fever, decreasing white blood cell count, improving symptoms, negative culture results.
  • Monitor for adverse effects: Tendon pain or swelling, diarrhea (especially watery/bloody), skin rash, mental status changes, heart rhythm changes.
  • Monitor intake and output: Ensure adequate urine output (at least 30 mL/hour). Watch for signs of crystalluria.

14. PATIENT EDUCATION & COMMUNITY TEACHING

  • A. How to Take the Medication: "Take this medicine with plenty of water. You can take it with food if your stomach hurts. Do NOT take it with milk, yogurt, cheese, or antacids. Wait at least 2 hours before or after."
  • B. Fluid Intake: "Drink at least 8 glasses of water every day while taking this medicine. This helps prevent crystals from forming in your urine."
  • C. Sun Protection: "This medicine can make your skin very sensitive to the sun. Stay out of direct sunlight. Wear long sleeves, a hat, and use sunscreen. This can happen while taking the medicine AND for several days after."
  • D. Tendon Warning: "If you feel pain, swelling, or a 'snap' in your ankle or any tendon, STOP the medicine and come to the clinic immediately! Rest the affected area. Do not exercise while taking this medicine."
  • E. Complete the Full Course: "Take ALL the medicine, even if you feel better. If you stop early, the infection may come back stronger."
  • F. When to Seek Help: Severe diarrhea, yellowing of skin or eyes, severe skin rash, difficulty breathing, chest pain or irregular heartbeat, severe dizziness or confusion.

15. ANTIBIOTIC RESISTANCE

What Is Resistance? Bacteria can change (mutate) so that quinolones no longer kill them. This is a growing problem worldwide, including in Uganda.

How Resistance Develops:

  • Mutations in target enzymes — Bacteria change their DNA gyrase or topoisomerase IV so the drug cannot bind.
  • Efflux pumps — Bacteria develop pumps that push the drug out before it can work.
  • Decreased permeability — Bacteria change their cell walls so the drug cannot enter.

How to Prevent Resistance: Only use quinolones when necessary — not for viral infections! Complete the full course of antibiotics. Do not share antibiotics with others. Use narrow-spectrum antibiotics when possible. Practice good hygiene to prevent infections.

💡 Community Teaching:
"Do not buy antibiotics from the shop without a prescription. Using antibiotics when you don't need them makes them stop working when you really need them!"

16. CLINICAL SCENARIOS & CASE STUDIES

❓ Scenario 1: Typhoid Fever in the Community

  • Patient: A 25-year-old woman with fever for 7 days, headache, abdominal pain, and constipation.
  • Diagnosis: Typhoid fever
  • Treatment: Ciprofloxacin 500mg orally twice daily for 14 days
  • Nursing Actions: Teach patient to take with water, warn about sun exposure, monitor for tendon pain, ensure completion of full course. Teach family about handwashing and safe water.

❓ Scenario 2: UTI in a Pregnant Woman

  • Patient: A 30-year-old pregnant woman with burning urination and frequency.
  • Important: Quinolones are contraindicated in pregnancy!
  • Alternative: The doctor will likely prescribe a safer antibiotic like amoxicillin or nitrofurantoin.
  • Nursing Actions: Do NOT give quinolones to pregnant patients, educate about safe alternatives, encourage plenty of fluids, teach about perineal hygiene.

❓ Scenario 3: Tendon Pain During Treatment

  • Patient: A 65-year-old man on levofloxacin for pneumonia reports pain "above his heel."
  • Assessment: Pain over the Achilles tendon.
  • Nursing Actions: STOP the medication immediately! Notify the healthcare provider. Rest the affected leg. Do NOT massage or exercise the tendon. Document the adverse reaction.

17. MNEMONICS FOR EASY RECALL

🧠 Mnemonic 1: "FLOXACINS" — Nursing Considerations

  • F - Fluid intake important (2L/day)
  • L - Long QT interval (monitor heart)
  • O - Older adults at risk for tendon rupture (>60 years)
  • X - Don't give with cations (Ca, Zn, Fe, Mg, Al) or dairy
  • A - Avoid in children and pregnancy
  • C - Watch for C. difficile diarrhea
  • I - Interactions with caffeine, warfarin, theophylline
  • N - Neuromuscular blockade (worsens myasthenia gravis)
  • S - Sun sensitivity (photosensitivity)

🧠 Mnemonic 2: "CIPRO" — Key Points About Ciprofloxacin

  • C - Cartilage damage risk (avoid in children)
  • I - Inhibits DNA gyrase
  • P - Photosensitivity
  • R - Renal excretion (good for UTIs)
  • O - Oral and IV routes

🧠 Mnemonic 3: "TENDON" — Tendon Rupture Warning Signs

  • T - Tenderness over tendon
  • E - Edema (swelling)
  • N - No ability to move the joint
  • D - Discomfort with movement
  • O - Obvious deformity
  • N - Notify doctor immediately!

18. EXAM TIPS & COMMON TEST QUESTIONS

  • Mechanism of action: Inhibits DNA gyrase and topoisomerase IV
  • Suffix: All end in "-floxacin"
  • Black box warning: Tendon rupture, peripheral neuropathy, CNS effects
  • Drug interactions: Antacids, dairy, iron, calcium reduce absorption
  • Contraindications: Pregnancy, children <18, myasthenia gravis
  • Side effects: Photosensitivity, GI upset, C. difficile, QT prolongation
  • Patient teaching: Drink plenty of water, avoid sun, complete full course

❓ Sample Exam Questions:

  • Q1: A patient taking ciprofloxacin reports pain in the Achilles tendon. What is the nurse's best action?
    A: Stop the medication immediately and notify the provider. This could be tendonitis, which can lead to tendon rupture.
  • Q2: A patient asks if they can take their ciprofloxacin with their calcium supplement. What should the nurse say?
    A: No. Calcium binds to ciprofloxacin and prevents absorption. Take the antibiotic 2 hours before or 6 hours after the calcium.
  • Q3: Why are quinolones contraindicated in children?
    A: They can damage growing cartilage and affect bone development.
  • Q4: A patient on levofloxacin develops severe watery diarrhea. What should the nurse suspect?
    A: C. difficile infection. This is a superinfection caused by disruption of normal gut bacteria.

📋 QUICK REFERENCE SUMMARY CARD

FeatureDetails
ClassFluoroquinolones
Suffix-floxacin
ActionBactericidal; inhibits DNA gyrase and topoisomerase IV
SpectrumBroad (Gram-negative and Gram-positive)
Common drugsCiprofloxacin, Levofloxacin, Moxifloxacin, Norfloxacin, Ofloxacin
RoutesOral, IV, topical (eye/ear drops)
Key side effectsGI upset, photosensitivity, tendon rupture, QT prolongation, C. difficile
Black box warningTendon rupture, peripheral neuropathy, CNS effects, myasthenia gravis
ContraindicationsPregnancy, children <18, myasthenia gravis, known allergy
Drug interactionsAntacids, dairy, iron, calcium, magnesium, zinc, corticosteroids, warfarin
Patient teachingPlenty of fluids, avoid sun, no dairy/antacids with dose, complete full course
Nursing priorityMonitor for tendon pain, diarrhea, rash, mental changes, heart rhythm

🌍 SPECIAL CONSIDERATIONS FOR UGANDAN COMMUNITIES

Common Infections in Uganda Treated with Quinolones:

  • Typhoid fever: very common; spread through contaminated food/water
  • Dysentery: bloody diarrhea; spread through poor sanitation
  • UTIs: common in women; related to hygiene and water quality
  • Pneumonia: especially in children and HIV-positive patients

Community Health Teaching Points:

  • Safe water: Boil or treat drinking water to prevent typhoid and dysentery
  • Handwashing: Wash hands with soap after using the toilet and before eating
  • Proper toilet use: Use latrines to prevent contamination of water sources
  • Complete antibiotics: Finish all prescribed medication
  • Don't self-medicate: See a healthcare provider before taking antibiotics
  • Report side effects: Tell the nurse or doctor if you have tendon pain, severe diarrhea, or skin rash

📚 REFERENCES

  • Osmosis. (2025). Antibiotics - Fluoroquinolones: Nursing Pharmacology.
  • Open RN. (2023). 3.11 Fluoroquinolones – Fundamentals of Nursing Pharmacology.
  • RegisteredNurseRN. (2023). Fluoroquinolones (Quinolones) Nursing Antibiotic Pharmacology Review.
  • Muntean et al. (2022). Overview of Side-Effects of Antibacterial Fluoroquinolones. PMC.
  • Australian Prescriber. Fluoroquinolone antibiotics and adverse events. PMC.

Quick Quiz

Quinolones (Fluoroquinolones) Quiz

Pharmacology

Privacy: Your details are used only for quiz tracking and certificates.

Quinolones (Fluoroquinolones) Read More »

Admit children involved in accidents

Admit children involved in accidents

Admitting Children, Assessment, and Prevention Strategies

A. Initial Assessment in the Emergency Department

When a child arrives at the hospital after an accident, the nurse must perform a systematic assessment. Do NOT be distracted by obvious injuries (like a bleeding arm) and miss a hidden life-threatening problem (like internal bleeding or a tension pneumothorax).

💡 Physiological Expansion: The Pediatric Airway
Children are not just "small adults." Their anatomy makes them highly vulnerable during trauma. A child's airway is funnel-shaped (narrowest at the cricoid ring, unlike adults where it is the vocal cords), their tongue is disproportionately large, and their occiput (back of the head) is prominent, causing airway kinking if they are laid flat on a hard spine board without a shoulder roll.

The "ABCDE" Approach (Secondary Survey)

LetterSystemWhat to AssessRed Flags (Danger Signs)
AAirwayIs it open? Any obstruction? Blood, vomit, foreign body?Gurgling sounds, stridor, inability to speak.
BBreathingRate, depth, effort, oxygen saturation.Fast breathing, chest retractions, cyanosis (blue lips), low SpO2.
CCirculationPulse rate, blood pressure, capillary refill time, skin color.Weak/fast pulse, low BP, CRT >2 seconds, pale/cold skin.
DDisabilityLevel of consciousness (AVPU), pupil size and reaction.Decreased consciousness, unequal pupils.
EExposureRemove all clothes to examine fully. Prevent hypothermia.Hidden injuries, bruising patterns, burns on back.

🧠 Exposure Mnemonic

"Always Be Careful — Don't Expose without covering!" Remember that children have a massive body surface area to mass ratio, meaning they lose heat rapidly. Hypothermia worsens bleeding by disrupting the coagulation cascade.

B. Vital Signs in Children (Know These for Exams!)

Normal vital signs in pediatrics are heavily age-dependent. Memorize these ranges:

AgeHeart Rate (bpm)Respiratory Rate (breaths/min)Systolic BP (mmHg)
Newborn (0-1 month)100-16030-6060-90
Infant (1-12 months)100-16025-4072-104
Toddler (1-2 years)90-15020-3074-100
Preschool (3-5 years)80-14020-2578-108
School-age (6-12 years)70-12016-2282-118
Adolescent (13-18 years)60-10012-2090-120
  • Capillary Refill Time (CRT): Press on the child's fingernail or sternum for 5 seconds. Color should return in less than 2 seconds. If longer ➔ shock! (This indicates peripheral vasoconstriction as the body attempts to shunt blood to vital organs).

C. Specific Admission Criteria

A child involved in an accident MUST be admitted to the hospital if ANY of the following apply:

1. Head Injury Admission Criteria:

  • Loss of consciousness (even brief).
  • Amnesia (cannot remember the accident).
  • Seizure after injury.
  • Persistent vomiting (A classic sign of rising Intracranial Pressure - ICP).
  • Severe or worsening headache.
  • Confusion, irritability, or unusual behavior.
  • Signs of skull fracture: clear fluid from nose/ears (CSF leak), bruising behind ears (Battle's sign), or "raccoon eyes".
  • High-risk mechanism (fall from height, high-speed Road Traffic Accident - RTA).

2. Chest/Abdominal Injury Admission Criteria:

  • Difficulty breathing or Chest pain.
  • Abdominal pain or tenderness.
  • Blood in vomit, urine, or stool.
  • Signs of internal bleeding (pale, fast pulse, low BP, distended rigid abdomen). Children's abdominal organs (liver, spleen) are relatively larger and less protected by the rib cage than in adults, making them prone to rupture.

3. Fracture Admission Criteria:

  • Open fractures (bone protruding through skin) - high risk of osteomyelitis.
  • Displaced fractures or Fractures near joints.
  • Multiple fractures.
  • Fractures with nerve or blood vessel damage (check pulse and sensation distal to the break).

4. Burn Admission Criteria:

  • Burns >10% Total Body Surface Area (TBSA).
  • Burns on face, hands, feet, genitals, or across joints (Due to severe functional impairment and scar contractures).
  • Electrical burns (High risk of cardiac arrhythmias).
  • Chemical burns.
  • Inhalation injury (smoke inhalation) - airway can swell shut hours later.
  • Burns in very young children (<2 years).
  • Circumferential burns (burns that go all the way around a limb) - acts like a tourniquet and cuts off blood supply.

5. Poisoning Admission Criteria:

  • ALL poisonings should be observed in the hospital!
  • Even if the child seems fine, delayed effects can occur as the immature liver and kidneys struggle to process the toxin.

D. Nursing Care Plan for the Admitted Child

  1. Airway Management: Position child to maintain open airway (sniffing position). Suction secretions as needed. Administer oxygen if SpO2 <94%. Have suction and resuscitation equipment immediately at bedside.
  2. Breathing Support: Monitor respiratory rate and effort every 15-30 minutes initially. Give oxygen via nasal cannula or face mask. Watch for signs of respiratory distress: nasal flaring, grunting, chest retractions.
  3. Circulation Monitoring: Insert IV line for fluids and medications. Monitor heart rate, BP, and CRT. Watch for signs of shock:
    • Tachycardia (fast heart rate): The earliest sign!
    • Hypotension (low BP): A VERY late sign in children!
    • Poor CRT and Decreased urine output.
    Physiological Note: Children compensate well initially by clamping down blood vessels, maintaining their BP. When they exhaust this mechanism, they crash suddenly and irreversibly!
  4. Neurological Monitoring: Assess level of consciousness using Glasgow Coma Scale (GCS) or AVPU. Check pupil size and reaction every 1-2 hours for head injuries. Watch for seizures.
  5. Pain Management: Assess pain using age-appropriate scales:
    • Infants: FLACC scale (Face, Legs, Activity, Cry, Consolability).
    • Older children: Faces pain scale or number scale (0-10).
    • Give analgesics as prescribed (paracetamol, morphine for severe pain).
  6. Wound Care: Clean and dress wounds. Administer tetanus toxoid if needed. Give antibiotics for open wounds. Monitor for signs of infection: redness, swelling, pus, fever.
  7. Fluid and Nutrition: Calculate fluid requirements based on weight (e.g., Holliday-Segar method). For burns, use the Parkland formula (4mL × kg × %TBSA). NPO (nothing by mouth) if surgery is planned. Start feeding as soon as safe to prevent malnutrition.
  8. Emotional Support: Keep parents/caregivers with the child. Explain procedures in simple language. Reassure the child — fear increases pain and stress hormones, which raises intracranial pressure.
  9. Documentation: Record all vital signs, treatments, and observations. Document time of injury, first aid given, and transport details. This is legal evidence if needed.

E. Discharge Planning

Before sending a child home, the nurse must ensure:

  • Medical clearance — doctor has reviewed and approved discharge.
  • Wound care instructions given to parents (cleaning, dressing changes, signs of infection).
  • Medications explained (dose, frequency, duration).
  • Follow-up appointment scheduled.
  • Tetanus immunization status confirmed.
  • Home safety assessment discussed.
  • Return precautions explained: When to come back immediately (Fever, Increased pain, Wound redness or pus, Vomiting, Loss of consciousness, Any new concerning symptoms).

4️⃣ EDUCATING MOTHERS ON PREVENTION OF ACCIDENTS

A. The "Three E's" of Accident Prevention

EMeaningWhat Mothers Can Do
EducationTeaching about dangersExplain risks in simple language, use stories.
EnvironmentMaking the home safeRemove hazards, create safe play areas.
EnforcementRules and supervisionSet boundaries, watch children constantly.

B. Home Safety Education for Ugandan Mothers

1. PREVENTING FALLS

Why it matters: Falls are the #1 cause of injury in Ugandan children under 5. (Toddlers have disproportionately large heads, shifting their center of gravity up, making them top-heavy).

  • Bunk beds: Install guard rails on top bunk. Do NOT let children under 6 sleep on the top bunk.
  • Verandas and stairs: Install barriers/gates. Block access with furniture.
  • Windows: Do not let children sit on sills. Install bars or keep locked.
  • Trees: Teach children not to climb tall trees alone. Clear hard objects (stones, metal) from underneath.
  • Baby walkers: These are highly dangerous — children can fall down stairs. Do NOT use them.

Simple Message: "If they can reach it, they will fall from it!"

2. PREVENTING BURNS

Why it matters: Burns are the #2 cause of injury and cause permanent scarring and disability.

  • Cooking area: Create a separate cooking space. Turn pot handles INWARD on the stove. Use back burners. Never leave cooking food unattended.
  • Hot liquids: Do NOT carry hot tea/coffee while holding a baby. Place hot drinks in the CENTER of the table. Test bath water with your ELBOW (it's more sensitive to heat than calloused hands).
  • Fire safety: Use a fixed cooking stove (jiko with walls) rather than open flames. Store kerosene/paraffin locked away.
  • Electrical safety: Cover exposed sockets with tape. Raise wires out of reach.

Simple Message: "Hot things hurt — keep them high and away!"

3. PREVENTING POISONING

  • Medicines: Store ALL medicines in a locked box/high cupboard. Do NOT call medicine "candy" or "sweet". Dispose of expired meds safely.
  • Chemicals: Store kerosene, pesticides, and cleaning products in original containers (never in soda bottles!). Do NOT store under the sink where toddlers explore.
  • Plants: Remove poisonous plants. Teach children not to eat unknown berries.

Simple Message: "If it is not food, it is poison — lock it up!"

4. PREVENTING DROWNING

  • Water containers: Empty buckets, basins, and drums immediately. A child can drown in just 5 cm of water!
  • Wells and latrines: Cover all open wells and pit latrines securely.
  • Bathing: Never leave a child alone in the bath, even for "just a minute."

Simple Message: "Water waits silently — never leave them alone near it!"

5. PREVENTING ROAD TRAFFIC INJURIES

  • Supervision: Children under 10 cannot judge traffic speed and distance (their peripheral vision and depth perception are not fully developed). Hold their hand.
  • Visibility: Dress children in bright colors at dawn/dusk.
  • Boda-boda safety: Children should wear helmets. Do NOT let children stand on motorcycles.

Simple Message: "Hold their hand until they can hold their own life!"

6. PREVENTING CHOKING

  • Food: Cut into small pieces. Do NOT give hard candy, nuts, or popcorn to children under 4.
  • Small objects: Keep coins, batteries (especially highly corrosive button batteries!), and beads out of reach.
  • Eating habits: Make children sit while eating. Do not run or play with food in mouth.

Simple Message: "Small things in small mouths = big danger!"

7. PREVENTING CUTS

  • Store knives/pangas in high locked drawers. Clean up broken glass immediately. Check play areas for nails/wires.

Simple Message: "Sharp things cut — keep them up and locked!"

C. The Role of Supervision & Play Areas

Supervision is the MOST IMPORTANT prevention strategy!

Age GroupSupervision Needed
Under 1 yearConstant, within arm's reach
1-3 yearsConstant visual contact
3-5 yearsClose supervision, especially near hazards
5-10 yearsRegular checking, teach safety rules
Over 10 yearsSupervise risky activities, set boundaries

Important Notes for Mothers: Older siblings are NOT adequate supervisors (A 10-year-old cannot safely watch a baby). "I was just gone for a minute" — accidents happen in seconds.

D. Creating Safe Play Areas:

In small/crowded homes, designate one safe corner. Use barriers (even a mat defines "safe space"). Provide age-appropriate toys with no small parts. Check the area daily for new hazards.

5️⃣ CLINICAL SCENARIOS

🚑 Scenario 1: Burn from Hot Porridge

  • Setting: A 2-year-old pulls a pot of hot porridge from the stove. Burns on face, chest, and right arm.
  • Nurse Actions: Remove child from heat source. Cool burn with running water for 20 minutes (stops the burning process in deeper tissues). Remove wet clothing (if not stuck). Cover with clean plastic wrap. Calculate burn area (use palm method). Start IV fluids if >10% burned. Give pain relief. Administer Tetanus toxoid. Admit for observation and wound care.

🚑 Scenario 2: Fall from Mango Tree

  • Setting: A 7-year-old falls from a mango tree. Complains of leg pain and headache.
  • Nurse Actions: Primary survey — ABC. Immobilize leg with splint. Assess head injury (AVPU, pupils). Check for neck pain or spinal symptoms (immobilize c-spine if suspect). Transport to hospital. X-ray leg and possibly skull. Observe for 24 hours even if initial assessment is normal.

🚑 Scenario 3: Choking on Groundnut

  • Setting: A 3-year-old eating groundnuts suddenly cannot breathe, turns blue.
  • Nurse Actions: Assess severity (severe choking = cannot cough). Because child is over 1 year: 5 back blows ➔ 5 abdominal thrusts (Heimlich) ➔ repeat. If unconscious: start CPR. Call for help. Even if object is expelled, observe in hospital for airway swelling.

🚑 Scenario 4: Drowning in a Bucket

  • Setting: A 1-year-old found head-down in a bucket of water.
  • Nurse Actions: Remove from water. Check breathing. If not breathing: 5 rescue breaths ➔ start CPR. If breathing: recovery position, keep warm. Transport to hospital — ALL near-drowning cases need observation. Monitor for secondary drowning (worsening breathing hours later due to pulmonary edema from aspirated water).

📚 MASTER MNEMONICS SUMMARY

MnemonicMeaningUse
DRS ABCDDanger, Response, Send for help, Airway, Breathing, CPR, DefibrillationPrimary survey for ALL emergencies
AVPUAlert, Voice, Pain, UnresponsiveQuick consciousness check
COOL, COVER, CALLCool burn, Cover with clean dressing, Call for helpBurn first aid
RICERest, Ice, Compression, ElevationSoft tissue injuries (sprains)
SAMPLESigns/Symptoms, Allergies, Medications, Past history, Last meal, EventsHistory taking
VOMIT PUPILSVomiting, Obvious fluid, Mental changes, Irregular breathing, Thin pupils, Unequal pupils, Paralysis, Unconsciousness, Increased headache, Lethargy, SeizuresSerious head injury signs
Three E'sEducation, Environment, EnforcementAccident prevention framework

6️⃣ EXAM TIPS & KEY POINTS

High-Yield Exam Facts:

  • Children compensate for shock better than adults — they maintain blood pressure until very late. Tachycardia (fast heart rate) is the EARLY sign of shock in children, NOT low blood pressure.
  • The most common cause of cardiac arrest in children is RESPIRATORY FAILURE, not a primary heart attack like in adults. Fix the breathing first!
  • Never give aspirin to children — risk of Reye's syndrome (brain and liver damage).
  • For choking infants under 1 year, use BACK BLOWS and CHEST THRUSTS — NEVER abdominal thrusts (Heimlich) as it can rupture their liver.
  • For burns, cool with water for 20 minutes — this is the single most effective first aid measure and reduces burn depth.
  • The child's palm (including fingers) = 1% of body surface area — easiest way to estimate burns in the field.
  • All head injuries need observation — even if the child seems fine, deterioration can occur hours later (epidural hematoma).
  • Tetanus immunization is needed for ALL open wounds and burns if not up to date.
  • The home is the most dangerous place for children under 5 — not the road, not school.
  • Supervision is the #1 prevention strategy — no safety device replaces a watchful adult.

🎯 Common Exam Questions (Test Yourself!)

  • Q: A 3-year-old is brought in after falling from a veranda. He is crying but seems alert. What is your FIRST action?
    A: Primary survey (DRS ABCD) — check for danger, response, airway, breathing, circulation. Do NOT be distracted by the crying.

  • Q: A mother brings a child with a burn on the hand. She applied raw egg and oil. What do you do?
    A: Gently wash off the egg/oil with cool water. Explain to the mother that these trap heat and cause infection. Cool with water for 20 minutes, then cover.

  • Q: A 6-month-old is choking on a piece of banana. What is the correct sequence of actions?
    A: Assess severity ➔ 5 back blows (baby face-down on forearm) ➔ check mouth ➔ 5 chest thrusts (two fingers on center of chest) ➔ repeat ➔ CPR if unconscious.

  • Q: Why is a child with a head injury admitted for 24 hours even if they seem fine?
    A: Because of the risk of delayed intracranial hemorrhage (bleeding inside the skull). Symptoms like vomiting, confusion, or seizures may develop hours later due to slow bleeding.

Quick Quiz

Accidents Quiz

Paediatrics

Privacy: Your details are used only for quiz tracking and certificates.

Admit children involved in accidents Read More »

Provide first aid management of various accidents in children

Provide first aid management of various accidents in children

Children Involved in Accidents

1️⃣ INTRODUCTION & EPIDEMIOLOGY

What is an Accident?

An accident is an unexpected, unplanned event that causes injury or harm to a child. In nursing, we prefer the term "unintentional injury" because most of these events are preventable — they are NOT truly "accidents" if we can stop them from happening.

Why Are Children at High Risk? (The Physiology & Psychology)

  • They are naturally curious: They explore everything with their hands and mouths.
  • They cannot judge danger: A 2-year-old does not have the cognitive development (frontal lobe maturity) to know fire burns or water drowns.
  • They are physically small and fragile:
    • Physiological Expansion: Their bones are more porous and bend/break easily (greenstick fractures). Their skin is much thinner, meaning it burns faster and deeper at lower temperatures. Their airways are incredibly narrow (about the width of their pinky finger), so they block quickly with small objects or minor swelling.
  • They imitate adults: They copy cooking, driving, or using tools without understanding the risks.

The Ugandan Research

Research from Jinja, Uganda shows that over 270,000 children under 5 die globally each year from injuries, and Sub-Saharan Africa has the highest proportion of these deaths. In Uganda specifically:

Type of InjuryPercentage of Cases
Falls (from beds, verandas, trees)~57%
Burns (from stoves, hot water, fire)~23-34%
Cuts/Lacerations (from knives, pangas, glass)~19%
Poisoning (from medicines, kerosene, soap)Common but underreported
Drowning (in wells, buckets, ponds)Significant risk
Road Traffic InjuriesIncreasing rapidly

💡 Key Fact & Point for Attention

The majority of injuries happen at home or in the courtyard — NOT on the road. This means mothers and caregivers are the first and most important line of defense! In pediatric nursing, anticipatory guidance (educating parents on safety before an accident happens) is your most powerful tool.

2️⃣ FIRST AID MANAGEMENT OF VARIOUS ACCIDENTS IN CHILDREN

🚨 THE PRIMARY SURVEY: "DRS ABCD"

Before treating ANY injury, always follow this order. Never skip steps! (Pathophysiology note: The goal of this survey is to maintain cerebral perfusion—keeping oxygenated blood flowing to the brain to prevent irreversible hypoxic brain death, which occurs in just 4-6 minutes).

LetterMeaningWhat You Do
DDANGERMake sure the scene is safe for YOU first. Look for fire, electricity, traffic, or angry animals. If you get hurt, you cannot help the child.
RRESPONSECheck if the child is awake. Shout their name, gently tap their shoulder. For babies, tap the bottom of their foot (elicits a reflex cry).
SSEND FOR HELPCall for an ambulance or ask someone to run for help. In Uganda, call the nearest health facility or use a boda-boda if urgent.
AAIRWAYOpen the airway. For children: head-tilt, chin-lift. For infants: keep head in neutral position (not tilted back too far — their necks are soft and hyperextending can actually kink and block their trachea!).
BBREATHINGLook, listen, and feel for breathing for up to 10 seconds. Normal rates: Infant 30-40/min, Child 15-25/min.
CCPRIf not breathing normally, start CPR immediately to manually pump the heart and circulate blood.
DDEFIBRILLATIONUse AED if available (rare in rural Uganda, but know the skill to shock lethal arrhythmias like Ventricular Fibrillation back to a normal rhythm).

🧠 Mnemonic for Primary Survey

"Don't Run Straight Away — Check Breathing Carefully, Dear!"

🩸 A. BLEEDING INJURIES (Cuts, Lacerations, Wounds)

Types of Bleeding You Must Know

TypeSourceAppearanceDanger Level
ArterialArtery (carries high-pressure blood FROM heart)Bright red (highly oxygenated), spurts with heartbeatLIFE-THREATENING (Can bleed out in minutes)
VenousVein (carries lower-pressure blood TO heart)Dark red (deoxygenated), steady flowLIFE-THREATENING if a large vein (e.g., jugular, femoral)
CapillaryTiny surface vesselsOozes slowly, tricklesUsually NOT life-threatening

Step-by-Step First Aid Management

  • STEP 1: PROTECT YOURSELF. Wear gloves if available. If not, use a plastic bag or clean cloth over your hands. Why? Blood can carry HIV, Hepatitis B, and other infections.
  • STEP 2: SIT OR LAY THE CHILD DOWN. This prevents fainting from blood loss (shock). Raise the injured part above the level of the heart if possible — gravity slows bleeding by decreasing hydrostatic pressure.
  • STEP 3: APPLY DIRECT PRESSURE. Use a clean cloth, gauze, or clean clothing. Press firmly and directly on the wound. Do NOT remove the first cloth if it becomes soaked — add more layers on top. Why? The body is forming a delicate platelet plug (clot). Removing the bottom layer rips the clot off and restarts the bleeding!
  • STEP 4: ELEVATE THE LIMB. If the wound is on an arm or leg, raise it above heart level while keeping pressure.
  • STEP 5: APPLY A PRESSURE BANDAGE. Wrap firmly (but not so tight that fingers/toes turn blue or cold). Check circulation below the bandage every 15 minutes (capillary refill test).
  • STEP 6: IF BLEEDING DOES NOT STOP. Apply pressure to the pressure point above the wound:
    • Arm bleeding → press on the inner upper arm (brachial artery)
    • Leg bleeding → press on the groin (femoral artery)
    • As a LAST RESORT, a tourniquet may be used for life-threatening limb bleeding, but this can cause permanent ischemic damage. Mark the time it was applied!
  • STEP 7: TREAT FOR SHOCK (Hypovolemic). Lay child flat with legs raised (if no spinal injury) to shunt blood back to the brain and heart. Keep warm with a blanket. Reassure the child — crying increases sympathetic tone, heart rate, and blood pressure, making bleeding worse!
  • STEP 8: TRANSPORT TO HOSPITAL. All deep cuts need stitching and tetanus immunization. Cuts on the face, hands, or genitals need special surgical care.

💡 Exam Tip

The most common cause of preventable death after trauma is severe bleeding. Stop the bleed FIRST!

🔥 B. BURNS AND SCALDS

Types of Burns

DegreeWhat You SeeDepthHealing
First Degree (Superficial)Red, painful, dry skin (like a sunburn)Top layer only (epidermis)3-6 days, no scar
Second Degree (Partial Thickness)Blisters, very painful, wet/weepingEpidermis + upper dermis2-3 weeks, may scar
Third Degree (Full Thickness)White, charred, leathery, painless (nerve endings are destroyed!)All skin layers + deeper tissueMonths, requires surgery/skin grafts, severe scarring

Common Causes in Ugandan Homes

  • Open charcoal stoves (jiko) — children pull pots down or fall onto stoves
  • Hot porridge/food — children reach up to grab from the table
  • Hot water for bathing — mothers test with elbow but water is still too hot for infant skin
  • Flame burns — children playing with matches or near cooking fires
  • Electrical burns — exposed wires, low sockets, children putting fingers in holes

Step-by-Step First Aid Management

  • STEP 1: STOP THE BURNING. Remove child from heat source. If clothes are on fire: STOP, DROP, and ROLL. For chemical burns: Brush off dry chemicals first (adding water to some dry chemicals causes boiling!), then flush with water for 20 minutes.
  • STEP 2: COOL THE BURN. Run cool (not cold) water over the burn for at least 10-20 minutes. DO NOT use ice — this causes intense vasoconstriction, cutting off blood supply and causing MORE tissue damage (ischemia). DO NOT apply butter, oil, toothpaste, or raw eggs — these trap heat inside the tissues and act as a breeding ground for deadly bacteria.
  • STEP 3: REMOVE JEWELRY AND LOOSE CLOTHING. Do this BEFORE swelling starts (edema happens quickly due to massive fluid shifts). DO NOT remove clothing that is STUCK to the burn — cut around it.
  • STEP 4: COVER THE BURN. Use a clean, non-stick dressing — a clean plastic bag, cling film, or sterile gauze. DO NOT wrap tightly — burns swell. DO NOT pop blisters — the blister fluid is perfectly sterile and protects the raw skin below from infection.
  • STEP 5: KEEP THE CHILD WARM. Burns cause massive heat loss because the skin's thermoregulation is destroyed. Cover unburned areas with a blanket. Why? A child with a large burn can become severely hypothermic even in hot Uganda.
  • STEP 6: FLUID RESUSCITATION (Hospital Level). For burns >10% of body surface area, give IV fluids (Ringer's Lactate is preferred to combat acidosis).
    • Use the Parkland Formula (for exam purposes):
    • First 24 hours: 4 mL × weight (kg) × % burn area
    • Half of this total volume is given in the first 8 hours, the remaining half in the next 16 hours.
  • STEP 7: PAIN RELIEF. Give paracetamol or ibuprofen. For severe burns, stronger IV pain medicine (morphine) is needed in hospital.
  • STEP 8: TETANUS PROPHYLAXIS. All burn wounds are "dirty" wounds. Give tetanus toxoid if immunization is not up to date.

🧠 Mnemonic & Pediatric Rule

Mnemonic for Burn First Aid: "COOL it, COVER it, CALL for help!"

Rule of Nines for Children: The pediatric head is much larger proportionally than an adult's! The easiest community method to estimate burn size: The child's palm (including fingers) = exactly 1% of their body surface area.

🌊 C. DROWNING AND NEAR-DROWNING

What is Drowning?

Drowning happens when a child's airway goes under water (or other liquid) and they cannot breathe. Near-drowning means they were rescued but may still have water in their lungs.

Pathophysiology: Initially, water touching the vocal cords causes severe laryngospasm (the airway clamps shut to protect the lungs). If the spasm breaks, water rushes into the lungs, washing out surfactant (the soapy substance that keeps alveoli open). This causes the alveoli to collapse, leading to profound hypoxia.

Common Causes in Uganda

  • Falling into open wells, pit latrines, or ponds
  • Buckets of water left unattended (even 5 cm of water can drown a baby!)
  • Bathing alone in basins
  • Flooding during rainy seasons
  • Playing near rivers or dams

Step-by-Step First Aid Management

  • STEP 1: REMOVE FROM WATER SAFELY. Do NOT jump in if you cannot swim — you may drown too. Use a stick, rope, or throw a floating object. If you must enter, approach from behind so the panicking child does not pull you under.
  • STEP 2: CHECK FOR BREATHING. Lay child on their back on firm ground. Open airway and check breathing for 10 seconds.
  • STEP 3: IF NOT BREATHING — START CPR IMMEDIATELY.
    • Do NOT waste time trying to "drain water" from lungs — this does NOT work and wastes precious time.
    • Start with 5 rescue breaths first (Unlike standard adult CPR, pediatric drowning is an OXYGENATION problem, not a primary heart problem. The lungs need oxygen!).
    • Then continue with 30 compressions : 2 breaths ratio.
    • For Infants: Place two fingers on the center of the chest (just below nipple line). Compress 1/3 depth (about 3-4 cm). Rate: 100-120 per minute.
    • For Children: Use one or two hands on center of chest. Compress 1/3 depth (about 4-5 cm). Rate: 100-120 per minute.
  • STEP 4: CONTINUE CPR UNTIL... Child starts breathing on their own, Help arrives, or You are too exhausted to continue.
  • STEP 5: IF CHILD IS BREATHING BUT UNCONSCIOUS. Place in recovery position (on their side) to allow water/vomit drainage to flow out. Keep warm. Monitor breathing constantly — they may stop again.
  • STEP 6: ALL NEAR-DROWNING CASES NEED HOSPITAL. Even if the child seems completely fine, secondary drowning (ARDS - Acute Respiratory Distress Syndrome) can occur hours later. The water in the lungs causes massive inflammation, swelling, and delayed suffocation.

🧠 Mnemonic for Drowning Rescue

"Pull, Check, Breathe, Squeeze — Don't Delay!"

⚡ D. ELECTRICAL INJURIES

Common Causes in Uganda

  • Exposed wires at low height
  • Children putting fingers in socket holes
  • Playing near transformers or electrical poles
  • Lightning strikes during rainy season
  • Fallen power lines after storms

Step-by-Step First Aid Management

  • STEP 1: ENSURE YOUR OWN SAFETY FIRST. DO NOT touch the child if they are still in contact with electricity! Turn off the power source at the main switch if possible. If you cannot turn off power, use a dry wooden stick, plastic pipe, or rubber item to push the wire away. Water conducts electricity — do NOT stand in water.
  • STEP 2: CHECK RESPONSE AND BREATHING.
    Pathophysiology: Electrical current scrambles the heart's electrical pacemaker, causing immediate Ventricular Fibrillation (cardiac arrest). Check for breathing immediately. If not breathing, start CPR at once.
  • STEP 3: CHECK FOR BURNS. Electrical burns often have an entry wound (where electricity entered) and an exit wound (where it grounded and left the body, usually hands or feet). These may look like tiny pinholes on the outside but cause massive "iceberg" damage inside (cooking muscles, organs, and blood vessels along the path).
  • STEP 4: IMMOBILIZE IF SPINAL INJURY SUSPECTED. The electrical shock causes violent muscle tetany (spasms), which can literally throw a child through the air. They may have hidden spinal fractures. Do NOT move the child unnecessarily.
  • STEP 5: TREAT BURNS AS DESCRIBED ABOVE. Cover with clean, dry dressings.
  • STEP 6: TRANSPORT URGENTLY. All electrical injuries need hospital evaluation.
    Clinical Note: The internal muscle damage releases massive amounts of myoglobin into the blood (rhabdomyolysis), which travels to the kidneys and clogs them, causing acute kidney failure. They need massive IV fluids at the hospital to flush the kidneys!

❓ Applied Clinical Question

You find a toddler lying unconscious on the floor holding a frayed electrical wire. They are not breathing. You cannot find the main power switch. What is your FIRST action?

Answer: Do NOT touch the child! Your first action is to find a dry, non-conductive object (like a wooden broom handle or plastic chair) to knock the wire out of the child's hands. Only then can you safely begin DRS ABCD and CPR.

🦴 E. FRACTURES (BROKEN BONES)

Common Causes in Uganda

  • Falls from trees (mango trees are very common!)
  • Falls from bunk beds (very common in crowded homes)
  • Falls from verandas without guard rails
  • Road traffic accidents (motorcycles/boda-bodas)
  • Sports injuries at school

Signs of a Fracture

  • Pain at the site: Child refuses to move the limb.
  • Swelling and bruising: Caused by broken blood vessels inside the bone marrow and surrounding periosteum.
  • Deformity: The limb looks bent or twisted out of its normal anatomical alignment.
  • Inability to move or bear weight.
  • Crepitus: A grinding feeling or sound when the broken bone ends rub against each other (Warning: DO NOT test for this intentionally, as it causes excruciating pain and further tissue damage!).
  • Open fracture: The broken bone sticks through the skin. This is very serious due to the massive risk of deep bone infection (osteomyelitis).

Step-by-Step First Aid Management

  • STEP 1: DO NOT TRY TO STRAIGHTEN THE BONE. You can severely damage nearby nerves and blood vessels. Splint the limb in the exact position it was found.
  • STEP 2: IMMOBILIZE (SPLINT) THE INJURY. Use anything rigid: cardboard, wooden sticks, rolled newspaper. Pad the splint with cloth to prevent pressure sores. Secure with cloth strips, bandages, or torn clothing.
    Crucial Rule: Splint the joint above AND below the fracture. (Example: For a forearm fracture, immobilize both the wrist AND the elbow to prevent any rotational movement).
  • STEP 3: FOR OPEN FRACTURES. Do NOT push the bone back in. Cover the wound with a clean/sterile dressing to prevent environmental contamination. Do NOT apply pressure directly on the exposed bone.
  • STEP 4: CHECK CIRCULATION BELOW THE INJURY. Check pulse, warmth, and color of fingers/toes (Capillary refill).
    Pathophysiology (Compartment Syndrome): If the fingers are pale, cold, or numb, the splint may be too tight, or internal bleeding is crushing the blood vessels inside the muscle fascia. This is a medical emergency that can lead to amputation if not relieved!
  • STEP 5: ELEVATE IF POSSIBLE. Reduce swelling by raising the limb above heart level (decreases hydrostatic pressure).
  • STEP 6: APPLY COLD PACK. Wrap ice or cold water in a cloth and apply for 15-20 minutes to reduce swelling and numb pain (causes localized vasoconstriction). Do NOT apply ice directly to skin (causes ice burns/frostbite).
  • STEP 7: PAIN RELIEF. Give paracetamol. Do NOT give aspirin, as it inhibits platelets and increases bleeding risk.
  • STEP 8: TRANSPORT TO HOSPITAL. All suspected fractures need X-rays and proper casting/reduction by an orthopedic specialist.

🧠 F. HEAD INJURIES

Types of Head Injury

TypeDescriptionDanger
ConcussionBrain is shaken inside the skull, causing temporary confusion or memory loss.Usually recovers, but requires strict monitoring for deterioration.
ContusionActual bruising and microscopic bleeding of the brain tissue.More serious, can lead to localized swelling.
Skull FractureBroken bone of the skull (linear, depressed, or basilar).High risk of brain infection (meningitis) and underlying brain damage.
Intracranial HemorrhageBleeding inside the rigid skull (epidural, subdural, or subarachnoid).LIFE-THREATENING. The skull cannot expand, so blood crushes the brain stem.

Step-by-Step First Aid Management

  • STEP 1: CHECK AIRWAY AND BREATHING. Head injuries disrupt the vomiting center in the brain. Clear the mouth if vomiting occurs. If unconscious, place in the recovery position (on side) to prevent choking on vomit (aspiration).
  • STEP 2: DO NOT MOVE THE NECK. Assume a cervical spinal injury until proven otherwise. Hold the head steady with both hands (manual inline stabilization). If you must roll the child to clear vomit, do a log roll (the whole body turns as one unit to keep the spine perfectly straight).
  • STEP 3: CONTROL BLEEDING. Apply gentle pressure with a clean cloth.
    Exception: DO NOT apply pressure if you suspect a depressed skull fracture (you feel an indentation or see bone). Pressing will push bone shards directly into the brain tissue!
  • STEP 4: WATCH FOR SIGNS OF SERIOUS HEAD INJURY. Red flags that indicate rising Intracranial Pressure (ICP) requiring URGENT transfer:
    • Loss of consciousness (even briefly)
    • Repeated projectile vomiting
    • Seizures (convulsions/fits)
    • Severe, worsening headache
    • Confusion, irritability, or unusual behavior
    • Weakness or numbness on one side of the body (hemiparesis)
    • Unequal pupil size (one pupil is blown/dilated - indicates brain herniation crushing the oculomotor nerve!)
    • Clear fluid (CSF) or blood leaking from nose or ears
    • Bruising behind the ears (Battle's sign) or around eyes (Raccoon eyes) - classic signs of a Basilar Skull Fracture.
  • STEP 5: KEEP CHILD WARM AND CALM. Reassure them. Crying increases blood pressure, which increases the pressure inside the head (ICP).
  • STEP 6: MONITOR CONTINUOUSLY. Check the level of consciousness every 15 minutes using the AVPU scale:
    • A = Alert (awake and responding appropriately)
    • V = Responds to Voice (opens eyes when shouted at)
    • P = Responds to Pain (only moves when pinched)
    • U = Unresponsive (deep coma)

🧠 Mnemonic for Serious Head Injury Signs: "VOMIT PUPILS"

  • Vomiting (especially projectile)
  • Obvious fluid (CSF) from ears/nose
  • Mental changes (confusion)
  • Irregular breathing (part of Cushing's Triad)
  • Thin/unequal pupils
  • Paralysis/weakness
  • Unconsciousness
  • Pain (Increased severe headache)
  • Increased Lethargy (very sleepy/hard to wake)
  • Loss of memory
  • Seizures

🚑 G. CHOKING (FOREIGN BODY AIRWAY OBSTRUCTION)

Mild vs. Severe Choking

Mild ChokingSevere Choking
Child can cough forcefully, speak, or cry loudly.Child CANNOT cough effectively, speak, or make noise (silent panic).
Airway is only partially blocked.Airway is completely blocked. Lips may turn blue (cyanosis).
Action: Encourage coughing — do NOT interfere with slaps.Action: Act immediately — oxygen is cut off!

First Aid for Conscious Choking Infant (Under 1 Year)

  • STEP 1: ASSESS. Is it severe choking? Can the baby cry? Cough? Breathe? If NO → act immediately.
  • STEP 2: POSITION THE BABY. Sit down. Lay the baby face-down along your forearm. Support the baby's head and jaw with your hand (don't squeeze the throat). Keep the baby's head lower than their chest (gravity helps dislodge the object!).
  • STEP 3: GIVE 5 BACK BLOWS. Use the heel of your free hand. Strike firmly between the shoulder blades. Check the mouth after each blow — if you clearly see the object, remove it with a pinky finger sweep.
  • STEP 4: IF BACK BLOWS DON'T WORK — 5 CHEST THRUSTS. Turn the baby face-up along your forearm. Place two fingers on the center of the chest (same place as CPR). Push sharply downward 5 times. Check the mouth after each thrust.
    Pathophysiology Note: We do NOT use abdominal thrusts (Heimlich) on infants because their liver is relatively massive and unprotected by the ribcage. Abdominal thrusts will rupture the infant's liver and cause fatal internal bleeding!
  • STEP 5: REPEAT. Alternate 5 back blows and 5 chest thrusts until: The object comes out, the baby starts breathing/crying, or the baby becomes unconscious.
  • STEP 6: IF BABY BECOMES UNCONSCIOUS. Lay baby on a flat surface. Start CPR immediately (30 compressions : 2 breaths). Each time you open the airway to give breaths, look in the mouth — if you see the object, remove it.
    Crucial Rule: DO NOT do blind finger sweeps — you will push the object deeper past the vocal cords!

First Aid for Conscious Choking Child (Over 1 Year)

  • STEP 1: ENCOURAGE COUGHING. If mild choking, let their own diaphragmatic reflexes clear it.
  • STEP 2: IF SEVERE — 5 BACK BLOWS. Bend the child forward at the waist. Give 5 firm blows between the shoulder blades with the heel of your hand.
  • STEP 3: IF BACK BLOWS DON'T WORK — 5 ABDOMINAL THRUSTS (Heimlich Maneuver). Stand behind the child. Make a fist with one hand. Place the thumb side of your fist just above the belly button (navel). Grasp your fist with your other hand. Pull sharply inward and upward 5 times. (This artificially forces the diaphragm up, forcing air out of the lungs to pop the object out like a cork).
  • STEP 4: REPEAT. Alternate back blows and abdominal thrusts. If the child becomes unconscious, immediately begin CPR.

🧪 H. POISONING

Common Poisons in Ugandan Homes

  • Medicines left within reach (paracetamol, highly toxic adult antimalarials, iron pills).
  • Kerosene/paraffin (commonly used for lamps and stoves, often mistaken for water).
  • Pesticides/herbicides (dangerously stored in used soda or water bottles!).
  • Household cleaners, bleach, and soap (highly alkaline, burns the throat).
  • Plants (some ornamental or wild plants are toxic if eaten).
  • Cosmetics and traditional/herbal concotions (unknown dosages).

Step-by-Step First Aid Management

  • STEP 1: ENSURE YOUR OWN SAFETY. Make sure the poison is not still in the child's mouth or on their skin (wear gloves if handling pesticides). If a chemical gas is in the air, move to fresh air immediately.
  • STEP 2: IDENTIFY THE POISON. Look at the container/bottle. Smell the child's breath (e.g., kerosene smell, garlic smell for organophosphates). Ask the child or witnesses what was taken. Bring the container to the hospital — doctors need to know exactly what it was to give the specific antidote (e.g., Atropine for pesticides).
  • STEP 3: DO NOT GIVE ANYTHING BY MOUTH UNLESS INSTRUCTED.
    • DO NOT induce vomiting! If the chemical burned the esophagus going down (like bleach), it will burn it a second time coming back up. It also drastically increases the risk of aspiration.
    • DO NOT give milk, water, or other traditional "antidotes" (like raw eggs) unless a poison center or doctor specifically tells you to.
    • MAJOR EXCEPTION / WARNING: If the child swallowed petroleum products (kerosene, paraffin, petrol), DO NOT INDUCE VOMITING under any circumstances. These liquids are highly volatile; if vomited, fumes easily enter the lungs causing severe, often fatal chemical pneumonitis.
  • STEP 4: IF POISON IS ON THE SKIN. Remove contaminated clothing immediately (cut it off if necessary so it doesn't pull over the face). Rinse the skin with running water for at least 15-20 minutes to dilute and wash away the chemical.
  • STEP 5: IF POISON IS IN THE EYES. Rinse eyes with clean, running water for at least 15-20 minutes. Hold the eyelids open. Do NOT let the child rub their eyes (causes severe corneal abrasions).
  • STEP 6: IF POISON IS INHALED. Move the child to fresh air immediately. If not breathing, start CPR.
  • STEP 7: TRANSPORT TO HOSPITAL IMMEDIATELY. All poisonings need medical evaluation, observation, and potentially activated charcoal. Call ahead if possible so the hospital can prepare antidotes.

🧠 Mnemonic for Poisoning Response

"Identify, Don't Vomit, Transport!"

🚗 I. ROAD TRAFFIC ACCIDENTS (RTAs)

Common Causes in Uganda

  • Pedestrian accidents: Children crossing busy roads unsupervised.
  • Boda-boda accidents: Children riding as passengers without helmets, or being hit while walking.
  • Falling from vehicles: Children hanging on matatus or open lorries.
  • Bicycle accidents: Very common in rural areas on uneven dirt roads.

Step-by-Step First Aid Management (Trauma Protocol)

  • STEP 1: SCENE SAFETY. Stop traffic if possible to prevent a secondary crash. Use warning triangles, large branches, or bystanders to direct traffic. Watch out for fuel leaks or fire risk from the vehicles. Wear gloves.
  • STEP 2: PRIMARY SURVEY (DRS ABCD). This is where it all comes together! Check for danger, response, and breathing. Start CPR if the child is in cardiac arrest.
  • STEP 3: CONTROL SEVERE BLEEDING. Apply immediate, heavy direct pressure to spurting wounds. Use a tourniquet only for life-threatening limb bleeding that pressure cannot stop.
  • STEP 4: IMMOBILIZE SPINAL INJURIES. The kinetic energy of an RTA easily snaps a child's fragile cervical spine. Do NOT move the child unless absolutely necessary (e.g., the car is on fire).
    • If you MUST move them, use the log roll technique:
    • One person takes charge and holds the head steady (inline stabilization).
    • Others support the shoulders, hips, and legs.
    • On the leader's count, roll the entire body as one solid unit so the spine does not twist or bend.
  • STEP 5: TREAT SHOCK. Lay the child flat, keep them warm with jackets/blankets, and elevate the legs (only if you are certain there is no spinal or leg injury) to push blood back to vital organs.
  • STEP 6: DO NOT REMOVE IMPALED OBJECTS. If a stick, piece of glass, or vehicle metal is stuck deep in the child, stabilize it with bulky dressings wrapped around the base of the object.
    Pathophysiology: The object may be acting like a plug in a major severed artery. Removing it on the roadside will unplug the hole, causing the child to bleed to death in seconds!
  • STEP 7: TRANSPORT. Call an ambulance or arrange safe, flat transport immediately. Time is tissue—the "Golden Hour" of trauma means survival rates plummet if surgical care is delayed. Keep the child warm during transport.

❓ Applied Clinical Question

Case: You witness a boda-boda hit a 6-year-old child. The child is lying on the tarmac, crying loudly, and holding a strangely bent forearm. You notice a sharp piece of metal from the motorcycle deeply impaled in their thigh, but it is barely bleeding. You are about to put the child in a car to rush them to the clinic.

What are the TWO things you absolutely MUST NOT DO in this scenario?

Answer:

  1. Do NOT pull the piece of metal out of the thigh. It is likely tamponading (plugging) the femoral artery. Secure it in place with bandages.
  2. Do NOT try to straighten the bent forearm. Splint it exactly as you found it to prevent further nerve/vessel damage before transport.

Quick Quiz

Accidents Quiz

Paediatrics

Privacy: Your details are used only for quiz tracking and certificates.

Provide first aid management of various accidents in children Read More »

Wilms Tumor (Nephroblastoma)

Wilms Tumor (Nephroblastoma)

Wilms Tumor (Nephroblastoma)

I. What is Wilms Tumor (Nephroblastoma)?

Wilms tumor is a highly malignant embryonic cancer of the kidney that primarily occurs in young children (usually peaking between ages 3 to 4 years). It is the most common primary renal tumor in childhood.

  • Laterality: It usually affects only one kidney (unilateral) but can affect both kidneys (bilateral) in 5-10% of cases.
  • Embryological Pathophysiology (Expansion): It develops from abnormally persistent, immature embryonic kidney cells called the metanephric blastema. Instead of maturing into normal nephrons (glomeruli and tubules), these blastemal cells multiply out of control, forming a solid, highly vascular tumor.
  • Histology (Expansion): The prognosis heavily depends on the microscopic appearance.
    • Favorable Histology (FH): Well-differentiated cells (accounts for 90% of cases, highly curable).
    • Unfavorable / Anaplastic Histology (UH): Poorly differentiated cells with huge, distorted nuclei (often associated with TP53 gene mutations). Highly resistant to standard chemotherapy.

II. Etiology and Genetic Associations

While most cases are sporadic (random), about 10% are associated with specific genetic mutations, birth defects, and overgrowth syndromes. These usually involve mutations on Chromosome 11 (WT1 and WT2 genes).

  1. WAGR Syndrome: Caused by a deletion on Chromosome 11p13.
    • Wilms tumor (about 30-50% chance of developing it)
    • Aniridia (absence of the iris in the eye, causing severe light sensitivity/blindness)
    • Genitourinary anomalies (e.g., cryptorchidism, hypospadias)
    • Retardation (Intellectual/Mental disability)
  2. Denys-Drash Syndrome: Caused by a point mutation in the WT1 gene.
    • Wilms tumor (very high risk, ~90%)
    • Pseudohermaphroditism (male pseudohermaphroditism / ambiguous genitalia)
    • Early-onset kidney disease (nephropathy leading to rapid renal failure)
  3. Beckwith-Wiedemann Syndrome (BWS): An overgrowth syndrome linked to the WT2 gene (Chromosome 11p15).
    • Large birth weight (Macrosomia)
    • Macroglossia (abnormally large tongue)
    • Organomegaly (enlarged internal organs)
    • Omphalocele or umbilical hernia
    • Increased risk for embryonic tumors (Wilms tumor, hepatoblastoma).
  4. Hemihypertrophy: An asymmetrical overgrowth condition where one side of the body (or a single limb) is noticeably larger than the other. Strongly associated with Wilms tumor.

🧠 Mnemonic: Syndromes Associated with Wilms Tumor

Remember: "Wilms has a BAD WAGR"

  • Beckwith-Wiedemann Syndrome (Overgrowth, macroglossia)
  • Aniridia (Part of WAGR)
  • Denys-Drash Syndrome (Kidney disease, ambiguous genitalia)
  • WAGR (Wilms, Aniridia, GU anomalies, Retardation)

III. Signs and Symptoms (Clinical Presentation)

1. The Classic Triad:

  • Painless abdominal mass: Usually discovered incidentally by a parent while bathing the child or by a pediatrician during a routine exam. Crucial distinguishing factor: The mass is smooth, firm, and does NOT cross the midline (unlike Neuroblastoma, which is nodular and frequently crosses the midline). It moves downwards with respiration.
  • Abdominal pain: Present in about 30-40% of cases (often occurs if the tumor undergoes rapid growth causing capsular stretching, or bleeding within the tumor).
  • Blood in urine (Hematuria): Present in 15-25% of cases. Microscopic or macroscopic, resulting from tumor invasion into the renal collecting system.

2. Secondary Signs & Symptoms:

  • Hypertension (HTN): Physiological Expansion: Occurs in up to 25% of patients. Why? The growing tumor compresses the normal renal artery, leading to renal ischemia. The kidney responds by inappropriately secreting massive amounts of Renin, activating the RAAS pathway (Renin-Angiotensin-Aldosterone System), causing severe vasoconstriction and fluid retention. Rule: Check BP in ALL children with an abdominal mass!
  • Fever: Low-grade, unexplained (due to tumor necrosis or cytokine release).
  • Weight loss & Anorexia: Cachexia due to the high metabolic demand of the malignancy.
  • Anemia: Due to chronic disease, hematuria, or tumor hemorrhage.
  • Varicocele: Enlarged, dilated veins in the scrotum. Anatomical Expansion: Usually occurs on the LEFT side. Why? The left testicular/gonadal vein drains at a 90-degree angle directly into the Left Renal Vein. If a Wilms tumor extends a "tumor thrombus" into the left renal vein, it blocks gonadal drainage, causing backup and a varicocele.
  • Respiratory distress: Occurs if the massive tumor pushes up against the diaphragm, restricting lung expansion.
  • Cough & Hemoptysis: Suggests advanced disease with lung metastases (the lungs are the #1 site for Wilms tumor metastasis via hematogenous spread).

IV. Diagnosis & Staging

⚠️ ABSOLUTE NURSING PRIORITY: DO NOT PALPATE THE ABDOMEN!
Once a Wilms tumor is suspected, place a large warning sign over the child's bed reading: "DO NOT PALPATE ABDOMEN." The tumor is highly friable and encapsulated by a thin, fragile membrane. Hard or repeated palpation can cause the capsule to rupture, spilling millions of cancer cells into the peritoneal cavity, instantly upgrading the cancer to Stage III and drastically worsening the prognosis.

1. Physical Examination:

  • Inspect the abdomen (avoid deep palpation).
  • Measure blood pressure in both arms (to check for renin-induced HTN).
  • Examine genitals for anomalies (hypospadias/cryptorchidism for WAGR/Denys-Drash).
  • Check for aniridia (look closely at the iris with a penlight).
  • Assess for hemihypertrophy.
  • Listen to lungs (checking for effusions or metastatic masses).

2. Laboratory Tests:

  • FBC (Full Blood Count): Anemia is common.
  • Urinalysis: Checks for microscopic blood and protein.
  • Kidney Function Tests (BUN, Creatinine): Usually normal unless bilateral, but baseline is needed before nephrectomy.
  • Liver function tests & Coagulation studies: Essential baseline before major surgery.

Note on Tumor Markers: Unlike Neuroblastoma (which has elevated VMA/HVA in urine), Wilms tumor has no specific diagnostic tumor markers in the blood or urine.

3. Imaging Studies:

  • Ultrasound: The first-line, non-invasive test. Differentiates a solid tumor from a fluid-filled cyst. Checks both kidneys and evaluates if the tumor is invading the renal vein or inferior vena cava (IVC).
  • CT scan (Abdomen/Pelvis): Provides exact anatomical detail, size, lymph node involvement, and checks the opposite kidney and liver for metastasis.
  • MRI: Superior for visualizing IVC tumor thrombus extension (which can reach all the way into the right atrium of the heart!).
  • Chest X-ray / Chest CT: Absolutely essential to rule out lung metastases (the most common site of distant spread).

4. Biopsy Principle:

  • Generally CONTRAINDICATED before surgery in unilateral Wilms tumor. You do not want to risk seeding the needle tract or spilling the tumor. The diagnosis is confirmed pathologically after the entire kidney is removed en bloc.
  • Exceptions: A biopsy is only done if the tumor looks highly atypical, if both kidneys are involved (bilateral), or if the tumor is deemed inoperable and needs chemotherapy to shrink it first.

V. Staging (NWTS/COG System)

Staging defines the extent of spread and directly dictates the intensity of chemotherapy and radiation required.

StageDescription
Stage ITumor is completely confined to the kidney and was completely completely removed with the capsule fully intact (no spillage).
Stage IITumor extends beyond the kidney (into renal fat or blood vessels) but was still completely removed with no residual cancer left behind.
Stage IIINon-hematogenous residual tumor left in the abdomen. This includes positive lymph nodes, incomplete resection, or tumor spillage/rupture before or during surgery. (Requires abdominal radiation).
Stage IVHematogenous distant metastases (spread via blood to the lungs, liver, bone, or brain).
Stage VBilateral kidney involvement at the time of initial diagnosis.

VI. Management & Nursing Care

IMPORTANT PRINCIPLE: The gold standard treatment involves a combination of Surgery, Chemotherapy, and sometimes Radiation. The exact sequence depends on the protocol (COG in America prefers upfront surgery; SIOP in Europe prefers upfront chemotherapy to shrink it first).

A. SURGERY (Radical Nephrectomy)

Goal: Remove the entire affected kidney, tumor, surrounding fat, and adrenal gland en bloc (all in one piece) without rupturing the capsule.

Pre-operative Nursing Care:

  • Signage: DO NOT palpate abdomen!
  • Blood pressure control: Give antihypertensives (e.g., Nifedipine, Captopril/Enalapril) if renin-induced HTN is present to prevent intra-op stroke.
  • Treat anemia: Transfuse packed RBCs if severely anemic to optimize oxygen delivery for surgery.
  • NPO & IV Access: 6-8 hours fasting. Ensure large-bore IV access and cross-match blood (tumors are highly vascular; high risk of massive hemorrhage).
  • Bowel preparation: Sometimes needed if the massive tumor is compressing the colon.
  • Psychological preparation: Explain to the child (using age-appropriate terms) that the "lump in their belly" will be removed. Comfort parents who are often shocked by the sudden diagnosis.

Post-operative Nursing Care:

  • Fluid Balance (CRITICAL): The child now only has ONE kidney. Strict Intake/Output monitoring is mandatory.
  • Urine Output: Monitor hourly. Must be >1 mL/kg/hour. Danger Sign: If urine output drops, notify the doctor immediately. It could indicate failure of the solitary remaining kidney, severe dehydration, or surgical obstruction of the remaining ureter.
  • Electrolytes: Monitor for hyperkalemia (high potassium) due to acute kidney injury or tumor lysis.
  • Blood pressure: Monitor regularly. The remaining kidney can still secrete excess renin in response to fluid shifts, or the child may be hypotensive from surgical bleeding.
  • Positioning & Activity: Semi-Fowler's (head elevated 30-45 degrees) to drop the abdominal organs away from the diaphragm, improving respiratory excursion. Early, gentle mobilization to prevent DVT/pneumonia, but avoid straining.
  • Pain Management: Epidural or PCA (patient-controlled analgesia) with IV morphine. Crucial Contraindication: AVOID NSAIDs (like Ibuprofen/Diclofenac) because they decrease renal blood flow and can damage the single remaining kidney!
  • Wound Care: Monitor the large flank/transabdominal incision for bleeding, hematoma, or infection. Monitor surgical drains.
  • Bowel Function: Risk of paralytic ileus. Maintain NPO with IV fluids until bowel sounds return and flatus is passed, then progress from clear liquids to a regular diet.

❓ Clinical Scenario: IVC Thrombus

Case: A child's preoperative MRI shows the Wilms tumor has grown a "tail" (tumor thrombus) straight up the renal vein and into the Inferior Vena Cava (IVC), almost reaching the heart. What specific post-operative complication must you monitor for?

Answer: Deep Vein Thrombosis (DVT) and Pulmonary Embolism (PE). Removing an IVC tumor often requires complex vascular reconstruction or bypass. The nurse must strictly monitor lower limb circulation, swelling, and administer prescribed anticoagulants (Heparin/LMWH) to prevent fatal clots.

B. CHEMOTHERAPY

Used for almost all stages (except some very early Stage I favorable tumors). Chemotherapy shrinks metastases and kills micrometastatic disease.

The Regimens & Specific Toxicities (Expansion):

  • Vincristine: A mitotic inhibitor. Side effects: Peripheral neuropathy (foot drop, loss of reflexes), severe constipation, and paralytic ileus. (Monitor bowel movements strictly!).
  • Dactinomycin (Actinomycin D): An antitumor antibiotic. Side effects: It is a severe vesicant (causes massive tissue necrosis if the IV line leaks). Ensure perfect IV patency; never give IM/SubQ. Can also cause liver toxicity (Veno-occlusive disease).
  • Doxorubicin (Adriamycin): Added for Stage III/IV. Side effects: Cardiotoxicity. Can cause irreversible heart failure years later. A baseline Echocardiogram is mandatory before starting.
  • Cyclophosphamide & Etoposide: Added for high-risk or anaplastic (unfavorable) histology. Side effects: Hemorrhagic cystitis (requires aggressive hydration).
  • Radiation Recall: If a child receives Dactinomycin or Doxorubicin and later receives abdominal radiation, the skin that was previously irradiated may suddenly become bright red, blistered, and inflamed (Radiation Recall Dermatitis).

C. RADIATION THERAPY

  • Indications: Used for Stage III (if the tumor ruptured/spilled), Stage IV (to treat lung/brain mets), or any stage with Unfavorable Histology. Usually applied to the whole abdomen or flank.
  • Nursing Care: Gentle skin care (no harsh soaps/lotions). Aggressive nausea/vomiting management. Monitor for radiation enteritis (severe diarrhea, cramping) and bowel obstruction due to radiation-induced inflammation and strictures.

VII. Special Situations & Complications

A. Bilateral Wilms Tumor (Stage V)

  • Goal: Preserve as much functional kidney tissue as absolutely possible to prevent the child from becoming dependent on lifelong dialysis.
  • Management: Standard protocol is flipped. A biopsy is done first to confirm histology. Then, neoadjuvant (pre-surgery) chemotherapy is given for several weeks to shrink both tumors. Finally, Nephron-sparing surgery (Partial Nephrectomy) is performed to cut out the tumors while leaving healthy kidney tissue behind.
  • Nursing Care: Exquisitely careful fluid and electrolyte management post-op. Long-term monitoring of GFR and renal function. Dialysis may be required if insufficient tissue survives.

B. Immediate & Long-Term Complications

  1. Tumor Rupture / Spillage:
    • Can happen from trauma (seatbelt injury), rough handling, or intra-operatively.
    • Consequence: Instantly increases the stage to Stage III, requiring highly toxic whole-abdominal radiation.
    • Nursing: If sudden rupture is suspected pre-op (sudden massive increase in abdominal pain, rapidly dropping BP/shock), prepare for emergency surgery and monitor for chemical peritonitis.
  2. Post-operative Bleeding:
    • The tumor bed and renal vessels are massive. A slipped surgical ligature can cause fatal internal bleeding.
    • Signs: Tachycardia, hypotension, pallor, rapidly distending abdomen, sudden massive increase in bloody drain output.
    • Management: Immediate fluid resuscitation, blood transfusion, and rush back to the OR for re-exploration.
  3. Acute Kidney Injury (AKI):
    • From the remaining kidney being overwhelmed, severe hypovolemia (dehydration), or administration of nephrotoxic drugs (e.g., Gentamicin, NSAIDs). Dialysis may be temporarily needed.
  4. Long-Term Survivorship Complications:
    • Renal Failure: Chronic kidney disease years later due to hyperfiltration injury of the single remaining kidney.
    • Heart Failure: Dilated cardiomyopathy from Doxorubicin toxicity.
    • Secondary Primary Malignancies: Developing leukemia or bone cancer decades later as a direct result of DNA damage from the childhood chemotherapy and radiation.
    • Musculoskeletal problems: Flank radiation stunts bone and muscle growth on that side, leading to severe scoliosis (curvature of the spine) and underdeveloped abdominal muscles.

VIII. Prognosis

Wilms tumor represents one of the great success stories of modern pediatric oncology. Due to highly coordinated, multi-disciplinary protocol treatments (surgery + chemo + radiation), survival rates are excellent.

  • Overall Cure Rate: ~90%
  • Stage I-II (Favorable Histology): >95% survival.
  • Stage III: 85-90% survival.
  • Stage IV (Metastatic): 70-80% survival (requires highly intensive, toxic treatment).
  • Unfavorable Histology (Anaplastic): Prognosis drops significantly to 50-70% due to chemo-resistance.
  • Bilateral (Stage V): 70-80% with a careful kidney-sparing approach.

Quick Quiz

Wilms Tumor Quiz

Paediatrics

Privacy: Your details are used only for quiz tracking and certificates.

Wilms Tumor (Nephroblastoma) Read More »

Brain Tumors and Neuroblastoma

Brain Tumors and Neuroblastoma in Children

Brain Tumors & NEUROBLASTOMA

I. What is a Brain Tumor?

A brain tumor is an abnormal growth of cells inside the skull. Because the skull is a hard box that cannot expand, any growth inside creates pressure and damages the brain.

💡 Physiological Expansion: The Monro-Kellie Doctrine

To truly understand brain tumors, you must understand the Monro-Kellie Hypothesis. The skull is a rigid, closed vault containing exactly three things: Brain tissue (80%), Blood (10%), and Cerebrospinal Fluid/CSF (10%).

Because the skull cannot expand, if a 4th component (a tumor) starts growing, one of the other three must be pushed out to make room. First, CSF is pushed down the spine. Then, blood flow is restricted (causing brain ischemia). Finally, the brain tissue itself is pushed out through the bottom of the skull (Herniation), which is fatal.

II. Types Common in Children

  1. Medulloblastoma:
    • Most common malignant brain tumor in children.
    • Starts in the cerebellum (the back of the brain, which controls balance and coordination).
    • Can spread through the spinal fluid (often called "drop metastases" because gravity pulls the cancer cells down the spinal cord).
    • More common in boys.
  2. Low-Grade Glioma (Astrocytoma):
    • Slow-growing, often benign.
    • Pathophysiology: Arises from astrocytes, the star-shaped glial cells that normally form the Blood-Brain Barrier.
    • Can be located in the cerebellum or the optic nerve (affecting vision).
    • Pilocytic astrocytoma is the most common type.
  3. Ependymoma:
    • Starts in the ventricles (the fluid spaces in the brain).
    • Pathophysiology: Arises from ependymal cells, the ciliated cells that line the ventricles and help produce/circulate CSF.
    • Can physically block cerebrospinal fluid (CSF) flow, causing a backup of fluid known as hydrocephalus.
  4. Brainstem Glioma:
    • Located in the brainstem (the medulla, pons, and midbrain).
    • Physiological Danger: The brainstem is the control center for vital, involuntary functions like breathing, heart rate, and blood pressure.
    • Difficult (or impossible) to operate on without killing the patient.
    • Often has a very poor prognosis.
  5. Craniopharyngioma:
    • Located near the pituitary gland (the hormone control center of the body).
    • Affects growth (Growth Hormone disruption), vision (it presses on the optic chiasm causing bitemporal hemianopsia/tunnel vision), and water balance.
    • Water Balance: Can cause Diabetes Insipidus due to a lack of Anti-Diuretic Hormone (ADH), leading to massive, dilute urination.

III. Signs and Symptoms

Symptoms heavily depend on the tumor's location, its size, and the child's age.

A. Signs of Increased Pressure in the Skull (Increased ICP):

  • Headache: Worse in the morning, wakes the child from sleep, and gets worse with coughing or straining (Valsalva maneuver increases pressure).
  • Vomiting: Especially in the morning, projectile (shoots out forcefully), and notably occurs without nausea.
    Physiology tip: Why worse in the morning? When sleeping flat, gravity doesn't help drain venous blood from the head. Also, breathing slows during sleep, retaining CO2. CO2 is a potent vasodilator, which increases blood volume in the brain, spiking the ICP first thing in the morning!
  • Bulging fontanelle: Seen in infants because the "soft spot" on the head bulges out (their skull bones are not yet fused).
  • Sunset eyes: In infants – the eyes look downward, and the white of the eye (sclera) shows above the iris. (Parinaud syndrome from dorsal midbrain compression).
  • Increased head circumference: In infants and young children, the head literally grows faster than normal because the unfused skull sutures stretch apart.
  • Irritability: Infant cries constantly, pitched in a high tone, and cannot be comforted.
  • Lethargy: Child sleeps excessively, hard to wake.

B. Signs of Cerebellum Problems:

  • Ataxia: Unsteady walking, falling to one side, wide-based gait (feet far apart to maintain balance).
  • Tremor: Shaking hands specifically when reaching for objects (Intention tremor).
  • Dysmetria: Misses target when reaching (overshoots or undershoots).
  • Nystagmus: Eyes move back and forth involuntarily.

C. Other Signs:

  • Seizures: New-onset seizures in a previously healthy child are highly suspicious of a brain mass.
  • Vision changes: Squinting, double vision (diplopia), loss of peripheral vision, child bumps into things.
  • Behavior changes: Personality changes, school performance drops, memory problems (especially if in frontal/temporal lobes).
  • Weakness: One side of the body weaker than the other (hemiparesis) due to motor cortex compression.
  • Cranial nerve palsies: Facial droop, difficulty swallowing, hoarse voice, tongue deviation.
  • Endocrine problems: Growth failure, diabetes insipidus (excessive thirst and urination), delayed or early puberty.

IV. Diagnosis

  1. Neurological Examination:
    • Check cranial nerves (pupil response, eye movements, facial sensation, hearing, gag reflex, tongue movement, shoulder shrug).
    • Check strength and sensation in all limbs.
    • Check balance and coordination (heel-to-toe walking, finger-to-nose test).
    • Check fundoscopy (looking at the back of the eye with an ophthalmoscope) for papilledema (swelling of the optic disc from severe intracranial pressure pushing down the optic nerve).
  2. Imaging:
    • CT Scan: Quick, available in many Ugandan hospitals. Shows tumor location, size, bleeding, and hydrocephalus. Downside: Uses radiation.
    • MRI: Better detail, no radiation. Shows exact tumor type and relation to important brain structures. May require sedation or general anesthesia in young children (because they must stay perfectly still).
    • Nursing care for MRI: Remove all metal objects (hair clips, jewelry, coins), check for implants, explain loud noises to the child, give sedation as ordered, monitor vitals during scan if anesthesia used, ensure child is NPO (nothing by mouth) if sedated.
  3. Lumbar Puncture (LP):
    • Checks for tumor cells in spinal fluid.
    • CRITICAL WARNING: Only done AFTER imaging confirms no risk of brain herniation! If intracranial pressure is very high, doing an LP creates a low-pressure vacuum below the brain. The brain will instantly be sucked down through the foramen magnum (coning/herniation), which is instantly fatal.
  4. Biopsy or Surgery:
    • Tissue sample needed for exact, definitive diagnosis (grading and typing). May be done as part of the surgery to remove the tumor.

V. Management: SURGERY

Goal: Remove as much tumor as safely possible without damaging healthy brain tissue (Maximal safe resection).

Pre-operative Nursing Care:

  • Psychological preparation: Explain to the child (use dolls, pictures), reassure parents, allow parents to stay until anesthesia takes effect.
  • Shave head: Only shave the minimal area needed (do not shave entire head unless necessary). Use clippers, not razors (razors create micro-abrasions that drastically increase infection risk).
  • Steroids: Usually Dexamethasone to reduce brain swelling around the tumor. Nursing Monitor: Watch for high blood sugar (steroid-induced diabetes), mood changes, increased appetite, and GI bleeding.
  • Anticonvulsants: Given prophylactically if the child has seizures or if the tumor is near a seizure-prone area (like the cortex).
  • Baseline assessment: Document exact neurological status (strength, speech, vision) BEFORE surgery for comparison after surgery. (If they wake up weak, you need to know if it's new!).
  • NPO: Nothing by mouth for 6-8 hours before surgery to prevent aspiration under anesthesia.
  • IV access: Ensure good IV line, type and cross-match blood for possible transfusion.

Post-operative Nursing Care (CRITICAL):

  • Positioning: Head of bed elevated 30-45 degrees to reduce brain pressure. Keep head in a neutral midline position (not twisted). Avoid neck flexion, which blocks the jugular veins and prevents blood from draining out of the brain!
  • Neurological checks: Every 15 minutes for the first hour, every 30 minutes for 2 hours, then every hour for 24 hours, then every 4 hours. Check:
    • Level of consciousness (AVPU: Alert, Voice, Pain, Unresponsive; or GCS: Glasgow Coma Scale).
    • Pupil size and reaction to light (use penlight).
    • Movement of all four limbs.
    • Vital signs (blood pressure, pulse, respiration, temperature).

🚨 EMERGENCY ALERT: Cushing's Triad

Cushing's Triad is a late, critical sign of severe brain pressure (impending herniation). It consists of:

  1. High blood pressure (Widening pulse pressure)
  2. Slow pulse (Bradycardia)
  3. Irregular breathing (Cheyne-Stokes respirations)
Physiology: The brainstem is being crushed and is starving for oxygen. It sends a massive sympathetic surge to squeeze all blood vessels in the body to force blood up into the head (High BP). The heart baroreceptors sense this extreme BP and reflexively slow the heart down (Bradycardia). The crushed brainstem loses its rhythmic respiratory control (Irregular breathing).
  • Fluid management: Strict input/output charting. Often fluid restriction is ordered (e.g., 2/3 maintenance) to prevent brain swelling. Use a pediatric infusion pump. Avoid hypotonic fluids (like plain dextrose water) because they cause water to rush into cells, which will drastically worsen brain swelling.
  • Pain management: Codeine, paracetamol, morphine if severe. Avoid NSAIDs (aspirin, ibuprofen) due to the risk of intracranial bleeding.
  • Seizure precautions: Keep suction and oxygen ready, padded side rails. Do not restrain during a seizure, turn head to side, time the seizure, and give diazepam or lorazepam if it lasts >5 minutes.
  • Wound care: Keep dressing clean and dry. Check for a CSF leak (clear fluid dripping from the wound, nose, or ear). Check for the "halo sign" on gauze (blood in the center, surrounded by a yellowish ring of CSF). Check for bleeding, swelling, redness.
  • Temperature control: Avoid fever! Fever increases brain metabolism and swelling. Use paracetamol and cooling measures. Watch closely for infection.
  • Nutrition: Start with clear liquids when awake, progress to a regular diet as tolerated. Some children have swallowing problems (dysphagia) after posterior fossa surgery – do a swallowing assessment first.
  • Communication: Child may have temporary or permanent speech problems. Use picture boards, gestures, patience.

VI. Specific Post-op Complications

  • Posterior fossa syndrome: After cerebellum surgery, the child may be mute, emotionally labile, have swallowing problems, and weakness. Usually temporary but can last weeks. Requires intensive rehabilitation.
  • Hydrocephalus: If CSF flow is blocked, they may need a temporary external ventricular drain (EVD) or a permanent shunt.
  • EVD nursing care: Keep the drainage system at the correct prescribed level (usually 15cm above the ear). Do not let it drop below level (too much drainage causes the brain ventricles to collapse and tear blood vessels, causing bleeding). Do not raise it above level (drainage stops, pressure builds). Keep system closed (do not disconnect). Monitor CSF color (should be clear/straw-colored; blood or pus is abnormal). Monitor amount hourly. Never clamp without a doctor's order!
  • Aseptic meningitis: Fever, headache, stiff neck after surgery (not caused by bacteria, but by chemical irritation from blood/tissue in the CSF). Usually responds to steroids.
  • Cranial nerve damage: Facial weakness, hearing loss, swallowing problems. May need a feeding tube, or eye protection/taping if they cannot blink.

VII. Management: CHEMOTHERAPY

Used for tumors that cannot be completely removed or that tend to spread.

  • Medulloblastoma: Chemotherapy is essential (vincristine, cisplatin, lomustine, cyclophosphamide).
  • Ependymoma: May need chemotherapy if there is residual or recurrent tumor.
  • Glioma: Less responsive to chemotherapy; surgery and radiation are the main treatments.
  • Special considerations for brain tumor chemotherapy:
    • Many systemic drugs cannot cross the blood-brain barrier.
    • Intrathecal chemotherapy (injected directly into the spinal fluid) may be used to bypass the barrier.
    • High-dose methotrexate requires highly specialized monitoring (hydration, leucovorin rescue).

VIII. Management: RADIATION THERAPY

Used for medulloblastoma, ependymoma, and some gliomas.

  • Craniospinal irradiation is used for medulloblastoma (radiating the whole brain and the entire spine because it drops metastases).
  • Nursing care:
    • Skin care (gentle washing, no perfumes, use loose hats).
    • Fatigue management.
    • Monitor for somnolence syndrome (excessive, profound sleepiness occurring 4-6 weeks after radiation ends).
    • Monitor for endocrine problems (growth hormone deficiency, thyroid problems due to radiation scatter).
    • Cognitive decline: Especially profound in young developing brains. Medical teams try to avoid radiation in children under age 3 if at all possible.

IX. SHUNT MANAGEMENT (For Hydrocephalus)

  • Ventriculoperitoneal (VP) shunt: A surgically implanted tube that runs from the brain ventricle, under the skin, down to the abdomen (peritoneum) to drain excess CSF.
  • Nursing care: Monitor for shunt malfunction (headache, vomiting, lethargy, irritability, sunsetting eyes, increased head size).
  • Monitor for infection (fever, redness tracking along the shunt tract under the skin, abdominal pain, peritonitis).
  • If an infection occurs, it usually requires surgical removal of the shunt, placement of an external drain, and heavy IV antibiotics.

X. Prognosis Overview

  • Pilocytic astrocytoma: >90% cure rate with surgery alone.
  • Medulloblastoma: 70-80% cure rate with surgery + radiation + chemotherapy (Prognosis is worse if it has metastasized or if there is residual tumor).
  • Ependymoma: 50-70% survival depending on location and if it was completely removed.
  • Brainstem glioma: Very poor, especially diffuse intrinsic pontine glioma (DIPG) – generally has a 9-12 months median survival.

🧠 Mnemonic: Brain Tumor Post-Op Nursing Priorities

Remember "H.E.A.D." to monitor the post-op brain tumor patient:

  • Head elevated 30-45° (Promotes venous drainage)
  • Evaluate Neuro status often (GCS, Pupils, Cushing's triad)
  • Assess for CSF leaks (Check dressings for Halo sign)
  • Decrease metabolic demands (Strict fever control, pain meds, avoid seizures)

NEUROBLASTOMA

What is Neuroblastoma?

Cancer that develops from immature nerve cells (neuroblasts). It usually starts in the adrenal glands (the small glands on top of the kidneys that make stress hormones) or along the sympathetic nerve chain in the spine/abdomen/chest. It is most common in infants and children under 5 years.

Why Does It Happen?

It develops from fetal neural crest tissue that fails to mature properly. The MYCN oncogene amplification makes it highly aggressive.

Signs and Symptoms

Primary Tumor Signs:

  • Abdominal mass: Firm, irregular mass that crosses the midline of the abdomen. (High-Yield Differential: Wilms tumor is usually smooth and stays on one side).
  • Abdominal pain, distension, constipation.
  • Hypertension: High blood pressure caused by kidney artery compression OR the tumor directly secreting catecholamines (adrenaline).
  • Respiratory distress if a chest tumor compresses the lungs.

Metastasis Signs (Spreads Early!):

  • Bone pain: Child refuses to walk, cries when moved.
  • Periorbital ecchymosis ("Raccoon eyes"): Bruising around both eyes caused by tumor metastasis into the orbital bones.
  • Proptosis: Bulging eyes.
  • Bone marrow failure: Anemia, bruising, infection (clinically looks like leukemia).
  • Skin nodules: Blue/purple skin nodules in infants ("blueberry muffin baby").
  • Hepatomegaly: Massive liver enlargement in infants (Stage 4S).

Paraneoplastic Syndromes (Caused by tumor secretions):

  • Opsoclonus-myoclonus syndrome: "Dancing eyes, dancing feet." Rapid, irregular eye movements and jerking muscles. (Associated with a better tumor prognosis, but the neurological damage can be permanent).
  • Secretory diarrhea: The tumor secretes Vasoactive Intestinal Peptide (VIP), causing severe watery diarrhea and dehydration.
  • Sweating and Palpitations: From catecholamine release.
❓ Clinical Scenario: Wilms vs. Neuroblastoma

Case: A 3-year-old child presents with a large abdominal mass. How can the nurse differentiate between Wilms Tumor (Nephroblastoma) and Neuroblastoma during physical assessment?

Answer: During palpation, a Wilms tumor typically feels smooth and is confined to one side of the abdomen (does not cross the midline). A Neuroblastoma usually feels nodular/irregular and heavily crosses the midline. Additionally, if the child has "raccoon eyes" or severe hypertension, it points strongly to Neuroblastoma.

Diagnosis & Staging

  1. Laboratory Tests:
    • Urinary catecholamines (VMA and HVA): Elevated in 90% of cases. This is the key diagnostic marker! (Because the tumor grows from adrenal medullary cells, it spits out adrenaline breakdown products into the urine).
    • FBC, LDH, Ferritin, Neuron-specific enolase (NSE).
  2. Imaging: Ultrasound, CT/MRI, Bone scan. MIBG scan: A special nuclear medicine scan using radioactive iodine that targets neuroblastoma cells. It lights up all primary and metastatic sites.
  3. Biopsy: Bilateral bone marrow aspiration (both hips), tumor biopsy, and MYCN amplification testing (crucial for prognosis).
  4. Staging (INSS):
    • Stage 1: Localized, completely removed.
    • Stage 2: Localized with residual or lymph node involvement.
    • Stage 3: Large tumor crossing midline.
    • Stage 4: Spread to distant lymph nodes, bone, marrow, liver, skin.
    • Stage 4S: Special "magic" stage for infants (<1 year) with spread limited to liver, skin, and/or minimal bone marrow. It frequently spontaneously regresses and cures itself!

Management of Neuroblastoma

  • LOW RISK: (Stage 1, some Stage 2, Stage 4S). Surgery alone, or observation only (for 4S spontaneous regression).
  • INTERMEDIATE RISK: (Stage 3, some Stage 4 in infants). Surgery + Moderate chemotherapy (Carboplatin, cyclophosphamide, doxorubicin, etoposide) for 4-8 cycles.
  • HIGH RISK (Very Intensive): (Stage 4 in children >18 months, or MYCN amplified).
    • Induction chemo: Cisplatin, etoposide, doxorubicin, cyclophosphamide, vincristine. (Intense immunocompromise monitoring).
    • Surgery & Radiation: To remove shrunk tumors and radiate metastatic sites.
    • Autologous Stem Cell Transplant: Collect the child's own stem cells, blast the body with lethal high-dose chemo (busulfan, melphalan) to kill hidden cancer cells, then rescue the patient by giving their stem cells back. (Nursing: Strict isolation, intense mucositis).
    • Differentiation therapy: 13-cis-retinoic acid (isotretinoin/Accutane) for 6 months post-transplant. It chemically forces any remaining primitive neuroblastoma cells to mature into harmless normal nerve cells! (Nursing: Causes severe dry skin/lips. Highly teratogenic. Avoid Vit A).
    • Immunotherapy: Anti-GD2 antibody (dinutuximab). Targets GD2, a protein on neuroblastoma cells. Side effects: GD2 is also on pain nerves, causing horrific severe pain requiring continuous IV morphine. Also causes Capillary Leak Syndrome (massive swelling, hypotension). Pre-medicate heavily!

Prognosis: Low risk (>95%), Intermediate (80-90%), High risk (40-50% despite brutal treatment). Stage 4S is excellent. MYCN amplification always means a worse prognosis.

Quick Quiz

Brain & Neuroblastoma Quiz

Paediatrics

Privacy: Your details are used only for quiz tracking and certificates.

Brain Tumors and Neuroblastoma in Children Read More »

Intro to Childhood Tumors and Leukemia

Intro to Childhood Tumors and Leukemia

INTRODUCTION TO CHILDHOOD TUMORS

What is a Tumor?

A tumor is a lump or mass made of abnormal cells that grow when they should not grow. In children, these cells usually grow very fast and can spread to other parts of the body. Normal cellular apoptosis (programmed cell death) fails.

  • Benign tumor: Not cancer. It grows in one place, is usually encapsulated, and does not spread. Usually not life-threatening, though it can cause issues if it presses on vital organs (like the brain).
  • Malignant tumor: This is cancer. It can grow into nearby tissues and spread (metastasize) to distant parts of the body through blood or lymph fluid.

Why Are Children Different from Adults?

  • Children are still growing: Cancer treatment (especially radiation and steroids) severely affects their physical growth, bone development, and cognitive development.
  • Children's bodies handle medicines differently: They have a higher percentage of total body water and immature liver/kidney enzyme systems, altering how chemotherapy is metabolized and excreted.
  • Different types of cancer: Adults mostly get carcinomas (epithelial cancers from aging/lifestyle), while children get embryonal tumors, leukemias, and sarcomas (cancers of developing mesoderm/tissues).
  • Better chances of cure: Because pediatric cancers are fast-growing, they are actually more responsive to chemotherapy (which targets rapidly dividing cells). Children also tolerate higher relative doses of chemotherapy than adults.
  • Not caused by lifestyle: Children's cancers are usually not caused by lifestyle (smoking, alcohol, diet) but by genetic changes (mutations) that happen spontaneously during fetal or early childhood development.

Common Types in Uganda/East Africa

  • Burkitt lymphoma: Very common, highly aggressive B-cell lymphoma. Strongly linked to endemic malaria and the Epstein-Barr virus (EBV). Often presents as a massive jaw or abdominal tumor.
  • Leukemia: Specifically ALL (Acute Lymphoblastic Leukemia).
  • Retinoblastoma: Eye tumor. Often noticed late due to lack of screening; presents as a white pupil (leukocoria).
  • Wilms tumor (Nephroblastoma): Kidney tumor, usually presenting as an asymptomatic, smooth abdominal mass.
  • Kaposi sarcoma: Endothelial cancer, especially prevalent in HIV-positive children (HHV-8 virus).
  • Brain tumors: Medulloblastoma, astrocytomas.

Warning Signs (The 5-Sign Approach for Communities)

Teach parents and community health workers to look for these early indicators:

  • Swelling or lump that does not go away.
  • Sores that do not heal.
  • Sudden weight loss.
  • Severe or persistent headaches, especially with vomiting in the morning (Pathophysiology: Lying flat at night increases Intracranial Pressure (ICP) from a brain tumor, triggering the vomiting center upon waking).
  • Swelling of the abdomen (tummy) (Could indicate Wilms tumor or Burkitt lymphoma).
  • Sudden eye changes (white pupil, squint) (Classic for Retinoblastoma).
  • Severe fatigue and paleness (Anemia from Leukemia).
  • Severe bone pain (Marrow expansion from Leukemia cells).
  • Seizures that start suddenly.

🧠 Mnemonic: Early Warning Signs of Childhood Cancer

Remember CHILD CANCER:

  • Continued, unexplained weight loss
  • Headaches with vomiting in the morning
  • Increased swelling or persistent pain in bones/joints
  • Lump or mass in abdomen, neck, or elsewhere
  • Development of a whitish appearance in the pupil
  • Constant infections
  • A whitish color behind the pupil
  • Nausea that persists
  • Constant tiredness or noticeable paleness
  • Eye or vision changes occurring suddenly
  • Recurrent fevers of unknown origin

GENERAL PRINCIPLES OF PEDIATRIC CANCER NURSING

The Nurse's Role

As a pediatric oncology nurse, you wear many hats:

  • Caregiver: Giving highly toxic medicines, managing severe symptoms and side effects.
  • Educator: Teaching the family about the disease, treatment phases, and critical home care (infection prevention).
  • Advocate: Speaking for the child when they cannot speak (especially regarding pain management).
  • Counselor: Supporting the child and family emotionally through a terrifying diagnosis.
  • Coordinator: Connecting the family with social services, transport, and food support (abandonment of treatment is high in resource-limited settings due to financial strain).

Key Nursing Concepts

  • Aseptic Technique: Always use clean hands, clean gloves, and clean equipment. Cancer treatment destroys the child's immune system (neutropenia), so even small, normally harmless germs (commensal flora) can cause deadly systemic sepsis.
  • Vascular Access Devices: Chemotherapy requires reliable venous access.
    • Peripheral IV: Short-term access in hand or foot veins. Highly risky for vesicant chemotherapies (can cause tissue necrosis if they leak).
    • Central Line (CVAD): Long-term catheter placed in large chest veins (Superior Vena Cava). Used for chemotherapy, frequent blood draws, and TPN/fluids.
    • Port-a-cath: Small device surgically placed completely under the skin with a chamber that is accessed with a special non-coring (Huber) needle. Lowest infection risk.
    • Nursing Care for Central Lines:
      • Keep the dressing clean, dry, and intact.
      • Check for signs of infection (CLABSI): redness, warmth, pus, fever.
      • Flush with heparin or saline as per protocol to maintain patency and prevent clots.
      • Never use the line for anything except what it is prescribed for.
      • EMERGENCY: If the line comes out accidentally, apply immediate deep pressure to the vein and call the doctor immediately (risk of severe hemorrhage or air embolism).
  • Chemotherapy Safety (Protecting Yourself):
    • Wear specialized chemotherapy gloves when handling drugs or body fluids for 48 hours after treatment.
    • Chemotherapy drugs are toxic and mutagenic – they can harm healthy skin and absorb into your bloodstream.
    • Dispose of contaminated materials in special yellow/purple cytotoxic waste bins.
    • Pregnant nurses should absolutely not handle chemotherapy due to the risk of teratogenicity (fetal malformation).
  • Body Fluid Precautions (Protecting the Family):
    • For 48-72 hours after chemotherapy administration: The child's urine, vomit, stool, and saliva may contain toxic drug residue.
    • Family should wear gloves when cleaning these fluids.
    • Flush toilet twice after use with the lid down to prevent aerosolization.
    • Wash soiled clothes separately with hot water and soap.

LEUKEMIA (BLOOD CANCER)

What is Leukemia?

Leukemia is cancer of the blood and bone marrow. Bone marrow is the soft spongy tissue inside bones where all blood cells are made (hematopoiesis). In leukemia, a genetic mutation causes the bone marrow to make too many immature, non-functional white blood cells called blasts. These abnormal blast cells divide uncontrollably and crowd out the healthy blood cells, leading to bone marrow failure.

  • Acute Lymphoblastic Leukemia (ALL): The most common cancer in children (75-80% of childhood leukemias). Affects the lymphoid cell line (B-cells and T-cells).
  • Acute Myeloid Leukemia (AML): Affects the myeloid cell line (precursors to red blood cells, platelets, and granulocytes). It is more aggressive and harder to treat than ALL.

Why Does It Happen?

  • Genetic changes (mutations or translocations) in developing blood cells.
  • Some genetic conditions greatly increase risk (Children with Down syndrome have a 10-20x higher risk of developing leukemia).
  • Exposure to radiation or certain chemicals (benzene).
  • In Uganda, some association with Epstein-Barr virus (EBV) and malaria in certain types of hematological malignancies.

💡 Pathophysiology Check: The "Crowding Out" Effect

Understand that leukemia cells don't usually attack other cells directly. Instead, they act like weeds in a garden. They grow so fast that they consume all the nutrients and physical space inside the bone marrow. As a result, the "good plants" (normal Red Blood Cells, Platelets, and healthy White Blood Cells) cannot grow. This marrow failure is what causes 100% of the clinical symptoms!

Signs and Symptoms (Driven by Marrow Failure)

Because leukemia affects the bone marrow, symptoms are directly related to the lack of normal blood cells (Pancytopenia):

  1. Low Red Blood Cells (Anemia):
    • Pale skin, lips, tongue (always check palms and conjunctiva/nail beds in dark-skinned children).
    • Extreme tiredness, weakness, and lethargy.
    • Shortness of breath with little activity (tissue hypoxia).
    • Fast heartbeat (tachycardia) – the heart pumps faster to compensate for low oxygen carrying capacity.
    • Dizziness.
  2. Low Platelets (Thrombocytopenia):
    • Easy bruising (bruises appear without any history of trauma/injury).
    • Tiny, pinpoint red/purple spots on skin (petechiae) that do not blanch when pressed.
    • Bleeding from nose (epistaxis) or gums.
    • Blood in urine (hematuria) or stool (melena).
    • Heavy, prolonged bleeding from very small cuts.
  3. Low Functional White Blood Cells (Infection Risk / Neutropenia):
    • Even though the total WBC count might be massively high, these are useless "blast" cells. The child lacks mature neutrophils to fight bacteria.
    • Frequent infections (fever, persistent cough, severe mouth sores).
    • Infections that do not respond to normal, standard antibiotics.
    • Fever without an obvious focal cause.
  4. Other Signs (Due to Infiltration of Leukemia Cells):
    • Bone pain: Caused by the massive expansion of marrow pressing against the periosteum (child refuses to walk, limps, or cries of leg pain).
    • Joint pain and swelling.
    • Swollen lymph nodes (Lymphadenopathy): Especially in neck, armpits, groin.
    • Swollen belly (Hepatosplenomegaly): Enlarged liver and spleen as leukemia cells infiltrate these extramedullary organs.
    • Loss of appetite and Weight loss.
    • Night sweats.

Diagnosis of Leukemia

Confirming leukemia requires a systematic approach from basic blood tests to invasive marrow sampling.

  1. Full Blood Count (FBC/CBC): Shows low hemoglobin, low platelets, and usually an abnormal white blood cell count (can be very low, or massively high). Crucially, it may show blast cells (immature WBCs) in the peripheral blood, which should normally never leave the marrow.
  2. Peripheral Blood Film: Looking at blood cells under a microscope by a hematologist. Shows abnormal cell shapes, sizes, and the presence of blasts.
  3. Bone Marrow Aspiration and Biopsy (The Gold Standard):
    • Procedure: A specialized Jamshidi needle is forcefully inserted into the hip bone (posterior superior iliac spine) or breastbone (sternum) to extract liquid marrow and a small core piece of bone.
    • Nursing care before: Explain to child using age-appropriate language (e.g., "taking a picture of your bones"), apply EMLA cream (numbing cream) 1 hour before if available, give IV sedation if ordered, ensure informed consent form is signed by parents.
    • Nursing care during: Position child properly (side-lying/lateral decubitus or prone), hold and physically comfort the child, continuously monitor vital signs (respirations during sedation), assist the doctor with sterile field.
    • Nursing care after: Apply a firm pressure dressing, keep child lying flat for 30-60 minutes to prevent bleeding, check site frequently for oozing/bleeding, give pain medicine (paracetamol/ibuprofen), monitor for infection, allow parent to comfort child.
    • Results: If there are more than 25% blast cells in the marrow, acute leukemia is definitively diagnosed.
  4. Lumbar Puncture (Spinal Tap):
    • Checks if leukemia cells have crossed the blood-brain barrier and spread to the brain/spinal fluid (CNS involvement).
    • Procedure: Needle inserted between vertebrae (L3/L4 or L4/L5) in the lower back to collect cerebrospinal fluid (CSF).
    • Nursing care: Position child in a tight fetal position (knees to chest) or sitting bent forward to open vertebral spaces. Apply EMLA cream, give sedation, hold child completely still. After procedure, keep child strictly flat for 1-4 hours to prevent post-dural puncture headache. Monitor for signs of infection, check puncture site for CSF leakage.
  5. Chest X-ray: Checks for an enlarged thymus gland (mediastinal mass, common in T-cell ALL) which can compress the airway, or checks for lung infections.
  6. Ultrasound: Checks for the extent of liver, spleen, and kidney enlargement (leukemic infiltration).
  7. Flow Cytometry: Special computerized test to identify the exact type of leukemia by looking at proteins (CD markers) on the cell surface. Distinguishes ALL from AML, and B-cell from T-cell.
  8. Cytogenetics: Looks at chromosome changes (DNA mutations) inside the cancer cells to guide treatment intensity and predict prognosis.

Staging and Risk Classification

Leukemia is not "staged" like solid tumors (Stage 1, 2, 3, 4) because it is already everywhere in the blood. Instead, it is grouped by Risk:

  • Standard risk: Good features. Ages 1 to 10 years old, low white blood cell count at diagnosis (< 50,000).
  • High risk: Age under 1 or over 10 years, high white blood cell count (> 50,000), certain genetic changes, or slow response to the first few weeks of treatment.
  • Very high risk: Specific aggressive chromosome changes (like the Philadelphia chromosome t(9;22)), or infant leukemia (under 1 year old).

❓ Applied Clinical Question

A 4-year-old child comes to the clinic with severe leg pain, pale skin, and tiny red spots covering his abdomen. The mother says he has had a fever for two weeks that won't go away. The doctor suspects ALL and orders a bone marrow biopsy.

  1. What are the tiny red spots called, and why are they happening?
  2. What percentage of blasts in the bone marrow will confirm the diagnosis of Leukemia?

Answers:

  1. They are petechiae. They happen because the bone marrow is full of leukemia cells and cannot produce platelets (Thrombocytopenia), leading to micro-hemorrhages under the skin.
  2. Greater than 25% blasts in the marrow confirms leukemia.

Treatment and Management of Leukemia

OVERALL GOAL: Kill all leukemia cells, allow normal blood cells to return, and prevent the spread to "sanctuary sites" (the brain/CNS and the testicles, where normal IV chemotherapy cannot easily reach due to the blood-brain and blood-testis barriers).

PHASE 1: INDUCTION (First 4-6 Weeks)

Purpose: To rapidly kill the vast majority of leukemia cells in the blood and bone marrow and achieve remission (defined as having less than 5% blast cells in the marrow and the return of normal blood counts).

Medicines used (The Induction Regimen):

  • Vincristine: IV injection weekly. Mechanism: Stops cells from dividing by inhibiting microtubules. Side effects: Highly neurotoxic. Causes constipation (paralytic ileus), hair loss, and severe nerve pain/damage (burning/tingling, jaw pain, loss of deep tendon reflexes, foot drop). NEVER give intrathecally—it is fatal!
  • Prednisone or Dexamethasone: Oral steroids daily. Mechanism: Directly toxic to lymphoid cancer cells (lymphocytotoxic). Side effects: Extreme mood changes (crying, rage), massively increased appetite, weight gain (Cushingoid "moon face"), high blood sugar (steroid-induced diabetes), severe stomach irritation, muscle weakness, and profound susceptibility to infection.
  • L-asparaginase: IV or IM injection. Mechanism: Starves the cancer cells of the amino acid asparagine, which they need to survive. Side effects: Severe allergic reactions (anaphylaxis), blood clotting problems, severe pancreas inflammation (pancreatitis - watch for severe abdominal pain), and liver problems.
  • Daunorubicin or Doxorubicin (Anthracyclines): IV chemotherapy (the "red drugs"). Mechanism: Damages cancer DNA. Side effects: Severe heart damage (cardiotoxicity)—must be monitored with an echocardiogram before and during treatment. Also causes red urine (teach parents this is NOT blood – just the drug color flushing out), mouth sores, massive hair loss, and low blood counts. Highly vesicant (burns tissue if IV leaks).
  • Intrathecal (IT) chemotherapy: Chemotherapy injected directly into the spinal fluid during a lumbar puncture to prevent or treat brain involvement. Medicines used include methotrexate, cytarabine, and hydrocortisone.

🚨 ONCOLOGIC EMERGENCY: Tumor Lysis Syndrome (TLS)

  • Pathophysiology: During Induction, chemotherapy is highly effective. Millions of leukemia cells burst open (lyse) at the exact same time, releasing their intracellular contents straight into the bloodstream. The kidneys become completely overwhelmed and fail.
  • Signs (The 4 Chemical Changes): High potassium (Hyperkalemia), high phosphorus (Hyperphosphatemia), low calcium (Hypocalcemia - because it binds to the high phosphorus), and high uric acid (Hyperuricemia).
  • Child may exhibit: Irregular heartbeat/cardiac arrest (from potassium), severe muscle cramps/tetany/seizures (from low calcium), and decreased/cloudy urine (uric acid crystals blocking the kidneys).
  • Prevention & Management: Give massive amounts of IV fluids (hyperhydration) before and during chemo to flush kidneys. Give Allopurinol or Rasburicase to destroy/lower uric acid. Monitor electrolytes 2-3 times daily. Monitor urine output hourly. If suspected, notify doctor immediately, increase IV fluids, and prepare for emergency dialysis if kidneys shut down.

Nursing Management During Induction:

  • Monitor blood counts daily: Transfuse packed red cells (PRBCs) if hemoglobin < 7 g/dL (or < 8 if symptomatic). Transfuse platelets if < 10,000 or if actively bleeding.
  • Infection prevention: Strict hand hygiene! Protect from visitors with colds. Monitor temperature every 4 hours. Start broad-spectrum antibiotics IMMEDIATELY if fever > 38°C (neutropenic fever protocol).
  • Nutrition support: Small frequent meals, high-protein foods (eggs, beans, groundnuts, milk if tolerated). Give oral supplements. Crucially, administer anti-nausea medicines (antiemetics like ondansetron, metoclopramide) before meals and before chemo.
  • Emotional support: Child may feel scared, parents may be in shock. Provide honest but hopeful information. Allow parents to stay with child constantly.
  • Medication administration: Double-check all chemotherapy doses (pediatric doses are strictly calculated by Body Surface Area - BSA, not just weight). Verify with a second RN. Ensure the IV line is patent and has a brisk blood return before pushing drugs to prevent vesicant tissue necrosis.

PHASE 2: CONSOLIDATION/INTENSIFICATION (Several Weeks)

Purpose: To kill any microscopic, stubborn leukemia cells that survived the induction phase. It uses different drugs to prevent the cancer from mutating and developing resistance.

Additional medicines:

  • Cyclophosphamide: IV. Side effects: Profound low blood counts, severe nausea, and bladder irritation (Hemorrhagic Cystitis). Nursing intervention: Give plenty of IV fluids and administer the rescue drug Mesna to bind the toxic metabolites and protect the bladder lining.
  • Cytarabine (Ara-C): IV or subcutaneous. Side effects: Fever, mouth sores, eye irritation (chemical conjunctivitis - may need steroid eye drops), and severe neurotoxicity (cerebellar toxicity causing unsteady gait).
  • 6-Mercaptopurine (6-MP): Oral daily. Side effects: Low blood counts, severe liver damage (hepatotoxicity).
  • Methotrexate: High-dose IV. Mechanism: Blocks folic acid, preventing DNA synthesis. Side effects: Massive mouth sores, kidney damage, liver damage. Nursing intervention: Must give Leucovorin rescue exactly on time to save the patient's normal cells from fatal toxicity, and hydrate aggressively with IV sodium bicarbonate to alkalinize the urine and protect the kidneys.

Nursing Care for Consolidation:

  • Monitor for mucositis (mouth sores): Inspect mouth every shift. Use an ultra-soft toothbrush, saline or bicarbonate mouth rinses (NO alcohol-based mouthwashes!). Give topical anesthetic gels before meals. Avoid spicy/acidic/rough foods.
  • Monitor liver function: Check for yellow eyes/skin (jaundice), dark urine, and right upper quadrant abdominal pain.
  • Ensure aggressive hydration to protect kidneys from methotrexate and cyclophosphamide.
  • Monitor for neurotoxicity from high-dose cytarabine: check for confusion, difficulty walking (ataxia), or seizures.

PHASE 3: CENTRAL NERVOUS SYSTEM (CNS) PROPHYLAXIS/TREATMENT

Purpose: To prevent or treat leukemia hiding in the brain and spinal cord behind the blood-brain barrier.

Methods:

  • Intrathecal chemotherapy via Lumbar Puncture (as described above).
  • Cranial radiation: Only used for high-risk cases or if CNS is already involved. It is rarely used in very young children (under age 3) because it causes permanent, severe brain damage and cognitive stunting.

Nursing Care for Radiation:

  • Mark radiation fields with ink (instruct parents DO NOT wash off the marks).
  • Protect unaffected areas of the body with lead shields.
  • Apply gentle moisturizer to irradiated skin (aloe vera, aqueous cream) – avoid perfumes, powders, or harsh soaps.
  • Monitor for skin redness (erythema), peeling, and blistering.
  • Monitor for extreme fatigue (somnolence syndrome), headache, and nausea.
  • Reassure the child during treatments (they must be alone in the radiation room but can hear you talk through the intercom).

PHASE 4: MAINTENANCE (1.5-2 Years for girls, 2-3 Years for boys)

Purpose: To keep the leukemia from coming back (relapse). Cancer cells can go dormant; this long, low-dose phase kills them when they wake up.

Medicines (The "Backbone" Regimen):

  • 6-Mercaptopurine (6-MP): Oral every evening. Give on an empty stomach (especially without milk/dairy) for better absorption.
  • Methotrexate: Oral or IM weekly.
  • Vincristine: IV monthly.
  • Prednisone/Dexamethasone: Oral for 5 days every 4 weeks (pulse therapy).

Nursing Care for Maintenance:

  • Adherence is life or death: Teach parents to give medicines at home EXACTLY as prescribed. Emphasize: Do not skip doses, do not give extra doses, give at the same time daily.
  • Monitor blood counts every 2-4 weeks in the clinic. If neutrophils drop too low, the doctor may temporarily reduce the dose.
  • Continue infection precautions.
  • Monitor growth and development (long-term steroids can stunt height and weaken bones).
  • Support school attendance when blood counts are safe! The child is not contagious and desperately needs social normalcy.

Treatment for Relapse & BMT

If leukemia returns (relapses), the cells have mutated and become resistant to the standard drugs.

  • Action: Requires much more intensive chemotherapy.
  • Bone Marrow Transplant (BMT) / Hematopoietic Stem Cell Transplant (HSCT):
    • Process: The child receives ultra-high-dose chemotherapy (and sometimes total body radiation) to deliberately destroy 100% of their bone marrow (myeloablation). Then, an infusion of healthy stem cells is given via IV to rescue them.
    • Types: Allogeneic (cells from a donor/sibling) or Autologous (the child's own cells collected when they were in remission).
    • Nursing care: Strict reverse isolation (positive pressure room). Monitor for Graft-Versus-Host Disease (GVHD) – a deadly complication where the donor's immune cells wake up, realize they are in a foreign body, and attack the child's skin, gut, and liver. Severe infection risk requires a very long hospitalization.

Major Complications and Their Nursing Management

  1. Neutropenia (Low Neutrophils < 500/μL):
    • Risk: Overwhelming, rapid, life-threatening bacterial and fungal infections (Sepsis).
    • Signs: Fever > 38°C (100.4°F) is an absolute MEDICAL EMERGENCY in a neutropenic child.
    • Management: Draw blood cultures immediately. Start broad-spectrum IV antibiotics within 1 hour (e.g., ceftazidime, piperacillin-tazobactam, meropenem). Add vancomycin if a central line infection is suspected. Add antifungals (amphotericin or voriconazole) if fungal infection is suspected. Monitor closely in the hospital.
    • Nursing care: No fresh flowers, dirt, or plants in the room (they carry Aspergillus mold). Cooked food only (no raw fruits/vegetables or unpasteurized dairy if severely neutropenic). Strict hand hygiene. Daily mouth and perineal care. Absolutely NO rectal temperatures, enemas, or suppositories (the rectal mucosa is fragile, and tearing it introduces gut bacteria directly into the blood, causing fatal sepsis).
  2. Thrombocytopenia (Low Platelets < 20,000/μL):
    • Risk: Spontaneous, fatal bleeding, especially in the brain (intracranial hemorrhage) or gut.
    • Signs: New bruises, petechiae, bleeding gums, blood in urine/stool, severe headache or changes in consciousness (brain bleed).
    • Management: Administer Platelet transfusions. Avoid IM injections (they will cause massive hematomas). Avoid aspirin and ibuprofen (which inhibit platelet function). Use an ultra-soft toothbrush. No contact sports. Apply firm pressure for a full 10 minutes after any needle stick.
    • Nursing care: Pad the side rails of the crib/bed. Avoid constipation (give stool softeners, as straining can burst vessels and cause bleeding). Monitor all stool, urine, and emesis for blood. Check skin daily for new bruises.
  3. Anemia (Low Hemoglobin):
    • Signs: Severe pallor, fast heartbeat (tachycardia), shortness of breath, chest pain, extreme fatigue.
    • Management: Transfuse packed red blood cells (PRBCs) if symptomatic or if Hb < 7 g/dL.
    • Nursing care: Pre-medicate with an antihistamine and paracetamol to prevent allergic/febrile transfusion reactions. Monitor vital signs every 15 minutes for the first hour of transfusion. Watch strictly for fever, rash, back pain, dark urine, or wheezing (signs of a hemolytic transfusion reaction). Give the blood slowly in children with heart problems to avoid fluid overload.
  4. Tumor Lysis Syndrome (TLS):
    • Already described above – remember the classic electrolyte triad: High K+, High Phos, High Uric Acid, Low Ca+. A medical emergency requiring hydration and allopurinol!
  5. Disseminated Intravascular Coagulation (DIC):
    • Especially common in a specific type of AML (the M3 subtype / APML).
    • Pathophysiology: The leukemia cells release tissue factor, causing microscopic blood clots all over the body. This uses up all the body's clotting factors, leading to massive, paradoxical bleeding.
    • Signs: Bleeding from multiple sites simultaneously, oozing from old IV sites, petechiae, very low blood pressure.
    • Management: Replace clotting factors with Cryoprecipitate, Fresh Frozen Plasma (FFP), and platelets. Treat the underlying leukemia immediately.
  6. Hyperleukocytosis:
    • Very high white blood cell count (> 100,000/μL).
    • Pathophysiology: The blood becomes physically thick (viscous) like sludge and gets stuck in the microscopic capillaries (Leukostasis).
    • Signs: Confusion/coma (brain vessels blocked), difficulty breathing (lung vessels blocked), priapism (painful prolonged erection due to blocked penile veins), stroke symptoms.
    • Management: Massive aggressive IV hydration. Careful exchange transfusion or leukapheresis (filtering WBCs out of blood) in specialized centers. Crucial Nursing Note: Avoid transfusing red blood cells initially until the WBC count is lowered, because adding red cells makes the blood thickness (viscosity) even worse and can trigger a stroke!

Prognosis

  • ALL: 80-90% cure rate in developed countries. 50-60% cure rate in resource-limited settings (due to late presentation, malnutrition, infection, or abandonment of treatment).
  • AML: 60-70% cure rate with intensive treatment (much harsher chemo required).
  • Prognosis is generally worse if: Infant age (under 1), extremely high white count at diagnosis, certain bad genetic mutations (Philadelphia chromosome), slow response to the first 4 weeks of treatment, or if the leukemia relapses.

❓ Applied Clinical Question: Prioritization

Case: You are the pediatric oncology nurse. You have four patients. Which child must you assess and intervene with FIRST?

  1. A child on Consolidation chemotherapy complaining of a sore mouth.
  2. A child in Maintenance phase with a platelet count of 35,000 and two new bruises on his leg.
  3. A child admitted for Induction therapy who has an Absolute Neutrophil Count (ANC) of 200 and just spiked a temperature of 38.2°C.
  4. A child receiving IV Vincristine complaining of tingling in their fingers.

Answer: You must see Patient 3 FIRST. A fever in a neutropenic patient is an absolute life-threatening emergency. They can progress to septic shock and die within hours. You have less than 60 minutes to draw blood cultures and hang broad-spectrum IV antibiotics.

Quick Quiz

Leukemia Quiz

Paediatrics

Privacy: Your details are used only for quiz tracking and certificates.

Intro to Childhood Tumors and Leukemia Read More »

Want notes in PDF? Join our classes!!

Send us a message on WhatsApp
0726113908

Scroll to Top
Enable Notifications OK No thanks