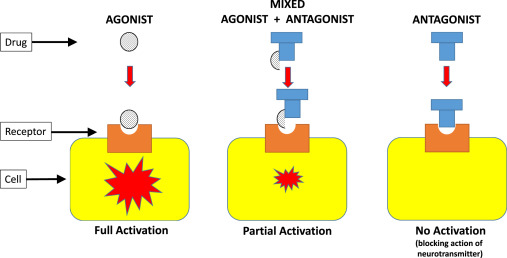
Estrogen Receptor Modulators are agents that either stimulate or block specific estrogen receptor sites.
They are used to stimulate specific estrogen receptors to achieve therapeutic effects of increased bone mass without stimulating the endometrium and causing other less desirable effects i.e. these drugs stimulate the estrogen receptors in the body so as to produce estrogen as needed by the body.
Examples of Estrogen Receptor Modulators.
Two available estrogen receptor modulators are raloxifene (Evista) and toremifene (Fareston).
Raloxifene
Dose : 60 mg/day Orally.
Indications :–Used therapeutically to stimulate specific estrogen receptor sites, which results in an increase in bone mineral density without stimulating the endometrium in women; – reduces risk of invasive breast cancer in postmenopausal women with osteoporosis who are at high risk for invasive breast cancer
Toremifene
Dose : 60 mg/day orally until disease progression occurs.
Indications: Used as an antineoplastic agent because of its effects on estrogen receptor sites for treatment of advanced breast cancer in postmenopausal women with estrogen receptor–positive and estrogen receptor–unknown tumors
Contraindications of Estrogen Receptor Modulators
Allergy to estrogen receptor modulators.
Contraindicated in pregnancy and lactation because of potential effects on the fetus or neonate.
History of venous thrombosis or smoking. Increased risk of blood clot formation if smoking and estrogen are combined.
Adverse Effects of Estrogen Receptor Modulators
Raloxifene has been associated with GI upset, nausea, and vomiting.
Changes in fluid balance may cause headache, dizziness, visual changes, and mental changes.
Specific estrogen receptor stimulation may cause hot flashes, skin rash, edema, and vaginal bleeding.
Warfarin: decreased prothrombin time if taken with raloxifene
Nursing Considerations
Assess for the mentioned cautions and contraindications (e.g. drug allergies, cardiovascular diseases, metabolic bone disease, history of thromboembolism, etc.) to prevent any complications.
Perform a thorough physical assessment (e.g. bowel sounds, skin assessment, vital signs, mental status, etc.) to establish baseline data before drug therapy begins, to determine effectiveness of therapy, and to evaluate for occurrence of any adverse effects associated with drug therapy.
Assist with pelvic and breast examinations. Ensure specimen collection for Pap smear and obtain a history of patient’s menstrual cycle to provide baseline data and to monitor for any adverse effects that could occur.
Arrange for ophthalmic examination especially for patients who are wearing contact lenses because hormonal changes can alter the fluid in the eye and curvature of the cornea, which can change the fit of contact lenses and alter visual acuity.
Monitor laboratory test results (e.g. urinalysis, renal and hepatic function tests, etc.) to determine possible need for a reduction in dose and evaluate for toxicity.
Advertisements
Nursing Diagnoses
Ineffective tissue perfusion related to changes in the blood vessels brought about by drug therapy and risk of thromboemboli
Excess fluid volume related to fluid retention
Acute pain related to systemic side effects of gastrointestinal (GI) pain and headache
Implementation withRationale These are vital nursing interventions done in patients who are taking female sex hormones and estrogen receptor modulators:
Administer drug with food to prevent GI upset.
Provide analgesic for relief of headache as appropriate.
Provide small, frequent meals to assist with nausea and vomiting.
Monitor for swelling and changes in vision or fit of contact lenses to monitor for fluid retention and fluid changes.
Provide comfort measures to help patient tolerate drug effects.
Provide safety measures (e.g. adequate lighting, raised side rails, etc.) to prevent injuries.
Educate client on drug therapy to promote understanding and compliance.
Evaluation
Here are aspects of care that should be evaluated to determine effectiveness of drug therapy:
Monitor patient response to therapy (palliation of signs and symptoms of menopause, prevention of pregnancy, decreased risk factors for coronary artery disease, and palliation of certain cancers).
Monitor for adverse effects (e.g. GI upset, edema, changes in secondary sex characteristics, headaches, thromboembolic episodes, and breakthrough bleeding).
Evaluate patient understanding on drug therapy by asking patient to name the drug, its indication, and adverse effects to watch for.
Subfertility, Ovulation Induction, and Fertility Drugs
GONADOTROPINS
Gonadotropins are fertility medications given by injection that contain follicle-stimulating hormone (FSH) alone or combined with luteinizing hormone (LH).
Gonadotropins are hormones that stimulate the gonads, which are the sex organs in the body.
Gonadotropins are produced by the pituitary gland, which is a small gland located at the base of the brain. The release of gonadotropins is regulated by the hypothalamus.
In females, the gonads are the ovaries, and in males, they are the testes.
Gonadotropins are a class of medications used to treat infertility and disorders associated with reproductive functions.
Types of Gonadotropins
There are two main types of gonadotropins:
1. Follicle-stimulating hormone (FSH): This hormone stimulates the growth and development of follicles in the ovaries of females and sperm production in the testes of males.
Females
Males
- Normal Ovarian Function: FSH is useful for the development and maturation of follicles in the ovaries, which contain the eggs. This ensures regular ovulation and fertility.
- Estrogen Production: FSH stimulates the production of estrogen by the growing follicles. Estrogen is for the development of female secondary sexual characteristics, menstrual cycle regulation, and overall reproductive health.
- Improved Egg Quality: FSH contributes to the development of healthy eggs, increasing the chances of successful fertilization and pregnancy.
- Fertility Treatment: FSH is a key component of fertility treatments like in vitro fertilization (IVF) to stimulate multiple egg production.
- Sperm Production: FSH is essential for the production of sperm in the testes. It stimulates the Sertoli cells, which are responsible for nourishing and supporting sperm development.
- Improved Sperm Quality: FSH contributes to the production of healthy, motile sperm, increasing the chances of fertilization.
2. Luteinizing hormone (LH): This hormone triggers ovulation in females and testosterone production in males.
Females
Males
- Ovulation: LH triggers the release of the mature egg from the follicle (ovulation), which is essential for fertilization.
- Corpus Luteum Formation: After ovulation, LH stimulates the formation of the corpus luteum, which produces progesterone. Progesterone is for maintaining the uterine lining for potential pregnancy.
- Hormonal Balance: LH plays a role in regulating the production of estrogen and progesterone, contributing to hormonal balance in the female body.
- Fertility Treatment: LH is used in fertility treatments to trigger ovulation and support the development of the corpus luteum.
- Testosterone Production: LH stimulates the Leydig cells in the testes to produce testosterone. Testosterone is essential for male sexual development, sperm production, and overall health.
- Secondary Sexual Characteristics: LH-driven testosterone production is responsible for the development of male secondary sexual characteristics like facial hair, muscle mass, and deepening of the voice.
- Libido and Sexual Function: Testosterone, produced under the influence of LH, plays a crucial role in libido and sexual function.
GONADOTROPIN DRUGS (Fertility Drugs)
Gonadotropin Drugs/Fertility drugs are agents that stimulate the female reproductive system.
Fertility drugs are medications used to help women who are having trouble getting pregnant. They work by stimulating the ovaries to produce more eggs, increasing the chances of conception.
Indications for Fertility Drugs:
1. Treatment of infertility in women with functioning ovaries whose partners are fertile: This is a broad category encompassing various causes of infertility, including:
Anovulation: When a woman doesn't ovulate regularly, fertility drugs can stimulate ovulation and increase the chances of pregnancy.
Polycystic Ovarian Syndrome (PCOS): PCOS often causes irregular ovulation. Fertility drugs can help regulate ovulation and improve fertility.
Endometriosis: This condition can affect ovulation and egg quality. Fertility drugs can help stimulate ovulation and improve chances of conception.
Premature Ovarian Failure: In some cases, women experience premature ovarian failure, leading to low egg reserves. Fertility drugs can help stimulate limited egg production.
Unexplained Infertility: When the cause of infertility is unknown, fertility drugs can be used to stimulate ovulation and see if it improves chances of pregnancy.
2. Used to stimulate multiple follicle development for harvesting of ova for in vitro fertilization (IVF): This is a crucial aspect of IVF, where multiple eggs are needed for fertilization and embryo transfer.
3. Menotropins are used to stimulate spermatogenesis in men with low sperm counts and otherwise normally functioning testes: While not directly related to female fertility, this highlights the broader application of fertility drugs in both men and women.
Contraindications for Fertility Drugs:
Allergy to fertility drug: Prevent hypersensitivity reactions.
Primary ovarian failure: These drugs only work to stimulate functioning ovaries.
Ovarian cysts: Can be stimulated by the drugs and can become larger.
Pregnancy: Due to the potential for serious fetal effects.
Idiopathic uterine bleeding: Can represent an underlying problem that could be exacerbated by the stimulatory effects of these drugs.
Lactation: Risk of adverse effects on the baby.
Thromboembolic disease: Increased risk of thrombus formation.
Women with respiratory diseases: Alterations in fluid volume and blood flow can overtax the respiratory system.
Adverse Effects:
Greatly increased risk of multiple births and birth defects.
Others: headache, fluid retention, nausea, bloating, uterine bleeding, ovarian enlargement, gynecomastia, and febrile reactions possibly due to stimulation of progesterone release.
Fluid retention is a common side effect of fertility medications, because;
Hormonal Changes: Fertility drugs increase estrogen levels, which can lead to fluid retention. Estrogen promotes sodium retention in the body, and sodium attracts water, causing fluid buildup.
Increased Blood Flow: Fertility drugs increase blood flow to the ovaries and uterus, which can lead to fluid buildup in the pelvic area.
Drugs used in treatment of infertility
Name
Clinical uses and dosage
Contraindications
Clomifene
Available in tablet form of 50mg
Brand name Clomid
Infertility due to failure to ovulate.
Given 50 mg daily × 5/7
Starting from the 5th day of the cycle ,
Increase to 100mg ×5/7
From day 5-10 if no response.
Pregnancy.
Bromocriptine
Available in tablet form of 2.5mg
Female infertility associated with hyperprolactinemia
Dosage 1.25 - 2.5mg
Bid × 3-7 days with food.
Inhibition of lactation 2.5mg bid with meals × 14 days.
Severe ischemic heart disease
Uncontrolled hypertension
Pregnancy
Breast feeding.
I. Major Causes of Subfertility in Couples
Subfertility (or infertility) is generally defined as the inability to conceive after 12 months of regular, unprotected intercourse. A clinical approach to subfertility requires an understanding of its major causes:
Unexplained: 28%
Male factors: 24%
Ovarian dysfunction (Anovulation): 21%
Tubal factors: 14%
Other causes: 13%
Reference: Jose-Miller AB, et al. Am Fam Physician 2007;75:849-56, 857-8.
II. Pre-Conception Counseling
Preconception care is a broad term that refers to the process of identifying social, behavioral, environmental, and biomedical risks to a woman's fertility and pregnancy outcome, and then reducing these risks through education, counseling, and appropriate intervention.
Key Advice and Interventions Given During Pre-Conception:
BMI (Body Mass Index): Counseling on weight optimization (weight loss for obese patients is a primary strategy to restore ovulatory cycles).
BP (Blood Pressure): Monitoring and optimization of cardiovascular health.
Lifestyle Counseling: Smoking cessation, reducing alcohol intake, managing stress, and maintaining a healthy diet.
Garbh Sanskar / Spiritual: Mental and spiritual preparation for pregnancy to reduce maternal stress.
Folic Acid Supplementation: To prevent neural tube defects.
Anemia Correction: Screening and treating iron-deficiency or other forms of anemia.
Sugar / Thyroid: Strict glycemic control for diabetics and optimization of TSH levels.
Correction of Endocrine Factors: Addressing underlying hormonal imbalances (e.g., hyperprolactinemia).
FOGSI recommends vaccination counseling as a part of pre-pregnancy counseling (for unvaccinated women).
History of occurrence of vaccine-preventable diseases, previous vaccinations administered, and allergic reactions to vaccinations must be recorded.
Rubella, Hepatitis B, and Varicella vaccination should be given, preferably during the postmenstrual period.
Pregnancy should be deferred for 3 months in the case of the Rubella vaccine.
III. Clinical Approach to Ovulation Induction
Ovulation induction is the method for treating anovulatory infertility. The clinical approach requires an understanding of the causes of anovulation. Goals of ovulation induction include inducing mono-follicular rather than multi-follicular development, leading to mono-ovulation, a singleton pregnancy, and the birth of a healthy newborn.
A. WHO Categories of Ovulation Disorders
Historically, The World Health Organization (WHO) categorized ovulation disorders into three groups. Patients eligible for ovulation induction belong either to WHO group I or to WHO group II.
B. Modern Classification: The Four Most Common Ovulatory Disorders
Most experts have moved away from the strict WHO terminology. The modern approach focuses on the specific pathology:
Polycystic Ovary Syndrome (PCOS)
Corresponds to WHO Class 2. This is the most common cause of anovulation.
Almost all women in this category have PCOS when using the Rotterdam criteria for diagnosis.
Treatment Approach:
First-line: Letrozole (superior to clomiphene, especially in restoring ovulation and improving live-birth rates regardless of BMI) or Clomiphene citrate. Weight loss and lifestyle changes (Grade 2B recommendation).
Second-line: Gonadotropin injections (FSH) or Laparoscopic Ovarian Diathermy (ovarian drilling) using electrocautery or laser.
Third-line: In Vitro Fertilization (IVF).
Hypogonadotropic Hypogonadism (HA)
Corresponds to WHO Class 1.
Hypothalamic causes include functional hypothalamic amenorrhea (FHA) and isolated gonadotropin-releasing hormone (GnRH) deficiency.
Multiple factors contribute to FHA: eating disorders (anorexia nervosa), excessive exercise, and stress.
Rarely, it presents as primary amenorrhea due to complete congenital GnRH deficiency (Idiopathic hypogonadotropic hypogonadism, or Kallmann syndrome if associated with anosmia).
Infiltrative diseases and tumors of the hypothalamus/pituitary can also cause it due to diminished GnRH or gonadotropin release.
Primary Ovarian Insufficiency (POI)
Corresponds to WHO Class 3. Formerly referred to as premature ovarian failure (POF).
Defined as menopause before age 40 years. Occurs in only 1% of all women but accounts for 5-10% of cases of anovulation.
In most cases, the follicle pool is exhausted due to accelerated follicle loss of unknown origin.
The only effective fertility option is IVF with donor oocytes. No ovulation induction strategy has been shown to be effective.
Women with POI have other health issues related to estrogen deficiency, including an increased risk of osteoporosis and cardiovascular disease if estrogen is not replaced.
Hyperprolactinemia
Did not have a separate WHO category. Accounts for 5 to 10% of women with anovulation.
Hyperprolactinemia inhibits gonadotropin secretion, presumably by inhibiting GnRH.
Most patients have oligomenorrhea or amenorrhea. Serum gonadotropin concentrations are usually normal or decreased.
Treatment: Ovulation induction with dopamine agonists (Bromocriptine or Cabergoline) (Grade 2C).
IV. Gonadotropins and Ovarian Stimulation
Gonadotropins are a class of fertility medications given by injection that contain follicle-stimulating hormone (FSH) alone or combined with luteinizing hormone (LH). They stimulate the gonads (ovaries in females, testes in males) and are regulated by the hypothalamus via GnRH.
A. Mechanism of Action in Females and Males
Hormone
Role in Females (Ovaries)
Role in Males (Testes)
Follicle-Stimulating Hormone (FSH)
- Stimulates growth, development, and maturation of ovarian follicles.
- Stimulates estrogen production by the growing follicles.
- Improves egg quality and is a key component of IVF.
- Essential for spermatogenesis.
- Stimulates Sertoli cells to nourish and support sperm development.
- Improves sperm quality and motility.
Luteinizing Hormone (LH)
- Triggers the release of the mature egg (ovulation).
- Stimulates the formation of the corpus luteum, which produces progesterone to maintain the uterine lining.
- Regulates estrogen/progesterone balance.
- Stimulates Leydig cells to produce testosterone.
- Drives male secondary sexual characteristics.
- Crucial for libido, sexual function, and sperm maturation.
B. Types of Gonadotropin Preparations
Since their introduction in 1961, various formulations have been used. Evidence indicates no significant difference in effectiveness (clinical pregnancy or live-birth rates) or OHSS rates between different preparations (Cochrane Database 2015).
hMG (Human Menopausal Gonadotropins): Extracted from the urine of postmenopausal women. The ratio of LH to FSH bioactivity is 1:1 (e.g., Pergonal, Humegon).
Highly Purified hMG (HP-hMG)
Urinary FSH (uFSH): Refinement of the crude preparation to isolate FSH. Purified uFSH has some LH activity.
Recombinant human FSH (rhFSH): Available since 1996, >99% purity. Does not contain LH activity. Appealing due to ease of subcutaneous administration and batch-to-batch consistency. *Note: Long-acting rhFSH is registered for IVF but not advised for basic ovulation induction.*
Clinical Note: Women with hypogonadotropic hypogonadism who have very low serum LH (<0.5 IU/L) need exogenous hCG or recombinant LH alongside rhFSH to maintain adequate estradiol biosynthesis and follicle development.
C. Candidates for Gonadotropin Therapy
Women with PCOS who have not ovulated or conceived with weight loss, clomiphene, or letrozole therapy (second-line).
Hypogonadotropic anovulatory women with hypopituitarism or hypothalamic amenorrhea (HA) who do not have access to pulsatile GnRH therapy.
Used to stimulate multiple follicle development for harvesting ova in IVF.
Used to stimulate spermatogenesis in men with low sperm counts and normal functioning testes.
D. Ovarian Stimulation Protocols (Non-IVF Cycles)
Because ovarian sensitivity to FSH varies, specific protocols are needed to achieve the formation of a single dominant follicle and avoid multiple pregnancies/OHSS. The starting dose depends on Age, Antral Follicle Count, AMH, and previous response.
1. Conventional Gonadotropin Protocol
Starting dose of FSH is 150 IU/day. However, this regimen is associated with an unacceptably high multiple pregnancy rate (up to 36%) and Ovarian Hyperstimulation Syndrome (OHSS) (up to 14%). It has largely been abandoned for PCOS patients.
2. Low-Dose, Step-Up Protocol (First Choice for PCOS)
Designed to allow the FSH threshold to be reached gradually, minimizing excessive stimulation.
Initial SC or IM dose of FSH is 37.5 to 75 IU/day.
The dose is increased only if, after 14 days, no response is documented on ultrasonography and serum estradiol monitoring.
Increments of 37.5 IU are given at weekly intervals up to a maximum of 225 IU/day.
Detection of an ovarian response is an indication to continue the current dose until hCG can be given to stimulate ovulation.
3. Low-Dose, Step-Down Protocol
Mimics normal physiological cycles more closely.
Therapy with 150 IU FSH/day is started shortly after spontaneous or progesterone-induced bleeding.
Continued until a dominant follicle (>10 mm) is seen on TVS.
The dose is then decreased to 112.5 IU/day, followed by a further decrease to 75 IU/day three days later.
Continued until hCG is administered. (Robustness in everyday practice remains evaluated; step-up is preferred first).
Advantages of CC + Gonadotropins: Higher pregnancy rate than CC alone, more cost-effective, lesser multiple pregnancy rate than gonadotropins alone, lower incidence of OHSS compared to conventional regimes. Disadvantages: Anti-estrogenic effect of CC on the endometrium. Letrozole + Gonadotropins: Used to reduce the requirement of gonadotropins and side effects. However, some studies found slightly lower pregnancy rates compared to FSH alone.
E. Monitoring Ovarian Stimulation
Transvaginal Ultrasound (TVS): The primary tool to monitor follicular diameter (number & size) and the pattern/thickness of the endometrium. Baseline D2 scan is performed. Scans in the late follicular phase are done every 2-3 days.
Serum Estradiol: Measurements are useful; preovulatory concentrations above normal ranges may predict OHSS.
Serum Progesterone: Sometimes useful before hCG to determine if a premature LH surge has occurred (routine measurement not suggested).
Dose Adjustments (IUI Cycle):
Lead follicle >10mm, 2-3 follicles: Keep same dose.
4-6 follicles: Keep same dose or taper.
>6 follicles: Taper and look for OHSS.
Lead follicle <10mm: Increase the dose.
F. The Ovulatory Trigger (hCG)
hCG acts as a surrogate for the natural LH surge to induce final oocyte maturation and ovulation.
When to give: Administered on the day at least one follicle appears mature.
HCG at 18-20 mm (CC + Gonadotropin cycles).
HCG at 20-22 mm (CC alone cycles).
Dose: 5000 - 10,000 IU of urinary hCG, OR 250 mcg of recombinant hCG (Ovidrel).
Withholding Trigger: Strict attention to follicle number is essential. To minimize the risk of multiple gestation and OHSS, if three or more follicles >15 mm are present, or serum estradiol is extremely high, stimulation should be stopped, hCG withheld, and barrier contraception advised.
G. GnRH Analogs in Ovulation Induction
GnRH Agonists: Used to avoid interference from endogenous gonadotropin secretion. However, use of GnRH analogues in standard IUI cycles is not recommended as they do not significantly improve pregnancy rates.
GnRH Antagonists (Cetrorelix, Ganirelix): Indicated for conversion of IUI to IVF cycles (flexibility) and programming to avoid weekends. However, Cochrane reviews concluded antagonists were not helpful in improving pregnancy rates for basic IUI. Protocols:
Lubeck Protocol: Antagonist started when follicle reaches 14mm, or from day 6 of stimulation (0.25mg/day until hCG injection).
French Protocol: Single 3mg dose of antagonist given when E2 is 150-200 pg/ml and follicle is 14mm.
V. Complications and Outcomes of Gonadotropin Therapy
1. Multiple Gestation
The risk of multiple gestation is increased with clomiphene, but to a much greater extent with gonadotropin therapy. Adherence to low-dose protocols and strict trigger-withholding criteria is required.
2. Ovarian Hyperstimulation Syndrome (OHSS)
OHSS is a potentially life-threatening complication of ovulation induction caused by excessive ovarian stimulation. It leads to massive fluid shifts from the intravascular space to the third space due to increased vascular permeability.
Severe: Ascites, pleural effusion, severe hemoconcentration, oliguria, thromboembolism. Requires In-patient care or ICU admission.
3. Cancer Risks (Ovarian, Breast, and Others)
Ovarian Cancer: Early studies suggested an association with borderline ovarian tumors. However, best evidence (systematic review of 11 case-control and 14 cohort studies of 182,972 women) shows no convincing evidence of an excess risk of invasive ovarian tumors with fertility drug therapy. Infertility itself is an independent risk factor. Note: Due to one study suggesting increased risk, women should generally not receive more than 12 cycles of clomiphene citrate.
Breast Cancer: There does not appear to be an increased risk of breast cancer in women treated with fertility drugs. In a prospective cohort, women who used fertility drugs and conceived had the same risk as non-users.
Other Cancers: No association found with melanoma, thyroid, cervical, or colon cancers.
4. Risks in Offspring
A large population-based study found that childhood tumor risk was not increased. Congenital malformation risk does not appear to be increased with oral ovulation induction agents, though ongoing monitoring is warranted.
5. Pregnancy Outcomes
Gonadotropin therapy following CC failure is the classical approach. Cumulative singleton live-birth rates of 71% over 24 months have been reported, confirming it as an effective means before proceeding to IVF. Success rates are negatively influenced by age, obesity, and insulin resistance.
VI. Luteal Phase Support
Luteal phase support is utilized to ensure the endometrium is receptive for implantation.
Required: Definitely required when using Gonadotropins AND GnRH analogs (Agonist or Antagonist). Supported by meta-analysis showing distinct clinical benefit.
Empirical: Often given empirically in most Letrozole and CC cycles, although meta-analyses show no significant benefit for CC alone (benefit is seen in CC + Gonadotropin cycles).
Progesterone and Dydrogesterone
Progesterone: Administered via different routes: oral, intramuscular, or vaginal (suppositories/gels).
Dydrogesterone: Structurally and pharmacologically similar to natural progesterone. Has good oral bioavailability, a good safety and tolerability profile, and crucially, no androgenic effects on the fetus.
VII. When Should the Gynecologist Refer a Patient to an IVF Specialist?
Early referral benefits include a reasonable chance of achieving pregnancy, an increase in live birth rate, and a reduction in recurrent pregnancy loss.
Unexplained Infertility (Idiopathic): IVF is the method of choice if the duration of infertility is 3 years or longer. If the woman is older than 36 years, IVF may be considered earlier. (IUI merits consideration before IVF).
Hormonal Disturbances: IVF is the method of choice in case of anovulatory cycle abnormalities if 12 cycles of treatment with ovulation induction have been unsuccessful.
COMPREHENSIVE FERTILITY DRUGS & FEMALE REPRODUCTIVE SYSTEM PHARMACOLOGY
Drugs that affect the female reproductive system typically include Female Sex Hormones, Estrogen Receptor Modulators, Fertility Drugs (Gonadotropins), Uterotonics, and Abortifacients.
A. Female Sex Hormones (Estrogens and Progestins)
Used for hormone replacement therapy (HRT), oral contraceptives, treating hypogonadism, endometriosis, dysmenorrhea, and palliative cancer care.
Functions: Stimulates development of female sex characteristics, thickens endometrial lining, maintains bone mineral density, prevents atherosclerosis (increases HDL, lowers LDL), and maintains vaginal lubrication/libido.
Dosages:
Estradiol: 1–2 mg/day orally, or 1–5 mg IM every 3–4 weeks, or 2–4 g intravaginal cream daily.
Functions: The "pregnancy hormone". Transforms proliferative endometrium into secretory endometrium. Prevents uterine contractions. Inhibits GnRH, FSH, and LH in contraceptives.
Dosages:
Etonogestrel (Implanon): 68 mg implanted sub-dermally for up to 3 years.
Medroxyprogesterone (Provera): 5–10 mg/day PO for 5–10 days (amenorrhea) or 150 mg deep IM every 3 months for contraception.
Indication: First-line for anovulatory infertility (WHO Group II). Mechanism: Binds to estrogen receptors in the hypothalamus, blocking negative feedback. This increases GnRH, driving up FSH/LH release to stimulate ovulation.
50 mg daily for 5 days. Starting within 5 days of onset of menstruation (usually Day 2 or Day 5). If no response, increase to 100 mg daily for 5 days in subsequent cycles.
Letrozole (Femara) Aromatase Inhibitor
Indication: Superior first-line for PCOS anovulation. Mechanism: Blocks the conversion of androgens to estrogens, dropping systemic estrogen, triggering a release of FSH from the pituitary without depleting peripheral estrogen receptors like CC.
2.5 mg to 7.5 mg daily for 5 days (typically Days 3-7 of cycle).
Bromocriptine & Cabergoline Dopamine Agonists
Indication: Hyperprolactinemic infertility, galactorrhea, benign breast disease. Mechanism: Mimics dopamine to inhibit pituitary secretion of prolactin.
Bromocriptine: Initially 1.25 mg at bedtime, increased gradually to 2.5 mg BID/TID with meals (max 30mg/day). Cabergoline: Given once or twice weekly due to longer half-life.
Indication: CC-resistant anovulation, IVF stimulation, male hypogonadotropic hypogonadism. Mechanism: Direct stimulation of ovaries (contains 1:1 FSH and LH).
Given via daily SC/IM injections. Dosages vary widely based on step-up or step-down protocols (e.g., 37.5 to 150 IU daily) guided by ultrasound.
Fluid Retention: Common due to high estrogen levels promoting sodium retention, and increased pelvic blood flow.
Others: Headache, nausea, bloating, visual disturbances (especially with Clomiphene - indicates immediate cessation), gynecomastia (in men), and febrile reactions.
NURSING CARE PLAN & MANAGEMENT FOR FERTILITY DRUG THERAPY
No.
Nursing Diagnosis
Interventions & Rationale
1
Deficient Knowledge regarding drug therapy, administration techniques, and monitoring schedules.
Educate on Injection Technique: Teach patients how to self-administer SC injections (e.g., rhFSH, hCG) safely, rotate sites, and dispose of sharps.
Explain Monitoring Requirements: Emphasize the absolute necessity of attending scheduled transvaginal ultrasounds and blood draws to monitor follicular growth and prevent OHSS.
2
Risk for Impaired Tissue Perfusion related to increased risk of thrombus formation secondary to high estrogen states.
Counsel against Smoking: Strongly advise women taking fertility drugs or estrogens to stop smoking due to the compounded risk of thrombotic events.
Monitor for VTE Signs: Instruct patients to report sudden leg pain, swelling, chest pain, or shortness of breath immediately.
3
Acute Pain / Fluid Volume Excess related to fluid retention, GI upset, and ovarian enlargement (Risk for OHSS).
Monitor for OHSS: Educate the patient on warning signs of severe OHSS: rapid weight gain, severe abdominal pain, bloating, decreased urination, and shortness of breath. Require daily weight monitoring.
Provide Comfort Measures: Recommend loose clothing and mild analgesics (approved by the physician) for minor bloating and headaches.
4
Situational Low Self-Esteem / Anxiety related to infertility diagnosis, invasive treatments, and hormonal mood swings.
Provide Psychological Support: Women receiving these drugs require extensive comfort measures. Hormonal fluctuations exacerbate anxiety. Provide a non-judgmental space to express fears.
Discuss Outcomes: Clearly explain the risk of multiple births and set realistic expectations for success rates per cycle to manage disappointment.
5
Sexual Dysfunction related to scheduled intercourse, pelvic discomfort, and altered normal hormone control.
Open Communication: Normalize the stress that "timed intercourse" places on a relationship. Encourage open communication between partners.
Key Nursing Reminders
Women receiving reproductive hormones should receive an annual medical examination, including breast examination and Pap smear.
Drugs used in the treatment of specific cancers in males (like estrogens for prostate cancer) require education about the possibility of estrogenic effects (gynecomastia).
Not indicated during pregnancy or lactation due to fetal risks. Always rule out pregnancy before starting a new cycle of ovulation induction.
References
Jose-Miller AB, et al. Major Causes of Subfertility. Am Fam Physician 2007;75:849-56, 857-8.
Lunenfeld B. Historical perspectives in gonadotrophin therapy. Hum Reprod Update 2004;10:453.
Weiss NS, Nahuis M, Bayram N, et al. Gonadotrophins for ovulation induction in women with polycystic ovarian syndrome. Cochrane Database Syst Rev 2015.
Balen AH. Practical considerations while using gonadotropins. Mol Cell Endocrinol. 2013 Jul 5;373(1-2):77-82.
Fauser BC, Van Heusden AM. Manipulation of human ovarian function: physiological concepts and clinical consequences. Endocr Rev 1997; 18:71.
White DM, Polson DW, Kiddy D, et al. Induction of ovulation with low-dose gonadotropins in PCOS. J Clin Endocrinol Metab 1996; 81:3821.
van Santbrink EJ, et al. Gonadotrophin induction of ovulation using a step-down dose regimen. Hum Reprod 1995; 10:1048.
Cohlen et al. GnRH analogue in combination with gonadotropins. Cochrane Database Syst Rev 2007 Apr 18;(2):CD005356.
Rizzuto I, Behrens RF, Smith LA. Risk of ovarian cancer in women treated with ovarian stimulating drugs for infertility. Cochrane Database Syst Rev 2013; CD008215.
Brinton LA, et al. Breast cancer risk associated with ovulation-stimulating drugs. Hum Reprod 2004; 19:2005.
Hill MJ, et al. Progesterone luteal support after ovulation induction and intrauterine insemination. Fertility and Sterility Vol. 100. No. 5. Nov 2013.
Ben-Ami I, et al. When Should the Gynecologist Refer a Patient to an IVF Specialist? Textbook of Assisted Reproductive Techniques. 2012; 18–30.
Quick Quiz
Gonadotropins Quiz
Pharmacology
Privacy: Your details are used only for quiz tracking and certificates.
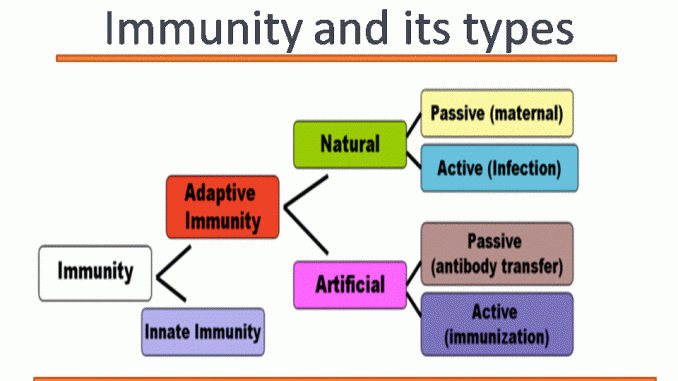
Immunization is a process of deliberate inoculation of live attenuated or dead vaccines and toxoids to induce immunity against a specific disease. Immunization against a specific disease provides artificially acquired active immunity. The principle of immunization is to increase specific immunity to infection by administration of either immune serum (passive immunization) or by administration of an antigen (active immunization).
Artificially acquired immunity against some diseases may require periodic booster injections to keep an adequate antibody level (or antibody titer) circulating in the blood. A booster injection is the administration of an additional dose of the vaccine to boost the production of antibodies to a level that will maintain the desired immunity. The booster is given months or years after the initial vaccine and may be needed because the life of some antibodies is short.
Types of Immunization Agents
Toxoids: is a toxin that is attenuated (or weakened) but still capable of stimulating the formation of antitoxins.
Vaccines: Special preparations of antigenic materials that can be used to stimulate the development of antibodies.
Immune Globulins: Preparations containing antibodies against infectious micro-organisms, usually prepared from human plasma or serum.
Antisera: Sterile preparations containing immunoglobulins obtained from the serum of immunized animals by purification. They have the power of neutralizing venoms or bacterial toxins.
Active vs. Passive Immunization
The principal goal of immunization is to increase specific immunity to infection. This can be achieved through two main strategies: active immunization and passive immunization.
Passive Immunization
Passive immunization is the administration of already active antibodies to prevent or ameliorate infection. It gives immediate protection but immunity lasts for a short period of time. Passive immunisation is used in post-exposure prophylaxis in immunocompetent hosts when immediate protection is required following exposure to the infection e.g. tetanus.
Infections for which passive immunization is useful are:
Hepatitis B
Rabies
Tetanus
Diphtheria
Advantages of passive immunisation:
Passive immunisation can be lifesaving if toxin is already circulating.
Prompt availability of large amount of antibodies.
Disadvantages of passive immunisation:
Protection is short-lived (up to 6 months) as the borrowed antibodies are eventually degraded and cleared.
Use of human antisera has dangers of transmitting infections like HIV or Hepatitis.
Antisera are expensive compared to vaccines.
They need to be kept cool and have limited life span.
Active Immunization
Active immunization is a process of increasing resistance to infection whereby micro-organisms or products of their activity act as antigens and stimulate certain body cells to produce antibodies with a specific productive capacity. It may be a natural process following recovery from an infection, or an artificial process induced by the administration of vaccines.
Active immunization is a process where the individual's own immune system is stimulated to produce antibodies and memory cells against a specific pathogen. This is achieved by administering an antigen, usually in the form of a vaccine. It may be a natural process following recovery from an infection, or an artificial process induced by vaccination.
Aims of Active Immunization:
To protect susceptible individuals against specific infections.
To reduce the incidence of infection in the community, leading to herd immunity.
To eliminate an infection in a particular country or worldwide (e.g., the successful eradication of smallpox and the ongoing effort to eradicate polio).
Booster Injections:
Artificially acquired immunity against some diseases may require periodic booster injections to keep the antibody level (titer) adequate for protection. A booster is an additional dose given months or years after the primary vaccination series to "boost" the immunological memory and production of antibodies.
Advantages of Active immunization:
Offers long-term, often lifelong, immunity due to the formation of memory cells.
Disadvantages of Active immunization:
Has a slow onset of action, as it takes time (days to weeks) for the body to mount a primary immune response and become fully protected.
Vaccines
Vaccines are special preparations of antigenic materials designed to stimulate the development of antibodies and confer active immunity. Vaccination refers to the administration of a vaccine.
Types of Vaccines:
Live Attenuated Vaccines:
These vaccines use live microorganisms that have been weakened (attenuated) so they can still replicate but do not cause disease in healthy individuals. They typically provide long-lasting immunity with a single dose (with some exceptions like OPV).
Live vaccines give longer protection than killed vaccines.
One dose of the vaccine is usually sufficient with exception of oral polio vaccines.
Disadvantages of Live Attenuated Vaccines
Live vaccines are often unstable e.g. measles and polio need to be stored at -20°C.
Live vaccines may not work in the presence of circulating antibodies e.g. measles vaccine has to be given around 9 months of age when maternal antibodies have gone.
Live vaccines may cause disease if the host is immuno deficient as in HIV infection.
Live vaccines occasionally interfere with each other so that the immune response is not so great if given together.
Killed or Inactivated Vaccines:
These vaccines use whole bacteria or viruses that have been killed and can no longer replicate. They are very safe but usually require a series of injections and booster doses to produce an adequate response.
These vaccines use bacterial toxins that have been chemically inactivated to become harmless toxoids. They stimulate the production of antitoxins.
Examples: Tetanus toxoid, Diphtheria toxoid.
Disadvantages: Immunity can be short-lived, requiring booster doses.
Indications of Vaccines and Toxoids:
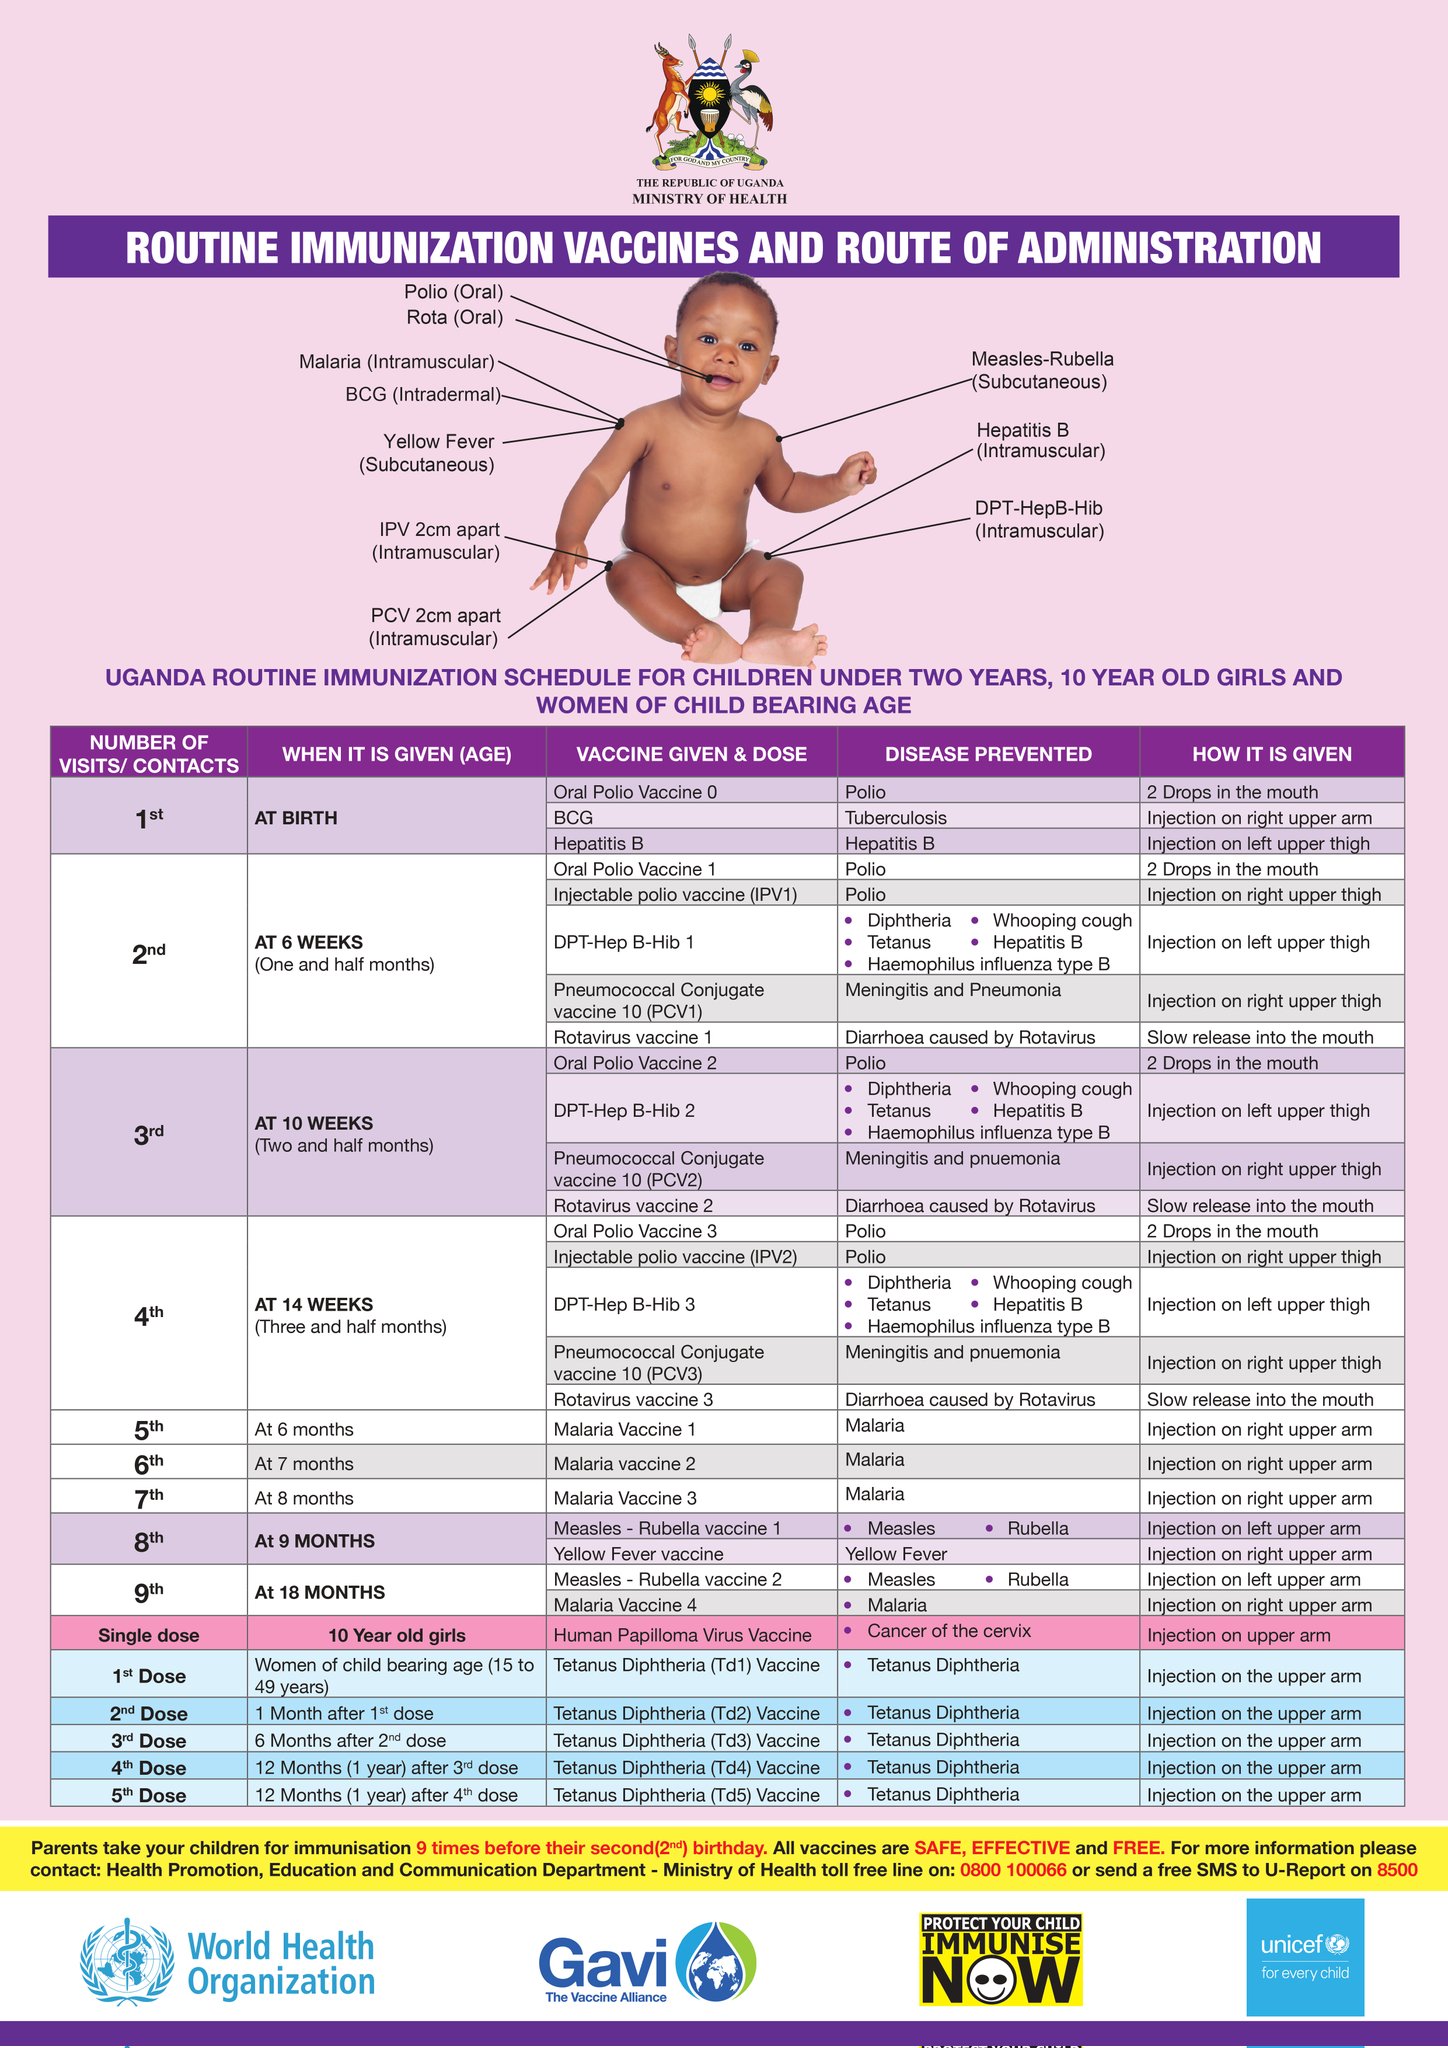
Routine immunization of infants and children.
Immunization of adults against tetanus.
Immunization of adults at high risk for certain diseases (e.g., pneumococcal and influenza vaccines).
Immunization of children or adults at risk for exposure to a particular disease (e.g., hepatitis A for those going to endemic areas).
Immunization of pre-pubertal girls or non-pregnant women of childbearing age against rubella and cervical cancer.
Adverse Reactions of Vaccines and Toxoids:
Adverse reactions from the administration of vaccines or toxoids are usually mild.
Chills, Fever, muscular aches and pains, rash, and lethargy may be present.
Pain and tenderness at the injection site may also occur.
Although rare, a hypersensitivity reaction may occur.
Contraindications and Precautions of Vaccines and Toxoids:
Hypersensitivity: Individuals with known severe allergic reactions to vaccine components or previous doses should not receive the vaccine.
Vaccines and toxoids are generally contraindicated during acute febrile illnesses, leukemia, lymphoma, immunosuppressive illness or drug therapy, and non-localized cancer.
The measles, mumps, rubella, and varicella vaccines are contraindicated in patients who have had an allergic reaction to gelatin, neomycin, or a previous dose of one of the vaccines.
The measles, mumps, rubella, and varicella vaccines are generally contraindicated during pregnancy, especially during the first trimester, because of the theoretical danger of birth defects. Women are instructed to avoid becoming pregnant for at least 3 months after receiving these vaccines.
Antisera and Immunoglobulins
Antisera: Sterile preparations containing immunoglobulins obtained from the serum of immunized animals (e.g., horses). They are used to neutralize venoms or bacterial toxins.
Immunoglobulins: Preparations containing specific antibodies, usually prepared from pooled human plasma. They are used for passive immunization.
Properties of an Ideal Vaccine
Should be able to induce an adequate and appropriate immune response without causing active infection.
The vaccine should be safe with minimal side effects.
The vaccine should be stable and remain potent during storage and transportation.
The vaccine should be cheap if it is to be used on a large scale.
It should be easy to administer.
It should be highly purified so that it consists of one or only a few antigens.
Autoimmune Diseases
Autoimmune diseases occur when the immune system loses its ability to distinguish "self" from "non-self" and mistakenly begins to attack the body's own cells and tissues. This failure of self-tolerance can be triggered by a combination of genetic susceptibility, environmental factors, and infections.
It is thought that female hormones like estrogen may enhance the inflammatory response, which could be one reason why autoimmune diseases are often more common or severe in women than in men.
Autoimmune Diseases and Parts Affected
Disease
Part of the Body Primarily Affected
Rheumatoid Arthritis
Cartilage and linings of the joints.
Graves' Disease
Thyroid gland (causes hyperthyroidism).
Insulin-Dependent Diabetes Mellitus (Type 1)
Insulin-producing beta cells of the pancreas.
Multiple Sclerosis (MS)
Myelin sheath of nerves in the brain and spinal cord.
Psoriasis
Skin cells.
Ankylosing Spondylitis
Joints of the spine.
Specific Vaccine Details
This section provides a detailed breakdown of the key vaccines used in immunization programs, including their type, indications, dose, side effects, contraindications, and special precautions.
BCG (Bacillus Calmette-Guérin) Vaccine
Type: Live attenuated bacterial vaccine.
Indications: Active immunization against severe forms of tuberculosis (TB) in children, such as TB meningitis and miliary TB. Protection against leprosy (in some contexts where leprosy is endemic and BCG is used for this purpose).
Dose:
Infants less than 12 months: 0.05ml administered intradermally in the right upper arm.
Adults and children over 12 months: 0.1ml administered intradermally in the right upper arm.
Side Effects: A localized papule, sore, and then ulceration at the injection site is a normal, expected reaction that heals to form a permanent scar. Lymphadenitis (swelling of local lymph nodes). Keloid formation at the scar site. Abscess formation at the injection site (rare, more severe). Osteitis/Osteomyelitis (inflammation of bone, very rare systemic complication). Disseminated BCG infection: A rare but severe complication that can occur in severely immunosuppressed patients.
Contraindications: Severely immunocompromised patients (e.g., advanced HIV/AIDS, congenital immunodeficiency, individuals on immunosuppressive therapy). Generalized skin conditions like eczema or scabies at the intended injection site. Patients undergoing antibacterial treatment for tuberculosis. Known allergy to any component of the vaccine. Infants weighing less than 2 kg. Individuals with a positive tuberculin skin test (PPD) or IGRA (Interferon Gamma Release Assay), as this may indicate latent TB infection. Acute severe febrile illness (generally a temporary contraindication).
Precautions: Pregnancy (though it may be given if the risk of TB exposure is high and benefits outweigh risks, especially in high-endemic areas). Infants born to HIV-positive mothers (careful risk-benefit assessment; may be given if the infant is asymptomatic for HIV and the risk of TB exposure is high, but generally avoided if HIV status is confirmed and symptomatic). Concomitant use with other live vaccines (spacing may be recommended by national guidelines, though many routine schedules allow co-administration).
Diphtheria, Pertussis, Tetanus (DPT) Vaccine (in Pentavalent)
Type: A combination vaccine containing Diphtheria and Tetanus toxoids and an inactivated (killed) whole-cell Pertussis bacteria component. Note: Modern DPT vaccines often use acellular pertussis (aP) components (DTaP) which have fewer side effects, but the provided text specifies whole-cell. Pentavalent typically contains DPT-HepB-Hib.
Indications: Active immunization against Diphtheria, Tetanus, and Pertussis (whooping cough) in infants and young children. Primary vaccination series for infants as part of routine immunization programs.
Dose: Given as part of the Pentavalent vaccine series: 0.5ml intramuscularly at 6, 10, and 14 weeks of age. Specific schedules may vary by national immunization guidelines.
Side Effects:
Common: Pain, redness, and swelling at the injection site; fever; irritability; restlessness; loss of appetite; drowsiness.
Less common: Persistent, inconsolable crying (lasting 3 hours or more); high fever (>=40.5°C); febrile seizures (very rare).
Rare: Anaphylaxis (severe allergic reaction); hypotonic-hyporesponsive episodes (HHE); peripheral neuropathy; severe neurological reactions (especially associated with the whole-cell pertussis component, e.g., encephalopathy). Injection site nodule/lump which can persist for weeks.
Contraindications: Known hypersensitivity to any of the ingredients of the vaccine or a severe allergic reaction to a previous dose. A history of a severe neurological reaction (e.g., encephalopathy not attributable to another identifiable cause) within 7 days of a previous dose of pertussis-containing vaccine. Progressive neurological disorder, including infantile spasms, uncontrolled epilepsy, or progressive encephalopathy (vaccination should be deferred until the condition has stabilized). Acute severe febrile illness (vaccination should be deferred until recovery).
Precautions: Minor illnesses (e.g., mild upper respiratory infection, low-grade fever) are generally NOT contraindications. Family history of seizures or other neurological disorders (not a contraindication but requires observation after vaccination). History of a reaction following a previous dose that is considered a precaution (e.g., temperature ≥40.5°C within 48 hours not due to another cause, collapse/shock-like state within 48 hours, persistent crying lasting ≥3 hours within 48 hours, seizures with or without fever within 3 days). In such cases, benefits versus risks of subsequent doses should be carefully considered, and acellular pertussis vaccines (DTaP) might be preferred if available.
Tetanus Toxoid (TT) or Tetanus-Diphtheria (Td) Vaccine
Type: Toxoid vaccine. Td contains tetanus toxoid and a reduced dose of diphtheria toxoid.
Indications: Active immunization against tetanus. Prevention of neonatal tetanus through the immunization of pregnant women and women of childbearing age. Boostering immunity against tetanus and diphtheria in adolescents and adults. Post-exposure prophylaxis for tetanus following wounds (often in combination with Tetanus Immunoglobulin if indicated).
Dose (for Women of Childbearing Age and General Adult Boosters):
Primary Series: Varies, but often 2-3 doses given at intervals (e.g., 0 and 4-8 weeks).
TT1 (for Pregnant Women/WOCBA): 0.5ml deep IM or SC at first contact/early in pregnancy.
TT2: 0.5ml at least 4 weeks after TT1 (preferably before 36 weeks of pregnancy).
TT3: 0.5ml at least 6 months after TT2.
TT4: 0.5ml at least 1 year after TT3.
TT5: 0.5ml at least 1 year after TT4. (5 doses provide long-lasting protection, often considered lifelong for practical purposes if fully completed).
Booster Doses: Recommended every 10 years for adolescents and adults.
Side Effects: Common: Local reactions like pain, tenderness, redness, swelling, and a lump at the injection site. These are usually mild and resolve within a few days. Less common: Low-grade fever, headache, body aches, tiredness. Rare: Anaphylaxis (severe allergic reaction); brachial neuritis (inflammation of nerves in the arm, very rare); peripheral neuropathy. Arthus-type reactions (severe local reaction with swelling and pain) can occur, particularly in adults who receive frequent booster doses.
Contraindications: Known hypersensitivity to any component of the vaccine or a severe allergic reaction to a previous dose. A history of a severe Arthus-type hypersensitivity reaction following a previous dose of tetanus or diphtheria toxoid-containing vaccine (usually not given again for at least 10 years). Acute severe febrile illness (defer vaccination until recovery).
Precautions: Minor illnesses (e.g., mild upper respiratory infection, low-grade fever) are generally NOT contraindications. History of Guillain-Barré Syndrome (GBS) within 6 weeks of a previous dose of tetanus toxoid-containing vaccine (decision to vaccinate should weigh benefits against potential risks).
Measles, Mumps, and Rubella (MMR) Vaccine
Type: Live attenuated virus vaccine.
Indications: Active immunization against Measles, Mumps, and Rubella. Recommended for all children as part of routine immunization schedules. Prevention of congenital rubella syndrome in women of childbearing age (ensure non-pregnant at vaccination and avoid pregnancy for recommended period). Outbreak control measures in susceptible populations.
Dose: 0.5ml administered by deep subcutaneous or intramuscular injection. First dose: Typically at 12-15 months of age (some regions, like Uganda, may give first measles dose earlier at 9 months, and then MMR later). Second dose: Recommended for sustained immunity, often at 4-6 years of age (e.g., prior to school entry) or later, depending on national schedules.
Side Effects: Common (5-12 days after dose 1): Fever (up to 15%), malaise, and a non-infectious, non-contagious maculopapular rash (measles-like) (5%). Common (3-4 weeks after dose 1): Parotid swelling (mild, mumps-like symptoms, <1%). Common (2-4 weeks after dose 1, particularly in post-pubertal females): Transient arthralgia or arthritis (joint pain/inflammation) related to the rubella component. Rare: Thrombocytopenia (transient low platelets, 1 in 30,000 to 40,000 doses). Very Rare: Febrile seizures (usually benign, related to the fever, not the vaccine itself causing epilepsy); anaphylaxis (severe allergic reaction, approx. 1 in 1,000,000 doses).
Contraindications: Pregnancy (known or suspected). Women should be advised to avoid pregnancy for at least 1 month after vaccination. Severe immunosuppression (e.g., congenital immunodeficiency, HIV with severe immunosuppression, leukemia, lymphoma, generalized malignancy, high-dose corticosteroids, chemotherapy, radiation therapy). Known hypersensitivity to vaccine components (e.g., neomycin, gelatin). A history of a severe allergic reaction (anaphylaxis) to a previous dose of MMR vaccine. Receipt of blood products (e.g., transfusions, immunoglobulin) containing antibodies within a certain period (typically 3-11 months, depending on the product), as these antibodies can interfere with vaccine efficacy. Acute severe febrile illness (defer vaccination until recovery).
Precautions: History of convulsions or epilepsy in the patient or family (parents should be advised on managing fever and monitoring for seizures, but vaccination is generally safe). Individuals with mild illness (e.g., low-grade fever, upper respiratory infection) can generally be vaccinated. The vaccine should be cautiously administered to individuals with a history of thrombocytopenia or thrombocytopenic purpura, as a recurrence is possible (risk vs. benefit should be assessed). Recent receipt of another live injected vaccine within the last 4 weeks (some guidelines prefer spacing by 4 weeks if not co-administered, but often co-administration is acceptable).
Hepatitis B Vaccine
Type: Recombinant subunit vaccine (contains inactivated Hepatitis B surface antigen, HBsAg), produced in yeast.
Indications: Active immunization against Hepatitis B infection. Universal vaccination of all infants and children as part of routine immunization programs. Crucial for high-risk groups: infants born to HBsAg-positive mothers (should receive birth dose and Hepatitis B Immunoglobulin - HBIG); healthcare personnel; public safety workers; hemodialysis patients; patients with chronic liver disease; individuals with multiple sexual partners; injecting drug users; close contacts and sexual partners of HBsAg carriers; international travelers to endemic areas.
Dose:
Infants: First dose given within 24 hours of birth (birth dose), then typically as part of the Pentavalent vaccine at 6, 10, and 14 weeks (some schedules use a 0, 1, 6 month pattern if given as stand-alone).
Children and Adolescents: Typically a 2- or 3-dose series depending on the specific vaccine and age.
Adults: Typically a 3-dose series (e.g., 0, 1, and 6 months) or a rapid 4-dose series for specific needs.
Administered intramuscularly, usually in the anterolateral thigh for infants/young children and deltoid muscle for older children/adults.
Side Effects: Common: Pain, tenderness, redness, and swelling at the injection site (up to 29%). Less common: Low-grade fever, headache, myalgia (muscle aches), arthralgia (joint pain), fatigue, gastrointestinal disturbances (nausea, diarrhea). These are usually mild and transient. Rare: Anaphylaxis (severe allergic reaction, extremely rare).
Contraindications: Known hypersensitivity to yeast or any other component of the vaccine. A history of a severe allergic reaction (anaphylaxis) to a previous dose of Hepatitis B vaccine. Acute severe febrile illness (defer vaccination until recovery).
Precautions: Immunocompromised patients (e.g., those on dialysis, HIV-infected individuals, transplant recipients) may have a diminished immune response and may require higher doses, additional doses, or post-vaccination serologic testing to ensure adequate protection. Mild illness (e.g., low-grade fever, common cold) is generally not a contraindication. Use with caution in pregnancy and lactation (no evidence of harm, but generally recommended if risk of exposure is high). The benefits of vaccinating pregnant women at high risk for HBV infection outweigh potential risks to the fetus.
Yellow Fever Vaccine
Type: Live attenuated virus vaccine (17D strain).
Indications: Active immunization against yellow fever, especially for residents of and travelers to endemic areas. Required for entry into certain countries where yellow fever is endemic or where there's a risk of transmission. Mass vaccination campaigns in areas with ongoing outbreaks or high risk.
Dose: A single 0.5ml dose administered by subcutaneous injection (preferred) or intramuscular injection. Typically given at 9 months of age in endemic regions. Provides lifelong immunity for most people after a single dose, according to WHO. Some countries may still require revaccination certificates every 10 years for entry, so checking international health regulations is crucial for travelers.
Side Effects: Mild (common, 5-10 days after vaccination): Headache, myalgia, low-grade fever, flu-like symptoms, injection site reactions (pain, redness, swelling). These usually resolve within a few days. Rare but serious: Anaphylaxis (severe allergic reaction, approx. 1 in 130,000 doses). Very Rare but severe: Yellow Fever Vaccine-Associated Neurologic Disease (YEL-AND), typically neurological symptoms like encephalitis or meningitis (occurs in approx. 0.8 in 100,000 doses). Very Rare and most severe: Yellow Fever Vaccine-Associated Viscerotropic Disease (YEL-AVD), a multi-organ failure resembling severe yellow fever (occurs in approx. 0.3 in 100,000 doses, higher risk in older individuals).
Contraindications: Infants under 6 months of age (and used with caution between 6-8 months due to higher risk of YEL-AND). Severe immunosuppression (e.g., congenital immunodeficiency, HIV with CD4 count <200 cells/mm3, leukemia, lymphoma, generalized malignancy, high-dose corticosteroids, chemotherapy, radiation therapy). Known hypersensitivity to eggs, egg proteins, or any other component of the vaccine (e.g., gelatin, chicken protein). Individuals with a history of thymus disorders (e.g., thymoma, thymectomy, myasthenia gravis, DiGeorge syndrome) due to increased risk of YEL-AVD. Acute severe febrile illness (defer vaccination until recovery).
Precautions: Age 60 years or older: Increased risk of YEL-AND and YEL-AVD. Benefits and risks should be carefully weighed, especially for first-time vaccine recipients. Pregnancy: Generally not recommended unless travel to an endemic area with high risk of exposure cannot be avoided. Risk vs. benefit assessment is crucial. Breastfeeding: Generally not recommended if the infant is under 9 months due to theoretical risk of transmission through breast milk, unless the risk of maternal infection is high. Mild illness is generally not a contraindication. As a live vaccine, it should ideally be given simultaneously with other live vaccines or spaced by at least 4 weeks.
Pneumococcal Vaccine
Type: There are two main types, which are not interchangeable:
Pneumococcal Conjugate Vaccine (PCV): Such as PCV10 (used in Uganda) or PCV13, PCV15, PCV20. The polysaccharide capsule antigens are "conjugated" (joined) to a protein carrier, which creates a strong and lasting immune response, especially in infants and young children, and induces T-cell dependent memory.
Pneumococcal Polysaccharide Vaccine (PPSV23): Contains antigens from 23 different serotypes. It provides broader serotype coverage but elicits a T-cell independent immune response, which is weaker and shorter-lived, and not effective in children under 2 years old. It is primarily used for adults and high-risk older children.
Indications: Active immunization against diseases caused by Streptococcus pneumoniae, including pneumonia, meningitis, bacteremia (invasive pneumococcal disease), and otitis media. Crucial for high-risk populations: all infants and young children (PCV); adults over 65 years (PCV and/or PPSV23); and individuals with underlying medical conditions such as sickle cell disease, functional or anatomic asplenia, chronic heart, lung, or kidney disease, diabetes mellitus, and immunosuppression (PCV and/or PPSV23).
Dose:
PCV (Routine for infants): 0.5ml IM at 6, 10, and 14 weeks (Uganda schedule). Other common schedules include 2, 4, 6 months with a booster at 12-15 months, or 2, 4 months with a booster.
PPSV23 (for adults/high-risk): 0.5ml IM or deep SC as a single dose. Revaccination with PPSV23 may be considered for those at highest risk after 5 years. Sequential vaccination with PCV followed by PPSV23 is often recommended for certain adult risk groups.
Side Effects: Common: Fever, irritability, drowsiness, and local reactions at the injection site (pain, redness, swelling, tenderness). These are generally mild and resolve within 1-2 days. Less common: Decreased appetite, vomiting, diarrhea. Rare: Anaphylaxis (severe allergic reaction).
Contraindications: A severe allergic reaction (anaphylaxis) to a previous dose of the specific pneumococcal vaccine or to any component of the vaccine. Acute severe febrile illness (defer vaccination until recovery).
Precautions: Mild illness or low-grade fever is generally not a contraindication. In individuals with compromised immune systems (e.g., due to HIV infection, immunosuppressive therapy), the immune response to the vaccine may be diminished. For PPSV23, administer with caution to individuals with a history of severe local reactions to previous doses.
Meningococcal Vaccine
Type: Can be a polysaccharide vaccine (e.g., MPSV4) or, more effectively, a conjugate vaccine (e.g., MCV4 or MenACWY). They are formulated against the most common disease-causing serogroups of Neisseria meningitidis: A, C, Y, and W-135 (quadrivalent vaccines). Monovalent (e.g., Men C) and bivalent (e.g., Men A+C) preparations are also available. Separate vaccines exist for serogroup B (MenB vaccines).
Indications: Active immunization against meningococcal meningitis and septicemia caused by vaccine-preventable serogroups. Essential for individuals residing in or traveling to the "meningitis belt" of sub-Saharan Africa, particularly during epidemic seasons. Recommended for travelers to high-risk areas, military recruits, university students living in dormitories, and individuals with certain medical conditions (e.g., asplenia, persistent complement component deficiencies, those on eculizumab). Outbreak control in specific populations.
Dose: 0.5ml by deep subcutaneous (polysaccharide) or intramuscular (conjugate) injection as a single dose or multi-dose series depending on the vaccine type, age, and schedule. For conjugate vaccines, routine vaccination for adolescents is common, with a booster dose.
Side Effects: Common: Local pain, redness, and swelling at the injection site; headache; fatigue; malaise; muscle aches; low-grade fever. These are usually mild and transient. Rare: Allergic reactions, including anaphylaxis.
Contraindications: Known severe allergy to any ingredient in the vaccine or a severe allergic reaction to a previous dose. Acute severe febrile condition (postpone vaccination until recovery).
Precautions: Use with caution during pregnancy: Generally recommended only if the benefit of vaccination outweighs the potential risk to the fetus, such as in high-risk travel or outbreak situations. The immune response from polysaccharide vaccines in children under 2 years may be short-lived and does not induce herd immunity or memory, making conjugate vaccines preferred for this age group and for broader public health impact. Individuals with mild illness are generally not a contraindication.
Cholera Vaccine
Type: An oral vaccine. There are two main types:
Live attenuated preparation: (e.g., Vaxchora) - single dose.
Inactivated whole-cell preparations: (e.g., Dukoral, Shanchol, Euvichol) - usually multi-dose. These contain killed whole cells of Vibrio cholerae, often combined with B subunit of cholera toxin (Dukoral).
Indications: Prophylactic immunization for travelers over 2 years of age (or younger depending on the specific vaccine) going to areas with high risk of cholera infection, particularly those who will be in areas with poor sanitation and hygiene. Used in outbreak control and humanitarian settings to reduce transmission, but is not a substitute for providing safe water, sanitation, and hygiene (WASH) interventions. Not typically part of a routine national immunization schedule in most non-endemic countries.
Dose: Varies significantly by vaccine type and manufacturer:
Inactivated (Dukoral): Requires a multi-dose schedule. Children 2-6 years: 3 doses, with 1-6 weeks between doses. Adults and children >6 years: 2 doses, with 1-6 weeks between doses. A booster dose is typically recommended after 2 years for continued protection.
Live attenuated (Vaxchora): Single dose for individuals aged 2 to 64 years.
Important Instruction: For most oral cholera vaccines, the patient must avoid food and drink for 1 hour before and 1 hour after taking the oral vaccine. Check specific product instructions.
Side Effects: Common: Abdominal discomfort, mild diarrhea, nausea, vomiting, headache, loss of appetite. These are usually mild and transient. Rare: Hypersensitivity reactions.
Contraindications: History of hypersensitivity or severe allergic reaction to any of the ingredients of the specific vaccine or a previous dose. Should be postponed during an acute moderate to severe gastrointestinal illness (e.g., acute diarrhea, vomiting) or acute moderate to severe febrile illness. For live attenuated vaccines: severe immunocompromise (similar to other live vaccines).
Precautions: Efficacy may be reduced if taken concurrently with certain medications (e.g., antacids, antibiotics). Check specific product information. Not a substitute for practicing safe food and water hygiene. Protection is not 100%, and duration of protection varies by vaccine. Pregnancy and breastfeeding: Consult with a healthcare provider; generally, only given if the risk of exposure is high and benefits outweigh potential risks.
Rabies Vaccine
Type: An inactivated (killed) virus vaccine. Prepared from purified chick embryo cell culture (PCEC), human diploid cell culture (HDCV), or Vero cell culture.
Indications:
Post-Exposure Prophylaxis (PEP): To prevent the development of rabies after a person has been bitten, scratched, or had mucous membrane exposure to a potentially rabid animal. This is a medical emergency, as rabies is nearly 100% fatal once symptoms begin. PEP includes immediate wound cleansing, vaccine administration, and in severe cases, Rabies Immunoglobulin (RIG).
Pre-Exposure Prophylaxis (PrEP): For persons at high and continuous risk of exposure, such as veterinarians, animal handlers, laboratory workers handling the rabies virus, speleologists, and travelers to rabies-endemic areas who may not have immediate access to medical care.
Dose:
Pre-exposure (PrEP): Standard: 1ml (or 0.5ml for intradermal) IM injection on days 0, 7, and 21 or 28. Newer schedules (e.g., 2 doses for some vaccines) are being explored.
Post-exposure (PEP): For unvaccinated individuals: 1ml IM injection on days 0, 3, 7, and 14 (4-dose regimen). In some settings, a 5-dose regimen (days 0, 3, 7, 14, 28) or 2-site intradermal regimens are used. For previously vaccinated individuals (PrEP complete): 1ml IM injection on days 0 and 3 (2-dose regimen), no RIG needed.
For severe exposures, especially in unvaccinated individuals, Rabies Immunoglobulin (RIG) should also be infiltrated around the wound and into the wound on day 0, as much as anatomically feasible.
Route: Intramuscular (IM) injection, usually in the deltoid muscle for adults and anterolateral thigh for young children. Intradermal (ID) routes are also approved for certain schedules in some regions, which can save vaccine.
Side Effects: Common: Pain, redness, swelling, and itching at the injection site (up to 30-70%). Systemic: Fever, headache, dizziness, myalgia (muscle aches), malaise (general discomfort), nausea, abdominal pain. These are usually mild. Rare: Hypersensitivity reactions (e.g., urticaria, rash, anaphylaxis). Neurological complications are extremely rare.
Contraindications: There are generally no contraindications to PEP once exposure to rabies is suspected or confirmed, given the fatal nature of the disease. For PrEP, contraindications are similar to other inactivated vaccines: severe allergic reaction to a previous dose or component of the vaccine, or acute moderate to severe febrile illness (defer until recovery).
Precautions: Administer with caution to individuals with a history of hypersensitivity reactions to previous doses. Pregnancy and breastfeeding: Not a contraindication for PEP; for PrEP, it should be given if the risk of exposure is substantial. Immunocompromised individuals: May require additional doses or serologic testing to confirm adequate immune response after PrEP, and for PEP, the full recommended series with RIG is crucial.
Hepatitis A Vaccine
Type: An inactivated (killed) virus vaccine. Whole virus particles are grown in cell culture, purified, and inactivated with formalin.
Indications: Active immunization against Hepatitis A infection, a common cause of acute viral hepatitis transmitted via the fecal-oral route. Recommended for: Travelers to high-risk areas, children as part of routine immunization schedules, laboratory workers, patients with chronic liver disease, individuals who use parenteral or illicit drugs, homosexual and bisexual men, individuals who work with nonhuman primates, people with clotting factor disorders, close contacts of adoptees from endemic countries, and individuals who change partners frequently.
Dose: Typically a two-dose series given by intramuscular injection. An initial dose (e.g., 0.5ml or 1.0ml depending on age and specific vaccine) is followed by a booster dose 6-12 months later (or up to 18 months for some vaccines). For combined Hepatitis A and B vaccine (Twinrix), the schedule is typically 3 doses over 6 months (0, 1, 6 months) or a rapid 4-dose schedule.
Side Effects: Common: Pain, tenderness, redness, and swelling at the injection site. Systemic: Headache, fever (low-grade), fatigue, malaise (general discomfort), myalgia (muscle aches). Less common: Nausea, loss of appetite, irritability, skin rash. Rare: Allergic reactions, including anaphylaxis.
Contraindications: Known hypersensitivity or severe allergic reaction to any component of the vaccine or a previous dose. Acute moderate to severe febrile illness (defer vaccination until recovery).
Precautions: Use with caution in patients with altered immunity; while generally safe, the immune response may be diminished. Pregnancy and lactation: Data on safety are limited, but the vaccine is considered safe, and vaccination should be considered if the risk of exposure to HAV is high.
Anti-D (Rho) Immunoglobulin
Type: This is a form of passive immunization, not a vaccine. It is a preparation of purified human immunoglobulin G (IgG) antibodies directed against the Rhesus D (RhD) antigen found on the surface of red blood cells. It works by destroying any Rh-positive fetal red blood cells that enter the Rh-negative mother's circulation before her immune system can produce its own antibodies.
Indications: To prevent a Rhesus-negative (Rh-negative) mother from forming her own anti-RhD antibodies when exposed to Rhesus-positive (Rh-positive) fetal red blood cells. This prevents Rh isoimmunization, which can cause severe Hemolytic Disease of the Newborn (HDN) or erythroblastosis fetalis in subsequent Rh-positive pregnancies. It is administered in Routine Antenatal Prophylaxis (RAP), Postnatal Prophylaxis, and following any potential sensitizing event (Abortion, Miscarriage, Ectopic pregnancy, Hydatidiform mole, Stillbirth, Amniocentesis, Chorionic villus sampling, Cordocentesis, External cephalic version, Abdominal trauma, Antepartum hemorrhage, or Transfusion of Rh-positive blood products).
Dose:
Antenatal Prophylaxis: Typically 300 mcg (1500 IU) IM around 28 weeks of gestation.
Postnatal Prophylaxis: Typically 300 mcg (1500 IU) IM within 72 hours of delivering an Rh-positive infant.
For sensitizing events earlier in pregnancy or with smaller potential bleeds, a lower dose (e.g., 50-120 mcg) may be used. For suspected or quantified large feto-maternal hemorrhage, additional doses may be required. One 300 mcg dose typically neutralizes 15 mL of Rh-positive red blood cells.
Side Effects: Common: Local tenderness, pain, swelling, and redness/stiffness at the injection site. Less common systemic effects: Low-grade fever, headache, malaise, nausea, vomiting, myalgia. Rare: Allergic reactions, including urticaria, rash, and very rarely, severe anaphylactic reactions. Extremely rare: Hemolysis (in the recipient).
Contraindications: Should NEVER be given to an Rh-positive individual. Should NEVER be given to the Rh-positive newborn infant. Contraindicated in individuals with a known severe allergy or hypersensitivity to human immunoglobulins or any component of the preparation. Contraindicated in individuals with isolated IgA deficiency with known anti-IgA antibodies. It is NOT indicated for an Rh-negative woman who has already been sensitized and has produced anti-RhD antibodies.
Drug Interactions: As Anti-D immunoglobulin is a preparation of antibodies, it can interfere with the immune response to live virus vaccines (e.g., MMR, Varicella, Oral Polio, Yellow Fever). Live attenuated vaccinations should generally be postponed for at least 3 months (and up to 6 months depending on the dose of immunoglobulin). Concomitant administration with other passive antibodies should be avoided unless specifically indicated.
Storage: Typically stored refrigerated at 2°C to 8°C (36°F to 46°F). Do not freeze. Protect from light.
Summary of Common Vaccines
Vaccine
Details
Measles–Rubella Vaccine
Available preparations: Injection powder for solution (live attenuated). Indications: Active immunization against measles and rubella. Dose: 0.5ml SC at 9 months and 18 months (left upper arm). Side effects: Fever, Headache and Malaise, Rashes and Thrombocytopenia. Contraindications: Hypersensitivity to any antibiotic present in the vaccine, Pregnancy, Immunosuppression.
Measles, Mumps and Rubella Vaccine (MMR vaccine)
Available brands: Trimovax®, Priovix®. Dose: By deep SC or by intramuscular injection 0.5ml (usually at 12-15 months). Indications: Active immunization against measles, mumps and rubella. Contraindications: Pregnancy, Hypersensitivity to components like neomycin, Immunosuppressed patients, Children who have received another live vaccine by injection within 4 weeks. Side effects: Fever and Malaise, Parotid swelling and Rashes. Precautions: History of convulsions.
BCG Vaccine
Available preparations: Powder for solution of live bacteria of strain derived from the bacillus of calmette and Guerin. Indications: Active immunization against tuberculosis. Dose: 0.05ml intradermal in the right upper arm to neonates; 0.1ml intradermal on the upper arm (children > 12 months). Side effects: Keloid, Lymphadenitis, Localized necrotic ulceration, Disseminated BCG infection in immunosuppressed patients, Anaphylaxis. Contraindications: Generalized oedema, Immunosuppressed patients, Antibacterial treatment. Precautions: Pregnancy, Eczema, Scabies. Vaccine site must be lesion free.
Diphtheria, Pertussis and Tetanus (DPT) Vaccine
Available brand: Tripacel®, Infantrix®. Indications: Active immunization against diphtheria, tetanus and pertussis. Dose: Infant: 0.5ml by intramuscular or deep SC injection at 6, 10 and 14 weeks. Side effects: Irritability and Limb swelling, Peripheral neuropathy, Urticaria, Fever, Restlessness and Malaise, Myalgia, Headache and Loss of appetite. Contraindications: Known hypersensitivity to any of the ingredients.
Tetanus Toxoid Vaccine
Available brand: Tetavax®. Indications: Active immunization against tetanus and neonatal tetanus. Dose: Women 15-49 years of age. 0.5ml deep SC or intramuscular injection. 5 doses (TT1-TT5) are required for lifelong protection. Side effects: Peripheral neuropathy.
Anti-tetanus Immunoglobulin
Available brand: Tetanea®. Indications: Passive immunization against tetanus as part of the management of tetanus prone wounds. Dose: Adult and Children: 1ml by IM injection. Side effects: Local reactions, Fever, Pain and tenderness at site of injection, Headache.
Yellow Fever Vaccine
Available brand: Stamaril®. Indications: Active immunization against yellow fever. Dose: Infant at 9 months: 0.5ml by SC injection. Side effects: Headache, Myalgia, Fever, Influenza like symptoms. Contraindications: Immunosuppressed patients, Hypersensitivity to any ingredient (including eggs), Infant under 4 months of age.
Typhoid Vaccine
Available brands: Typhim VI®, Typherix PFS®. Indications: Active immunization against typhoid. Dose: Adult and Children > 2 years: By deep SC or intramuscular 0.5ml with booster doses every 3 years for those at continued risk. Side effects: Headache, Nausea, Myalgia, Malaise. Contraindications: Immunosuppressed patients, Febrile illness, Hypersensitivity.
Pneumococcal Vaccine
Available brand: Pneumo 23® (Polysaccharide version). Indications: Immunization against pneumococcal infections in Sickle cell disease Children > 2 years of age, and immunocompromised patients > 5 years. Dose: Adults and Children > 2 years: 0.5ml deep SC or IM as a single dose. Side effects: Fever, Myalgia. Contraindication: Severe allergic reaction to any ingredients.
Meningococcal Vaccine
Available brand: Meningo A + C®, Mencevax ACWY®. Indications: Active immunization against Neisseria meningitidis infections. Dose: Adult and Children > 2 years of age. 0.5ml deep SC or IM injection as a single dose. Side effects: Allergic reaction, Anaphylaxis, Erythema. Contraindications: Known allergy, Febrile conditions.
Cholera Vaccine
Available brand: Dukoral® (Oral). Indications: Immunization for travellers > 2 years of age at high risk. Dose: Multiple oral doses given at intervals of at least 1-6 weeks. Side effects: Abdominal discomfort, Diarrhoea, Headache, Fever, Vomiting, Nausea, Loss of appetite. Contraindications: Hypersensitivity, Acute GIT or febrile illness.
Rabies Vaccine
Available brand: Verorab®. Indications: Pre-exposure prophylaxis and post-exposure treatment to prevent rabies. Dose: Pre-exposure: 1ml on days 0, 7 and 28. Post-exposure: 1ml on days 0, 3, 7, 14 and 30. Side effects: Pain/erythema at injection site, Nausea, Fever, Headache, Myalgia, Malaise.
Hepatitis B Vaccine
Available brand: Euvax B®, Engerix B®. Indications: Active immunization against Hepatitis B infection for all infants and high-risk persons. Dose: Infants: 0.5ml IM at 6, 10, 14 weeks. Adults: 1ml IM, 3 doses. Side effects: Abdominal pain, GIT disturbance, Peripheral neuropathy, Myalgia, Lymphadenopathy. Precautions: Immunocompromised patients may need further dose, Pregnancy, Lactation.
Hepatitis A Vaccine
Available brand: Avaxim®, Havrix®. Indications: Active immunization against Hepatitis A for high-risk groups. Dose: By IM injection, 0.5ml single dose with a booster 6-12 months later. Side effects: Headache, Fever, Malaise, Fatigue, Myalgia, Loss of appetite, Nausea. Contraindications: Severe febrile infections.
Anti-D (Rho) Immunoglobulin
Indications: Prevention of antibody formation to Rh-positive blood cells in Rh-negative mothers. Given following any sensitizing episode (birth of Rh+ infant, abortion, miscarriage). Dose: Varies by episode, typically 250-500mcg IM within 72 hours. Side effects: Fever, Nausea, Myalgia, Abdominal pain, Local tenderness and stiffness. Contraindications: Rhesus positive individuals, Isolated IgA deficiency.
THE UGANDA NATIONAL EXPANDED PROGRAMME ON IMMUNIZATION (UNEPI)
The Uganda National Expanded Programme on Immunization (UNEPI), officially launched in October 1993, was established to address critical challenges in immunization services. These included low immunization coverage, the use of non-potent vaccines, inadequate skills among health workers, limited community participation, and a lack of regular monitoring and evaluation. The re-launch of the program in 1997 marked a significant turning point, leading to great improvements in routine immunization coverage and a reduction in the incidence of Vaccine Preventable Diseases (VPDs) like measles.
UNEPI Strategic Objectives
The core objectives that guide UNEPI's work are:
To formulate and update national immunization policy, standards, and guidelines.
To ensure a consistent and reliable supply of potent and effective vaccines.
To increase both access to and demand for immunization services from the community.
To build technical and management capacity for the immunization program at all levels of the health system.
To continuously monitor disease trends and program performance to guide actions.
UNEPI Strategies
To achieve its objectives, UNEPI employs a multi-faceted approach:
Service Delivery: Providing routine immunization through the national health delivery system, including static (at the facility) and outreach services.
Logistics: Providing and maintaining an effective cold chain and logistics system at all levels.
Communication: Improving the communication skills of health workers to effectively engage with parents, leaders, and communities.
Supervision: Strengthening technical and administrative support supervision to ensure quality.
Training: Providing technical guidance for both pre-service training of health workers and continuous on-the-job training.
Partnerships: Strengthening partnerships with other child health programs, NGOs, civil society, religious organizations, and the private sector.
Advocacy & Social Mobilization: Enhancing public education and community involvement to increase vaccine uptake.
Injection Safety: Promoting and ensuring safe injection practices and proper waste management.
Surveillance: Maintaining a robust surveillance system for vaccine-preventable diseases using the Integrated Disease Surveillance and Response (IDSR) approach.
AEFI Management: Promoting the monitoring, investigation, and management of Adverse Events Following Immunization (AEFI).
Supplemental Activities: Carrying out mass vaccination campaigns (Supplemental Immunization Activities - SIAs) against targeted diseases as needed.
Innovation: Adopting internationally recommended approaches like Reaching Every District/Reaching Every Child (RED/REC) and developing strategies to reach hard-to-reach populations.
Disease Control Goals: Strengthening specific disease control measures, including for measles, maternal and neonatal tetanus elimination, and polio eradication.
Roles and Responsibilities in Immunization Service Delivery
Central Level (UNEPI and National Medical Stores)
UNEPI: Policy and guideline formulation, strategic planning, resource mobilization, technical support and supervision, capacity building, and national monitoring and evaluation.
National Medical Stores (NMS): Procurement, storage, and distribution of vaccines, injection materials, and other logistics to the district level.
District Level
Implementation of national policies and plans.
Forecasting, ordering, and storing vaccines and logistics.
Distribution of supplies to lower-level health facilities.
Cold chain maintenance and repair.
Support supervision and on-the-job training for health facility staff.
Monitoring performance data (e.g., coverage, dropout rates, vaccine wastage) for action.
Conducting active surveillance for diseases like Acute Flaccid Paralysis (AFP), Neonatal Tetanus (NNT), and measles.
Health Facility Level (The Frontline)
This is where nurses and midwives play their most direct role.
Providing daily immunization services (static and outreach).
Counseling and health-educating parents/caretakers.
Screening every child visiting the facility for their immunization status to reduce missed opportunities.
Estimating vaccine needs, ordering, and storing them correctly.
Maintaining the vaccine refrigerator temperature between +2°C and +8°C and recording it twice daily.
Monitoring and reporting performance data (coverage, wastage, dropouts).
Tracking defaulters through home visiting and community engagement.
Working with community mobilizers like Village Health Teams (VHTs).
Ensuring safe injection practices and proper disposal of sharps in a safety box.
Community Level (VHTs, Parents/Caregivers)
Taking children for all scheduled immunizations and ensuring completion.
Participating in planning for outreach services.
Mobilizing other parents and community members for immunization.
Keeping the child's health card safe and presenting it at every health facility visit.
Uganda Routine Immunization Schedule
Visit/Contact
When it is Given (Age)
Vaccine Given & Dose
Disease(s) Prevented
How it is Given (Route and Site)
1st
AT BIRTH (Within 24 hours is best)
Oral Polio Vaccine 0 (OPV0)
Polio
2 Drops in the mouth (Oral)
BCG
Tuberculosis (severe forms like TB meningitis)
0.05ml Injection on right upper arm (Intradermal)
Hepatitis B (Birth Dose)
Hepatitis B (prevents mother-to-child transmission)
Injection on left upper thigh (Intramuscular)
Injectable Polio Vaccine (IPV1)
Polio
Injection on right upper thigh (Intramuscular)
2nd
AT 6 WEEKS (One and a half months)
Pentavalent 1 (DPT-HepB-Hib 1)
Diphtheria, Pertussis (Whooping cough), Tetanus, Hepatitis B, Haemophilus influenzae type B
Injection on left upper thigh (Intramuscular)
Pneumococcal Conjugate Vaccine (PCV1)
Meningitis and Pneumonia (caused by S. pneumoniae)
Injection on right upper thigh (Intramuscular)
Rotavirus vaccine 1
Diarrhoea caused by Rotavirus
Slow release into the mouth (Oral)
Oral Polio Vaccine 2 (OPV2)
Polio
2 Drops in the mouth (Oral)
3rd
AT 10 WEEKS (Two and a half months)
Pentavalent 2 (DPT-HepB-Hib 2)
Diphtheria, Pertussis, Tetanus, Hepatitis B, Haemophilus influenzae type B
Injection on left upper thigh (Intramuscular)
Pneumococcal Conjugate Vaccine (PCV2)
Meningitis and Pneumonia
Injection on right upper thigh (Intramuscular)
Rotavirus vaccine 2
Diarrhoea caused by Rotavirus
Slow release into the mouth (Oral)
Injectable Polio Vaccine (IPV2)
Polio
Injection on right upper thigh (Intramuscular)
4th
AT 14 WEEKS (Three and a half months)
Pentavalent 3 (DPT-HepB-Hib 3)
Diphtheria, Pertussis, Tetanus, Hepatitis B, Haemophilus influenzae type B
Injection on left upper thigh (Intramuscular)
Pneumococcal Conjugate Vaccine (PCV3)
Meningitis and Pneumonia
Injection on right upper thigh (Intramuscular)
Rotavirus vaccine 3
Diarrhoea caused by Rotavirus
Slow release into the mouth (Oral)
5th
At 6 months
Malaria Vaccine 1
Malaria
Injection on right upper arm (Intramuscular)
6th
At 7 months
Malaria Vaccine 2
Malaria
Injection on right upper arm (Intramuscular)
7th
At 8 months
Malaria Vaccine 3
Malaria
Injection on right upper arm (Intramuscular)
8th
AT 9 MONTHS
Measles-Rubella vaccine 1
Measles, Rubella
Injection on left upper arm (Subcutaneous)
Yellow Fever vaccine
Yellow Fever
Injection on right upper arm (Subcutaneous)
9th
AT 18 MONTHS
Measles-Rubella vaccine 2
Measles, Rubella
Injection on left upper arm (Subcutaneous)
Malaria Vaccine 4
Malaria
Injection on right upper arm (Intramuscular)
Single dose
10 Year old girls
Human Papilloma Virus (HPV) Vaccine
Cancer of the cervix
Injection on the upper arm (Intramuscular)
TETANUS-DIPHTHERIA (Td) FOR WOMEN OF CHILDBEARING AGE (15-49 years)
Dose
When to Give
Vaccine
Disease Prevented
Route and Site
Td1
At first contact or as early as possible in pregnancy
Tetanus Diphtheria (Td) Vaccine
Tetanus, Diphtheria in the mother; Prevents Neonatal Tetanus in the baby
Injection on the upper arm (Intramuscular)
Td2
At least 1 month after Td1
Td3
At least 6 months after Td2
Td4
At least 1 year after Td3
Td5
At least 1 year after Td4
Vaccines and Practical Administration
Vaccines Used in the Immunization Schedule
BCG (Bacillus Calmette-Guérin) Vaccine: This is a live attenuated (weakened) bacterial vaccine. It is used in the immunization program to protect the child against tuberculosis. BCG is given in a single dose at birth or first contact. The vaccine is very sensitive to light and loses much of its potency when exposed to light. It is given by injecting the child in the skin (intradermally) at the right upper arm. The amount of 0.05 ml is recommended for children up to eleven (11) months of age, and 0.1 ml for children after eleven years.
Polio Vaccine: Polio vaccine is a live attenuated virus vaccine used in the immunization program to protect the child against poliomyelitis. The Sabin type is given orally (by mouth) in Uganda. Some countries use another type called Salk vaccine, which is given by injection. Oral polio vaccine is given four times beginning: at birth (polio 0); at 6 weeks polio 1; at 10 weeks polio 2, and at 14 weeks polio 3 respectively. 2 drops in the mouth are recommended for each dose. It should be noted that booster doses are sometimes given to all children below five years of age in the entire country regardless of immunization status. This is done during national immunization days (NIDs), whose primary objective is to eradicate poliomyelitis. It is nice to remember that polio vaccine is made up of three polio viruses, and the oral polio vaccine is given four times to enable each of three viruses to stimulate the production of antibodies.
Pentavalent Vaccine: Pentavalent vaccine has 5 vaccines which include DPT and Hep.b & Hib. The DPT vaccine is commonly referred to as a triple vaccine because it is used to prevent three diseases, namely diphtheria, pertussis, and tetanus. The diphtheria and tetanus parts of the vaccine are made from the respective toxins, while the pertussis vaccine is made of killed bacterial antigen. It has become necessary to add hepatitis B and haemophylus influenza type b vaccines to DPT to form what is now known as the Pentavalent vaccine (five vaccines). These are given three times because they do not stimulate the body to produce antibodies as well as the live attenuated vaccines. When the second and the third dose are given, the body’s memory of the earlier dose quickly leads to the production of more antibodies. The Pentavalent vaccine is given by injecting the child intramuscularly (in the muscle) at the left upper thigh. It is given three times beginning: at 6 weeks, at 10 weeks, and at 14 weeks, respectively. A dose of 0.5 ml is recommended each time given.
Tetanus Toxoid Vaccine: This is a toxoid vaccine used in the immunization program to prevent children against neonatal tetanus. UNEPI targets all women of childbearing age (15-49 years) and pregnant mothers for tetanus toxoid (TT) vaccination. It is better and safe to give two doses of TT vaccine to any pregnant woman if you are not sure she has had TT in a previous pregnancy. The aim is to use the TT vaccine to provide passive immunity for unborn babies, through the transfer of the mother’s antibodies. This type of immunity reduces with time and is normally boosted by giving the child Pentavalent vaccines at 6 weeks after birth.
Pneumococcal Conjugate Vaccine (PCV 10): PCV 10 consists of sugars (polysaccharides) from the capsule of the bacterium streptococcus pneumonia, which are conjugated to a carrier protein. The PCV 10 contains serotypes 1, 4, 5, 6B, 7F, 9V, 14, 18C, 19F, and 23F. It is highly effective and protects children younger than 2 years of age against severe forms of pneumococcal disease, such as meningitis, pneumonia, and bacteremia. It will not protect against these conditions if they are caused by agents other than pneumococcus or pneumococcal serotypes not present in the vaccine. The World Health Organization and Ministry of Health recommend that infants be given three doses of PCV vaccine, at 6 weeks, 10 weeks, and 14 weeks. PCV should be integrated with DPT-HepB-Hib vaccination.
Rotavirus Vaccine: Rotavirus vaccine is a vaccine used to protect against rotavirus infections. These viruses are the leading cause of severe diarrhea among young children. The vaccines are safe. This includes their use in people with HIV/AIDS. The vaccines are made from weakened rotavirus. The World Health Organization recommends the first dose of vaccine be given right after 6 weeks of age. Two or three doses more than a month apart should be given, depending on the vaccine administered. The vaccine is not recommended for use in children over two years of age.
Malaria Vaccine (RTS,S/AS01): The malaria vaccine, known by its brand name Mosquirix™, is a landmark achievement in public health. It is a recombinant protein-based vaccine that targets the Plasmodium falciparum parasite, the most deadly species causing malaria in Africa. It works by preventing the parasite from infecting the liver and maturing, thus stopping the disease before it can cause symptoms. It is given in a four-dose schedule starting at 6 months of age, with subsequent doses at 7, 8, and 18 months. It is administered as an intramuscular injection in the upper arm.
Human Papillomavirus (HPV) Vaccine: The HPV vaccine is a crucial tool for cancer prevention. It is a recombinant vaccine that protects against specific high-risk types of HPV that are responsible for the vast majority of cervical cancer cases. In Uganda, it is targeted at 10-year-old girls before they are likely to be exposed to the virus through sexual activity. Providing the vaccine at this age ensures the strongest possible immune response. It is administered as an injection in the upper arm.
Administration of Vaccines: General Principles
Immunization coverage should be high to reduce disease transmission. As health workers, we should aim to achieve immunization coverage of over 80%. All children should be immunized at every opportunity. There is no contraindication for immunization. If immunization is done daily, this improves immunization coverage.
Children with minor illnesses should be immunized. The misconception that sick children should not be immunized should be discarded. Very sick children admitted to the hospital should be immunized on discharge. Malnourished children should also be immunized. The danger of vaccine of any given type to the malnourished child is much less than the infection itself.
For children with HIV/AIDS, BCG can spread rapidly and thus should be treated as an opportunistic infection.
Administering Vaccines: Practical Steps
Preparing Vaccines
Vaccines used in the immunization program are in different forms. Some vaccines are in powder form and must be dissolved in the diluent supplied with them, while others come in liquid form and will not need a diluent. There is a need to prepare the vaccine before immunization.
Preparing Polio Vaccine: To prepare this vaccine the following should be done: If a dropper is separate, attach it securely to the vial (bottle). Keep polio vaccine shaded from sunlight during the immunization session. Place the vial on a frozen icepack or place it in the sponge hole placed at the mouth of the vaccine carrier, which is provided for this purpose to maintain the temperature.
Preparing BCG and Measles Vaccines: The following should be done: Use the diluent provided for each vaccine. The diluent should be cold, +4°C – +8°C. Use different 9 ml syringes for mixing measles and BCG vaccines. Draw up the full required amount of the diluent provided as per instruction on the vial. Draw and expel mixture back into the bottle three times or until the vaccine is mixed. Do not shake the vial. BCG and measles vaccines should be placed on a frozen icepack or use the sponge in the vaccine carrier for maintaining the correct temperature. Draw 0.5 ml of measles vaccine (recommended dosage). Draw 0.05 ml of BCG vaccine for babies up to 11 months old and 0.1 ml for babies above 11 months of age (recommended dose).
Preparing DPT and TT: DPT and TT come in liquid form. You will not need to dissolve or mix them. Remove the metal top from the vial. Draw 0.5 ml into the sterile syringe. Remove bubbles. Keep the vaccine shaded from the light.
Preparing PCV 10: Ensure availability of a clean vaccine carrier and a sponge. The vaccine carrier should be able to close tightly. Condition icepacks prior to packing vaccines in a vaccine carrier to prevent freezing of PCV, TT, and DPT-Hep B-Hib. On a table with a plastic sheet: – Vaccines, diluent, and droppers – Thermometer – Cotton swab in a clean container – Clean water in a clean container for cleaning injection sites – A tin of vitamin A and a pair of scissors – AD syringe and needles – Child health cards – Child register.
Important Points to Remember Before Administering
Never take two vials of the same vaccine out of the vaccine carrier at the same time.
Do not mix vaccines until mothers and children are present.
Mix one vial of a particular vaccine at a time.
Keep opened vials of polio, measles, and BCG vaccines on a frozen icepack or use the sponge in the vaccine carrier. Their temperature must be carefully maintained.
Do not keep vials of DPT and TT vaccines directly on the frozen icepack.
Open the vaccine carrier when necessary.
NEVER SHAKE VACCINE VIALS!!!
After preparing vaccines, the next step is to administer them. Before administering vaccines, you should always remember the following important points:
Use one sterile syringe and needle per vaccine (antigen) per child or mother.
Avoid holding loaded syringes in your hand for long to avoid exposing the vaccine to heat or direct sunlight.
Inform each parent what type of vaccine you are giving the child, the possible reactions to it, what to do about the reactions, and when to bring the child back for more immunization.
Listen to parents and encourage questions.
Remove any child’s clothes that are in your way when vaccinating.
During immunization, ask the mother to hold the child firmly to restrict their movement during immunization.
Administer the vaccine.
Give specific health information about each vaccine.
Administration Techniques
Administering BCG:
Clean the skin with cotton wool soaked in clean water and let it dry.
Hold the middle of the child’s upper right arm firmly with your left hand.
Hold the syringe by the barrel with the millimeter scale upward and the needle pointing in the direction of the child’s shoulder. Do not touch the plunger.
Point the needle against the skin, barrel turned up about 3 cm above the thumb. Gently insert its tip into the upper layer of the skin (intradermally).
Make sure that the needle is in the skin (intradermally) and not under the skin. If the needle goes under the skin, take it out and insert it again. If you bend the needle, replace it with another sterile one.
Holding the barrel with your index and middle finger, put your thumb on the plunger.
Holding the syringe flat (parallel to the surface of the skin), inject the vaccine intradermally.
If the vaccine is injected correctly into the skin, a wheal, with the surface pitted like an orange peel, will appear at the injection site. An indication that the vaccine has been injected incorrectly is that the plunger will move much more easily when the needle is injected under the skin than when it is injected in the skin. If there is no local reaction, re-immunize the child.
Give the mother health information about BCG, i.e., in 7-9 days, a small sore will appear at the site where the injection was given. The sore might ooze a bit and will last for 6-8 weeks. Keep the baby’s arm clean with soap and water. Do not put dressing or medicine on the sore. The sore will not hurt and it will heal by itself.
Change the syringe and needle after each vaccine and each child.
Fill in the immunization tally sheet in the BCG section.
Administer the next vaccine.
Administering DPT Vaccine:
Ask the mother to hold the child across her laps so that the front of the child’s thigh is facing upwards. Then ask her to hold the child’s legs from moving.
Clean the site to be injected with a cotton swab moistened in clean water and let it dry.
Place your thumb and index finger on each side of the place you intend to inject. Stretch the skin slightly.
Quickly push the needle deeply into the muscle (intramuscular). Pull the plunger back; if there is blood in the syringe, withdraw the needle and discard the vaccine. Obtain a sterile syringe with a needle and new vaccine.
If no blood appears in the syringe, inject 0.5 ml of vaccine.
Withdraw the needle.
Rub the injection spot quickly with a clean piece of cotton swab.
Give health advice about DPT. Tell the mother that: DPT may cause some tenderness at the site which will go away after a few days, and may cause fever but it will subside in 24 hours.
Fill the immunization tally sheet appropriately.
Use another needle and syringe to vaccinate another child.
Administering PCV Vaccine:
Explain to the mother that the child is going to be given two types of vaccines in the form of injections. One will be given in the right and the other in the left thigh.
Explain to the parent the disease prevented by the vaccine, the number of doses in order to achieve the protection, and reassure her that there is no danger in giving two injections in one visit.
Explain to the mother the likely side effects and how to manage them, then wash hands with soap and water, drip dry.
Open the vaccine carrier and pick one vial of PCV and quickly check the expiry date and status of the vial.
Observe the vial content for unusual appearance and particles. If either is observed, the vial must be discarded.
Shake the vaccine vial gently to obtain a uniform solution.
Draw 0.5 ml of the vaccine from the vial using an AD syringe and return the partially used vial in a sponge in a vaccine carrier.
Instruct the mother on how to hold the child for vaccine administration.
Clean the right upper outer thigh with a swab soaked in water and administer the vaccine intramuscularly.
Press the injection site firmly for a few seconds. Do not massage.
Dispose of the used syringe and needle immediately into the safety box. Do not put swabs in the safety box. Do not recap the needle.
If a vial is opened for one child and another child is not immediately available to be vaccinated with the remaining vaccine dose in the vial, write on the vial the time it was opened and ensure that the vial is kept cool in the sponge pad and away from any potential contamination for 6 hours.
Administering Oral Polio:
Ask the child’s mother whether the child has diarrhea. If yes, note this on the child’s card and tell the mother that this dose of polio needs to be repeated after one month. This child with diarrhea should have a total of 4-9 doses of polio vaccine depending on whether the child got polio 0 or not.
Use the dropper or device supplied with the vaccine.
If the child will not open the mouth, gently squeeze his/her cheeks to open his mouth.
Put 2 drops of vaccine on the child’s tongue.
Fill in the immunization tally sheet appropriately.
Note that every child below 5 years of age should receive an extra 2 doses of oral polio vaccine (OPV) each year during national immunization days (NIDs), whether she/he was immunized before or not.
Administering Measles:
Use a sterile syringe and needle for each injection. Draw 0.5 ml dose of mixed measles vaccine.
Ask the mother to expose the child’s left outer upper arm and hold the child firmly to restrict their movement.
Clean the injection site with a cotton swab soaked in clean water and let it dry.
With the fingers of one hand, pinch the skin on the outer side of the upper arm.
Hold the syringe at an acute angle to the child’s arm. Inject the vaccine subcutaneously.
To avoid injecting the vaccine into a vein, withdraw the plunger slightly before injecting the vaccine. Never give the vaccine if blood is seen in the syringe.
Press the plunger gently, inject 0.5 ml of vaccine.
Withdraw the needle. If a drop of blood appears at the injection site, ask the mother to wipe it away with a piece of cotton wool.
If blood is drawn back in the syringe, the vaccine should not be given. Use another needle and syringe to obtain new vaccine.
Record the immunization in the immunization tally sheet.
Administering TT Vaccine:
Pregnant mothers should be given two doses of TT vaccine (0.5 ml) a month apart. However, if it is not possible to establish whether the mother had previously been immunized with TT or whether the mother was a default from a previous dose, two doses should be given a month apart.
Use a sterile syringe and needle for each injection.
Clean the thigh with cotton wool moistened in clean water.
Hold the thigh muscle between your thumb and forefinger.
With your other hand, inject the vaccine intramuscularly.
Withdraw the needle.
Discard the needle and syringe into a safety box. Ensure you do not put swabs in the safety box. Safety boxes are collected and burned.
Fill the immunization tally sheet.
Equipment/Logistics Needed for Safe Vaccination
A well-prepared immunization session requires specific equipment to ensure vaccines are kept potent and administered safely.
Vaccine Carrier with Conditioned Ice Packs: A portable, insulated container to maintain the cold chain during an immunization session.
Foam Pad/Sponge: A slotted sponge placed in the top of the vaccine carrier to hold opened multi-dose vials and protect them from heat and direct sunlight.
Vaccines and their specific Diluents: The correct vaccines and diluents for the session.
Syringes and Needles: Including single-use Auto-Disable (AD) syringes and separate mixing syringes.
Safety Box (Sharps Container): A puncture-proof container for the immediate and safe disposal of used needles and syringes.
Cleaning Supplies: Cotton swabs and a bottle of clean water for cleaning injection sites.
Documentation Tools: Child health cards, immunization register, and tally sheets.
Supplemental Supplies: Vitamin A capsules and a pair of scissors to open the blister packs.
Cold Boxes and Ice Packs: Larger insulated containers used for transporting vaccines from a district store to a health facility.
Post-Vaccination Counselling and Health Education
Communication with the parent or caregiver after vaccination is a critical nursing role. It builds trust and ensures proper follow-up care.
Reassure parents of the vaccine's safety and explain the common, minor side effects, such as swelling and redness at the injection site, slight fever, or soreness.
Advise parents on how to manage these side effects (e.g., giving paracetamol for fever).
Offer integrated health education on topics like nutrition, hygiene, and the importance of breastfeeding.
Always ask mothers if they have any concerns and take the time to answer their questions respectfully.
Clearly inform the mother about the date of the next visit required for immunization.
Administer Vitamin A supplementation to children according to the national schedule (e.g., at 6 months and 12-59 months). If a child receives their first measles dose at 6 months, inform the mother the second dose is due at 18 months.
Record Keeping: The Foundation of Program Monitoring
Accurate record keeping is mandatory for the immunization program. All vaccines administered must be recorded in tally sheets and registers to monitor performance, check a child's immunization status, calculate coverage rates, and plan for future needs.
The Immunization Register
The register must be clearly labeled with the name of the health facility.
It should include the names of the children (not parents), their date of birth, and their medical file/card number.
For each vaccine (BCG, Polio, Pentavalent, Measles, etc.), enter the date the dose was given. If a dose was missed or not given, it should be clearly indicated, often with a zero (0).
Note: Supplemental doses like extra OPV or Vitamin A given during campaigns are typically recorded on the child's health card, not in the main immunization register.
Health Cards
Each child must have their own health card.
The card must contain essential identifying information: child’s name, mother’s name, date of birth, village, and the primary health unit.
It serves as the child's personal record of all vaccines received, including dates. Other health information, like Vitamin A administration, is also recorded here.
Always ensure the child’s card is up-to-date before administering any vaccine.
The Refrigerator and Cold Chain Management
The Vaccine Refrigerator
The refrigerator is the most critical piece of equipment for storing vaccines at the health facility. It must be properly maintained and kept in good working condition at all times. All refrigerators must be maintained at a temperature between +2°C and +8°C.
Types of Refrigerators Used in Immunization:
Solar direct drive (SDD) vaccine refrigerator.
Gas refrigerators (using Kerosene or paraffin).
Electric vaccine refrigerator.
The refrigerator should also be able to freeze ice packs. These ice packs are used to keep vaccines cool in vaccine carriers during outreach sessions. Ice packs inside a vaccine carrier are referred to as Conditioned Icepacks.
Preventive Maintenance and Repair
All refrigerators should be serviced and maintained regularly (e.g., every 3 months). During maintenance, the following activities are done:
The refrigerator is cleaned thoroughly.
The thermostat setting is checked for accuracy.
The defrosting system is checked.
The cooling system and compressor are checked and cleaned.
The electrical connection or gas/kerosene system is checked.
Managing Adverse Events Following Immunization (AEFI)
An AEFI is any untoward medical occurrence which follows immunization and does not necessarily have a causal relationship with the use of the vaccine. It is important to respond appropriately to any AEFI.
Fever: Advise parents to give the child paracetamol (acetaminophen) in the correct dose for their weight. Do not give aspirin to children. Encourage plenty of fluids.
Swelling or Redness at the Site of Injection: This is usually a normal, mild reaction. Reassure the parent it will go away on its own. Do not give any drug or apply any substance to the site.
Swelling of the Limbs or Face, or Difficulty in Breathing: This is a sign of a potential severe allergic reaction and is a medical emergency. Do not give any drug. Advise the parent to seek medical attention at the nearest health facility immediately.
Loss of Weight, Generalized Body Swelling, Poor Feeding, or Coughing: These are unlikely to be side effects of vaccination and are more likely symptoms of an underlying condition like malnutrition or another illness. Refer the child to the health facility for assessment and treatment.
Diarrhea: This is most likely not related to vaccination. Ensure the child receives oral rehydration solution (ORS) or other appropriate fluids to prevent dehydration.
Conducting Mass Vaccination Campaigns
Mass vaccination campaigns, such as National Immunization Days (NIDs) or outbreak responses, require careful planning and execution.
Planning and Training: Plan the campaign, identify target populations, and train healthcare workers on all procedures.
Community Mobilization: Inform communities well in advance about the campaign's purpose, date, and location.
Logistics: Ensure all necessary equipment (vaccines, syringes, safety boxes, cold chain equipment) is in place.
Safety Measures: Implement infection control, safe waste disposal, and crowd control measures at vaccination sites.
Vaccination Site Setup: Organize sites for an efficient flow of people from registration to vaccination to a post-vaccination observation area.
Vaccine Administration: Follow standard procedures, ensuring one sterile syringe and needle per injection.
Monitoring and Reporting: Monitor the campaign’s progress, track doses administered, and ensure AEFIs are reported and managed promptly.
Documentation: Maintain detailed records of all vaccines administered, including tallies and vaccine wastage.
Post-Campaign Evaluation: Evaluate the campaign’s success and identify areas for improvement.
Follow-Up: After the campaign, ensure routine immunization services continue and that children receive follow-up doses as needed.
Quick Quiz
Immunization Quiz
Pharmacology
Privacy: Your details are used only for quiz tracking and certificates.
Pathogens are foreign disease-causing substances, such as bacteria and viruses, and people are exposed to them every day.
Antigens are attached to the surface of pathogens and stimulate an immune response in the body.
An immune response is the body’s defense system to fight against antigens and protect the body.
Immunity is the body's ability to resist infection and disease. It is a state of having sufficient biological defenses to avoid invasion by pathogens and to destroy foreign substances.
Immunology is the scientific study of this complex system and how it responds to challenges.
Terminology in Immunology
Pathogen: A foreign, disease-causing microorganism, such as a bacterium, virus, fungus, or parasite.
Antigen (Ag): Any substance, usually a protein or polysaccharide on the surface of a pathogen, that is recognized as "foreign" by the immune system and provokes an immune response. Think of antigens as the "uniforms" that identify an invader.
Antibody (Ab) or Immunoglobulin (Ig): A highly specific protein produced by plasma cells (a type of B-lymphocyte) in response to a specific antigen. Antibodies bind to antigens to neutralize them or mark them for destruction.
Immunogen: Any antigen that is capable of inducing a humoral (antibody) and/or cell-mediated immune response. All immunogens are antigens, but not all antigens are immunogens (some are too small or simple to provoke a response on their own).
Hapten: A small molecule that can only provoke an immune response when it is attached to a larger carrier protein. On its own, it is an antigen but not an immunogen.
Chemotaxis: The chemical attraction of phagocytic cells (like neutrophils and macrophages) to a site of injury or infection. They follow a chemical trail of substances called chemokines.
Chemokines: A family of small proteins that act as chemical messengers, stimulating the movement of leukocytes (white blood cells) towards the source of inflammation.
Types of immunity
The immune system is broadly divided into two interconnected branches:
Innate (Non-specific) Immunity: The body's general, inborn protection against all invaders. It acts immediately or within hours and does not have immunological memory. It includes physical barriers and general immune cells.
Adaptive (Acquired/Specific) Immunity: A highly specific defense system that is "acquired" during life after exposure to a pathogen or vaccine. It is characterized by specificity for a particular pathogen and immunological memory, allowing for a much stronger response upon re-exposure.
1. Innate Immunity: The First and Second Lines of Defense
Innate immunity is our built-in defense system. It is non-specific, meaning it responds in the same way to all pathogens, and it does not "remember" previous encounters.
Types of innate immunity
First line of defenses: These barriers are designed to prevent pathogens from entering the body in the first place.
Second line of defenses: If pathogens breach the first line of defense, they encounter a range of non-specific internal defenses.
First Line of Defense: External or Physical and Chemical Barriers
These barriers are designed to prevent pathogens from entering the body in the first place.
Skin: The unbroken epidermis, with its tough outer layer of keratin (stratum corneum), is a formidable physical barrier. Sebum (skin oil) contains fatty acids that create an acidic environment hostile to many bacteria.
Mucous Membranes: These line the respiratory, digestive, urinary, and reproductive tracts. They produce mucus, which traps microbes.
Ciliary Escalator: The ciliated epithelium of the upper respiratory tract constantly sweeps mucus (with trapped dust and pathogens) up towards the pharynx, where it is swallowed and destroyed in the stomach.
Bodily Fluids and Washing Actions:
Tears (Lacrimal Apparatus): Constantly wash the surface of the eye to dilute and remove microbes. Blinking spreads tears over the surface of the eyeball, and the continual washing action of tears helps to dilute microbes and keep them from settling on the surface of the eye. Tears also contain lysozyme, an enzyme capable of breaking down the cell walls of certain bacteria.
Saliva: Washes microbes from the teeth and mouth.
Urine Flow: The one-way flow of urine through the urethra mechanically flushes out microbes, preventing ascending infections.
Vaginal Secretions: Move microbes out of the female reproductive tract.
Chemical Barriers:
Acidity: The low pH of skin (3-5), gastric juice (1.2-3.0), and vaginal secretions discourages the growth of most microbes.
Lysozyme: An enzyme found in tears, saliva, nasal secretions, and perspiration that can break down the peptidoglycan cell walls of bacteria.
Expulsion Mechanisms: Defecation and vomiting also expel microbes. For example, in response to some microbial toxins, the smooth muscle of the lower gastrointestinal tract contracts vigorously; the resulting diarrhea rapidly expels many of the microbes.
Second Line of Defense: Internal Defenses
When pathogens penetrate the physical and chemical barriers of the skin and mucous membranes, they encounter a second line of defense which include the following:
1. Internal Antimicrobial Substances
Interferons (IFNs): Proteins produced by virus-infected cells. They don't save the infected cell, but they signal to neighboring uninfected cells to produce antiviral proteins, helping to limit the spread of the virus.
Complement System: A group of over 20 plasma proteins that circulate in an inactive state. When activated (e.g., by an antigen-antibody complex), they "complement" the immune response by:
Causing lysis (bursting) of microbial cells.
Stimulating inflammation.
Enhancing phagocytosis by coating pathogens (a process called opsonization).
Iron-Binding Proteins: Proteins like transferrin (in blood), lactoferrin (in milk, saliva), and ferritin (in liver) bind to iron, making it unavailable for bacteria that need it for growth.
Antimicrobial Proteins (AMPs): Short peptides that have broad-spectrum antimicrobial activity, directly damaging microbial membranes. Examples include defensins and dermicidin.
2. Defensive Cells
Phagocytes ("Eating Cells"): These cells engulf and digest pathogens and cellular debris.
Neutrophils: The most abundant type of white blood cell. They are the "first responders" that rapidly move to sites of infection to perform phagocytosis.
Macrophages ("Big Eaters"): Develop from monocytes. Fixed macrophages reside in specific tissues (e.g., in the liver, lungs), while wandering macrophages roam through tissues. They are powerful phagocytes and also act as Antigen-Presenting Cells (APCs).
Dendritic Cells: Also phagocytes and potent APCs, found in skin and mucous membranes.
Natural Killer (NK) Cells: A type of lymphocyte that performs immunological surveillance. They are unique because they can detect and kill abnormal body cells (like tumor cells and virus-infected cells) without needing to be activated by a specific antigen.
Basophils and Mast Cells: Release inflammatory chemicals like histamine and heparin. Basophils circulate in the blood, while mast cells are fixed in tissues. They are key players in inflammation and allergic reactions.
Eosinophils: Specialize in fighting parasitic worm infections and are also involved in allergic reactions.
3. Inflammation: The Body's Emergency Response
Inflammation is the physiological response to tissue damage. Its purpose is protective: to isolate the problem, inactivate and remove the causative agent and damaged tissue, and initiate repair.
The Cardinal Signs of Inflammation:
Redness (Rubor): Caused by vasodilation (widening) of arterioles and capillaries in the damaged area, which increases blood flow. This is triggered by chemical mediators like histamine.
Heat (Calor): Results from the increased blood flow. The localized increase in temperature can inhibit microbial growth and enhance the activity of immune cells.
Swelling (Tumor): Caused by increased capillary permeability. Fluid (exudate) and plasma proteins leak from the blood into the interstitial spaces, leading to edema.
Pain (Dolor): Results from the compression of sensory nerve endings by the swelling and from irritation by chemical mediators like bradykinin and prostaglandins.
Loss of Function (Functio Laesa): The combination of swelling and pain may temporarily limit movement of the affected area, which helps protect it from further injury.
4. Immulogical surveillance
Natural killer (NK cells) cells: are leukocytes that attack and destroy tumor cells, or cells that have been infected by viruses
Although they are lymphocytes, they are much less selective about their targets than the other T-cells & B-cells.
2. Adaptive Immunity
Adaptive immunity is a highly specific, powerful defense system that develops throughout our lifetime. It is "acquired" after exposure to a pathogen or vaccine. Its two defining characteristics are specificity (it targets one particular antigen) and memory (it "remembers" past encounters, leading to a much faster and stronger response upon re-exposure).
Lymphocytes
The Cells of Adaptive Immunity
B-lymphocytes (B-cells) and T-lymphocytes (T-cells) are the major players. Both originate from stem cells in the bone marrow but mature in different locations.
T-Cells and Cell-Mediated Immunity
T-cells are responsible for cell-mediated immunity, which is crucial for fighting intracellular pathogens (like viruses and some bacteria) and eliminating abnormal body cells (like cancer cells). They mature in the Thymus gland.
Antigen Recognition: T-cells cannot recognize whole antigens. They can only "see" small fragments of an antigen that have been processed and displayed on the surface of an Antigen-Presenting Cell (APC) like a macrophage or dendritic cell.
Clonal Expansion: When a T-cell recognizes its specific antigen presented by an APC, it becomes activated and begins to rapidly divide, creating a large clone of identical cells programmed against that antigen.
Types of T-Cells:
Helper T-Cells (TH or CD4+ cells): The "generals" of the immune system. When activated, they produce chemical messengers called cytokines that coordinate the entire immune response. They help activate cytotoxic T-cells, B-cells, and macrophages. HIV specifically targets and destroys these cells, crippling the immune system.
Cytotoxic T-Cells (TC or CD8+ cells): The "soldiers." They directly track down and kill any body cells displaying the specific antigen they recognize (e.g., virus-infected cells, tumor cells) by releasing powerful toxins.
Suppressor (Regulatory) T-Cells (Treg): These cells turn off the immune response after the pathogen has been cleared, preventing excessive and potentially damaging immune activity.
Memory T-Cells: Long-lived cells that persist after the infection is resolved, ready to mount a swift response upon re-exposure to the same antigen.
B-Cells and Humoral (Antibody-Mediated) Immunity
B-cells are responsible for humoral immunity, which involves the production of antibodies that circulate in the body's fluids ("humors" like blood and lymph). This is most effective against extracellular pathogens like bacteria circulating in the blood. B-cells are produced and mature in the Bone marrow.
Antigen Recognition: B-cells can recognize and bind to whole, unprocessed antigens.
Activation and Clonal Expansion: Once a B-cell binds to its specific antigen, it typically requires a confirmation signal from a helper T-cell to become fully activated. It then enlarges and divides into a clone of two cell types:
Plasma Cells: These are "antibody factories." They dedicate all their energy to producing and secreting thousands of antibody molecules per second into the bloodstream. These antibodies are specific to the antigen that initiated the response.
Memory B-Cells: Long-lived cells that provide immunological memory, enabling a rapid and massive antibody production (the secondary response) if the same antigen is encountered again.
Types of Adaptive Immunity
Acquired (adaptive) immunity develops during an individual's lifetime. It can be classified into two major categories—Active and Passive—each of which can be acquired either naturally or artificially.
Active Immunity: The Body's Own Production Line
Active immunity is protection that is induced in the host itself after exposure to an antigen. The individual's own immune system is stimulated to produce memory B-cells and T-cells. This process takes time to develop but results in long-lasting, sometimes lifelong, immunological memory.
1. Naturally Acquired Active Immunity
Mechanism: This is the most natural way to become immune. It occurs when a person is exposed to a live pathogen through an infection (which may be a full-blown illness or a subclinical infection without symptoms).
The Process: Upon first exposure, the body mounts a primary immune response. It manufactures specific antibodies and T-cells to fight the invading pathogen. While this initial response takes time (often allowing the person to get sick), it results in the creation of a large pool of memory cells.
Outcome: For the rest of that individual's life, any subsequent exposure to the same pathogen will trigger a rapid and powerful secondary immune response. The memory cells will mobilize to produce antibodies and T-cells so quickly that the invading antigen is destroyed before it can cause disease.
Clinical Example: A child who gets sick with and recovers from chickenpox develops naturally acquired active immunity. They are protected from getting chickenpox again for the rest of their life.
2. Artificially Acquired Active Immunity
Mechanism: This type of immunity is acquired through the deliberate action of vaccination (immunization). An individual is intentionally given a prepared antigen.
The Process: The vaccine contains a safe form of the antigen—it might be a killed pathogen, a live attenuated (weakened) pathogen, a subunit (a piece of the pathogen), or a toxoid (an inactivated toxin). This antigen is enough to stimulate the recipient's immune system to produce its own antibodies and memory cells, but it does not cause the actual disease.
Outcome: The individual develops long-term immunity without ever having to suffer through the illness. Sometimes, a person might experience minor symptoms like a low-grade fever or soreness after a vaccine; this is a sign that their immune system is actively learning to fight the antigen.
Clinical Example: A baby receiving the Measles, Mumps, and Rubella (MMR) vaccine. The vaccine contains live attenuated viruses, which stimulate the baby's immune system to create memory cells against all three diseases, providing long-term protection.
Passive Immunity: Borrowed Protection
Passive immunity is protection that is acquired through the transfer of pre-formed antibodies from an immune individual to a non-immune individual. The recipient's body does not produce the antibodies itself. This provides immediate protection but is always temporary because the "borrowed" antibodies are eventually broken down and eliminated, and no immunological memory is created.
1. Naturally Acquired Passive Immunity
Mechanism: This occurs naturally from mother to child. It is nature's way of protecting a newborn while its own immune system is still immature.
The Process:
During Pregnancy: IgG antibodies are actively transported across the placenta from the mother's bloodstream to the fetus, especially during the last one to two months of pregnancy. A full-term infant is born with the same set of IgG antibodies as its mother.
After Birth: IgA antibodies (secretory IgA) are transferred from the mother to the infant through breast milk (especially the colostrum). This IgA protects the baby's gastrointestinal tract from infections.
Outcome: The antibodies protect the infant from specific diseases that the mother is immune to. This protection is crucial but temporary, typically lasting for the first 6-12 months of life, until the maternal antibodies wane and the infant's own immune system begins to produce its own antibodies.
Clinical Relevance: This is why the timing of infant vaccinations is so important—they are scheduled to begin as the mother's protective antibodies start to disappear.
2. Artificially Acquired Passive Immunity
Mechanism: This involves injecting a person with ready-made antibodies (immunoglobulins or antiserum) that were produced in another human or an animal (like a horse).
The Process: This is used when a person needs immediate protection from a fast-acting toxin or pathogen and there is no time to wait for their own active immune response to develop.
It can be used prophylactically (to prevent disease) in individuals who have been exposed to an infection they are not immune to.
It can be used therapeutically (to treat a disease) after symptoms have already developed, to help neutralize a toxin or pathogen.
Outcome: Provides immediate but short-lived protection. There is no memory formation. There is also a potential risk of a hypersensitivity reaction (like serum sickness) if the antibodies come from a non-human source.
Clinical Examples:
Giving Tetanus Immunoglobulin (TIG) to a person with a deep, contaminated wound who has an uncertain vaccination history.
Giving Rabies Immunoglobulin (RIG) infiltrated around a wound from a suspected rabid animal bite.
Giving pooled human immunoglobulin (IVIG) to treat immunodeficiency diseases like hypogammaglobulinemia.
Summary of Acquired Immunity
Type of Immunity
How It Is Acquired
Memory Produced?
Duration
Example
Naturally Acquired Active
Surviving an infection
Yes
Long-term / Lifelong
Recovering from measles
Artificially Acquired Active
Vaccination
Yes
Long-term / Lifelong
Receiving the polio vaccine
Naturally Acquired Passive
Antibodies from mother to child (placenta/breast milk)
No
Short-term (months)
An infant's temporary immunity to diseases the mother had
Artificially Acquired Passive
Injection of pre-formed antibodies (antiserum)
No
Short-term (weeks to months)
Receiving Rabies Immunoglobulin after a bite
Antibodies (Immunoglobulins)
Antibodies are Y-shaped glycoprotein molecules produced by plasma cells in response to a specific antigen. They are found in blood serum and other body fluids. Their primary function is not to kill pathogens directly, but to bind to them and facilitate their destruction.
The Five Classes of Antibodies (Isotypes)
Class
Abundance
Key Features and Functions
IgG (Gamma)
~80% (Most abundant in serum)
Provides the majority of long-term antibody-based immunity. It is the only antibody class that can cross the placenta, providing passive immunity to the fetus. It is the main antibody in the secondary response.
IgA (Alpha)
~15%
Known as the secretory antibody. Found in mucosal secretions (saliva, tears, mucus), respiratory, GI, and urogenital tracts. It prevents pathogens from colonizing and attaching to mucous membranes. Also found in breast milk, providing passive immunity to the infant's gut.
IgM (Mu)
~10%
It is a very large molecule (a pentamer). It is the first antibody to be produced during a primary immune response, indicating a recent or current infection. It is a potent activator of the complement system.
IgD (Delta)
<1%
Functions mainly as an antigen receptor on the surface of B-cells. Its exact role is still being researched.
IgE (Epsilon)
~0.002% (Lowest concentration)
Binds to mast cells and basophils. When it encounters its specific antigen (an allergen like pollen), it triggers the release of histamine, causing an allergic reaction. It also plays a role in defending against parasitic worm infections.
Acquired Immunity
Acquired immunity develops during an individual's lifetime and can be classified based on how it was obtained: naturally or artificially, and actively or passively.
The Four Types of Acquired Immunity
Naturally Acquired Active Immunity:
How it's acquired: By getting an infection. The body is exposed to a live pathogen, mounts a primary immune response, and develops long-lasting memory cells.
Memory: Yes (long-term).
Example: Recovering from chickenpox gives you lifelong immunity to that specific virus.
Naturally Acquired Passive Immunity:
How it's acquired: Through the transfer of antibodies from mother to child. IgG crosses the placenta to the fetus, and IgA is passed through breast milk to the infant.
Memory: No. The immunity is temporary (lasts a few months) because the infant did not make the antibodies themselves.
Example: Protection of a newborn from infections during the first few months of life.
Artificially Acquired Active Immunity:
How it's acquired: Through vaccination (immunization). The body is deliberately exposed to a harmless form of a pathogen (e.g., killed or weakened) or its antigens, which stimulates a primary immune response and creates memory cells without causing the disease.
Memory: Yes (long-term).
Example: The measles vaccine provides long-term protection against measles.
Artificially Acquired Passive Immunity:
How it's acquired: Through the injection of pre-formed antibodies (immunoglobulins) from an immune human or animal. This provides immediate but temporary protection.
Memory: No.
Example: Giving someone an injection of tetanus antitoxin (antibodies against the tetanus toxin) after a deep, dirty wound for immediate protection while their own active immunity develops. Another example is giving Rabies Immunoglobulin (RIG) after a suspected rabid animal bite.
Hypersensitivity
The term hypersensitivity refers to an exaggerated or inappropriate immune response to an antigen that results in significant inflammation and damage to host tissues. While the immune system's job is to protect us, in hypersensitivity reactions, the protective response itself becomes the cause of the illness.
These reactions are classified into four types based on the primary immune mediators involved and the time it takes for a reaction to occur.
Type I: Immediate / Anaphylactic Hypersensitivity
Key Immune Mediator: IgE antibodies.
Onset Time: Immediate (within minutes to a few hours of exposure).
Mechanism: This is a two-step process.
Sensitization Phase (First Exposure): An individual is exposed to an allergen (e.g., pollen, bee venom). Their B-cells are stimulated to produce large amounts of IgE antibodies against this allergen. This IgE then binds to the surface of mast cells and basophils, effectively "priming" them.
Activation Phase (Subsequent Exposure): Upon re-exposure, the allergen binds to the IgE already attached to the mast cells. This triggers the immediate and massive release (degranulation) of inflammatory mediators like histamine, leukotrienes, and prostaglandins.
Pathological Effects: The released mediators cause:
Vasodilation and Increased Capillary Permeability: Leads to swelling (edema), skin rashes (hives/urticaria), and a dangerous drop in blood pressure.
Bronchoconstriction: Contraction of smooth muscles in the airways, leading to wheezing and difficulty breathing (as seen in asthma).
Increased Mucus Secretion: Causes a runny nose and watery eyes (as in hay fever).
Clinical Examples:
Systemic Anaphylaxis: A severe, life-threatening reaction to bee stings, food allergies (e.g., peanuts), or drugs (e.g., penicillin), causing circulatory collapse and airway obstruction.
Atopic Diseases (Localized Allergies): Allergic asthma, hay fever (allergic rhinitis), eczema (atopic dermatitis), and hives (urticaria).
Type II: Antibody-Dependent Cytotoxic Hypersensitivity
Key Immune Mediators: IgG or IgM antibodies.
Onset Time: Hours to days.
Mechanism: In this type, antibodies (IgG or IgM) bind directly to antigens that are located on the surface of host cells. This "tags" the host cell for destruction through three main pathways:
Complement Activation: The antibody-antigen complex on the cell surface activates the complement system, leading to the formation of the Membrane Attack Complex (MAC), which punches holes in the cell membrane, causing it to lyse (burst).
Phagocytosis: The antibody acts as an opsonin, coating the cell and making it a prime target for phagocytes like macrophages.
Antibody-Dependent Cell-Mediated Cytotoxicity (ADCC): Natural Killer (NK) cells bind to the antibodies attached to the host cell and release cytotoxic granules to kill it.
Clinical Examples:
Incompatible Blood Transfusion: If a person with Type B blood (with anti-A antibodies) receives Type A blood, their antibodies will attack the transfused red blood cells, causing massive hemolysis.
Hemolytic Disease of the Newborn (Rh Incompatibility): An Rh-negative mother carrying an Rh-positive fetus can develop anti-Rh antibodies. In a subsequent Rh-positive pregnancy, these antibodies can cross the placenta and destroy the fetal red blood cells.
Some Autoimmune Diseases: For example, in Goodpasture's syndrome, antibodies attack proteins in the kidneys and lungs.
Type III: Immune Complex-Mediated Hypersensitivity
Key Immune Mediator: Soluble Immune Complexes (clumps of antigen and antibody, usually IgG).
Onset Time: Hours to days, or can be chronic.
Mechanism: The key difference from Type II is that the antigens are soluble (floating freely) in the blood, not fixed on a cell surface. Large quantities of antigen-antibody complexes are formed. If the body cannot clear these complexes efficiently, they get deposited in the walls of small blood vessels, especially in the kidneys, joints, and skin. These deposited complexes activate the complement system, which attracts a large number of neutrophils to the site. The frustrated neutrophils release their powerful lytic enzymes, causing inflammation and damage to the underlying tissue ("innocent bystander" damage).
Clinical Examples:
Serum Sickness: A classic example where a patient reacts to foreign proteins in injected antisera (e.g., from a horse). It causes fever, rash, joint pain, and kidney damage.
Post-Streptococcal Glomerulonephritis: Kidney inflammation following a strep throat infection, caused by the deposition of streptococcal antigen-antibody complexes in the glomeruli.
Systemic Lupus Erythematosus (SLE): An autoimmune disease where complexes of self-antigens and autoantibodies deposit in multiple organs.
Type IV: Delayed-Type / Cell-Mediated Hypersensitivity
Key Immune Mediator: T-Cells (specifically Helper T-cells and Cytotoxic T-cells). No antibodies are involved.
Onset Time: Delayed (24-72 hours or more).
Mechanism: This reaction is mediated by T-cells, and the delay is because it takes time for the T-cells to migrate to the area and orchestrate a response.
Sensitization Phase: On first contact with the antigen (e.g., chemicals from poison ivy, proteins from M. tuberculosis), an Antigen-Presenting Cell (APC) presents it to Helper T-cells, creating a population of sensitized memory T-cells.
Elicitation Phase: On second exposure, these memory T-cells are activated. They migrate to the site and release cytokines, which recruit and activate a large number of macrophages. It is the prolonged activity and cytokine release from these T-cells and macrophages that causes the inflammation and tissue damage.
Clinical Examples:
The Mantoux (Tuberculin) Skin Test: A classic example. If a person has been exposed to TB, their memory T-cells will cause a localized, hardened red swelling at the injection site 48-72 hours later.
Contact Dermatitis: Skin rash caused by contact with substances like poison ivy, nickel in jewelry, or latex.
Granuloma Formation: In chronic infections like tuberculosis and leprosy, the body forms granulomas to wall off the pathogen, which is a classic Type IV reaction causing tissue destruction over time.
Summary of Hypersensitivity Reactions
Type
Name
Key Mediator
Onset Time
Mechanism Summary
Clinical Examples
Type I
Immediate / Anaphylactic
IgE
Minutes
IgE on mast cells binds to allergen, triggering degranulation and histamine release.
Anaphylaxis, Asthma, Hay Fever, Hives
Type II
Cytotoxic
IgG, IgM, Complement
Hours to Days
Antibodies bind to antigens on host cells, leading to cell destruction.
Blood Transfusion Reactions, Hemolytic Disease of Newborn
Type III
Immune Complex
Antigen-Ab Complexes
Hours to Days
Soluble immune complexes deposit in tissues, causing inflammation and damage.
Immunological agents are a broad class of drugs that modify the immune system’s activity, either by enhancing or suppressing its function. They are like tools that help your immune system work better or differently. For example, vaccines help your body fight off specific diseases (enhancing) or autoimmune drugs treat autoimmune diseases, where the immune system attacks the body’s own tissues (suppressing).
Types of Immunological Agents:
Immunostimulants: These are drugs that boost the immune system’s function, often used when the immune system is weakened or underperforming.
Immunosuppressants: These drugs reduce or suppress the immune system’s activity, essential in preventing transplant rejection and treating autoimmune diseases.
I. Immunostimulants (Immune Stimulants)
They are also known as Immunomodulators or Immunostimulators. They are substances that stimulate the immune system and increase the ability of the immune system to fight against disease and infection.
These are drugs that enhance cell-mediated immunity by acting on T lymphocytes.
Uses: Multiple myeloma, Erythema Nodosum Leprosum, and Lupus erythematosus.
Warning: They are highly teratogenic drugs (causing severe fetal limb deformities like phocomelia) so they MUST be strictly avoided in pregnancy.
4. Interferons
Interferons are cytokines. They are natural proteins produced naturally by cells (such as T helper or CD4 cells) in response to viral infections and other stimuli. They help the body's immune system fight infection and other diseases, such as cancer.
Therapeutic Action: They prevent viral particles from replicating inside host cells. They stimulate cells to produce antiviral proteins and enhance the cytotoxicity of T-cells and natural killer (NK) cells. They inhibit tumor growth by enhancing the host’s immune response and increasing antigen presentation to lymphocytes.
Pharmacokinetics: Well absorbed via subcutaneous (SC) or intramuscular (IM) injection, reaching peak plasma levels within 3-8 hours. Metabolized in the liver and kidneys and excreted primarily through the kidneys.
Contraindications: Allergies to interferons, pregnancy and lactation (due to teratogenic effects), cardiac diseases (particularly arrhythmias and hypertension), and severe myelosuppression.
Uses: Melanoma, Kaposi sarcoma, leukemia, lymphomas, and severe viral infections (Hepatitis B & C).
Longer-lasting effects due to its pegylated form, allowing less frequent dosing (usually once weekly).
Similar to Peginterferon alfa-2a, including severe hematologic toxicity and major depression.
5. Interleukins
Interleukins are cytokines that play an essential role in the immune response by promoting the proliferation of lymphocytes and other immune cells. Think of the immune system as a big army; Interleukins are like the signals that tell different parts of the army what to do.
Activate immune cells: Tell certain cells to start fighting off invaders.
Control inflammation: Help regulate how much inflammation happens in response to an infection or injury.
Promote cell growth: Help immune cells multiply and become stronger.
Pharmacokinetics: Absorbed via SC or IV injection, peak levels within hours. Metabolized in the kidneys and excreted in urine.
Contraindications: Allergies to interleukins or E. coli-produced products. Pregnancy, lactation, and patients with severe renal, liver, or cardiovascular impairments.
Administration of immunostimulants often mimics a viral infection because these are the very chemicals the body releases during an illness.
Nausea, chills, profound fatigue.
Headache, back pain, and joint pain (myalgia/arthralgia).
Fever and vomiting.
Constipation.
II. Immunosuppressants (Immune Suppressants)
Immunosuppressants are drugs that inhibit immunity. They suppress cell-mediated immune responses, antibody-mediated immune responses, or both.
These are like the “peacekeepers” of the immune system. They dampen down the immune response, preventing it from overreacting. They are mainly used to prevent transplant/graft rejection and to treat autoimmune diseases.
General Uses & Indications:
Organ transplant (Prevention of rejection)
Inflammatory bowel disease (IBD), including Crohn’s disease and ulcerative colitis
These drugs specifically disrupt T-cell activation and proliferation, which are the primary cells responsible for cellular rejection of transplanted organs. Cyclosporine is the most commonly used immunosuppressant for this purpose.
Cyclosporine: Inhibits calcineurin, preventing the production of IL-2. Side effects include profound nephrotoxicity, hypertension, hirsutism, and gingival hyperplasia.
Tacrolimus: A macrolide that also inhibits calcineurin. More potent than cyclosporine. Associated with nephrotoxicity and neurotoxicity.
Sirolimus (Rapamycin): An mTOR inhibitor that prevents T-cell response to IL-2. Often used in renal transplants to avoid calcineurin-induced nephrotoxicity.
2. T- and B-Cell Suppressors (Cytotoxic Drugs)
These drugs inhibit the proliferation and activity of T-cells and B-cells. They are generally well absorbed (PO or IV), metabolized in the liver, and excreted via the kidneys. Contraindicated in pregnancy, lactation, renal/hepatic impairment, active infections, or known neoplasms.
Drug
Indications
Therapeutic Action & Notes
Adverse Effects
Azathioprine
Prevention of kidney transplant rejection, severe rheumatoid arthritis.
A cytotoxic antimetabolite that inhibits purine synthesis, directly reducing T and B-cell DNA synthesis and proliferation.
Severe bone marrow suppression, hepatotoxicity, profound nausea, increased risk of neoplasms.
Action: Potent anti-inflammatory agents that suppress the entire inflammatory cascade, reduce cytokine production, and cause lymphocyte apoptosis. Used heavily in acute transplant rejection episodes and severe autoimmune flares.
4. Interleukin-Receptor Antagonists
This class of drugs blocks interleukin activity, which is critical in the inflammatory and immune response.
Drug
Indications
Therapeutic Action & Notes
Adverse Effects
Anakinra
Moderate to severe Rheumatoid arthritis (when one or more DMARDs have failed).
Competitively blocks the interleukin-1 (IL-1) receptor, reducing inflammation and halting joint cartilage degradation/damage.
Headache, sinusitis, nausea, severe infections, injection-site reactions.
Monoclonal antibodies are laboratory-produced molecules that can mimic the immune system’s ability to fight off harmful pathogens or selectively suppress specific pathways. These are like highly specific “guided missiles” or a "sniper team" designed to target and attack specific cells or molecules, leaving the rest of the immune army alone.
Pharmacokinetics: Administered via IV injection/infusion and have variable half-lives depending on the specific antibody. Metabolized and excreted through the reticuloendothelial system.
Contraindications: Known allergy to murine (mouse) products. Contraindicated in fluid overload. Should be used cautiously with fever (treat the fever before beginning therapy). Avoid in pregnancy/lactation unless the benefit clearly outweighs fetal risk.
Severe skin rash, infusion reactions, hypomagnesemia.
Rituximab (Rituxan)
B-cell non-Hodgkin lymphoma, severe RA.
Targets CD20 antigen on B-cells, causing B-cell lysis.
Fatal infusion reactions, tumor lysis syndrome, severe mucocutaneous reactions.
Other Specific Indications for Monoclonal Antibodies:
Treatment of paroxysmal nocturnal hemoglobinuria (PNH) to reduce hemolysis (e.g., Eculizumab).
Treatment of asthma with a very strong allergic component and seasonal allergic rhinitis not controlled by common medicine (e.g., Omalizumab targeting IgE).
Prevention of serious RSV (Respiratory syncytial virus) infection in high-risk premature children (e.g., Palivizumab).
Treatment of metastatic breast cancer overexpressing HER2 (e.g., Trastuzumab).
Treatment of severe psoriasis.
General Side-Effects of Immunosuppressants & Monoclonal Antibodies:
The most serious adverse effect associated with the use of monoclonal antibodies is acute pulmonary edema (dyspnea, chest pain, wheezing), which is associated with severe fluid retention and capillary leak.
Infections (Due to suppressed immune system):
Blood infections like sepsis.
Fungal infections like oral thrush and skin fungus.
Skin infections like cellulitis.
Respiratory infections, including severe colds, flu, and pneumonia.
Hematologic: Intravascular hemolysis with resultant fatigue, pain, dark urine, shortness of breath, and blood clots.
Corticosteroid-specific effects: Acne, diabetes (hyperglycemia), rapid weight gain, thinning bones (osteoporosis), fatigue, hair loss or abnormal hair growth, high blood pressure.
NURSING CARE PLAN & MANAGEMENT
No.
Nursing Diagnosis
Interventions & Rationale
1
Risk for Infection related to profound immunosuppression secondary to T/B cell inhibitors, monoclonal antibodies, or corticosteroids.
Implement strict neutropenic precautions: Ensure scrupulous hand hygiene. Restrict visitors with active respiratory or systemic infections. Avoid fresh flowers/plants in the room.
Monitor vital signs closely: A low-grade fever may be the only sign of a life-threatening systemic infection in an immunosuppressed patient.
Educate the patient on hygiene: Teach proper oral care to prevent thrush, meticulous skin care to prevent cellulitis, and avoidance of large crowds.
2
Acute Pain & Impaired Comfort related to "flu-like syndrome" (myalgia, arthralgia, fever, chills) secondary to Interferon or Interleukin therapy.
Administer pre-medications as ordered: Give Acetaminophen (paracetamol) or antihistamines before injecting interferons to blunt the severe flu-like response.
Encourage rest and fluid intake: Promotes comfort and clears metabolic waste products.
Monitor injection sites: Rotate sites for SC injections to prevent tissue necrosis and localized severe injection-site reactions.
3
Risk for Impaired Gas Exchange / Fluid Volume Excess related to capillary leak syndrome (Aldesleukin) or acute pulmonary edema (Monoclonal antibodies).
Assess respiratory status constantly: Auscultate lungs for crackles/wheezes. Monitor for dyspnea, chest pain, and declining oxygen saturation.
Monitor Daily Weights and strict I&O: Extreme fluid retention is a critical adverse effect; sudden weight gain indicates fluid shifting to extravascular spaces.
Be prepared for emergency intervention: Have oxygen and emergency resuscitation equipment readily available during initial monoclonal antibody infusions (due to risk of anaphylaxis and pulmonary edema).
Educate on strict contraception: Patients taking teratogenic drugs (like Thalidomide) MUST use two forms of birth control and undergo routine pregnancy testing.
Teach self-administration techniques: If the patient is discharged with SC injections (e.g., Anakinra, Adalimumab), ensure they demonstrate proper aseptic technique and site rotation.
V. References
Karch, A. M. (2019). Focus on Nursing Pharmacology (8th ed.). Wolters Kluwer.
Burchum, J. R., & Rosenthal, L. D. (2021). Lehne's Pharmacology for Nursing Care (11th ed.). Elsevier.
World Health Organization (WHO) Guidelines on Immunizations and Biological Preparations.
Provided Presentation Slides and Lecture Notes on Immunostimulants and Immunosuppressants.
Quick Quiz
Immunological Agents Quiz
Pharmacology
Privacy: Your details are used only for quiz tracking and certificates.