Nurses Revision

Pharmacology

mechanism of action

Mechanism of Drug Action

Mechanism of Drug Action

Mechanism of Drug Action (Pharmacodynamics)

Learning Objectives for this Exam

Pharmacodynamics is the study of how drugs interact with the body at a molecular level. By the end of this guide, you will master:

  • The four primary protein targets for drugs: Receptors, Ion Channels, Enzymes, and Transporters.
  • The specific properties of receptors, including affinity, intrinsic activity, potency, and efficacy.
  • The exact definitions of agonists (full, partial, inverse) and antagonists.
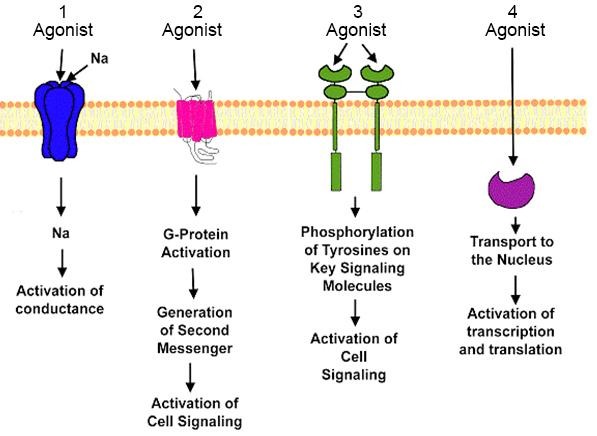
  • The four major families of receptors and their specific operating speeds and mechanisms.
  • A detailed understanding of G-Protein-Coupled Receptors (GPCRs) and their internal signaling pathways (cAMP and IP3/DAG).

Introduction to Pharmacodynamics

Pharmacodynamics is the branch of pharmacology concerned exclusively with the actions, interactions, and the specific mechanism (or mode) of action of drugs within the body. In simple terms, it studies exactly what the drug does to the body to produce a biological effect.

When a drug enters the body, it must interact with something to cause a change. These interactions fall into two broad categories:

  • Highly Specific Interactions: The drug precisely binds to a specific biological target (most commonly a pharmacological receptor) to exert its effect.
  • Non-Specific Interactions: The drug produces an effect without binding to a specific receptor. For example, an antacid (like calcium carbonate) simply neutralizes stomach acid through basic chemistry, without needing a receptor.

Molecular & Biochemical Mechanisms of Drug Action

For drugs that act specifically, they must bind to certain proteins on or inside mammalian cells. These protein targets can be broadly divided into four fundamental categories:

  1. Receptors
  2. Ion Channels
  3. Enzymes
  4. Carrier Molecules (Transporters)

Let us examine each of these four targets in deep detail, including the exact drugs that target them.

Target I: Receptors

Receptors are highly specialized protein structures located either on the surface of the mammalian cell membrane or entirely within the cell.

They act as the sensing elements in the chemical communication system that coordinates the functions of all the different cells in the body. Natural chemical messengers (endogenous ligands) bind to these receptors to tell the cell what to do. These natural messengers include:

  • Hormones (e.g., insulin, estrogen).
  • Neurotransmitters (e.g., acetylcholine, dopamine).
  • Other local mediators / Autocoids (e.g., Histamine, Serotonin / 5-HT).

Many therapeutically useful drugs work by hijacking this system. They act either as agonists (mimicking the natural messenger) or antagonists (blocking the natural messenger) on these known endogenous receptors.

Key Characteristics of Drugs Acting via Receptors

  • Low Concentrations: Because receptors are highly sensitive, drugs targeting them can act effectively at very low concentrations in the blood.
  • Structure–Activity Relationship (SAR): Receptors are extremely picky about shape. Very small modifications to a drug's functional chemical groups, stereochemistry (3D arrangement), or molecular shape can significantly impact how tightly the drug binds (binding affinity) and how well it works (pharmacological activity).
  • Specific Antagonism: Their effects can be precisely blocked by specific antagonists.

Examples:

  • Acetylcholine receptors can be blocked.
  • Adrenaline receptors can be blocked.
  • Histamine acts on specific H1, H2, H3, and H4 receptors (allergy medicines block H1).
  • Dopamine acts on D1–D5 receptors (antipsychotic drugs block these).
  • Morphine acts on specific opioid receptors named μ (mu), κ (kappa), and δ (delta).
Target II: Ion Channels

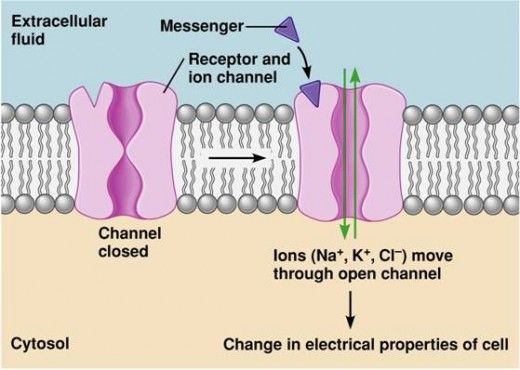
Cells use electrical charges to communicate, especially nerves and muscles. They do this by moving ions (like Sodium, Calcium, Potassium, and Chloride) in and out of the cell through specialized protein gates called Ion Channels.

There are two main types of ion channels:

  • Ligand-gated (ionotropic) channels: These are locked gates that only open when a specific chemical key (an agonist) binds directly to the receptor on the gate.
  • Voltage-gated channels: These gates do not need a chemical key. Instead, they sense the electrical charge of the cell. They open or close in response to changes in the membrane potential (electrical voltage).

How Drugs Act on Ion Channels:

  • Direct Action: The drug physically binds directly to the channel protein itself, acting like a plug to block it, or locking it in an open position.
  • Indirect Action: The drug binds to a separate receptor nearby, which then uses a messenger (like a G-protein) to tell the ion channel to open or close.

Examples of Drugs Acting on Ion Channels:

  • Voltage-gated sodium channels: These are blocked by local anesthetics (e.g., lidocaine). By blocking sodium from entering the nerve, the nerve cannot send a pain signal to the brain.
  • L-type calcium channels: These are inhibited by dihydropyridines (a class of vasodilators, e.g., nifedipine). By blocking calcium from entering blood vessel muscles, the vessels relax, heavily lowering blood pressure.
  • GABA receptor–chloride channel system: This is modulated by benzodiazepines (tranquillizers, e.g., diazepam). Diazepam binds to the channel, helping it open wider to let negatively charged chloride ions into the brain cell, severely calming and slowing down brain activity.
  • ATP-sensitive potassium channels (KATP): Located in the pancreatic β-cells. These are blocked by sulfonylureas (diabetes medications). Blocking potassium from leaving the cell forces the pancreas to release stored insulin into the blood.
Target III: Enzymes

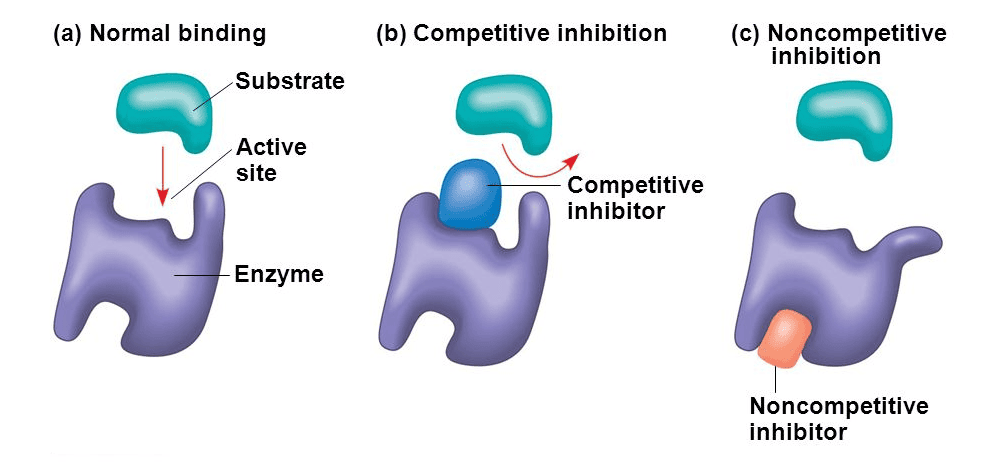
Enzymes are biological catalysts that speed up chemical reactions in the body (building things up or breaking them down). Many drugs act specifically as enzyme inhibitors.

  • I. Competitive, Reversible Inhibition: The drug temporarily fights the natural substance for the active spot on the enzyme. If the drug wins, the enzyme halts. Because it is reversible, the effect wears off as the drug leaves the body.
    • Example: Neostigmine. It reversibly inhibits the enzyme acetylcholinesterase (the enzyme that destroys acetylcholine). This allows acetylcholine to build up and help patients with severe muscle weakness.
  • II. Irreversible, Non-Competitive Inhibition: The drug permanently binds to the enzyme, destroying its ability to function forever. The body must physically build entirely new enzymes to recover.
    • Example: Aspirin. It permanently inhibits the cyclo-oxygenase (COX) enzyme, permanently stopping the production of chemicals that cause pain and inflammation.
  • III. False Substrates: The drug tricks the enzyme. The enzyme thinks the drug is a normal building block and tries to process it, producing abnormal, broken metabolites that disrupt cell pathways.
    • Example: Fluorouracil. This is an anticancer drug. Cancer cells take it up thinking it is a building block for DNA, but it ruins their DNA production, killing the cancer cell.
Target IV: Carrier Molecules (Transporters)

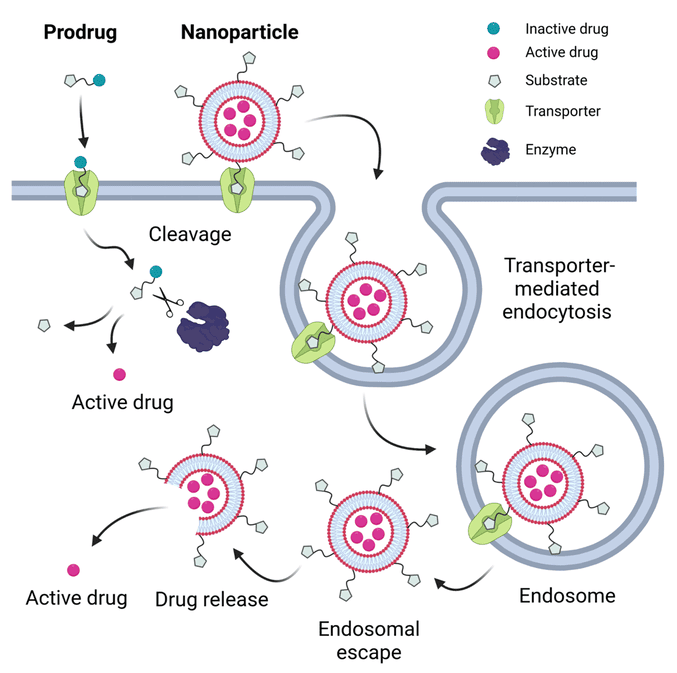
Many essential molecules in the body are polar ions or small organic molecules. Because they are polar, they cannot diffuse freely through the fatty cell membrane. They require special "taxi cabs" called carrier molecules or transporters to carry them across the membrane.

Natural examples of these transporters include Glucose and amino acid transporters, Ion transporters, and Neurotransmitter transporters (which vacuum up used neurotransmitters like choline, noradrenaline, serotonin, and glutamate from the brain synapses to be recycled).

Amine Transporters (Distinct from Receptors)

These belong to a separate structural family from receptors. Carrier proteins have highly specific recognition sites for their substrates. Drugs can target these exact sites to block transport.

Crucial Examples of Drugs Targeting Carriers/Transporters:

Tricyclic antidepressants (TCAs)

Block the reuptake transporters for noradrenaline and serotonin, leaving more of these mood-boosting chemicals in the brain.

Advertisements

Cocaine

Blocks the reuptake transporters for dopamine, noradrenaline, and serotonin, causing a massive, temporary high.

Selective Serotonin Reuptake Inhibitors (SSRIs)

(e.g., Fluoxetine). Specifically inhibit the serotonin transporter (SERT), leading to increased serotonin at synapses to treat depression.

Omeprazole

Inhibits the H⁺/K⁺-ATPase proton pump (a specific transporter) in the stomach's parietal cells, stopping severe acid reflux.

Cardiac glycosides

(e.g., digoxin): Inhibit the Na⁺/K⁺-ATPase pump in heart cells. This indirect action forces intracellular calcium levels to rise, causing the heart to pump with much greater force.

Loop Diuretics

(e.g., Furosemide): Inhibit the Na⁺-K⁺-2Cl⁻ cotransporter (NKCC2) in the renal tubules of the kidneys, causing massive water loss (urine).

Thiazide Diuretics

(e.g., Hydrochlorothiazide): Block the Na⁺-Cl⁻ cotransporter (NCC) in the distal tubule of the kidney.

SGLT2 inhibitors

(e.g., Dapagliflozin): Block the sodium-glucose cotransporter-2 in the kidney. This prevents the kidney from reabsorbing sugar, leading to increased glucose excretion in the urine to treat diabetes.


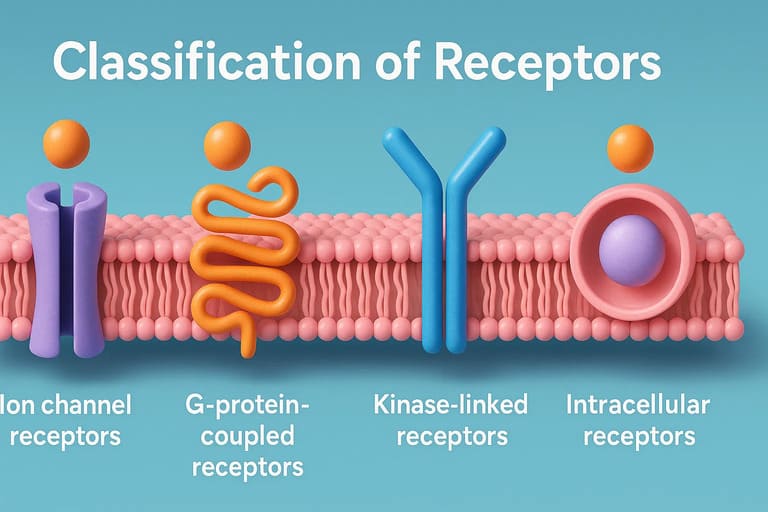
The Four Main Types of Receptors

Receptors are not all built the same. They differ heavily in their physical structure, their internal signaling mechanism, and their speed of response. They are divided into four main classes:
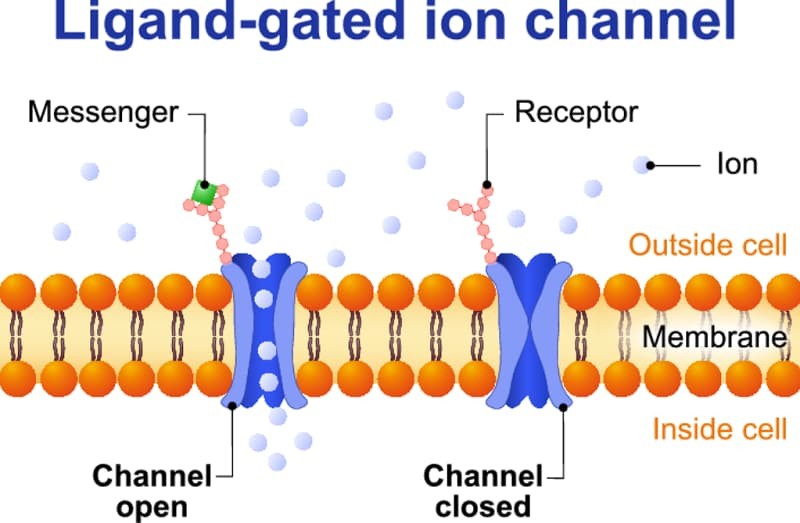
Type 1: Ligand-Gated Ion Channels (Ionotropic Receptors)

  • Structure: Membrane proteins containing an extracellular ligand-binding site physically attached to an ion channel pore.
  • Function: Mediate incredibly fast synaptic transmission between nerves.
  • Operating time: Milliseconds (the fastest receptor type).
  • Examples:
    • The Nicotinic Acetylcholine Receptor (nAChR): Composed of exactly five protein subunits forming a ring structure. These subunits are of four different types: α (alpha), β (beta), γ (gamma), and δ (delta). Each subunit is embedded in the cell membrane, forming a central pore. Mechanism: The receptor has exactly two binding sites for acetylcholine (ACh). The channel opens only when both binding sites are occupied by ACh molecules.
    • GABAA receptor
    • Glutamate (NMDA) receptor

Type 2: G-Protein–Coupled Receptors (GPCRs) / Metabotropic Receptors

  • Structure: A single polypeptide chain winding through the cell membrane exactly seven times (seven transmembrane domains). A large loop on the inside of the cell interacts with a G-protein.
  • Function: These are membrane receptors linked to intracellular effector systems (enzymes inside the cell) through intermediary G-proteins. They form the largest receptor family in the human body.
  • Operating time: Seconds.
  • Effectors: They mediate the actions of many hormones, peptides, catecholamines, and slow neurotransmitters.
  • Examples: Muscarinic acetylcholine receptors, adrenoceptors, and chemokine receptors. While multiple subtypes exist, they all share the exact same basic structural 7-transmembrane framework.
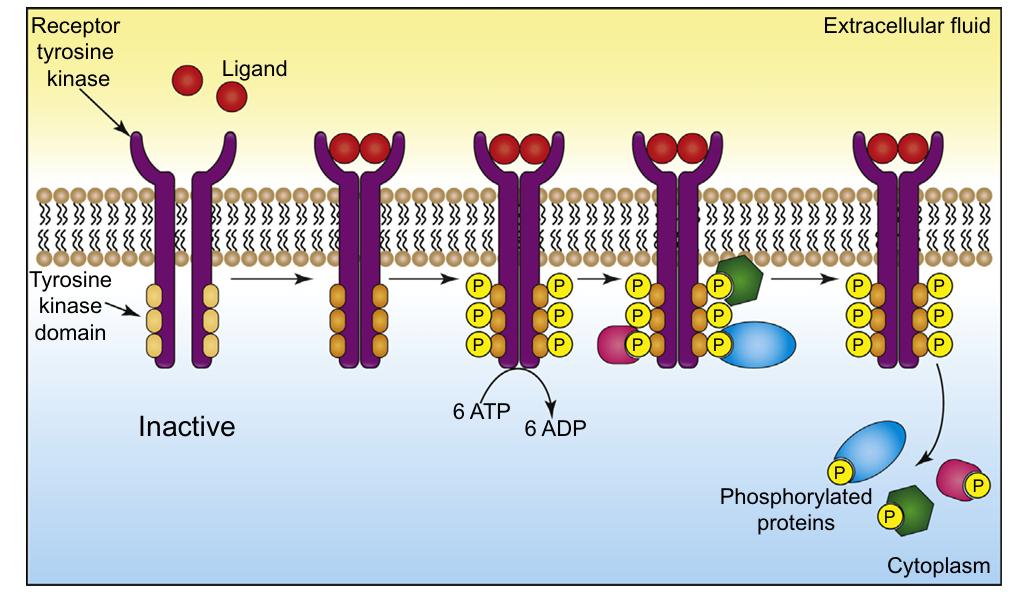
  • Structure: A large and extremely heterogeneous group. They consist of an extracellular ligand-binding domain, a single transmembrane helix, and an intracellular domain that acts directly as an enzyme.
  • Function: The inside of the receptor has enzymatic activity (e.g., protein kinase or guanylyl cyclase activity) or is tightly coupled to intracellular enzymes.
  • Operating time: Hours.
  • Effectors: They mainly respond to protein mediators like peptide hormones and growth factors.
  • Subclasses and Examples:
    • Receptor Tyrosine Kinases (RTKs): e.g., the Insulin receptor, Epidermal Growth Factor (EGF) receptor.
    • Receptor Serine/Threonine Kinases: e.g., receptors for Transforming Growth Factor-β (TGF-β).
    • Cytokine Receptors: e.g., receptors for interleukins, growth hormone, erythropoietin. These are strongly associated with Janus kinases (JAKs).
    • Receptor Guanylyl Cyclases: e.g., atrial natriuretic peptide (ANP) receptor.
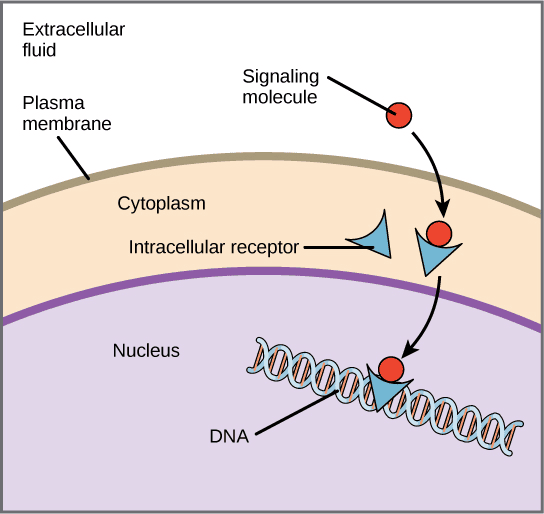
Type 4: Nuclear (Intracellular) Receptors

  • Structure & Location: Unlike the other three, these are not stuck in the cell membrane. Although termed "nuclear" receptors, some float freely in the cytosol (the cell fluid) and only translocate (move) into the nucleus after the ligand binds to them.
  • Function: They strictly regulate gene transcription. They act as transcription factors, physically binding to specific DNA sequences to turn gene expression on or off.
  • Operating time: Hours to days (This is a very long-term process because building new proteins from DNA takes significant time).
  • Examples: Receptors for steroid hormones (glucocorticoids, mineralocorticoids, androgens, estrogens), thyroid hormones, retinoic acid, and vitamin D.


The Receptor Concept and Drug Interactions


History of the Receptor Concept

  • The initial idea of drugs acting on invisible specific targets (receptors) is credited to John Langley (1878) while he was studying the antagonism between two plant chemicals, atropine and pilocarpine, and how they induced or blocked salivation.
  • The actual term receptor was introduced in 1909 by Paul Ehrlich. He proposed a famous rule: drugs exert therapeutic effects only if they possess the "right sort of affinity."
  • Ehrlich defined a receptor as: “that combining group of the protoplasmic molecule to which the introduced group is anchored.”
  • Today, we know that from a numerical standpoint, proteins are the most important class of drug receptors. This encompasses hormone receptors, growth factor receptors, transcription factors, neurotransmitter receptors, and cellular enzymes.

Drug–Receptor Interaction and Bonding

When a drug finds its receptor, it must stick to it. Drug binding to receptors can involve various chemical forces:

  • Noncovalent bonds: Ionic bonds, hydrogen bonding, hydrophobic interactions, and van der Waals forces. Most drug–receptor interactions involve multiple types of these weak, temporary bonds.
  • Covalent bonds: These are incredibly strong, permanent chemical bonds. Covalent binding usually results in prolonged, irreversible drug action (like Aspirin permanently breaking COX enzymes). *Note: Extremely high-affinity noncovalent interactions can sometimes behave as if they are irreversible because they hold on so tightly.*
Affinity vs. Intrinsic Activity (The Key and Lock Analogy)

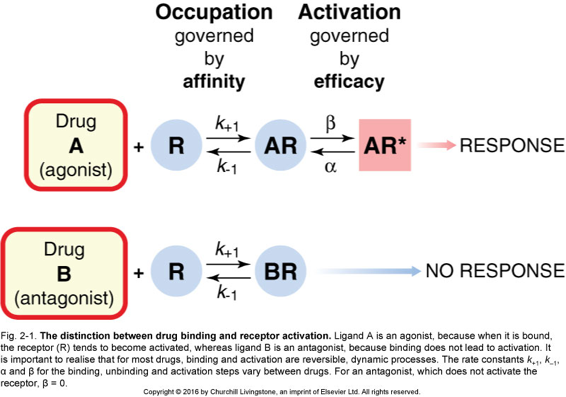
Drug-receptor interaction occurs in two distinct steps:

  1. Binding (Affinity): This is the ability of the drug to locate, physically bind to, and maintain a connection with the receptor. It is determined by the chemical shape and forces. Analogy: Affinity is how well the key fits into the lock.
  2. Generation of a Response (Intrinsic Activity): This reflects the ability of the drug-receptor structure to actually produce a biological pharmacological effect once connected. Analogy: Intrinsic activity is whether or not the key can actually turn and open the door.
Potency and Efficacy

These two terms are strictly different and frequently tested:

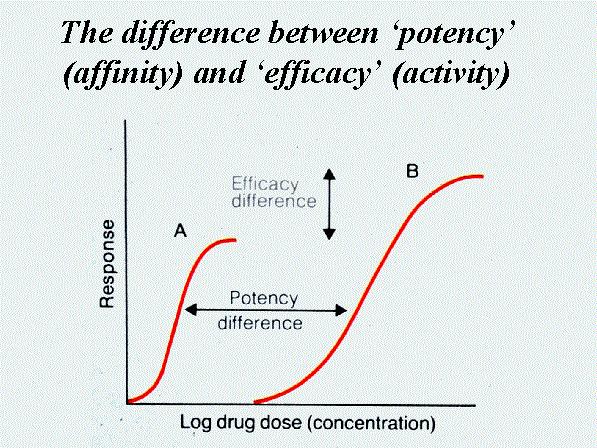
  • Potency: Refers to the amount (dose/weight) of drug strictly required to produce a given effect. A drug is considered highly potent if it produces a significant response at a very low dose (e.g., 1 milligram). Potency is important for doctors when determining the appropriate dosage to prescribe.
  • Efficacy: Refers to the maximum or peak response a drug can physically produce, regardless of how high you push the dose. It is a critical factor in drug selection. If a patient is in severe pain, you need a drug with high efficacy (like morphine), not just a highly potent drug that has a low ceiling of effect.

Theories Explaining the Intensity of Drug Response

When a drug binds, how does the body decide how intense the reaction should be? Three main theories attempt to explain this mathematical relationship:

Advertisements

  • Rate Theory: The response depends solely on the speed (rate) at which the drug associates with and dissociates from the receptor, rather than how many receptors are occupied at a given time.
    • Drug activity depends on k₁ (the rate of association/binding) and k₂ (the rate of dissociation/breaking apart).
    • Agonists have high association and high dissociation rates, leading to a rapid turnover of binding events, which creates a strong response.
  • Drug-Induced Protein Change Theories: The drug induces a physical conformational (shape) change in the receptor protein upon binding. This physical structural alteration initiates the biological response.
    • Agonists cause temporary structural changes that alter cell membrane permeability to produce a response. Antagonists cause changes that block further binding.
  • Receptor Occupation Theory: The simplest theory. The response is strictly, directly proportional to the physical number of receptors occupied by the drug. A maximal effect occurs when 100% of all available receptors are occupied.
Importance of the Receptor Concept

Receptors are central to pharmacology. They mediate most drug actions, determine the selectivity of both therapeutic and toxic effects, and dictate the exact mathematical quantitative relationship between the drug dose and the pharmacologic response.

Types of Drugs Based on Receptor Interaction

Agonist

A drug, hormone, or neurotransmitter that binds to its specific receptor, successfully activates it, and initiates a full response. It has both high affinity and high intrinsic activity.

Examples: Acetylcholine, noradrenaline.

Antagonist

A drug that binds firmly to a receptor but does not activate it. Instead, it acts as a shield, preventing the action of a natural agonist by blocking receptor access. A pure competitive antagonist has high affinity but absolutely zero intrinsic activity of its own.

Examples: Atropine, Naloxone.

Partial Agonist

A drug that binds to a receptor and activates it, but mathematically produces a weaker (submaximal) response compared to a full agonist. Its intrinsic activity is greater than 0 but less than 1.

Unique feature: Under certain conditions, if a full agonist is already present, adding a partial agonist will actually act as an antagonist because it steals the receptor seat from the full agonist, resulting in a lower overall response.

Example: Aripiprazole (an atypical antipsychotic). It acts as a partial agonist at dopamine receptors—it inhibits severely overactive dopaminergic pathways (calming the brain) while gently stimulating underactive ones.

Inverse Agonist

A drug that produces an effect physically opposite to that of an agonist.

Crucial Clarification: An inverse agonist does not simply produce an effect "opposite to the agonist" in a general behavioral sense. Instead, it produces an effect opposite to the receptor's constitutive (basal/resting) activity. While a normal antagonist just sits there and blocks, an inverse agonist actively shuts down the receptor's baseline hum.

Example: Benzodiazepines (agonists) on GABA receptors cause severe sedation and anxiolysis. Inverse agonists (like β-carbolines) bind to the exact same receptor but actively cause extreme stimulation, anxiety, and convulsions.

Mixed Agonist–Antagonist

A drug that acts as a full agonist at one specific receptor subtype, but simultaneously acts as an antagonist at a different related subtype.

Example: Some opioids, such as pentazocine and nalorphine. They can produce bizarre psychotomimetic (hallucinatory) effects that are uniquely not reversed by naloxone, and they may instantly precipitate withdrawal symptoms in opioid-dependent patients, heavily limiting their clinical use.

Mechanism of Signal Transduction: GPCRs in Detail

Let us take a deeper look at the Type 2 receptors: G-protein–coupled receptors (GPCRs), also known as metabotropic receptors.

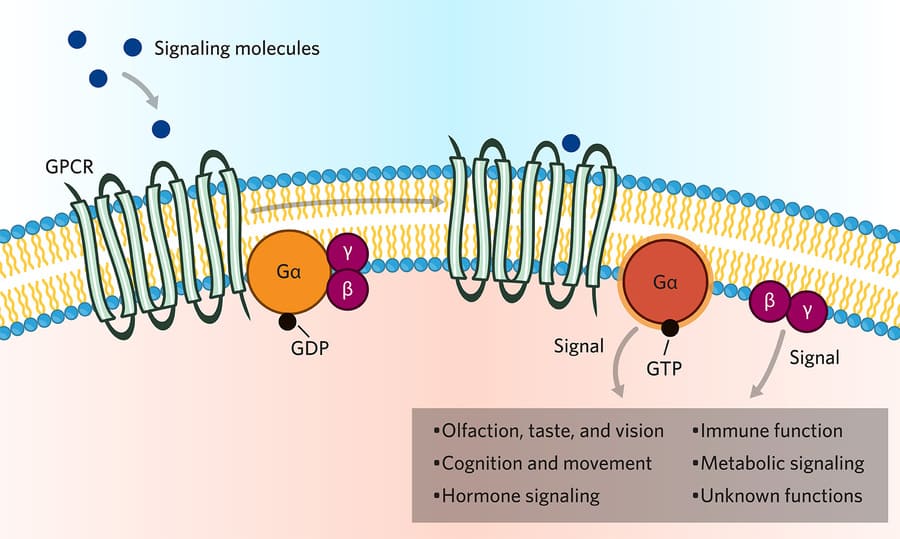
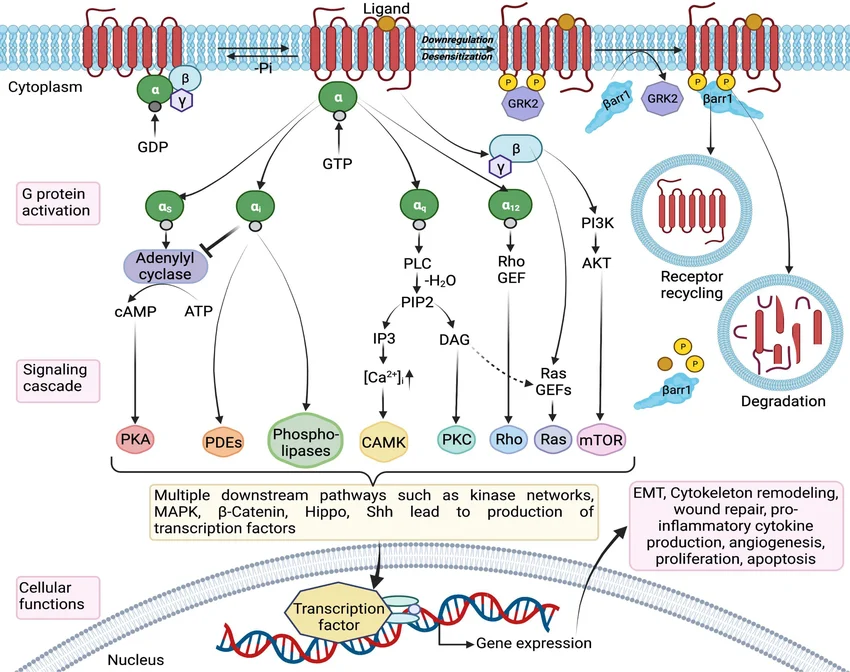
GPCRs regulate cellular functions by activating intracellular signaling pathways. The physical connection between the receptor on the outside of the cell and the signaling enzymes on the inside of the cell is mediated by a middle-man known as a G-protein.

Facts about G-Proteins:

  • They act as physical intermediaries between the receptor and the effector targets (enzymes or ion channels).
  • They are named "G-proteins" because of their interaction with guanine nucleotides (GTP and GDP).
  • They are heterotrimeric proteins, meaning they are built from three different subunits named α (alpha), β (beta), and γ (gamma).
  • The α-subunit possesses GTPase activity, which acts as a timer to regulate and eventually shut off the signaling.

The Three Main Classes of G-Proteins

Depending on which specific G-protein the receptor is attached to, the cell will do entirely different things:

  • Gs (Stimulatory): Stimulates the enzyme Adenylyl Cyclase → Increases cAMP levels in the cell.
  • Gi (Inhibitory): Inhibits the enzyme Adenylyl Cyclase → Decreases cAMP levels in the cell.
  • Gq: Activates the enzyme Phospholipase C (PLC) → Increases IP₃ and DAG → Increases Calcium (Ca²⁺) levels.
  • (Minor class) G12/13: Activates RhoGEFs (RhoA) to regulate the cellular cytoskeleton, cell shape, and migration. It does not use classical second messengers.

Target 1: The Adenylyl Cyclase / cAMP System (Gs and Gi)

Many drugs regulate the activity of the membrane-bound enzyme adenylyl cyclase. Here is the step-by-step pathway:

  1. A drug binds to a Gs-coupled receptor.
  2. The Gs protein is activated and turns on the enzyme Adenylyl Cyclase.
  3. Adenylyl Cyclase rapidly converts regular ATP energy molecules into a second messenger called cAMP.
  4. Rising cAMP levels activate Protein Kinase A (PKA).
  5. PKA goes on to phosphorylate proteins, increasing heart rate, increasing lipolysis (fat breakdown), and changing gene expression.

To stop the signal: cAMP is continuously degraded and destroyed by maintenance enzymes called phosphodiesterases (PDEs), which turn it into inactive 5′-AMP.

Conversely, if a drug binds to a Gi-coupled receptor, the exact opposite happens. Adenylyl cyclase is blocked, cAMP drops, PKA activity drops, and protein phosphorylation decreases.

Target 2: The Phospholipase C / IP₃–DAG System (Gq)

If a drug binds to a Gq-coupled receptor, a completely different signaling pathway occurs:

  1. A drug binds to a Gq-coupled receptor.
  2. The Gq protein activates a different membrane enzyme called Phospholipase C (PLC-β).
  3. PLC acts like a pair of scissors. It cuts a fat molecule in the membrane called PIP₂ into two distinct second messengers: IP₃ and DAG.
  4. IP₃ (Inositol trisphosphate): Diffuses deep into the cytoplasm and triggers massive Calcium (Ca²⁺) release from the cell's storage unit (the endoplasmic reticulum).
  5. DAG (Diacylglycerol): Remains stuck in the cell membrane and activates Protein Kinase C (PKC).

The combined action of skyrocketing Calcium and PKC activation causes intense cellular effects, primarily smooth muscle contraction and glandular secretion.

Target 3: Direct Ion Channel Regulation by GPCRs

Sometimes GPCRs do not use complex enzymes. Certain GPCRs directly regulate ion channels using the G-protein's leftover βγ (beta-gamma) subunits.

  • Potassium (K⁺) channels: These are often physically opened by Gi-coupled receptors. This causes potassium to flood out, leading to hyperpolarization and deeply lowered excitability. (Example: Muscarinic M₂ receptors doing this in the heart causes the heart rate to slow down).
  • Calcium (Ca²⁺) channels: These are often physically inhibited (closed) by Gi-coupled receptors. This reduces calcium entry, which instantly stops the nerve from releasing neurotransmitters. (Example: Presynaptic autoreceptors shutting down the nerve terminal).

Through these intricate systems, GPCRs seamlessly control membrane potential, neuronal firing, massive muscle contractions, and cellular secretion.
Quick Quiz

Mechanism of Drug Action Quiz

Pharmacology

Privacy: Your details are used only for quiz tracking and certificates.

Advertisements

Mechanism of Drug Action Read More »

drug elimination

Elimination & Clearance of Drugs

Elimination & Clearance of Drugs

Pharmacokinetics of Elimination


Module Overview

This module covers the final stages of a drug's journey through the body: Elimination and Excretion. You will learn not only how the body gets rid of drugs, but the mathematical principles (kinetics) that govern this removal. Mastering these concepts is crucial for determining how much of a drug to give (dosing) and how often to give it (dosing intervals) to maintain safe, steady, and therapeutic levels in a patient.


The Fundamentals: Elimination vs. Excretion

While often used interchangeably in casual conversation, in pharmacology, these two terms have different meanings:

Elimination

Elimination is the broad, overarching term. It concerns all the processes involved in the removal of active drugs from the body (and/or plasma) and their kinetic characteristics. If a drug is no longer active in the body, it has been eliminated. The major modes of drug elimination are:

  • Biotransformation (Metabolism): The liver chemically alters the active drug into inactive metabolites. Even though the physical atoms of the drug are still in the body, the active drug has been eliminated.
  • Excretion: The physical removal of the drug from the body.

Excretion

Excretion is a specific sub-process of elimination. It is the process by which drugs or their metabolites are irreversibly transferred from the internal environment to the external environment (i.e., passed out of the systemically absorbed body).

Drugs and their metabolites can be excreted via several routes:

  • Urine: The primary route (Renal Excretion).
  • Feces: Biliary excretion via the bile duct into the intestines.
  • Exhaled Air: Important for volatile anesthetics and alcohol.
  • Saliva and Sweat: Minor routes.
  • Breast Milk: Clinically crucial because excreted drugs can be unintentionally passed to a nursing infant.


Renal Excretion: The Kidney's Role

The kidneys are the principal organs of excretion. For a drug to be efficiently excreted in the urine (renal excretion), it ideally needs to possess certain physical characteristics:

  • Water-soluble (Hydrophilic): So it dissolves in urine.
  • Small in molecular size: So it can be filtered.
  • Slowly metabolized: If it is rapidly metabolized by the liver, the kidney only excretes the metabolites, not the parent drug.
  • Non-volatile: Volatile gases are excreted by the lungs, not the kidneys.
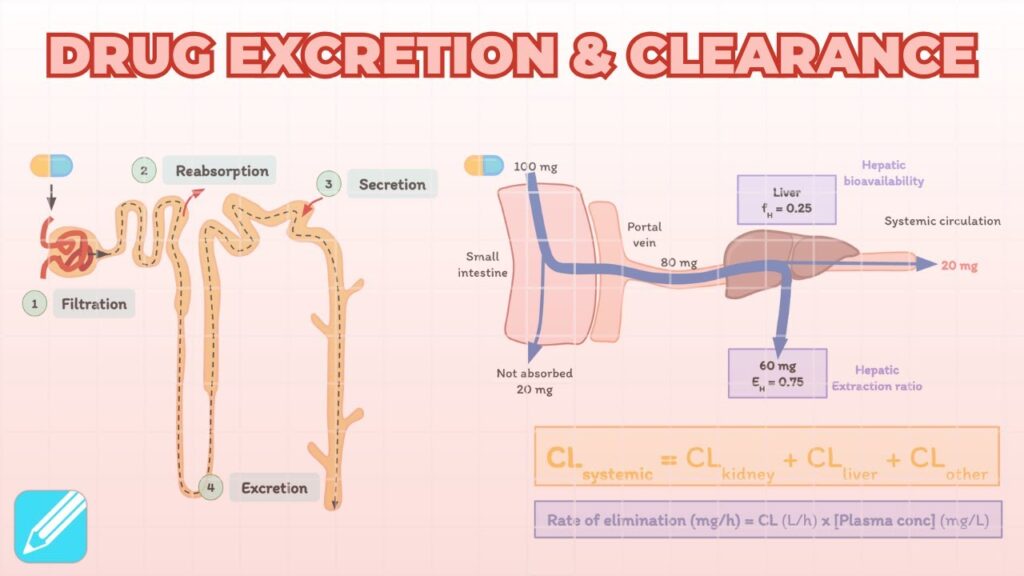
Net Renal Excretion = (Glomerular Filtration + Tubular Secretion) - Tubular Reabsorption

To understand the equation above, we must break down the three distinct processes that occur inside the nephron (the functional unit of the kidney):

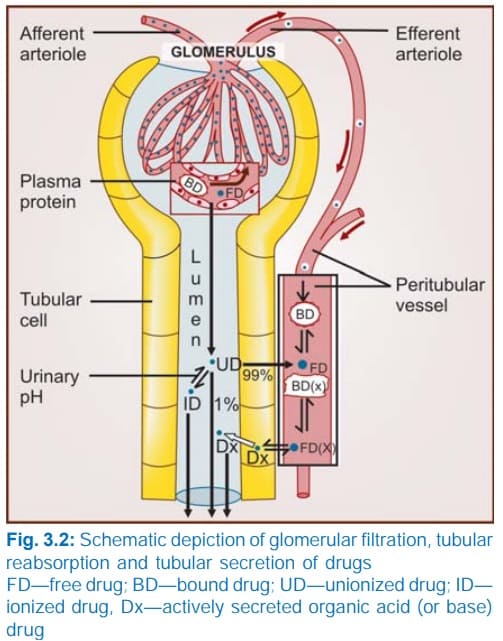
A. Glomerular Filtration

Blood enters the kidney's glomerulus under high pressure. Glomerular filtration is a non-selective, unidirectional process. It acts like a simple sieve.

  • What gets filtered? Water, small molecules, and unbound (free) drugs.
  • What does NOT get filtered? Large proteins (like albumin) and any drug bound to those plasma proteins. Protein-bound drugs are simply too large to pass through the glomerular filter.
  • Normal Rate: The normal Glomerular Filtration Rate (GFR) is approximately 120 ml/min.
Clinical Note: GFR declines progressively after the age of 50 and drops drastically in patients with renal failure, requiring doctors to lower drug doses.

B. Tubular Reabsorption

As the filtered fluid travels down the renal tubules to become urine, the body realizes it has accidentally filtered out things it wants to keep. It reabsorbs them back into the blood. For drugs, this occurs mostly by passive diffusion.

  • Lipid Soluble Drugs: If a drug is highly lipid-soluble, it will easily diffuse across the tubule walls back into the blood. In fact, 99% of the glomerular filtrate (mostly water) is reabsorbed, and lipid-soluble drugs follow this water back into the body.
  • Non-Lipid Soluble & Ionized Drugs: These cannot cross the tubule membranes. They remain trapped in the urine and are excreted.
Clinical Application

The Role of Urinary pH (Ion Trapping)

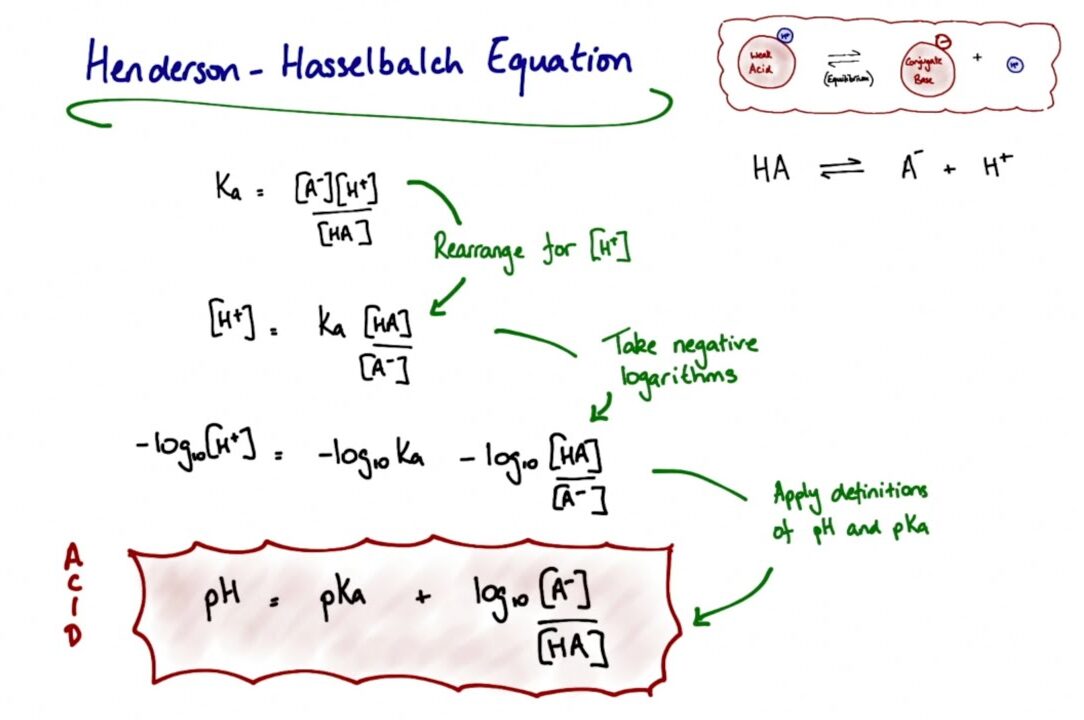
The pH of human urine can vary significantly (from 4.5 to 7.5). Because most drugs are weak acids or weak bases, the pH of the urine determines whether the drug becomes ionized (charged) or unionized (uncharged).

Rule of thumb: Drugs become highly ionized in opposite-pH environments.

  • Weak Bases: Ionize more in an acidic medium. If urine is acidic, basic drugs become ionized, cannot be reabsorbed, and are excreted.
  • Weak Acids: Ionize more in a basic (alkaline) medium. If urine is alkaline, acidic drugs become ionized, are trapped in the tubule, and are excreted.

Clinical Application: In an aspirin (weak acid) overdose, doctors administer sodium bicarbonate to alkalize the urine. This ionizes the aspirin in the kidney tubules, preventing its reabsorption and rapidly flushing it out of the body.

C. Tubular Secretion

This is the active transfer of organic acids and bases directly from the blood into the renal tubule, bypassing the glomerulus entirely.

  • It is a carrier-mediated process that requires cellular energy because it pumps compounds against their concentration gradient.
  • OATP (Organic Anion Transporting Polypeptide): Transports acidic drugs (anions). Examples include Penicillin, probenecid, uric acid, salicylates (aspirin), and furosemide.
  • OCT (Organic Cation Transporter): Transports basic drugs (cations). Examples include Amiloride, quinine, procainamide, choline, and cimetidine.
  • Competitive Inhibition: Because these transporters are limited in number, two drugs can compete for the same pump. For example, Probenecid competes with Penicillin for the OATP pump. Giving them together blocks Penicillin from being secreted, keeping it in the blood longer (historically used to prolong the effects of scarce penicillin).

Elimination Kinetics: The Half-Life (t 1/2)

To mathematically model how fast a drug leaves the body, pharmacologists rely heavily on the concept of half-life.

Definition: The Elimination Half-Life (t 1/2) is the time required to eliminate 50% of a given amount of drug from the body, or specifically, the time it takes for the plasma concentration of a drug to fall to exactly half of its initial concentration.

  • Plasma half-life: Time for plasma levels to drop by 50%.
  • Whole body half-life: Time to eliminate 50% of the total drug content from the entire body.

Why is Half-Life Important?

  • It tells us the rate of decline of drug concentrations (though it does not necessarily dictate the duration of the biological effect).
  • Most drugs are dosed according to their half-life. A drug with a 4-hour half-life might be taken every 6 hours, whereas a drug with a 24-hour half-life is taken once daily.
  • It determines the time it takes to reach a Steady State (which we will cover below).
  • Drug accumulation in the body is directly related to the drug's half-life and the dosing intervals.

Factors Affecting Half-Life:

Half-life is not always a static number; it changes based on physiological conditions. Major factors include:

  • Age: Elderly patients often have slower metabolisms and reduced kidney function, significantly extending a drug's half-life.
  • Renal Excretion: Kidney disease severely prolongs the half-life of renally excreted drugs.
  • Liver Metabolism: Liver disease (cirrhosis) prolongs the half-life of hepatically metabolized drugs.
  • Protein Binding: Highly bound drugs stay in the blood longer, extending their half-life.

First-Order vs. Zero-Order Kinetics

How a drug's concentration declines over time falls into two distinct mathematical categories.

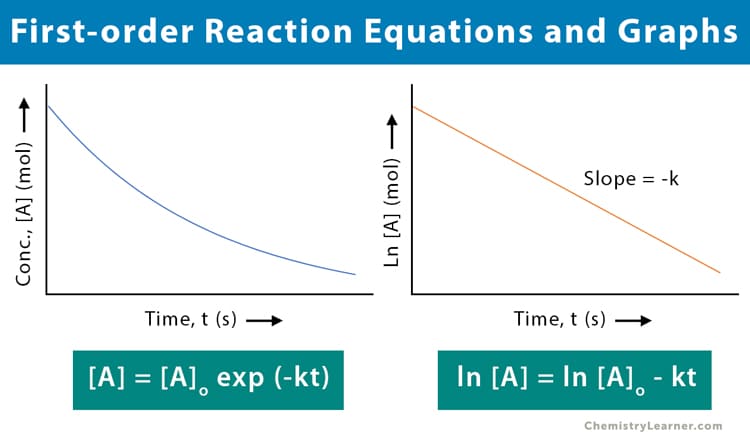
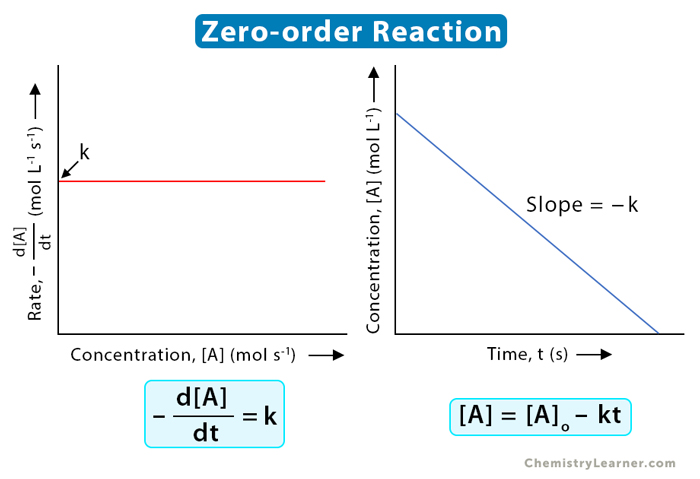
FeatureFirst-Order Kinetics (Linear Kinetics)Zero-Order Kinetics (Saturation Kinetics)
Core PrincipleA constant FRACTION (percentage) of the drug is eliminated per unit of time (e.g., 50% every hour).A constant AMOUNT of the drug is eliminated per unit of time (e.g., exactly 10 mg every hour).
Dependence on ConcentrationRate of elimination is directly proportional to drug concentration. (More drug in the body = faster elimination rate).Rate of elimination is independent of plasma concentration. The elimination mechanisms (enzymes) are saturated and working at max capacity.
Half-Life (t 1/2)Constant. It always takes the same amount of time to cut the concentration in half.No fixed half-life. It is highly variable and depends entirely on how much drug is currently in the body.
Graphical PlotPlotting Concentration vs. Time yields an exponential (curved) graph. Plotting Log[Drug] vs. Time yields a straight, linear line.Plotting Concentration vs. Time yields a straight, linear line descending directly downwards.
Clinical ExamplesApplies to the vast majority of drugs within their normal therapeutic dosage range.Applies to drugs that easily saturate liver enzymes: Ethanol (Alcohol), Phenytoin (seizure drug), and Aspirin/Salicylates (at high/toxic doses).
Simplification / Analogy

Imagine emptying a swimming pool:

First-Order: You have a magic drain that always empties exactly half of whatever water is left in the pool every hour. Hour 1: 1000L to 500L (drained 500L). Hour 2: 500L to 250L (drained 250L). The amount drained changes, but the fraction (50%) is constant.

Zero-Order: You are using a bucket that can only hold 10 Liters, and you can only throw out one bucket per minute. It doesn't matter if the pool has 10,000 Liters or 50 Liters; your rate is maxed out at exactly 10 Liters per minute. The amount is constant.


The Concept of Clearance (Cl)

Clearance is a vital concept, yet frequently misunderstood. It does not refer to an amount of drug.

Definition: Clearance is the theoretical VOLUME of plasma from which a drug is completely removed (freed) in a unit of time. It provides an estimate of the functional capacity of the organs of elimination. It is expressed in volume/time (e.g., ml/min or Liters/hour).

Clearance (Cl) = Elimination Rate (mg/hr) / Plasma Drug Concentration (mg/L)

In First-Order kinetics, Clearance is a constant proportionality factor used to determine the rate of elimination.

Types of Clearance

  • Total Body Clearance: The plasma volume cleared of the drug per unit time via all elimination mechanisms combined (liver metabolism + kidney excretion + sweat, etc.).
  • Renal Clearance: Specifically, the volume of plasma cleared of the non-metabolized (unchanged) drug strictly via excretion by the kidneys per minute.

The Mathematical Relationship: Clearance, Volume of Distribution, and Half-Life

There is a holy trinity of pharmacokinetic variables that dictate a drug's behavior:

Advertisements

t 1/2 = (0.693 × V d) / Cl

How to interpret this:

  • Elimination half-life is inversely proportional to clearance. If your kidneys are highly efficient and clear the drug rapidly (high Cl), the drug's half-life will be very short.
  • Elimination half-life is directly proportional to Volume of Distribution (V d). If a drug has a massive V d, it means it is hiding deep inside fat or tissue cells, far away from the blood plasma. Because the kidneys and liver can only clear drugs that are in the blood, a high V d protects the drug from elimination, resulting in a very long half-life.

Factors Affecting Renal Clearance

  • Glomerular Filtration Rate (GFR): High GFR = higher clearance.
  • Plasma Protein Binding: Only the free fraction of a drug can be filtered. Protein-bound drug is not cleared. Therefore, Cl = Free Fraction × GFR.
  • Tubular Reabsorption: Reabsorption pulls drug back into the blood, decreasing clearance.
  • Tubular Secretion: Secretion pumps extra drug into the urine, dramatically increasing clearance.

Interpreting Specific Renal Clearance Values

By measuring a drug's renal clearance against known standards, scientists can deduce exactly how the kidney is handling it:

Renal Clearance ValueMechanism in the KidneyClassic Examples
0 ml/min (Lowest)Drug is filtered, but then 100% is actively reabsorbed back into the body.Glucose (In a healthy person, you shouldn't pee out sugar).
< 130 ml/minDrug is filtered, and partially reabsorbed passively.Most highly lipophilic drugs.
Exactly 130 ml/min (Equal to GFR)Drug is filtered ONLY. It is neither reabsorbed nor secreted. (This makes it the perfect marker to measure a patient's GFR).Creatinine, Inulin.
> 130 ml/minDrug is filtered AND actively secreted into the tubule by pumps.Polar/ionic drugs (e.g., Penicillin).
~ 650 ml/min (Highest)Clearance is equal to the total Renal Plasma Flow Rate. Almost all drug arriving at the kidney is ripped from the blood and secreted.PAH (Para-aminohippurate).

The Steady State (C ss) and Drug Accumulation

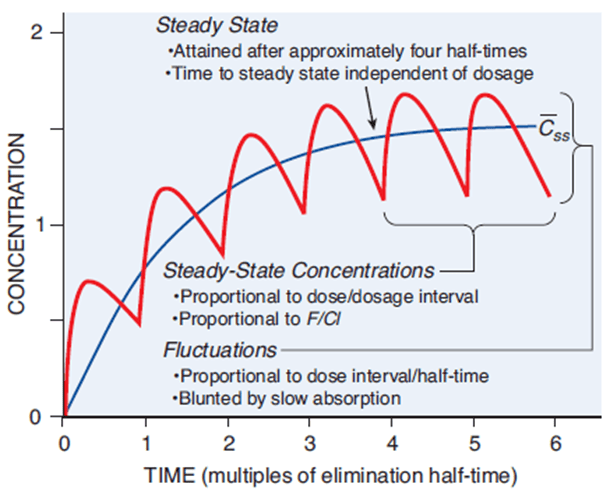
Successful drug therapy for chronic illnesses usually requires keeping the drug concentration at a stable, continuous, effective level in the blood. This plateau is called the Steady State (C ss).

The Water Tank Analogy

Imagine a sink with the tap turned on (Rate of Administration/Rate In) and the drain left open (Clearance/Rate Out). When you first turn on the tap, water accumulates in the sink because the water entering is faster than the water draining. However, as the water level rises, the weight (pressure) of the water pushes it down the drain faster. Eventually, the rate of water entering exactly matches the rate of water leaving. The water level stops rising and stays perfectly flat. This is the Steady State.

Mathematical Definition: Steady State is reached when Rate In = Rate Out.

The Plateau Principle

How long does it take for a patient taking regular pills to reach this flat steady state? This is governed by the Plateau Principle:

  • The time to reach steady state is dependent ONLY on the elimination half-life of the drug.
  • It is completely independent of the dose size or how frequently the doses are administered. Taking double the dose doesn't get you to steady state faster; it just results in a higher final plateau.
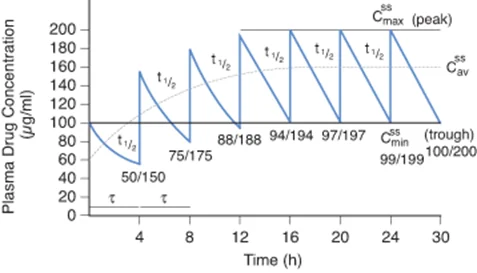
  • As a mathematical rule of thumb, it takes approximately 4 to 5 half-lives to reach a clinical steady state.
Number of Half-Lives ElapsedPercentage of Steady State Reached
1 Half-Life50%
2 Half-Lives75% (50 + 25)
3 Half-Lives87.5% (75 + 12.5)
4 to 5 Half-Lives~ 95% (Clinical Steady State)
> 7 Half-Lives100% (Mathematical Steady State)

Plasma Level Fluctuations

The way a drug is administered determines how smooth that steady state is:

  • Continuous IV Infusion: Provides a perfectly flat, smooth steady state line.
  • Intermittent Dosing (e.g., Oral pills every 8 hours): Creates oscillations. The plasma level spikes after taking the pill (Peak/C-max) and drops right before the next pill (Trough/C-min). The average between these peaks and troughs is the steady-state concentration.

To minimize severe fluctuations (which could cause toxicity at the peak, or loss of effect at the trough), doctors prefer to divide the total daily dose into smaller, more frequent doses, or use sustained-release drug formulations. However, patient compliance drops if they have to take pills too frequently.


Clinical Significance: Dosing Equations

Using these pharmacokinetic principles, doctors can precisely calculate how to dose a patient.

1. Maintenance Dose (MD)

Once steady state is reached, you only need to administer enough drug to replace what the body cleared. Since Rate In = Rate Out, the Maintenance Dose rate must equal the Elimination Rate.

MD = (Clearance × Target C ss × τ) / F

Where τ (tau) = dosing interval (e.g., every 8 hours), and F = Bioavailability fraction (For IV drugs, F = 1).

2. Infusion Rate (k 0)

If giving a continuous IV drip, you want to set the machine's rate to exactly match clearance.

If the rate of infusion is doubled, the resulting steady-state plasma level will exactly double (linear kinetics).

k 0 = Clearance × Target C ss

3. Loading Dose (LD)

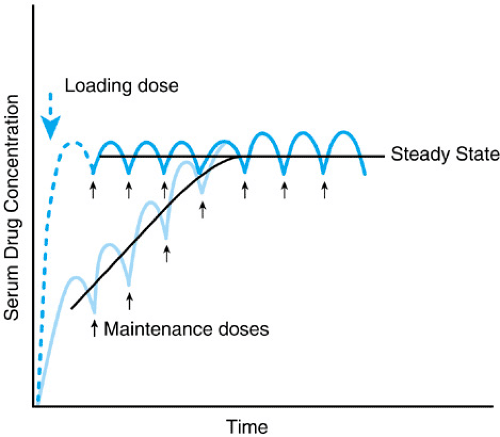
The Problem: For drugs with very long half-lives (e.g., Digitoxin, Methadone), waiting 4 to 5 half-lives to reach steady state could mean waiting weeks for the drug to start working effectively. In emergencies, this is unacceptable.

The Solution: Give a large, one-time Loading Dose to instantly fill the body's Volume of Distribution (V d) up to the target steady-state concentration.

LD = (V d × Target C ss) / F
Important Note: The loading dose depends only on the Volume of Distribution (V d), whereas the maintenance dose depends only on Clearance (Cl).

If a drug is given exactly every half-life, the mathematically calculated Loading Dose will be exactly twice the Maintenance Dose.

Change in Elimination Characteristics During Therapy

Steady state calculations assume the body's physiology remains constant. In the real world, patients change:

  • Acceleration of Elimination (Enzyme Induction): Some drugs force the liver to produce more metabolic enzymes. This clears drugs faster. Consequently, the steady-state plasma level will steadily decline, and the drug effect may diminish or disappear completely unless the dose is increased.
  • Changes in Urinary pH: Diet or concurrent medications can alter urine pH, increasing the excretion of certain drugs (as discussed in Ion Trapping).
  • Inhibition or Impairment of Elimination: If a patient develops progressive renal insufficiency (kidney failure) or liver disease, the body's clearance plummets. If the doctor does not adjust the dose, the steady-state level will aggressively rise, potentially entering the toxic concentration range.


Detailed Pharmacokinetics: Clearance & Dosing Mathematics

An exhaustive, elaborated continuation focusing strictly on Clearance, Mathematical Relationships, and Clinical Dosing (Excluding basic Steady State definitions).

1. The Fundamental Concept of Clearance (Cl)

To safely dose a patient, a physician must know exactly how efficiently the patient's body removes the drug. This is quantified by Clearance (Cl).

Definition & Simplification

Clearance of a drug is the theoretical VOLUME of plasma from which a drug is completely removed (freed) in a unit of time.

Simplification: Do not think of clearance as an "amount" of drug (like 10 mg/hour). Think of it strictly as a volume of blood being purified. If a drug's clearance is 50 ml/min, it means the kidneys/liver act like a filter that completely scrubs all drug molecules out of 50 milliliters of blood every single minute.

  • It is expressed in units of volume per time, typically ml/min or Liters/hour.
  • For any drug following first-order kinetics, clearance is a constant for any given plasma drug concentration.
  • It serves as the ultimate estimate of the function of the organs of elimination (kidneys, liver, etc.) and the rate of removal of the drug from the body.
Clearance (Cl) = Rate of Elimination (mg/hr) / Plasma Drug Concentration (mg/L)

Mathematically, Clearance is the proportionality factor used to determine the exact rate of elimination. If you know the clearance and the concentration in the blood, you can calculate exactly how many milligrams are leaving the body per hour.

Conditions for Clearance

  • First-Order Kinetics: Cl remains absolutely constant.
  • Relation to GFR: Cl is exactly equal to the Glomerular Filtration Rate (GFR) only when there is no tubular reabsorption, no active tubular secretion, and no plasma protein binding.
  • Protein Binding Limitation: Protein-bound drug is not cleared by glomerular filtration because the proteins are too large to pass through the kidney's filter.

Therefore, the true clearance of a filtered drug is dictated by its free fraction:
Cl = Free Fraction × GFR


Types of Clearance & Affecting Factors


A. Total Body Clearance

This is the big picture. It is the total plasma volume cleared of the drug per unit of time via the elimination of the drug from all biotransformation (liver) and excretion (kidneys, lungs, bile) mechanisms combined in the entire body.

B. Renal Clearance

This is organ-specific. It is described strictly as the rate of the excretion of a drug specifically from the kidneys. In other words, it is the volume of plasma cleared from the non-metabolized (unchanged) drug via excretion by the kidneys per minute.

Four Important Factors Affecting Renal Clearance

Because renal clearance is a physical process happening in the kidney tubules, it is directly influenced by four biological factors:

  1. Plasma protein binding of the drug: High binding drastically reduces clearance because the drug cannot be filtered at the glomerulus.
  2. Tubular reabsorption ratio of the drug: High reabsorption (drug moving from urine back into blood) reduces net clearance.
  3. Tubular secretion ratio of the drug: High active secretion (pumping drug directly from blood into urine) drastically increases clearance.
  4. Glomerular filtration ratio (GFR) of the drug: A higher GFR (healthy kidneys) means more plasma is filtered, increasing clearance.
  5. Advertisements


The Mathematical Relationship: Clearance, Elimination & Half-Life

The speed at which a drug leaves the body is a delicate balance between how efficiently the body clears it (Cl) and how deeply the drug is hiding in the body's tissues (Volume of Distribution, V d).

  • Core Principle: The faster the clearance, the better (more rapid) the elimination.
  • Clearance (Cl) is directly proportional to the elimination rate constant (k). Written as: Cl ∝ k.

Deriving the Ultimate Half-Life Equation

Let's trace the logic step-by-step from the lecture slides to see how we calculate half-life (T 1/2):

  1. We know the unit for Clearance (Cl) is Volume / Time.
  2. Therefore, we can express it as: Cl = V d × (1/t) (where V d is Volume of Distribution).
  3. The elimination rate constant (k) represents 1/t. Therefore: Cl = V d × k.
  4. Rearranging to solve for k, we get: k = Cl / V d.
  5. The formula for half-life in first-order kinetics is: T 1/2 = 0.693 / k (often rounded to 0.7 for simplicity).
  6. By substituting our k value into the half-life formula, we get the master equation:
T 1/2 = (0.693 × V d) / Clearance (Cl)

Important Points to Remember About This Half-Life Equation:

  • Inverse Proportion to Clearance: Elimination half-life is inversely (negatively) proportional to clearance. If a patient has highly efficient kidneys (large Cl), the denominator is large, making the half-life (T 1/2) very short.
  • Direct Proportion to Volume of Distribution (V d): Elimination half-life is directly proportional to the volume of distribution. Why? The higher the duration of stay of that drug in the body, the more it becomes distributed to peripheral tissues (hence, a higher volume of distribution). Because the drug is hiding in the fat and tissues, it is not in the blood, meaning the kidneys cannot clear it. Therefore, a massive V d results in a massive (long) half-life.
  • Metabolism: The plasma concentration of the drug is directly proportional to the rate of metabolism.
  • Clinical Importance: Half-life and drug clearance are practically used to predict how long it takes for a periodic dosing regimen to achieve steady-state concentrations. Half-life establishes how often the drug must be administered (the dosing interval) to prevent dangerous drug accumulation, especially for drugs with a very long t 1/2.

Calculating Renal Elimination & The Role of Inulin

The total rate of renal elimination can be summarized as:

Rate of Elimination = Glomerular Filtration Rate (GFR) + Active Secretion - Reabsorption (active or passive)

Remember, filtration is a non-saturable linear function. Both ionized and non-ionized forms of drugs are filtered freely, but protein-bound drug molecules are absolutely not.

The Marker for GFR: Inulin

To measure a patient's exact GFR, doctors use a substance called Inulin (not to be confused with insulin). Inulin clearance is the perfect estimate for GFR because it possesses unique properties: it is 100% filtered, and it is strictly NOT reabsorbed AND NOT secreted. Whatever amount is filtered is exactly the amount that ends up in the urine.

A normal, healthy GFR measured by inulin clearance is close to 120 ml/min.

Renal Clearance (CL R) = (V × C U) / (t × C P)
  • V = Collected urine volume (amount of urine the patient produced).
  • t = Duration to collect the urine (time).
  • C P = Plasma concentration of the drug.
  • C U = Urine concentration of the drug.

Relationship Between Renal Clearance Values & Mechanism

By calculating the Renal Clearance of an unknown drug and comparing it to the standard GFR (120-130 ml/min), pharmacologists can instantly deduce exactly how the kidney is handling that specific drug.

Renal Clearance Value (ml/min)Renal Clearance Ratio (Drug Cl / GFR)Mechanism of Renal Clearance inside the KidneyClassic Examples
0 (Least Value)0Drug is filtered at the glomerulus, but then 100% is reabsorbed completely back into the bloodstream.Glucose. (Healthy kidneys reabsorb all sugar; none should appear in urine).
< 130Above 0, Below 1Drug is filtered, and then partially reabsorbed.Lipophilic drugs. (Fat-soluble drugs passively diffuse back into the blood).
Exactly 130 (Equal to GFR)1Drug is filtered only. Zero reabsorption, zero active secretion.Creatinine, Inulin.
> 130> 1Drug is filtered, AND it is actively secreted into the urine via transport pumps.Polar, ionic drugs. (e.g., Penicillin is actively pumped out).
~ 650 (Highest Value)5Clearance is equal to the total Renal Plasma Flow Rate. 100% of the drug that arrives at the kidney is immediately ripped from the blood and dumped into the urine.Iodopyracet, PAH (Para-aminohippurate).

Changes in Elimination Characteristics During Therapy

When a patient takes a drug regularly, the goal is to accumulate the drug to a desired, steady plasma level. However, a clinician must remember that conditions for biotransformation (liver) and excretion (kidney) do not necessarily remain constant over time.

  • Acceleration of Elimination: Elimination may suddenly be hastened due to enzyme induction (the liver produces more metabolic enzymes due to repeated exposure to the drug) or due to a change in urinary pH (which causes ion trapping in the urine).
    • Consequence: The steady-state plasma level declines to a new, lower value corresponding to the faster rate of elimination. The drug effect may dangerously diminish or disappear entirely.
  • Inhibition / Impairment of Elimination: Conversely, elimination can be impaired (e.g., a patient developing progressive renal insufficiency/kidney failure, or taking a second drug that inhibits liver enzymes).
    • Consequence: Because the drug cannot leave the body, the mean plasma level of renally eliminated drugs rapidly rises and may enter a toxic concentration range, leading to overdose symptoms despite taking a "normal" dose.

Clinical Dosing: Rate of Infusion (k o) and Loading Dose (LD)

Rate of Infusion (k o)

When giving a drug via an IV drip, the rate of infusion directly determines the final plasma level at steady state. Because this operates on linear (first-order) kinetics:

  • If the rate of infusion is doubled, then the plasma level of the drug at steady state is exactly doubled.
  • A similar relationship exists for oral administration: doubling the oral dose will double the average plasma levels of a drug.
  • Plotting dose against plasma concentration yields a perfect straight line.
Crucial Note: Regardless of the rate of infusion, it takes the exact same amount of time (4-5 half-lives) to reach the steady state. Pumping the drug in faster does NOT get you to a steady state faster; it just means the final steady state plateau will be much higher.

The Loading Dose (LD)

We know it takes 4 to 5 half-lives to achieve a steady state. For drugs that are eliminated very slowly (e.g., phenprocoumon, digitoxin, methadone), the optimal, effective plasma level would only be attained after a very long period (sometimes weeks).

To solve this, doctors use a Loading Dose. This is an initial, abnormally high dose given to rapidly bypass the waiting period and instantly achieve effective blood levels.

  • Loading doses are often a one-time only administration.
  • They are mathematically estimated to put into the body the exact total amount of drug that should be there once a steady state is naturally reached.
  • Example Rule: If doses are to be administered at an interval exactly equal to the half-life of the drug, then the loading dose is exactly twice the amount of the dose used for maintenance (assuming normal clearance and identical bioavailability).
LD = (Volume of Distribution (V d) × Target Plasma Concentration (C ss)) / Bioavailability (F)

Notice that the Loading Dose equation relies on the Volume of Distribution (V d) to know how much fluid needs to be "filled up" with the drug.


Maintenance Dose (MD) & Master Equation Summary

Once the Loading Dose has forced the patient's blood up to the target concentration, the doctor switches to a Maintenance Dose. The goal of the maintenance dose is simply to replace exactly what the body is eliminating.

Deriving the Maintenance Dose:

  1. At steady state, the system is perfectly balanced: Rate In = Rate Out.
  2. The "Rate Out" is determined by Clearance. Therefore, Rate Out = C ss × Cl.
  3. The "Rate In" is your dosing. If you give a Maintenance Dose (MD) every dosing interval (τ), the Rate In = MD / τ.
  4. Setting them equal: MD / τ = C ss × Cl.
  5. Solving for MD gives the final formula: MD = C ss × Cl × τ.
MD = (Clearance (Cl) × Target Plasma Concentration (C ss) × Dosing Interval (τ)) / Bioavailability (F)

Notice that the Maintenance Dose relies strictly on Clearance (Cl), because you only need to replace what the body clears.

Comprehensive Master List of Pharmacokinetic Equations

The following relationships are critical for clinical calculations:

Legend of Variables

C 0 = Concentration at time zeroCl = Clearance
C p = Concentration in plasmaC ss = Steady state concentration
D = DoseF = Bioavailability (Fraction reaching systemic circulation)
k o = Infusion rateLD = Loading dose
MD = Maintenance doseτ (tau) = Dosing interval (e.g., every 8 hours)
V d = Volume of distributiont 1/2 = Half-life

1. Single-Dose Equations

  • Volume of Distribution: V d = D / C 0
  • Half-Life: t 1/2 = (0.7 × V d) / Cl

2. Multiple Doses or Infusion Rate Equations

  • Infusion Rate (k o): k o = Cl × C ss
  • Loading Dose (LD): LD = V d × C ss
  • Maintenance Dose (MD): MD = Cl × C ss × τ

Note: For oral dosing, always divide the final LD or MD calculation by the bioavailability fraction (F) to account for drug lost to first-pass metabolism or poor absorption.

Quick Quiz

Elimination & Clearance Quiz

Pharmacology

Privacy: Your details are used only for quiz tracking and certificates.

Advertisements

Elimination & Clearance of Drugs Read More »

Metabolism of Drugs

Metabolism of Drugs

Metabolism of Drugs

Drug Metabolism (Biotransformation)

How to Approach This Topic

Many students fear "Drug Metabolism" because of the heavy biochemistry and enzyme names. Do not panic. Think of drug metabolism simply as the body's waste management system. The body wants to get rid of foreign chemicals (drugs). To do this, it must change their shape and properties so they can be flushed down the drain (kidneys). This guide will break down every mechanism, enzyme, and clinical scenario so you understand the "why" behind the science.


Drug Metabolism

Drug metabolism, also known as Biotransformation, is a core pillar of Pharmacokinetics. Remember the acronym ADME: Absorption, Distribution, Metabolism, and Excretion. Metabolism bridges the gap between a drug moving through your tissues and a drug leaving your body.
The Journey of a Drug:

  • Dose → Absorption → Blood Plasma (Free vs. Protein-Bound) → Distribution to Tissues/Receptors (Effect) → METABOLISM → Elimination (Renal Excretion).

Why is Metabolism Absolutely Necessary?

  • The Fundamental Problem: Most drugs that enter the body are designed to be lipophilic (fat-soluble). They need to be lipophilic so they can easily diffuse through the lipophilic cell membranes in your gut to be absorbed, and cross into tissues (like the brain) to exert their effects.
  • The Catch-22: The kidneys (the body's main filter) cannot efficiently excrete lipophilic drugs. When blood is filtered through the renal glomerulus, lipid-soluble drugs simply slide right back through the renal tubule membranes and are reabsorbed back into the systemic circulation. If we couldn't metabolize them, lipophilic drugs would stay in the body forever, leading to massive accumulation and fatal toxicity.

The Solution: The Definition of Metabolism

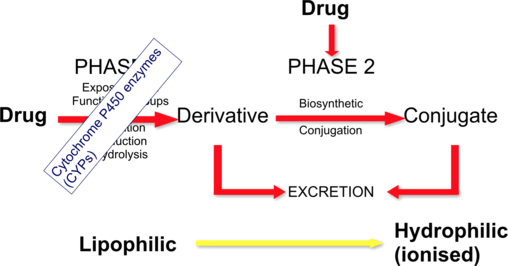
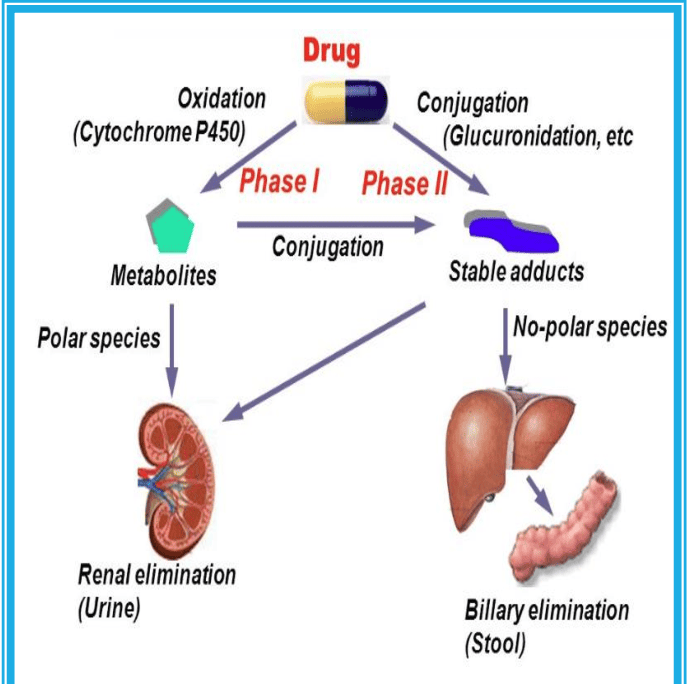
Metabolism is the process where a drug is structurally altered (biotransformed) to become more polar and hydrophilic (water-soluble) so that it can be trapped in the urine and excreted.

Analogy: Imagine trying to wash engine grease (a lipophilic drug) off your hands using only water (urine). It doesn't work; the grease clings to your skin. You need soap (metabolism) to chemically alter the grease, making it mix with water so it can be rinsed down the drain.


The Four Consequences of Drug Alteration

When the body chemically alters a drug, four different clinical outcomes can occur. Metabolism doesn't just mean destroying a drug; it means changing its pharmacological activity.

1. Most Common

Active Drug → Inactive Metabolite

The standard detoxifying process. The drug does its job, and the liver shuts it off.

  • Examples: Paracetamol, Ibuprofen, Chloramphenicol.
2. Unpredictable

Active Drug → Active or Toxic Metabolite

Sometimes, the body's attempt to alter a drug creates a byproduct that still has a therapeutic effect, or worse, is highly toxic.

3. Metabolic Activation

Inactive Prodrug → Active Drug

A Prodrug is a drug administered in an inactive form. It relies entirely on the body's metabolism to activate it. We use prodrugs to improve absorption or bypass harsh stomach acid.

4. Clearance

Unexcretable (Lipophilic) → Excretable (Hydrophilic)

The structural conversion that allows final renal clearance and removal from the body.

Consequence Tables

Original Active DrugActive/Toxic Metabolite Formed (Outcome 2)
Allopurinol (Gout medication)Alloxanthine (Also lowers uric acid)
DigitoxinDigoxin (Active heart medication)
MorphineMorphine-6-glucuronide (Highly active painkiller)
Chloral hydrateTrichloroethanol
Inactive ProdrugActive Metabolite (The functional drug) (Outcome 3)
Levodopa (Crosses Blood-Brain Barrier)Dopamine (Treats Parkinson's Disease)
SulindacSulfide metabolite
PrednisonePrednisolone (Active anti-inflammatory)

Where Does Drug Metabolism Occur?

While enzymes capable of biotransformation exist in almost every tissue (gut, lung, kidney, skin, placenta), the LIVER is the undisputed chief organ for drug metabolism. Nearly 90% of all drug metabolism happens here.

Why the Liver?

  • Blood Supply: The liver receives massive blood flow, specifically from the portal vein, which brings blood directly from the digestive tract.
  • Enzyme Concentration: Liver cells (Hepatocytes) contain the body's full complement of metabolizing enzymes in their smooth endoplasmic reticulum (ER), cytosol, and mitochondria.
Crucial Concept

The First-Pass Effect

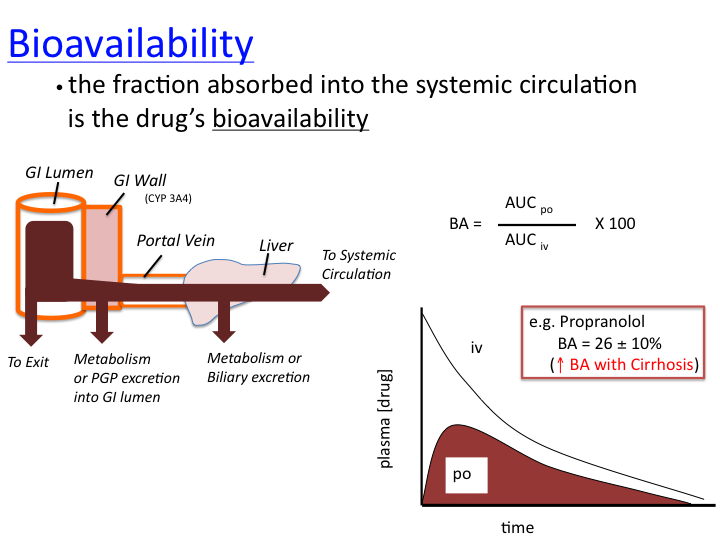
When you swallow a pill (PO - Per Os), it is absorbed in the intestines and goes into the portal vein. The portal vein goes straight to the liver before the drug reaches the rest of the body. The liver enzymes immediately metabolize a large portion of the drug. This "first-pass" can drastically reduce the amount of active drug that makes it to systemic circulation (bioavailability). If a drug has massive first-pass metabolism, it must be given via IV, sublingually, or transdermally to bypass the liver initially.

Levels of Metabolism by Organ:

  • High: Liver
  • Medium: Lung, Kidney, Intestine
  • Low: Skin, Testes, Placenta, Adrenals
  • Very Low: Nervous System

Reactions of Drug Metabolism: Phase I & Phase II

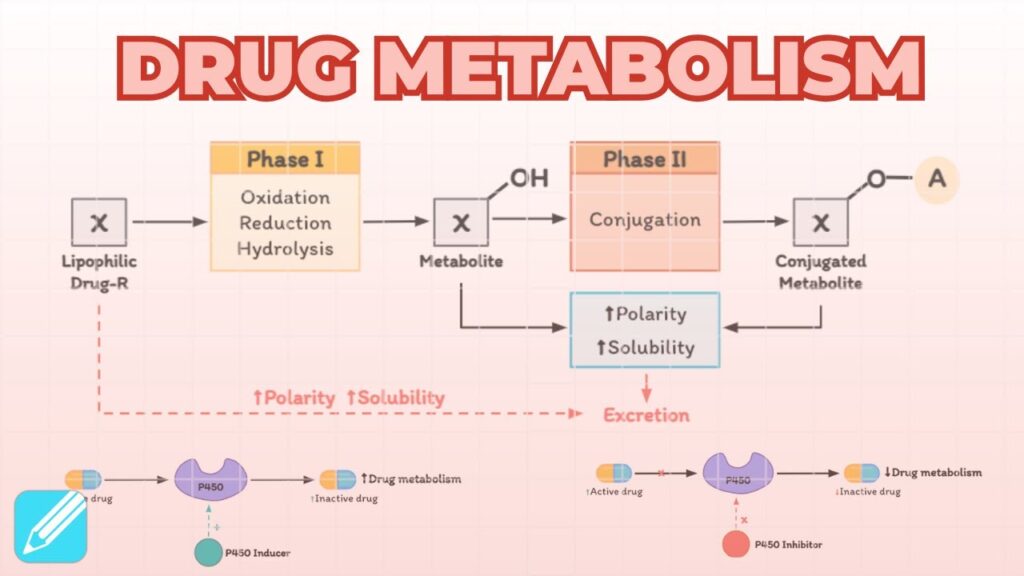
To turn a stubborn, lipophilic drug into a water-soluble waste product, the liver uses a two-step process: Phase I and Phase II. (Note: Not all drugs go through both; some skip Phase I, some skip Phase II, and some go in reverse, but the standard sequence is I → II).

Advertisements

Phase I Reactions: Modification (Functionalization)

Goal: To modify the drug by unmasking or adding a small, polar "chemical hook" (like an -OH, -NH2, or -COOH group). This makes the drug slightly more water-soluble, but more importantly, it provides a handle for Phase II enzymes to grab onto.

Types of Phase I Reactions:

  • Oxidation: The most common. Involves the addition of oxygen or removal of hydrogen (e.g., converting a C-H bond to a C-OH bond: Hydroxylation, Dealkylation).
  • Reduction: Addition of hydrogen.
  • Hydrolysis: Breaking bonds using water.

The Enzymes of Phase I

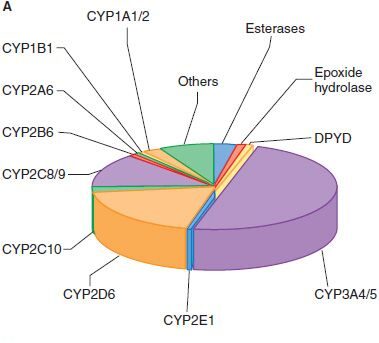
Phase 1 is dominated by the Cytochrome P450 (CYP450) superfamily of enzymes, responsible for >95% of oxidative metabolism. They are located in the microsomes of the smooth endoplasmic reticulum (hence called microsomal monooxygenase enzymes).

Understanding CYP450 Nomenclature:
There are at least 18 different forms in humans. Take the most important one: CYP3A4 (which metabolizes ~50% of all drugs alone).

  • CYP = Cytochrome P450
  • 3 = Family (Families 1, 2, and 3 handle most drug metabolism)
  • A = Subfamily
  • 4 = Specific individual enzyme gene

Overall, 60% of all drugs are metabolized primarily by the CYP450 family.

Non-CYP Enzymes in Phase I (<5% of metabolism):

  • Monoamine Oxidase (MAO): Found in mitochondria. Oxidizes endogenous neurotransmitters (dopamine, serotonin, epinephrine) and drugs related to them.
  • Alcohol & Aldehyde Dehydrogenase: Found in liver cytosol. Responsible for breaking down ethanol (alcohol).
  • Xanthine Oxidase (XO): Converts hypoxanthine to xanthine, and then to uric acid. Target for gout drugs (Theophylline, 6-mercaptopurine).
  • Esterases: Hydrolyze endogenous substances (e.g., Acetylcholinesterase breaks down acetylcholine).

Phase II Reactions: Conjugation

Goal: If Phase I added a "hitch" to the drug, Phase II attaches a massive, heavy, highly polar "trailer" to that hitch. This process is called Conjugation.

Phase II enzymes attach large, endogenous, water-soluble molecules to the -OH, -NH2, or -SH functional groups created in Phase I. This effectively inactivates the drug and makes it highly lipid-insoluble, guaranteeing its rapid excretion in urine or bile.

The 6 Types of Phase II Conjugation Reactions

These require specific transferase enzymes to link the endogenous compound to the drug.

1. Glucuronidation (Addition of Glucuronate)
  • Enzyme: UDP-glucuronosyltransferase.
  • Details: The most common Phase II reaction. It is highly inducible.

  • Examples: Digoxin, Morphine, Paracetamol, Bilirubin.

  • Clinical Scenario (Neonates): Newborns have very low activity of UDP-glucuronosyltransferase. Bilirubin accumulation causes Neonatal Jaundice. Lack of conjugation of chloramphenicol causes the fatal "Gray Baby Syndrome."
2. Acetylation (Addition of Acetate)
  • Enzyme: Acetyltransferase.
  • Examples: Isoniazid (Anti-TB drug), Dapsone, Hydralazine, Procainamide.
  • Clinical Scenario (Genetics): Humans are genetically divided into "Fast" and "Slow" acetylators. Slow acetylators taking Hydralazine or Procainamide can develop Drug-Induced Systemic Lupus Erythematosus (SLE).
3. Glutathione Conjugation (Addition of Glutathione)
  • Enzyme: Glutathione transferase.
  • Details: Glutathione is the body's primary antioxidant. This pathway neutralizes free radicals and highly reactive, toxic metabolites.
  • Examples: Methyldopa, Paracetamol.
4. Methylation (Addition of a Methyl Group)
  • Enzyme: Methyltransferase.
  • Example: Inactivation of Histamine.
5. Sulfation (Addition of Sulphate)
  • Enzyme: Sulphate transferase.
  • Examples: Almost all steroid hormones, Salbutamol (asthma inhaler), Paracetamol.
6. Addition of Glycine
  • Details: Less common, generally pairs with benzoic acid derivatives.
Deeper

Paracetamol (Acetaminophen) Toxicity Pathway

This is a classic, heavily tested scenario that proves why Phase I and Phase II balance is critical for survival.

  • Normal Doses: ~95% of paracetamol skips Phase I entirely. It goes straight to Phase II, where it safely undergoes Glucuronidation and Sulfation to form non-toxic metabolites excreted in urine.
  • The Danger (Phase I): The remaining ~5% goes through Phase I via CYP450 2E1. This oxidation creates a highly reactive, highly toxic free radical metabolite called NAPQI (N-acetyl-p-benzo-quinone imine).
  • The Savior (Phase II): Normally, Phase II Glutathione conjugation immediately binds to NAPQI, neutralizing it into harmless mercapturic acid.
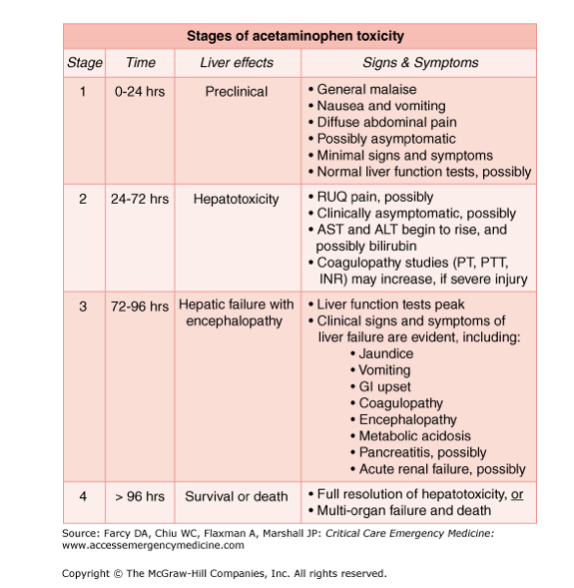
  • The Overdose Scenario: In an overdose, the glucuronidation and sulfation pathways get saturated (full). The body pushes the massive excess of paracetamol down the CYP450 2E1 pathway, generating massive amounts of toxic NAPQI. The liver's supply of Glutathione is rapidly depleted. Unbound NAPQI begins binding covalently to hepatic cell proteins, causing severe Hepatotoxicity (liver death).
  • The Antidote: We administer NAC (N-acetylcysteine), which acts as a substitute for depleted glutathione to bind and neutralize the toxic NAPQI.

Factors Affecting Drug Metabolism

Drug metabolism is an enzymatic process. Therefore, anything that affects enzymes affects metabolism. This leads to massive inter-individual variability (why a dose that cures one patient might poison another).

Advertisements

A. Environmental Factors: Enzyme Induction vs. Inhibition

Exposure to certain exogenous compounds (other drugs, food, environmental pollutants, smoke) can modulate enzyme activity.

1. Enzyme Induction (Speeding up)

  • Mechanism: Exposure to an inducer stimulates the DNA to synthesize more CYP450 enzymes. The metabolic capacity increases, so the drug is metabolized and cleared much faster.
  • Consequences of Induction:
    • Increased rate of metabolism.
    • Decreased plasma concentration of the drug.
    • Reduced bioavailability and Reduced efficacy (the drug stops working).
    • Exception: If the drug is a prodrug or has a toxic metabolite, induction leads to increased toxicity.
  • Therapeutic Implication: Dosing rates must be increased to maintain effective blood levels. Be careful: it takes days to weeks for induction to fully occur and wear off.
  • Classic General Inducers: Anticonvulsants (Phenobarbital, Phenytoin, Carbamazepine), Antibiotics (Rifampin), Chronic Alcohol use, St. John's Wort. Cigarette smoking specifically induces CYP1A2 (smokers require higher doses of Theophylline).

2. Enzyme Inhibition (Slowing down)

  • Mechanism: Inhibitors block the enzyme from working. This can occur rapidly with no warning. Types of inhibition include:
    • Competition: A high-affinity drug hogs the active site, slowing metabolism of a lower-affinity drug.
    • Irreversible Inactivation: The drug forms a complex with the heme iron of CYP450 (e.g., Cimetidine, Ketoconazole) or destroys the heme group entirely (Secobarbital).
    • Depletion of Cofactors: E.g., running out of NADH2 for Phase II.
  • Consequences of Inhibition:
    • Increase in plasma concentration of the parent drug.
    • Reduction in metabolite concentration.
    • Exaggerated, prolonged pharmacological effects.
    • High likelihood of drug-induced toxicity.
  • Classic General Inhibitors: Anti-ulcer meds (Cimetidine, Omeprazole), Antimicrobials (Chloramphenicol, Macrolides, Ritonavir, Ketoconazole, Quinolones/Ciprofloxacin), Acute Alcohol ingestion, Grapefruit Juice (potent inhibitor of CYP3A4).

B. Disease Factors

Since the liver is the primary metabolic factory, Liver Disease (Cirrhosis, Alcoholic liver disease, Jaundice, Hepatic Carcinoma) severely impairs metabolism. There is less functional liver mass and decreased enzyme activity. This reduces the first-pass effect, potentially increasing bioavailability by 2-4x, leading to exaggerated responses and severe adverse effects unless drug doses are heavily reduced.

C. Age and Sex

  • Newborns and Infants: Metabolize drugs slowly because their liver enzyme systems are immature and underdeveloped.
  • Adolescents/Adults: Full metabolic maturity appears in the second decade of life.
  • Elderly: Experience a slow decline in metabolic function associated with aging (decreased liver mass and hepatic blood flow).

D. Genetic Variation (Polymorphism)

Genetic Polymorphism refers to the existence of multiple forms of a DNA sequence at a specific locus within a population. It creates distinct subgroups of people who differ drastically in their ability to perform biotransformation.

Changes in a single allele (Single Nucleotide Polymorphisms or SNPs) dictate the phenotype (observable physical/biochemical function) of the enzyme. Mutations can cause decreased, increased, or completely absent enzyme activity.

The Four Metabolic Phenotypes:

1. Poor Metabolizers (PMs)
  • Carry 2 defective alleles (e.g., gene deletions or mutations resulting in no functional enzyme).
  • Result: Active drugs build up (high toxicity risk). Prodrugs fail to activate (zero efficacy).
2. Intermediate Metabolizers (IMs)
  • Heterozygous (carry one normal wild-type allele and one defective allele).
  • Slower metabolism than normal, but not absent.
3. Normal / Extensive Metabolizers (EMs)
  • Carry wild-type (normal) alleles.
  • They encode normal enzyme function. This is the baseline population.
4. Ultra-Rapid Metabolizers (UMs)
  • Carry genetic duplications (two or more copies of an amplified gene).
  • Result: Unusually high enzyme activity. Active drugs are cleared so fast they have no therapeutic effect. Prodrugs are activated so fast they can cause sudden toxicity.
Important Note

Genetics vs. Drug Interactions

The Codeine Scenario: Codeine is an inactive prodrug. It must be metabolized (oxidized) by the enzyme CYP2D6 into Morphine to relieve pain.

  • In Poor Metabolizers (PMs), codeine is never converted to morphine. They receive no pain relief.
  • In Ultra-Rapid Metabolizers (UMs), codeine turns into morphine instantly, risking fatal respiratory depression.

Interplay of Genetics and Inducers/Inhibitors:

  • Inhibitors affect EMs more than PMs: If you give an inhibitor to an Extensive (Normal) Metabolizer, their metabolism crashes, and you see a huge change. If you give an inhibitor to a Poor Metabolizer, they already had zero enzyme activity, so nothing changes.
  • Inducers affect PMs more than EMs: Inducing an enzyme in someone who naturally metabolizes poorly causes a massive, highly noticeable relative jump in enzyme activity compared to inducing someone already functioning at maximum normal capacity.

Quick Quiz

Metabolism of Drugs Quiz

Pharmacology

Privacy: Your details are used only for quiz tracking and certificates.

Advertisements

Metabolism of Drugs Read More »

Drug Absorption & Distribution

Drug Absorption & Distribution

Drug Absorption & Distribution

Learning Objectives

By the end of this comprehensive lecture guide, you will be deeply conversant with:

  • Fundamental definitions: What is a drug, and what is pharmacology?
  • The subdivisions of pharmacology, focusing heavily on Pharmacokinetics.
  • The mechanisms, factors, and clinical importance of drug Absorption and Bioavailability.
  • The concept of Drug Distribution across various body fluid compartments.
  • How to define, calculate, and interpret the Volume of Distribution (Vd).
  • The critical role of Plasma Protein Binding and the dangers of drug displacement.
  • Physiological factors affecting distribution (Blood Brain Barrier, tissue binding, pathology).

What is a Drug?

In pharmacology, a drug is defined as any chemical agent which affects any biological process. This is a very broad definition intentionally. It does not just mean medicine prescribed by a doctor; it includes naturally occurring substances, synthetic laboratory chemicals, recreational substances, and even everyday items like caffeine or alcohol, provided they cause a change in biological function when introduced to the body.

What is Pharmacology?

Pharmacology is the overarching scientific study of how drugs affect biological systems. To make this massive field manageable, it is divided into several specific sub-disciplines:

Pharmacokinetics

Simply put, this is what the body does to the drug. It covers how the drug moves through the body over time.

Pharmacodynamics

This is what the drug does to the body. It involves the molecular mechanisms, receptor binding, and physiological effects (e.g., lowering blood pressure).

Pharmacotherapeutics

The clinical study of the practical use of drugs to prevent, treat, or diagnose disease.

Pharmacocognosy

The highly specialized branch dealing with the identification of crude materials (like medicinal plants, herbs, or animal extracts) as potential drugs.

Toxicology

The study of the poisonous, adverse, or toxic effects of chemicals on living organisms.


Introduction to Pharmacokinetics

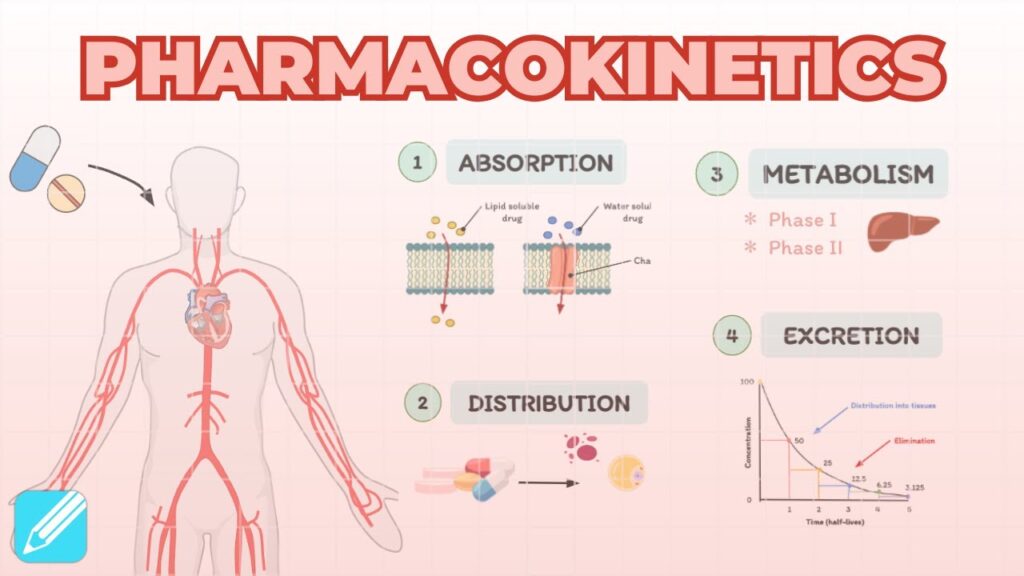
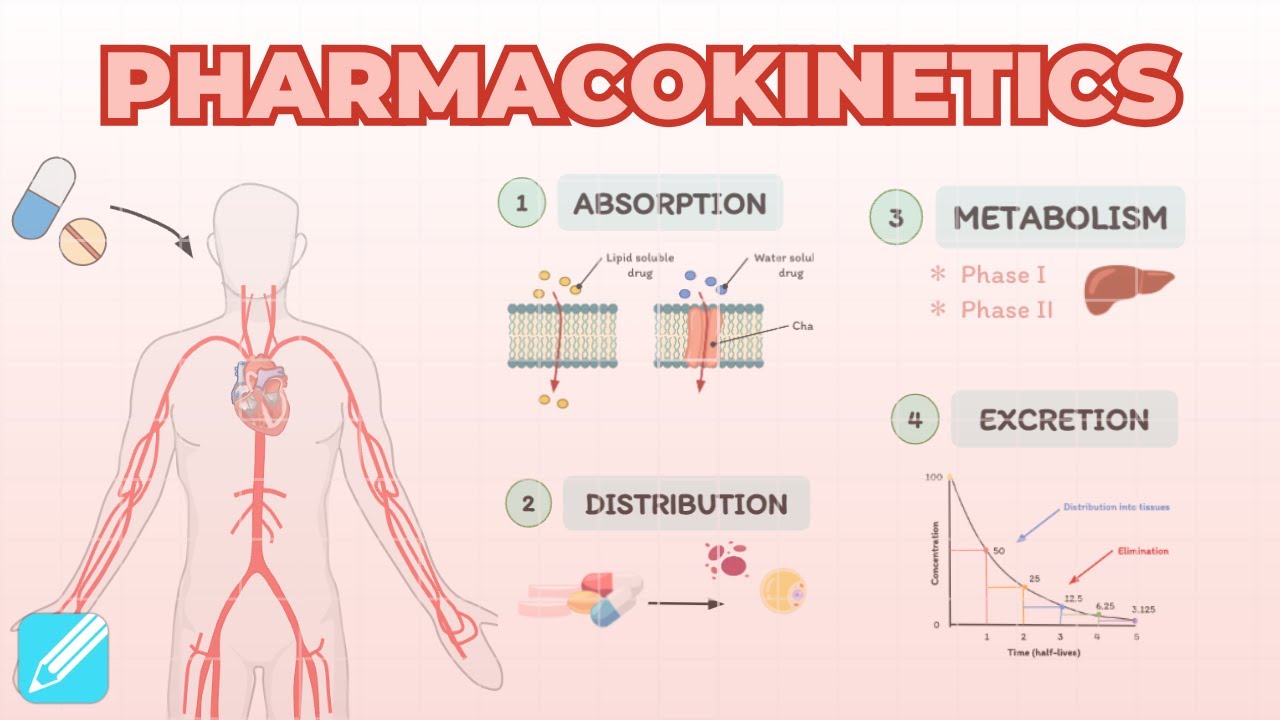
Pharmacokinetics is the journey of the drug through the body. It dictates how much of a dose actually reaches the target organ and how long it stays there. It is defined by four core processes (remembered by the acronym ADME):

  • Absorption: The drug entering the blood.
  • Distribution: The drug traveling via the blood to tissues.
  • Metabolism (Biotransformation): The body (usually the liver) chemically altering the drug.
  • Excretion: The body (usually the kidneys) removing the drug.

Absorption of the Drug

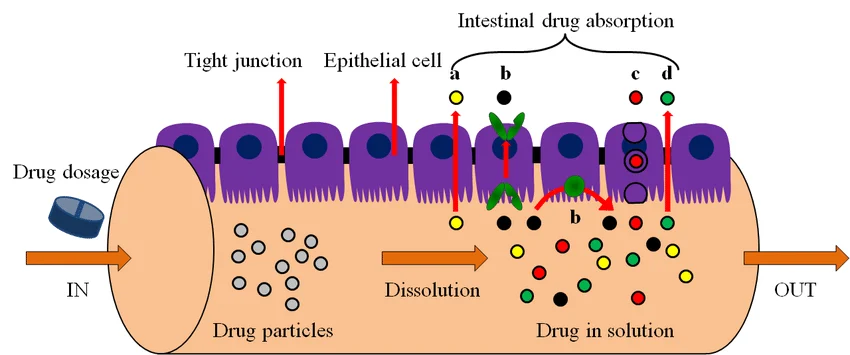
Absorption is the crucial first stage. It is defined as the process that involves the movement (transportation or passage) of a drug from its site or route of administration (e.g., the gut for an oral pill, the muscle for an injection) across biological membranes into the systemic blood stream.


Mechanisms Used by Drugs to Cross Membranes

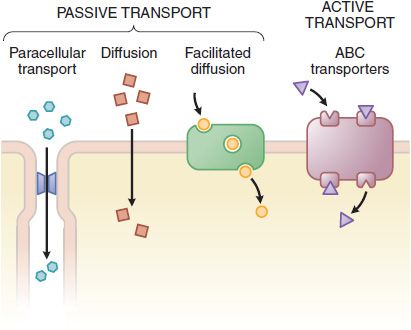
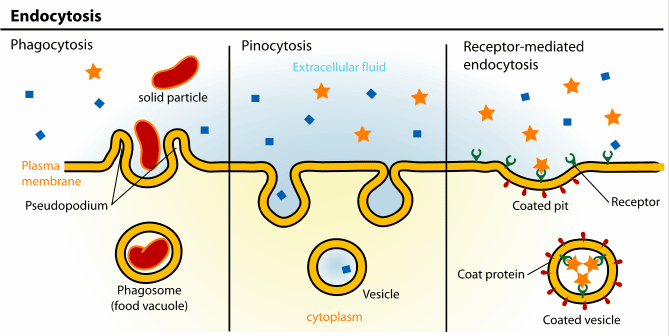
Cell membranes are essentially biological barriers made of a lipid (fat) bilayer. Drugs must navigate this barrier using one of four primary mechanisms:


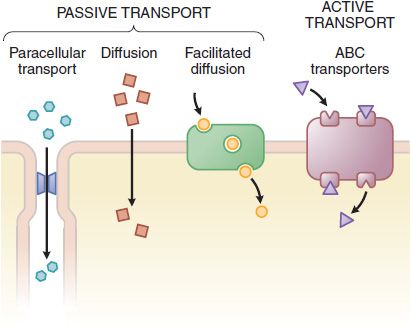
1. Simple (Passive) Diffusion

This is the most common way drugs are absorbed. "Passive" means it happens naturally without the body spending any energy.

  • Mechanism: Drugs move down a concentration gradient (from an area of high concentration, like the stomach, to an area of low concentration, like the blood).
  • Energy: No energy (ATP) is required.
  • Carriers: There is no use of special transport (carrier) proteins.
  • Saturation: Because there are no carriers to get "full," there is no saturation gradient required; as long as there is a concentration difference, diffusion continues.

Types of Passive Diffusion:

  • Via Aqueous Pores: Highly water-soluble (ionized or polar) drugs slip through tiny water-filled channels or pores in the membrane. Examples: Caffeine, ascorbic acid (Vitamin C), acetylsalicylic acid (Aspirin), nicotinamide. However, because these pores are very small, they play a limited role overall.
  • Via the Lipid Layer: Highly lipid-soluble (non-ionized or non-polar) drugs dissolve directly into and pass through the fat of the cell membrane itself. Examples: Artemisinin, lumefantrine (antimalarials). The lipid layer plays the major role in simple diffusion.

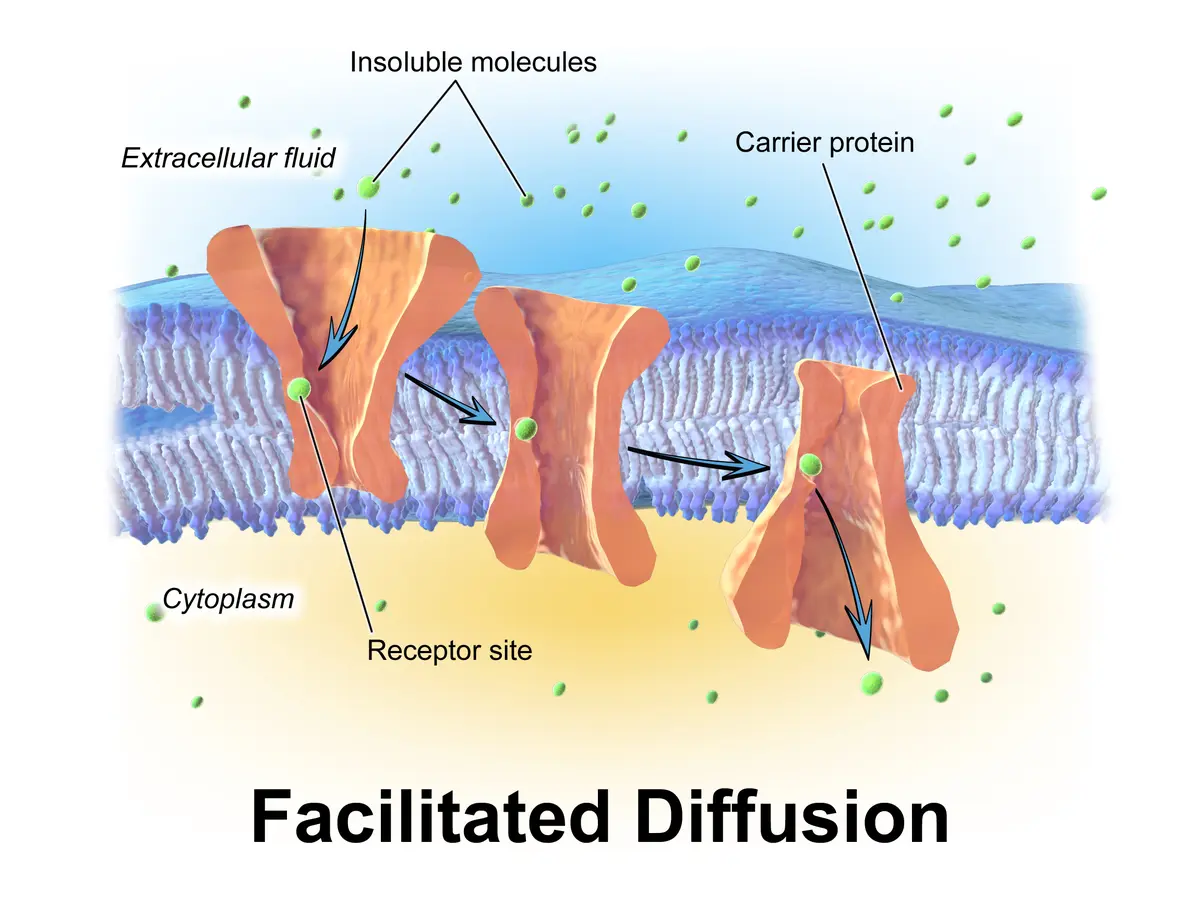
2. Facilitated Diffusion

While still a passive process (no energy used), this mechanism requires a "helper."

  • Mechanism: It occurs by the use of carrier proteins located within the cell membrane. The drug binds to the protein, the protein changes shape, and releases the drug on the other side.
  • Gradient: The net flux is still from high concentration to low concentration.
  • Energy: No energy is required.
  • Saturation: Unlike simple diffusion, this requires a saturable gradient. Since there is a limited number of carrier proteins, if there is too much drug, all carriers become busy (saturated), and absorption maxes out.
  • Examples: It is used for essential molecules that are too large or too polar for simple diffusion, such as amino acids, glucose, and folic acid.

3. Active Transport

This mechanism forces drugs to move where they naturally wouldn't go.

  • Mechanism: Transportation acts against a concentration gradient or an electrochemical gradient (moving from low to high concentration).
  • Energy: It strictly requires cellular energy (ATP) to pump the drug across.
  • Carriers: It requires special transporter (carrier) proteins.
  • Saturation: There is a "transport maximum" (T-max) for the substances; once all pumps are working, rate cannot increase.
  • Rate: The rate of active transport heavily depends on the drug concentration in the environment competing for these pumps.

4. Pinocytosis

Also known as "cell drinking," this is reserved for massive molecules.

  • Mechanism: Drugs with a Molecular Weight (MW) over 900 are transported this way. The drug molecule adheres to the cell membrane. The membrane then invaginates (folds inward), surrounds the drug, and pinches off to form a small intracellular vesicle.
  • Energy: This is a highly active process and requires energy.

Factors Affecting Drug Absorption

Drug absorption is not uniform; it varies wildly based on the nature of the drug and the body itself. These factors are split into two categories.

  1. Dosage Form: Solid drugs (like tablets) must break down before they can be absorbed.
    • Disintegration: Breaking up of the large tablet into smaller granules/pieces after administration.
    • Dissolution: The solid drug entering into a solvent (stomach fluid) to form a completely dissolved liquid solution.
    • Rule of thumb: Solution forms (liquids, syrups) are absorbed much faster than unsolved (solid) forms because they skip the disintegration and dissolution steps.
  2. Chemical Nature: The physical chemistry of the drug matters.
    • Salt Formations: Drugs are often formulated as salts to improve absorption. Salt forms of weak acids (e.g., Sodium, Potassium, Calcium compounds) and weak bases (e.g., HCl, HBr compounds) are much more easily absorbed compared to their original, pure "free" forms.
    • Crystal Forms: An amorphous (unstructured, random) structure of a drug has a higher dissolution rate compared to a tightly packed, rigid crystalline structure.
    • Solvate Form: Drugs can bind to solvent molecules. Hydrates (drugs bound to water molecules) are generally more soluble in water compared to other solvates.
  3. Particle Size: Decreasing the particle size (making the powder finer) drastically increases the total surface area exposed to stomach fluids. This fastens its dissolution, thereby increasing the absorption rate.
  4. Complex Formation: The solubility of poorly soluble drugs can sometimes be increased by forcing them to form a chemical complex with another, highly soluble molecule.
  5. Concentration of the Drug: The higher the concentration of the drug at the administration site, the steeper the concentration gradient, resulting in a higher absorption rate.
  6. Molecular Size: There is a negative relationship between molecular size and absorption rate. As molecular size increases, the ability of the drug to cross membranes decreases, lowering the absorption rate.
  7. Lipid Solubility: Cell membranes are made of lipids. Therefore, the more lipid-soluble a drug is, the easier it crosses the membrane. This is measured by the lipid-water partition coefficient (K). A high coefficient means high lipid solubility, resulting in excellent absorption.
  8. Advertisements

Deeper

Degree of Ionization and the Henderson-Hasselbalch Equation

Most drugs are either weak acids or weak bases. When placed in bodily fluids, they exist in an equilibrium of two forms:

  • Ionized form: Carries an electrical charge. It is water-soluble (hydrophilic) and repelled by cell membranes. (Poorly absorbed).
  • Non-ionized (unionized) form: Carries no charge. It is lipid-soluble (lipophilic) and easily crosses cell membranes. (Highly absorbed).

The ratio of ionized to non-ionized drug is determined by the environmental pH (acidity of the fluid, variable) and the drug's pKa (a constant property of the drug). This relationship is defined by the Henderson-Hasselbalch equation.

The Golden Rule of Ionization:
"Like dissolves like, but like is unionized in like."

  • A weak acid placed in an acidic medium (like the stomach) will remain mostly unionized, meaning it is highly absorbed there.
  • A weak base placed in a basic medium (like the intestines) will remain mostly unionized, meaning it is highly absorbed there.
Clinical Application

Local Anesthetics (LAs)

Local anesthetics (e.g., lidocaine) are weak bases. To work, the uncharged (unionized, RN) form must penetrate the nerve cell membrane. Once inside, the cationic (ionized, RNH+) form binds to the receptor to block pain.

In a healthy tissue, the pH is normal (~7.4). A good anesthetic has a pKa close to this, allowing enough unionized drug to cross the membrane.

What happens in an infected tissue or abscess?
Infected tissues have an acidic pH. Because LAs are weak bases, placing them in an acidic environment forces them to become highly ionized (BH+). This ionized form is hydrophilic and cannot cross the nerve membrane. Therefore, acidic tissues are notoriously difficult to anesthetize, as the acidic pH decreases the potency, speed of onset, and duration of the anesthetic.

Clinical Application

Renal Clearance and Ion Trapping

Ionization isn't just for absorption; it dictates excretion in the kidneys. In the kidney glomerulus, free drugs are filtered into the urine. If the drug is lipid-soluble (unionized), it will simply be reabsorbed back into the blood passively. If the drug is ionized, it gets "trapped" in the filtrate and is excreted in the urine.

Doctors use this to treat drug overdoses:

  • Alkalinization of urine: Giving a patient sodium bicarbonate makes their urine basic. This forces weak acids (like an aspirin overdose) to become ionized in the urine, trapping them there and increasing their renal elimination.
  • Acidification of urine: Giving ammonium chloride makes the urine acidic. This forces weak bases (like an amphetamine overdose) to become ionized, increasing their renal elimination.
  • Blood Flow: If the blood flow is high at the site of application (e.g., a well-perfused muscle vs. subcutaneous fat), the absorbed drug is quickly swept away. This maintains a steep concentration gradient, causing a rapid increase in absorption rate.
  • Area of Absorption: The wider the surface area, the higher the absorption rate. This is why the small intestine (which has massive surface area due to microvilli) absorbs far more drug than the stomach.

Drug Absorption Vs Drug Bioavailability

Absorption is the act of moving into the blood. Bioavailability is a strict measurement of the result.

Definition: Bioavailability is the fraction (or percentage) of the administered dose of a drug that successfully reaches the systemic circulation in an unchanged, active form.

  • By definition, the bioavailability of a drug injected directly into the vein (Intravenously / IV) is exactly 100%, because none of the drug is lost; it goes straight into the blood.
  • Bioavailability of an oral drug is calculated by plotting a graph of Plasma Concentration over Time, and comparing the Area Under the Curve (AUC) of the oral dose to the AUC of an IV dose.
Bioavailability = (AUC oral / AUC injected) x 100

Measuring Bioavailability Indicators

When looking at a plasma concentration-time graph, two key metrics indicate bioavailability:

  • Rate of Absorption (T-max): The time it takes for the drug to reach its maximum peak concentration in the blood. A short T-max means rapid absorption.
  • Extent of Absorption (C-max): The maximum concentration (height of the peak) achieved in the blood. This indicates exactly how much of the dose actually entered circulation.

Factors Influencing Bioavailability

Why isn't an oral pill 100% bioavailable? Several hurdles exist:

  • First Pass Hepatic Metabolism: When a drug is swallowed, it is absorbed from the gut into the portal vein, which goes straight to the liver before reaching the rest of the body. The liver's job is to destroy toxins. If the liver aggressively metabolizes the drug on this "first pass," very little unchanged drug makes it to systemic circulation, severely dropping bioavailability.
  • Solubility of the drug: If it won't dissolve, it won't absorb.
  • Chemical instability: Some drugs are destroyed by the harsh stomach acid (e.g., Penicillin G) or digestive enzymes (e.g., Insulin) before they can be absorbed.
  • Nature of drug formulation: The excipients, binders, and coatings used by the manufacturer affect dissolution. Bioavailability is vital for comparing two different brands of the same drug to ensure they are Bioequivalent (e.g., ensuring generic brand X acts exactly like name brand Y).

Drug Distribution and Fluid Compartments

Once the drug is safely absorbed into the bloodstream, it must travel to its site of action. Drug Distribution is the process by which drugs leave the blood circulation and enter the interstitial fluids (fluid between cells) and/or the intracellular fluids (inside the cells of tissues).

The sequence is: Drug Administration → Absorption → Blood (Plasma) → Extracellular Fluid → Intracellular Fluid.

The Body Fluid Compartments

To understand distribution, we must divide the body's water (which makes up roughly 60% of total body mass, or ~42 Liters in an average adult) into theoretical compartments:

  • Extracellular Fluids (22% of body weight): Fluid outside the cells. Comprised of two sub-compartments:
    • Plasma Fluid: The fluid part of the blood. Represents 5% of body weight, or roughly 4 Liters.
    • Interstitial Fluid: The fluid bathing the tissues outside the blood vessels. Represents 16% of body weight, or roughly 10 Liters.
  • Intracellular Fluids (35% of body weight): The fluid trapped inside all the billions of cells in the body. Roughly 28 Liters.

Volume of Distribution (Vd)

Volume of Distribution (Vd) is a deeply important, yet highly theoretical concept. It answers the question: How much of the drug is distributed into the different body compartments?

It is defined as a hypothetical volume of fluid into which a drug is distributed to produce the concentration observed in the blood plasma. It is the ratio of the drug amount in the entire body (the dose) to the concentration of the drug in the blood.

Vd (Liters) = Dose administered (mg) / Plasma concentration (mg/L)

Why is Vd Important?

Vd is clinically vital for calculating the Loading Dose (a large initial dose given to quickly achieve therapeutic blood levels). Furthermore, a large Vd generally means the drug is hidden deep in the tissues, away from the liver and kidneys, resulting in a long duration of action.

Advertisements

Distribution Scenarios Based on Vd

  1. Drugs restricted to the Plasma Compartment Vd ≈ 4 Liters
    • Characteristics: These drugs have a very large molecular weight, or they bind extensively to plasma proteins. They become physically too large to squeeze out through the endothelial slit junctions of the blood capillaries.
    • Result: They are trapped in the blood vascular compartment, meaning they have a low volume of distribution.
    • Examples: Warfarin (binds heavily to proteins), Heparin (massive molecule).
  2. Drugs distributed into the Extracellular Compartment Vd ≈ 14 Liters
    • Characteristics: These drugs have a low molecular weight, allowing them to pass through the endothelial capillary slits into the interstitial fluid. However, they are highly hydrophilic (water-soluble/lipid-insoluble).
    • Result: Because they are not lipid-soluble, they cannot cross the lipid cell membrane to enter the cells. They are distributed in Plasma (4L) + Interstitial fluid (10L) = 14 Liters. They still have a relatively low Vd.
    • Examples: Mannitol, Gentamycin, Atracurium, Insulin.
  3. Drugs distributed into Total Body Water Vd ≈ 42 Liters
    • Characteristics: These drugs have a low molecular weight and are hydrophobic (lipid-soluble).
    • Result: They easily move out of the capillaries, through the interstitial fluid, and effortlessly cross cell membranes to enter the intracellular fluid. They distribute into the total 42 Liters of body water.
    • Examples: Ethanol (Alcohol) has a Vd equal to total body water (approx 38L, ranging 34-41L).
  4. Drugs heavily distributed intracellularly Very High Vd, often > 42L
    • Characteristics: These are highly lipid-soluble drugs that actively bind to tissues outside of the plasma.
    • Result: Because they hide inside tissues, the concentration remaining in the plasma is very low. Mathematically, dividing the dose by a tiny plasma concentration yields a massive Vd. They have higher concentrations in tissues than in plasma.
    • Examples: Digoxin, Phenytoin, Morphine.


Plasma Protein Binding

After absorption, a drug circulates in the blood in two forms: Free form or Bound to plasma proteins. This binding is dynamic and reversible.

The plasma constitutes several important binding proteins:

  • Albumin: The most abundant protein. Acidic drugs primarily bind to albumin.
  • α1-acid glycoprotein: Basic drugs primarily bind here.
  • Lipoproteins and others.

The Golden Rules of Protein Binding:

  • Bound drugs are kept pharmacologically inactive (only the free fraction can bind to receptors to exert an effect).
  • Bound drugs are physical complexes that are too large, so they are prevented from crossing membranes to leave the blood.
  • Bound drugs are prevented from being metabolized by the liver.
  • Bound drugs are prevented from being excreted by the kidneys.
  • Protein-binding capacity is usually much larger than drug concentration, meaning the fraction of drug that remains free is generally constant under normal conditions.

The Danger of Drug Displacement

Because protein binding sites are finite, drugs can compete for them. If two drugs with high affinity for plasma proteins are given together, one drug may competitively displace the other.

Example 1: Warfarin and Aspirin
Imagine Warfarin is given alone. It is highly protein-bound (e.g., 75% bound, 25% free). Only the 25% free Warfarin is actively thinning the blood. If the patient then takes Aspirin (which also binds strongly to albumin), the Aspirin knocks the Warfarin off the proteins. Suddenly, the amount of free, active Warfarin in the blood might double. This rapid increase in free drug concentration can lead to severe toxicity (in Warfarin's case, dangerous internal bleeding).

Example 2: Tolbutamide and Sulfonamide
A diabetic patient takes Tolbutamide (normally 95% bound, 5% free active). The patient is then prescribed a Sulfonamide antibiotic. The Sulfonamide has a higher affinity and entirely displaces the Tolbutamide. The free Tolbutamide shoots from 5% to 100%, causing a massive, potentially fatal drop in blood sugar (hypoglycemia).


Factors Affecting Drug Distribution

Beyond protein binding, several physiological factors dictate where a drug goes:

  • Organ Size: Organs with a large physical size (like skeletal muscle) can take up a large overall amount of drug simply driven by the concentration gradient. Conversely, distributing even a small amount of drug into a tiny organ will drastically raise the tissue concentration there.
  • Blood Flow: The greater the blood flow (perfusion) to a tissue, the faster the distribution occurs from plasma to interstitium. Drugs distribute very rapidly to highly perfused organs like the brain, liver, and kidneys, much faster than to poorly perfused tissues like resting skeletal muscle and fat.
  • Membrane Permeability:
    • Capillary Permeability: In most tissues (like the liver), endothelial cells of capillaries have large fenestrations (wide slit junctions) allowing easy movement and exchange of both lipid and water-soluble drugs.
    • Blood Brain Barrier (BBB): The brain is heavily protected. Brain capillaries lack slits; instead, they have tight junctions and are covered by astrocyte foot processes. Only strictly lipid-soluble drugs or those with active transport carriers can cross the BBB. Hydrophilic (ionized/polar) drugs cannot. Clinical Note: Inflammation, such as in meningitis, damages these tight junctions, increasing permeability and allowing hydrophilic drugs like penicillin and gentamycin to enter the brain to treat the infection.
    • Placental Barrier: Lipid-soluble drugs can easily cross the placental barrier and enter fetal blood, potentially causing harm.
  • Tissue Binding: Some drugs have a very specific chemical affinity for macromolecules in certain tissues, accumulating there in high concentrations:
    • Tetracycline binds to calcium in bone and developing teeth.
    • Phenobarbitone accumulates in the brain.
    • Chlorpromazine binds to melanin in the eye.
    • Chloroquine accumulates in the kidneys and liver.
  • Other Factors:
    • Fat to Lean Body Mass Ratio: Highly lipid-soluble drugs distribute heavily into fat. Individuals with high body fat percentages will trap more of the drug in fat tissue, slightly decreasing the active concentration available to other organs.
    • Pregnancy: The fetus acts as an additional fluid compartment and tissue mass, increasing the overall distribution volume of the drug.
  • Pathological States: Disease alters physiology.
    • Congestive Heart Failure: Alters total body water and reduces blood flow to organs, impairing distribution.
    • Cirrhosis of the Liver: The liver produces albumin. Cirrhosis leads to decreased synthesis of plasma proteins. Less albumin = less protein binding = more dangerous free drug in circulation.
    • Uremia (Kidney Failure): Leads to an accumulation of toxic metabolic waste products in the blood. These wastes compete with drugs for protein binding sites, displacing the drugs and increasing toxicity.

Redistribution

For highly lipid-soluble drugs acting on the Central Nervous System (CNS), the termination of their effect is often not due to metabolism or excretion, but due to a phenomenon called Redistribution.

  • Mechanism: When an IV dose is given, the drug rushes first to the most highly perfused organs (the brain). The patient falls asleep instantly. However, within minutes, the drug follows the concentration gradient back out of the brain, back into the blood, and redistributes into less-perfused but larger fat tissues. As the drug leaves the brain, the patient wakes up. Therefore, the short duration of action of the initial dose depends almost entirely on the rapid redistribution rate, not the drug's half-life.

Warning: If a second dose (or continuous infusion) is given, the fat stores eventually fill up. The blood/fat gradient diminishes, the rate of redistribution slows to a halt, and the second dose will cause a massively prolonged duration of action because the body must now rely on slow liver metabolism to remove the drug.

Quick Quiz

Absorption & Distribution Quiz

Pharmacology

Privacy: Your details are used only for quiz tracking and certificates.

Advertisements

Drug Absorption & Distribution Read More »

Drugs Used in the Treatment of Cancer

Drugs Used in the Treatment of Cancer

Drugs Used in the Treatment of Cancer

Cancer is a disease characterized by a shift in the control mechanisms that govern cell survival, proliferation, and differentiation. 

Uncontrolled multiplication of cells leads to the formation of tumors that may be benign or malignant. Benign tumors do not spread to other tissues, while malignant tumors do.

Types of Cancer

  • Carcinoma: Affects the skin and cells in the tissue lining internal organs.
  • Sarcoma: Affects muscles, bones, and fibrous tissues.
  • Leukemia: Affects white blood cells.
  • Lymphoma: Affects the lymph glands.

Drugs used in the treatment of cancer either kill cancer cells or modify their growth.

Table 1: Classification of Anticancer Drugs

Class

Examples

Antimetabolites

Methotrexate, 5-Fluorouracil, Cytarabine, 6-Mercaptopurine

Antitumor Antibiotics

Bleomycin, Dactinomycin

Alkylating Agents

Cyclophosphamide, Busulfan, Chlorambucil, Carmustine, Dacarbazine, Melphalan

Anthracyclines

Daunorubicin, Doxorubicin, Idarubicin

Vinca Alkaloids

Vincristine, Vinblastine

Platinum Analogs

Cisplatin

Hormonal Agents

Tamoxifen, Estrogen

Others

Hydroxyurea, Procarbazine

Bleomycin

Available Preparations:

  • Powder for Injection: 15 units/vial

Available Brands: Blenoxane®

Pharmacokinetics: IM administration results in lower serum levels than those occurring after equivalent IV doses. It distributes widely into total body water, mainly in the skin, lungs, kidneys, peritoneum, and lymphatic tissue. It undergoes extensive tissue inactivation in the liver and kidney; bleomycin and its metabolites are excreted primarily in urine.

Indications:

  • Squamous cell carcinoma (head, neck, penis, cervix)
  • Testicular carcinoma
  • Non-Hodgkin’s lymphoma
  • Lymphosarcoma

Contraindications:

  • Pregnancy
  • Breastfeeding
  • Previous allergic reaction

Dosage:

  • A test dose of 1-2 units given 2-4 hours prior to therapy is recommended.
  • 0.25-0.5 unit/kg body weight or 10-20 units/m² body surface area given IV, IM, or SC once or twice weekly.

Side Effects:

  • Skin rash
  • Striae
  • Redness of the skin
  • Fever
  • Acute anaphylactoid reaction
  • Anorexia
  • Urticaria
  • Pruritus
  • Hyperpigmentation
  • Stomatitis
  • Hyperkeratosis
  • Weight loss
  • Progressive pulmonary fibrosis
  • Mucositis
  • Pneumonitis
  • Phlebitis
  • Vomiting

Drug Interactions:

  • Cisplatin may decrease bleomycin clearance and increase the risk of bleomycin toxicity.
  • Concomitant use may decrease serum levels of phenytoin and digoxin.

Key Issues to Note:

  • Increased pigmentation, particularly affecting the flexures and subcutaneous sclerotic plaques, may occur.
  • A test dose should be administered before starting therapy to check for hypersensitivity reactions.
  • Monitor pulmonary function tests during treatment.

Doxorubicin

Available Preparations:

  • Powder for Injection: 10 mg/vial, 50 mg/vial

Available Brands: Doxorubin®

Pharmacokinetics: It distributes widely into body tissues, with the highest concentrations found in the liver, heart, kidneys, skin, and muscles; it does not cross the blood-brain barrier. It is metabolized both in the liver and plasma; excreted largely in feces, with small amounts in urine.

Advertisements

Indications:

  • Acute leukemia
  • Lymphomas
  • Breast carcinoma
  • Thyroid carcinoma
  • Non-Hodgkin’s lymphoma
  • Ovarian carcinoma
  • Bone and soft tissue sarcomas
  • Hodgkin’s disease
  • Kaposi’s sarcoma in patients with AIDS
  • Transitional cell bladder carcinoma

Contraindications:

  • Hepatic dysfunction
  • Cardiomyopathy
  • Pregnancy and lactation
  • Persistent myelosuppression
  • Severe cardiac failure
  • Recent myocardial infarction

Dosage:

  • 60-74 mg/m² or 1.2-2.4 mg/kg once every 3 weeks as a single intravenous injection of a solution in sodium chloride 0.9% or glucose 5% over 3 minutes or more.
  • Children: 35-75 mg/m² as a single intravenous injection, once every 3 weeks.

Side Effects:

  • Bone marrow depression
  • Anorexia
  • Hyperpigmentation of nail beds
  • Diarrhea
  • Irreversible CHF
  • Reversible alopecia
  • Nausea and vomiting
  • Stomatitis
  • Fever and chills
  • Urticaria
  • Conjunctivitis
  • Lacrimation

Drug Interactions:

  • Cholestasis induced by mercaptopurine may be potentiated by the concurrent administration of doxorubicin.
  • Concomitant use of daunorubicin or cyclophosphamide may potentiate the cardiotoxicity of doxorubicin through additive effects on the heart.
  • Serum digoxin, carbamazepine, and phenytoin levels may be decreased if used concomitantly with doxorubicin.
  • Phenobarbitone increases the elimination of doxorubicin.

Key Issues to Note:

  • Notify the patient that the urine may turn red for the first 1-2 days.
  • Doxorubicin may induce hyperuricemia; therefore, monitor the patient’s blood uric acid levels.
  • Encourage the patient to take adequate fluid intake to increase urine output and facilitate excretion of uric acid.
  • Advise the patient to call if fever, bleeding, and sore throat occur.
  • Avoid exposure to sunlight to prevent sunburns.
  • Warn the patient that alopecia will occur. Explain that hair growth should resume 2-5 months after the drug is stopped.
  • Tell the patient not to receive any immunization during therapy and for several weeks after.
  • Advise the patient to avoid exposure to people with infections.


Methotrexate

Available Preparations:

  • Tablets: 2.5 mg
  • Injection: 25 mg/ml

Available Brands: Texol®

Indications:

  • Treatment and palliation of solid tumors
  • Burkitt’s lymphoma
  • Leukemia
  • Psoriasis

Contraindications:

  • Known hypersensitivity to methotrexate
  • Pregnancy and lactation
  • Severe hepatic and renal impairment
  • Bone marrow suppression
  • Anemia
  • Immunodeficiency syndromes
  • Active infection

Dosage:

  • Leukemia: 15-30 mg/m² orally, intramuscularly, or intravenously; once a week.

Side Effects:

  • Nausea and vomiting
  • Stomatitis
  • Diarrhea
  • Anorexia
  • Malaise
  • Headache
  • Skin rash
  • Dermatitis
  • Pruritus
  • Dizziness
  • Blurred vision

Drug Interactions:

  • Concomitant use with probenecid and salicylates increases the therapeutic and toxic effects of methotrexate by inhibiting its renal clearance.
  • Alcohol enhances the hepatotoxicity caused by methotrexate.
  • Phenytoin, co-trimoxazole may give additive antifolate activity and increase the risk of methotrexate toxicity.
  • Advertisements

Key Issues to Note:

  • Full blood count, urea, and liver function tests should be carried out prior to and during treatment.
  • Folinic acid is required for rescue procedures.
  • Patients with hyperuricemia should maintain adequate fluid intake and alkalinization of urine.

Vincristine

Available Preparations:

  • Solution for Injection: 1 mg/ml, 0.1 mg/ml

Available Brands: Cristol®

Indications:

  • Leukemias
  • Lymphomas
  • Some solid tumors

Contraindications:

  • Demyelinating form of Charcot-Marie-Tooth syndrome
  • Pregnancy
  • Breastfeeding mothers
  • Current radiotherapy to the liver
  • Known hypersensitivity to vincristine

Dosage:

  • Adult: IV 1.4 mg/m² up to a max weekly dose of 2 mg/m².
  • Children: IV 2 mg/m² once a week.
  • Children < 10 kg: 0.05 mg/kg once a week.

Side Effects:

  • Hair loss
  • Stomatitis
  • Constipation
  • Abdominal cramps
  • Diarrhea
  • Skin rash
  • Headache
  • Jaw pain
  • Hoarseness
  • Diplopia
  • Nausea and vomiting
  • Abdominal distention
  • Urinary tract disturbance
  • Peripheral neuropathy

Drug Interactions:

  • Vincristine may decrease digoxin plasma levels and renal excretion.
  • Vincristine may reduce phenytoin plasma levels.

Key Issues to Note:

  • Allopurinol may be given to prevent uric acid nephropathy.
  • Stool softeners should be used for constipation prophylaxis.
  • Vincristine is a tissue irritant; care should be taken to avoid extravasation.

Tamoxifen

Available Preparations:

  • Tablets: 10 mg, 20 mg

Available Brands: Nolvadex®

Pharmacokinetics: Tamoxifen is well absorbed after oral administration, distributed widely into total body water, metabolized extensively in the liver, and excreted primarily in feces.

Indications:

  • Breast cancer
  • Female infertility (induction of ovulation)

Contraindications:

  • Known hypersensitivity to tamoxifen
  • History of deep vein thrombosis or pulmonary embolism in high-risk women
  • Pregnancy

Dosage:

  • Breast cancer: 20 mg daily.
  • Induction of ovulation (infertility): 20 mg daily on days 2, 3, 4, and 5 of the cycle; if necessary, the daily dose may be increased to 40 mg then 80 mg for subsequent courses.

Side Effects:

  • Hot flushes
  • Nausea
  • Vomiting
  • Lightheadedness
  • Bone pain
  • Confusion
  • Vaginal bleeding
  • Vaginal discharge
  • Headache
  • Decreased libido
  • Weakness

Drug Interactions:

  • Estrogen may decrease the effect of tamoxifen.
  • The anticoagulant effect of oral anticoagulants may be increased by tamoxifen.
  • Bromocriptine may elevate serum levels of tamoxifen.

Key Issues to Note:

  • Adverse effects may be controlled by dosage reduction.
  • Use cautiously in pre-existing leukopenia and thrombocytopenia.
  • Advise women not to become pregnant during therapy with tamoxifen.

Drugs Used in the Treatment of Cancer Read More »

Endocrine and Metabolic Drugs

Endocrine and Metabolic Drugs

Endocrine and Metabolic Drugs

Drugs Used in Diabetes Mellitus

Diabetes mellitus is a chronic disorder characterized by hyperglycemia, altered metabolism of carbohydrates, proteins, and fats, due to insulin deficiency or resistance.

Classification of Diabetes Mellitus

Diabetes mellitus is classified into two:

  • Type 1 diabetes mellitus
  • Type 2 diabetes mellitus

Type 1 Diabetes Mellitus

This type of diabetes is due to autoimmune destruction of the beta cells. It is more common in young children than adults. Patients with type 1 diabetes require exogenous insulin for survival.

Type 2 Diabetes Mellitus

Type 2 diabetes usually presents in obese adults and has a strong family history. It is caused by insulin deficiency and insulin resistance.

Drugs used in the treatment of diabetes mellitus include:

  • Oral antidiabetic drugs
  • Insulin

Oral Antidiabetic Drugs

Oral antidiabetic drugs are used in the treatment of type 2 diabetes mellitus which has not responded to lifestyle modification.

Classification of Oral Antidiabetics

Oral antidiabetics are classified as follows:

  • Sulfonylureas
  • Biguanides
  • Thiazolidinediones
  • Alpha-glucosidase inhibitors

Sulfonylureas

Sulfonylureas are structurally related to sulfonamides. They are divided into generations as follows:

First Generation

  • Tolbutamide
  • Chlorpropamide

Second Generation

  • Glibenclamide
  • Glimepiride
  • Gliclazide
  • Glipizide

Mode of Action

Sulfonylureas act by stimulating insulin secretion from the beta cells of the pancreas, thus increasing insulin levels. Increased insulin secretion results in lowering of blood glucose levels. These drugs are only effective in the presence of functioning beta cells.

Tolbutamide

Available Preparations:

  • Tablets: 500 mg

Pharmacokinetics

Tolbutamide is readily absorbed after oral administration, metabolized in the liver, and excreted in the urine and feces chiefly as metabolites.

Indications

  • Type 2 diabetes mellitus

Contraindications

  • Severe hepatic and renal impairment
  • Presence of ketoacidosis
  • Breastfeeding
  • Pregnancy
  • Porphyria
  • Insulin-dependent diabetes mellitus

Dosage

  • Adult: 500-1500 mg daily in 2 divided doses, max 2 g daily

Side Effects

  • Nausea and vomiting
  • Constipation
  • Dyspepsia
  • Hypoglycemia
  • Headache
  • Diarrhea
  • Skin rash
  • Tinnitus
  • Taste alteration

Drug Interactions

  • Beta-blockers may mask hypoglycemic symptoms caused by tolbutamide
  • Hypoglycemic effect caused by tolbutamide may be reduced by corticosteroids
  • Disulfiram-like reaction may occur when tolbutamide is taken concurrently with alcohol
  • Hypoglycemic effect of tolbutamide may be increased by sulfonamide antibiotics, ranitidine, and cimetidine

Key Issues to Note

  • Tolbutamide should be given with or immediately after food
  • Elderly, debilitated patients, and those with impaired renal or hepatic function usually require a lower initial dose
  • Because of its complete metabolism and short duration of action, it is recommended in the elderly
  • The drug should not be taken at bedtime because of the potential for nocturnal hypoglycemia
  • Avoid alcohol while taking tolbutamide

Glibenclamide

Available Preparations:

  • Tablets: 5 mg

Available Brands: Daonil®, Glibol®, Glibetics®, Euglucon®, Betanase®, Diaben®, Glamide®

Advertisements

Combinations: Duotrol® (Glibenclamide/Metformin) 5/500

Pharmacokinetics

Glibenclamide is reliably and almost completely absorbed when taken orally, metabolized in the liver to weakly active metabolites, and excreted in urine and feces.

Indications

  • Type 2 diabetes mellitus

Contraindications

  • Presence of ketoacidosis
  • Type 1 diabetes mellitus
  • Severe renal and hepatic impairment
  • Pregnancy and breastfeeding
  • Previous hypersensitivity to the drug

Dosage

  • Initially 5 mg in the morning, dose adjusted according to response, max 15 mg/day

Side Effects

  • Headache
  • Weakness
  • Epigastric fullness
  • Hypoglycemia
  • Dizziness
  • Nausea
  • Weight gain
  • Heartburn

Drug Interactions

  • Beta-blockers may mask warning symptoms of hypoglycemia caused by glibenclamide
  • Hypoglycemic effect of glibenclamide is reduced by drugs which are insulin antagonists such as bendrofluazide, oral contraceptives, and glucocorticoids
  • Metformin has a synergistic hypoglycemic action with glibenclamide
  • Alcohol increases the hypoglycemic effect caused by glibenclamide and may also cause disulfiram-like reaction
  • An enhanced hypoglycemic response to glibenclamide may occur when given together with drugs such as aspirin, cimetidine, fluconazole, and ketoconazole

Key Issues to Note

  • Glibenclamide should be given with or 30 minutes before a meal
  • Warn the patient of the possibility of hypoglycemia and advise on how to manage it
  • Encourage the patient to maintain lifestyle modifications
  • Glibenclamide tablets should be stored in a cool, dry place and protected from light
  • Avoid alcohol while taking the drug
Biguanides

Biguanides are the drugs of choice in the treatment of type 2 diabetes mellitus in overweight patients. They do not increase insulin secretion; therefore, they do not usually cause hypoglycemia or weight gain. Metformin is the only available biguanide. It may be combined with a sulfonylurea to provide better glycemic control.

Mode of Action

Biguanides act by decreasing the production of glucose by the liver and also promote the uptake of glucose by tissues.

Metformin

Available Preparations:

  • Tablets: 500 mg, 850 mg, 1000 mg

Available Brands: Glyformin®, Glucophage®, Glucomet®, Metformin-Denk®, Glycomet®, Bigomet®

Combinations:

  • Avandamet® (Rosiglitazone/Metformin) 2/500
  • Pionorm-M® (Pioglitazone/Metformin) 30/500
  • Piosafe-M® (Pioglitazone/Metformin) 15/500

Pharmacokinetics

Metformin is slowly and incompletely absorbed when taken orally. Food delays or decreases the extent of absorption. It is excreted mainly as unchanged drug in urine.

Indications

  • Type 2 diabetes mellitus
  • Polycystic ovary syndrome

Contraindications

  • Pregnancy
  • Hepatic dysfunction
  • Acute metabolic acidosis
  • Pancreatitis
  • Renal dysfunction
  • Breastfeeding

Dosage

  • Initially 500 mg with breakfast for 1 week, then 500 mg with breakfast and evening meal for at least 1 week, then 500 mg with breakfast, lunch, and evening meal, max 2 g daily in divided doses

Side Effects

  • Nausea
  • Anorexia
  • Rash
  • Lactic acidosis
  • Malabsorption of vitamin B12
  • Vomiting
  • Diarrhea
  • Metallic taste
  • Abdominal pain

Drug Interactions

  • There is an increased risk of hypoglycemia when metformin is given with digoxin or furosemide
  • Alcohol increases the risk of lactic acidosis associated with metformin
  • Nifedipine may enhance the absorption of metformin
  • Metformin may interfere with vitamin B12 absorption
  • Cimetidine increases peak metformin blood concentrations
  • Advertisements

Key Issues to Note

  • Advise the patient not to change or discontinue the drug without consulting the prescriber
  • Avoid alcohol during treatment
  • Advise the patient to take the drug with meals
  • Extended-release tablets should be taken whole without chewing or crushing


Insulin

Insulin is a hormone produced by the beta cells of the pancreatic islets of Langerhans.

It plays an important role in the regulation of carbohydrate, protein, and fat metabolism. Insulin lowers blood glucose by inhibiting glycogenolysis and gluconeogenesis in the liver and stimulates glucose uptake by muscles and adipose tissues.

Insulin is used in the treatment of type 1 diabetes mellitus and is also used in type 2 diabetes mellitus in the following cases:

  • Severe infection
  • Major surgery
  • Ketoacidosis
  • During pregnancy
  • When hyperglycemia does not respond to non-pharmacological measures and oral antidiabetics

Sources of Insulin

Insulin for therapeutic use is extracted from the pancreas of any of the following:

  • Cattle
  • Pig
  • Human

Types of Insulin Preparations

There are 3 main types of insulin preparations which differ in time of onset and duration of action. They include:

  • Short-acting insulin (e.g., insulin soluble) – It is the only insulin that can be given by IV bolus, IV infusion, or IM
  • Intermediate-acting insulin (e.g., insulin zinc suspension – Lente) – Have slower onset of action but with prolonged duration of action. They are formulated to dissolve more gradually when administered
  • Long-acting insulin (e.g., glargine – Lantus) – Has a duration of action of 24 hours

Insulin Administration

Insulin is usually given subcutaneously in the buttock, abdomen, anterior thigh, and dorsal arm. Absorption is usually most rapid from the abdomen, followed by the arm, then the buttock and thigh. The rate of absorption is increased by massage, hot bath, or exercise. The type of insulin used depends on the type of diabetes, patient’s age, and blood glucose levels.

Soluble Insulin

Available Preparations:

  • Injection: 100 IU/ml

Available Brands: Actrapid®

Indications

  • Type 1 diabetes mellitus
  • Diabetic ketoacidosis
  • During pregnancy, surgery, trauma, infections, and fever

Contraindications

  • Hypersensitivity to insulin
  • Hypoglycemia

Dosage

  • Insulin dosage is individualized and determined in accordance with the needs of the patient, usual range 0.3-1 unit/kg/day

Side Effects

  • Hypoglycemia
  • Skin rash
  • Edema
  • Fat hypertrophy at injection site
  • Local reaction
  • Urticaria
  • Abdominal bloating
  • Blurred vision

Drug Interactions

  • Alcohol may increase the effects of insulin
  • Beta-blockers may mask signs and symptoms of hypoglycemia
  • Corticosteroids antagonize effects of insulin and result in increased glucose levels
  • ACE inhibitors may increase the hypoglycemic effect of insulin

Key Issues to Note

  • Advise the patient to watch out for symptoms of hypoglycemia such as fatigue, confusion, headache, hunger, rapid breathing
  • Advise the patient to always carry a quick source of sugar to rectify hypoglycemia when it occurs
  • Injection sites should be rotated to avoid lipodystrophy

Endocrine and Metabolic Drugs Read More »

Drugs Used in the Treatment of Cardiovascular Disorders

Drugs Used in the Treatment of Cardiovascular Disorders

Drugs Used in the Treatment of Cardiovascular Disorders

These drugs are used in the treatment of conditions such as:

  • Hypertension
  • Angina pectoris
  • Heart failure
  • Hyperlipidemia
  • Arrhythmias

Drugs Used in the Treatment of Hypertension

Hypertension

Hypertension is the persistent elevation of blood pressure higher than normal (140/90 mmHg).

Common Terms Used in Hypertension

  • Blood Pressure: This is the pressure of blood against the walls of the main arteries.
  • Diastolic Blood Pressure: This is the pressure exerted in the vessels when the ventricles are relaxing and refilling.
  • Systolic Pressure: This is the pressure exerted in the vessels when the ventricles are contracting.
  • Orthostatic Hypotension (Postural Hypotension): This is the decrease in blood pressure that occurs when a person stands erect.
  • Peripheral Vascular Resistance: This is the pressure that blood must overcome as it flows in the vessels.
  • Isolated Systolic Hypertension: This is defined as systolic blood pressure greater than or equal to 140 mmHg with diastolic blood pressure less than 90 mmHg. It is common in elderly patients.
  • Malignant Hypertension: This is a rapidly progressing, potentially fatal form of hypertension with diastolic pressure exceeding 120 mmHg.
  • Hypertensive Emergency: This is characterized by severe elevation in blood pressure > 180/120 mmHg complicated by target organ dysfunction. These situations require immediate reduction of blood pressure to limit target organ damage.
  • Hypertensive Urgency: This is a situation with severe elevation of blood pressure without target organ dysfunction.

Table 1: Stages of Hypertension

Category

Systolic

Diastolic

Normal

< 130

< 80

High Normal (Pre-hypertension)

130-139

81-89

Mild Hypertension (Stage I)

140-159

90-99

Moderate Hypertension (Stage 2)

160-179

100-109

Severe Hypertension (Stage 3)

180-209

110-119

Very Severe Hypertension (Stage 4)

> 209

> 119

Classification of Hypertension

Hypertension may be classified as:

  • Essential (Primary) Hypertension
  • Secondary Hypertension

Essential Hypertension

Essential hypertension is the most common type of hypertension, contributing to over 90% of the cases of hypertension encountered in medical practice. The cause of essential hypertension is not known.

Secondary Hypertension

Secondary hypertension is an elevation of blood pressure due to an identifiable cause such as:

  • Renal disease
  • Drugs like oral contraceptives
  • Pre-eclampsia
  • Renovascular disease

Treatment is directed at elimination of the cause.

Management of Hypertension

Non-Pharmacological Measures

  • Encourage regular exercise (e.g., walking, jogging)
  • Advise the patient to lose weight (if overweight)
  • Advise the patient to limit alcohol intake
  • Advise the patient to restrict salt intake
  • Advise the patient to stop smoking
  • Encourage a diet high in fruits and vegetables
  • Advise the patient to relax and manage stress
  • Diet should be low in saturated fats and cholesterol

Note: Non-pharmacological measures may be employed alone in pre-hypertension or in combination with drugs in mild to severe hypertension.

Drugs used in the treatment of hypertension may be classified as follows:

  • Beta blockers
  • ACE inhibitors
  • Alpha-II blockers
  • Diuretics
  • Centrally acting antihypertensives
  • Calcium channel blockers
  • Angiotensin II antagonists
  • Direct vasodilators

Table 2: Choice of Antihypertensives in Different Conditions

Comorbid Disease

Drugs Recommended

Diabetes mellitus

Calcium channel blockers, ACE inhibitors

Congestive heart failure

Diuretics, ACE inhibitors

Angina pectoris

Beta blockers, calcium channel blockers, ACE inhibitors, and diuretics as alternative

Asthma, chronic pulmonary disease

Calcium channel blockers, diuretics, and ACE inhibitors

Hyperlipidemia

ACE inhibitors, calcium channel blockers

Previous myocardial infarction

Beta blockers, calcium channel blockers, ACE inhibitors, and diuretics

Chronic renal disease

Diuretics, calcium channel blockers, beta blockers, and ACE inhibitors

Beta Blockers

These drugs are recommended in the treatment of hypertension, angina pectoris, and post-myocardial infarction.

Beta blockers are classified as follows:

Non-selective beta blockers

  • Propranolol
  • Sotalol

Selective beta-1 blockers

  • Atenolol
  • Bisoprolol
  • Metoprolol

Alpha and beta blockers

  • Carvedilol
  • Labetalol

Mode of Action

Beta blockers competitively block the response to beta receptors, resulting in a decrease in heart rate and heart contractility, thereby lowering blood pressure.

Atenolol

Available Preparations:

  • Tablets: 25 mg, 50 mg, 100 mg

Available Brands: Tenormin®, Totamol®, Velorin®, Atelor®, Betagard®, Cardinol®, Tensimin®

Combinations:

  • Tenoret® (Atenolol/Chlorthalidone) 50/12.5 mg
  • Tenoretic® (Atenolol/Chlorthalidone) 100/25 mg

Pharmacokinetics

About half of the dose is absorbed following oral administration, crosses the placenta, and is distributed into breast milk. Atenolol undergoes little or no hepatic metabolism and is excreted unchanged in the urine.

Indications

  • Hypertension
  • Angina pectoris
  • Cardiac arrhythmias
  • Prophylaxis in migraine
  • Acute myocardial infarction

Contraindications

  • Hypersensitivity to atenolol
  • Sinus bradycardia
  • Second and third-degree heart block
  • Symptomatic heart failure

Dosage

  • Hypertension: 25-100 mg once daily (100 mg is only slightly better than 50 mg)
  • Angina: 100 mg once daily or 50 mg twice daily
  • Arrhythmias: 50-100 mg daily
  • Migraine Prophylaxis: 50-100 mg daily

Side Effects

  • Fatigue
  • Hypotension
  • Impotence
  • Muscle ache
  • Dizziness
  • Wheezing
  • Insomnia

Drug Interactions

  • Cimetidine may increase atenolol blood concentration
  • Diuretics and other antihypertensives may increase the hypotensive effect of atenolol
  • Atenolol may mask the symptoms of hypoglycemia and prolong the hypoglycemic effect of insulin and oral hypoglycemics
  • NSAIDs may decrease the antihypertensive effects of atenolol
  • Alcohol enhances the hypotensive effect of atenolol
  • Concurrent use with digoxin increases the risk of AV block and bradycardia
  • Oral contraceptives antagonize the hypotensive effect of atenolol
  • Concurrent use with verapamil results in severe hypotension and heart failure

Key Issues to Note

  • Atenolol should be used with caution in patients with diabetes since it may mask symptoms of hypoglycemia
  • Atenolol may be administered with or without food
  • Abrupt withdrawal of the drug should be avoided; it should be discontinued over 1-2 weeks through gradual reduction of the dose

Calcium Channel Blockers

These drugs are used in the treatment of hypertension and angina pectoris and are safe for patients with asthma, hyperlipidemia, diabetes, and renal dysfunction. They are subdivided into two groups:

  • Dihydropyridines

  • Non-dihydropyridines

Dihydropyridines: Drugs in this group produce significant blockage of calcium channels in blood vessels and minimal in the heart.

Examples:

  • Nifedipine
  • Amlodipine
  • Felodipine

Non-Dihydropyridines: These drugs act on vascular smooth muscle and the heart. Since they suppress AV conduction, they are useful in cardiac arrhythmias.

Advertisements

Examples:

  • Verapamil
  • Diltiazem

Mode of Action

Calcium channel blockers decrease the influx of calcium into smooth muscles, thereby reducing vascular tone, which results in a reduction of peripheral resistance and blood pressure.

Nifedipine

Available Preparations:

  • Tablets: 10 mg, 20 mg retard, 30 mg long-acting

Available Brands: Adalat®, Nifelat®, Nifedipine-denk®

Pharmacokinetics

Nifedipine is rapidly and almost completely absorbed from the gastrointestinal tract, but bioavailability is reduced by first-pass metabolism. It is extensively metabolized in the liver and excreted in the urine as inactive metabolites.

Indications

  • Hypertension
  • Prophylaxis of angina pectoris

Contraindications

  • Hypersensitivity to nifedipine
  • Unstable or acute attacks of angina
  • Porphyria
  • Cardiogenic shock

Dosage

The dose and frequency of administration vary depending on the preparations used.

  • Short-acting nifedipine is given 3 times a day
  • Nifedipine retard is given twice daily
  • Long-acting nifedipine is given once daily

Hypertension:

  • Adults: 10-20 mg twice daily, increased to 20-40 mg twice daily (Nifedipine retard)
  • Nifedipine long-acting: 30-90 mg once daily

Angina Pectoris:

  • Nifedipine retard: 10-40 mg twice daily or nifedipine long-acting: 30-90 mg once daily

Side Effects

  • Oedema of ankle
  • Headache
  • Flushing
  • Dizziness
  • Tachycardia
  • Palpitations
  • Impotence
  • Tremors
  • Muscle cramps
  • Dry mouth
  • Constipation
  • Nausea

Drug Interactions

  • Beta blockers may have additive hypotensive effects when given together with nifedipine
  • Nifedipine may increase digoxin blood concentration
  • Nifedipine increases the plasma concentration of digoxin
  • Rifampicin increases the metabolism of nifedipine, leading to reduced plasma concentrations

Key Issues to Note

  • Administer nifedipine with food and swallow sustained-release tablets without chewing
  • Advise the patient to avoid alcohol
  • Advise the patient to rise slowly from a prolonged sitting or lying position
  • Advise the patient not to stop using the drug suddenly
  • Inform the patient that excessive hypotension may occur, especially at the beginning of treatment

Amlodipine

Available Preparations:

  • Tablets: 5 mg, 10 mg
  • Capsules: 5 mg, 2.5 mg

Available Brands: Norvasc®, Amtas®, Asomex®, Amlong®, Lovasc®, Lofral®, Amlodac®, Amedin®

Pharmacokinetics

Amlodipine is well absorbed following oral administration. It is extensively metabolized in the liver and excreted in the urine.

Indications

  • Hypertension
  • Prophylaxis of angina pectoris

Contraindications

  • Unstable angina
  • Known hypersensitivity to amlodipine
  • Breastfeeding

Dosage

  • Hypertension or Angina: Initially 5 mg once daily, increased after 10-14 days to a max of 10 mg once daily if necessary

Side Effects

  • Headache
  • Dizziness
  • Oedema
  • Fatigue
  • Flushes
  • Hypotension
  • Malaise
  • Bradycardia
  • Palpitations
  • Taste disturbances
  • Abdominal pain

Drug Interactions

  • Cimetidine increases serum levels of amlodipine
  • Rifampicin may decrease serum concentrations of amlodipine
  • Erythromycin may reduce clearance of amlodipine
  • Barbiturates reduce plasma concentrations of amlodipine

Key Issues to Note

  • Amlodipine may be administered without regard to food but take with caution with grapefruit juice
  • Inform the patient not to discontinue the drug abruptly
  • Inform the patient to report to the clinician in case of irregular heartbeat, shortness of breath, swelling of the feet and hands, pronounced dizziness, and hypotension


Angiotensin-Converting Enzyme Inhibitors (ACEIs)

These drugs are useful in the treatment of hypertension and heart failure.

Examples:

  • Captopril
  • Enalapril
  • Ramipril
  • Lisinopril
  • Quinapril

Mode of Action

ACE inhibitors act by inhibiting the conversion of angiotensin I to angiotensin II (a powerful vasoconstrictor). This results in relaxation of blood vessels, which lowers blood pressure.

Captopril

Available Preparation:

  • Tablets: 25 mg

Available Brands: Epistron®, Angiopril®

Pharmacokinetics

Captopril is absorbed throughout the GIT, and the presence of food may reduce absorption. It is distributed to body tissues except the CNS, metabolized in the liver, and excreted in the urine and small amounts in feces.

Indications

  • Mild to moderate hypertension
  • Congestive heart failure
  • Diabetic nephropathy
  • Prophylaxis after infarction

Contraindications

  • Hypersensitivity to captopril and other ACE inhibitors
  • Pregnancy
  • Hereditary or idiopathic angioedema
  • Bilateral or single renal artery stenosis

Dosage

  • Hypertension: Initially 12.5 mg twice daily. Maintenance dose: 25 mg twice daily, max 50 mg twice daily in severe hypertension
  • Heart Failure (Adjunct): Initially 6.25-12.5 mg under close supervision. Maintenance dose: 25 mg 2-3 times daily, max 150 mg daily
  • Diabetic Nephropathy: 75-100 mg daily in divided doses

Side Effects

  • Hypotension
  • Chest pain
  • Palpitations
  • Fatigue
  • Non-productive cough
  • Tachycardia
  • Dyspepsia
  • Hyperkalemia
  • Taste disturbances
  • Malaise

Drug Interactions

  • Alcohol, diuretics may increase the effect of captopril
  • NSAIDs may decrease the effect of captopril
  • Potassium-sparing diuretics, potassium supplements may cause hyperkalemia

Key Issues to Note

  • Advise the patient to rise slowly to sitting or standing position to minimize orthostatic hypotension
  • Inform the patient that dizziness, fainting, lightheadedness may occur during the first few days of treatment
  • Advise the patient to take the drug on an empty stomach about one hour before food
  • Captopril should not be administered together with antacids because they hinder its absorption
  • The dose administered and frequency of administration should be reduced in renal impairment
Angiotensin II Receptor Antagonists

These drugs include:

  • Losartan
  • Valsartan
  • Telmisartan

They are normally used as an alternative in patients who cannot tolerate side effects such as dry cough associated with ACE inhibitors.

Mode of Action

They produce a fall in blood pressure by direct antagonism of the vasoconstrictor angiotensin II at the AT1 receptor site.

Losartan

Available Preparations:

  • Tablets: 50 mg, 100 mg

Available Brands: Losacar®, Tozaar®, Losartec®, Losartas®

Combinations:

  • Presartan-H50® (Losartan/Hydrochlorothiazide)
  • Tozaar-H®

Pharmacokinetics

Losartan is readily absorbed from the gastrointestinal tract following oral administration, undergoes first-pass metabolism forming active and inactive metabolites. Losartan is excreted in the urine and feces.

Indications

  • Hypertension
  • Diabetic nephropathy

Contraindications

  • Known hypersensitivity to losartan
  • Pregnancy (2nd and 3rd trimester)
  • Lactation

Dosage

  • Usually 50 mg once daily, increased after several weeks to 100 mg once daily if necessary

Side Effects

  • Dizziness
  • Taste disturbance
  • Myalgia
  • Fatigue
  • Diarrhea
  • Urticaria
  • Vertigo
  • Migraine

Drug Interactions

  • Fluconazole may decrease conversion of losartan to active metabolites resulting in loss of anti-hypertensive effects
  • NSAIDs may reduce the hypotensive effect of losartan
  • Potassium-sparing diuretics may increase the risk of hyperkalemia when given together with losartan
  • Cimetidine may increase the effect of losartan
  • Alcohol may potentiate the hypotensive effect of losartan

Key Issues to Note

Advertisements

  • Avoid tasks that require alertness until response to drug is established (possible dizziness effect)
  • Advise the patient not to take any OTC preparations or nasal decongestants without recommendation of a clinician
  • Advise the patient not to stop taking the medication unless told by the clinician
  • The drug may be taken with or without meals
Direct-Acting Vasodilators

These drugs are rarely used as first-line drugs and are reserved for resistant cases of hypertension and for treatment of hypertensive emergencies. These drugs also cause sodium and water retention; therefore, they are useful when combined with diuretics to counteract the sodium retention. They are also combined with beta blockers to prevent the reflex tachycardia.

Examples:

  • Hydralazine
  • Minoxidil

Mode of Action

Hydralazine reduces blood pressure by acting directly on the arterial smooth muscle to cause vasodilation and reduction in total peripheral vascular resistance.

Hydralazine

Available Preparations:

  • Injection: 20 mg/ml
  • Tablets: 25 mg

Available Brands: Apresoline®

Pharmacokinetics

Orally administered hydralazine is rapidly and completely absorbed from the gastrointestinal tract but undergoes considerable first-pass metabolism in the gastrointestinal mucosa and liver. It is widely distributed, metabolized in the liver by acetylation, and excreted in the urine as metabolites.

Indications

  • Hypertensive crisis
  • Moderate to severe hypertension
  • Moderate to severe chronic congestive heart failure (in combination with long-acting nitrates)
  • Hypertension secondary to pre-eclampsia/eclampsia

Contraindications

  • Known hypersensitivity to hydralazine
  • Severe tachycardia
  • Heart failure with high cardiac output
  • Myocardial insufficiency due to mechanical obstruction
  • Idiopathic systemic lupus erythematosus
  • Porphyria

Dosage

  • Hypertension: By mouth 25 mg twice daily, increased to usual max 50 mg twice daily
  • Heart Failure: 25 mg 3-4 times daily, increased every 2 days if necessary. Maintenance dose: 50-75 mg 4 times daily
  • By Intravenous Infusion, Hypertension with Renal Complications and Hypertensive Crisis: Initially 200-300 micrograms/minute, maintenance 50-150 micrograms/minute

Side Effects

  • Headache
  • Severe tachycardia
  • Hypotension
  • Angina
  • Oedema
  • Heart failure
  • Dizziness
  • Flushing
  • Palpitations
  • Joint swelling
  • Anorexia
  • Gastrointestinal disturbances

Drug Interactions

  • Diuretics, other antihypertensives may increase hypotensive effects of hydralazine
  • Indomethacin may decrease hypotensive effects of hydralazine

Key Issues to Note

  • Prolonged treatment of more than 6 months may induce lupus-like syndrome
  • Beta blockers and thiazides are often used with hydralazine to prevent tachycardia and fluid retention
  • Advise the patient to avoid driving until the effect of the drug is established
Centrally Acting Antihypertensive Drugs

These drugs are effective antihypertensives but are no longer considered drugs of choice as they are less tolerated than other antihypertensives. Methyldopa is a drug of choice in the treatment of hypertension in pregnancy.

Examples:

  • Methyldopa
  • Clonidine

Mode of Action

These drugs reduce blood pressure by acting in the CNS to reduce the activity of the sympathetic nervous system.

Methyldopa

Available Preparations:

  • Tablets: 250 mg

Available Brands: Aldomet®, Medopress®

Pharmacokinetics

Methyldopa is variably absorbed from the gastrointestinal tract when taken orally, crosses the blood-brain barrier, is extensively metabolized in the liver, and excreted in urine.

Indications

  • Hypertension, especially in pregnancy

Contraindications

  • Hypersensitivity to methyldopa
  • Active liver disease
  • Depression
  • Phaeochromocytoma
  • Porphyria

Dosage

  • Adult: Initially 250 mg 2-3 times daily, increased gradually at an interval of at least 2 days until the desired response is obtained, max 3 g daily
  • Elderly: Initially 125 mg twice daily, increased gradually, max 2 g daily

Side Effects

  • Sedation
  • Dry mouth
  • Stomatitis
  • Myalgia
  • Impaired mental acuity
  • Impotence
  • Hemolytic anemia
  • Dizziness
  • Constipation
  • Oedema
  • Postural hypotension
  • Decreased libido
  • Bradycardia

Drug Interactions

  • Enhanced hypotensive effect when methyldopa is given with ACE inhibitors, alcohol, atenolol, or propranolol
  • Methyldopa may impair tolbutamide metabolism, enhancing its hypoglycemic effects
  • Hypotensive effect of methyldopa is antagonized by NSAIDs
  • Hypotensive effect of methyldopa is antagonized by estrogen
  • Oral iron therapy reduces the bioavailability of methyldopa

Key Issues to Note

  • Methyldopa may be administered with or without regard to food
  • Advise the patient to avoid alcohol during treatment
  • Warn the patient that methyldopa may cause drowsiness and impair activities requiring mental alertness
  • Advise the patient to rise slowly from a prolonged sitting or lying position
  • Inform the patient that transient sedation or depression may occur
  • Advise the patient not to stop the drug abruptly
Alpha Adrenoceptor Blocking Drugs

These drugs may be used in combination with other drugs in the treatment of resistant hypertension. In addition to lowering blood pressure, they also improve urinary flow rates in benign prostatic hypertrophy.

Examples:

  • Prazosin
  • Doxazosin
  • Terazosin

Mode of Action

These drugs competitively inhibit postsynaptic alpha receptors, which results in vasodilation of veins and arterioles. This leads to a decrease in total peripheral resistance and blood pressure. They also block alpha receptors in non-vascular smooth muscle (e.g., the bladder neck), where alpha-blockade reduces resistance to urinary flow.

Prazosin

Available Preparations:

  • Tablets: 1 mg, 2 mg, 5 mg

Available Brands: Hypovase®, Minipress®

Pharmacokinetics

Prazosin is well absorbed after oral administration, extensively metabolized in the liver, and excreted in urine.

Indications

  • Hypertension
  • Congestive heart failure
  • Benign prostatic hyperplasia
  • Raynaud’s syndrome

Contraindications

  • Hypersensitivity to quinazolines
  • Congestive heart failure due to mechanical obstruction

Dosage

  • Hypertension: 0.5 mg twice daily, increased to 1 mg 2-3 times daily after 3-7 days, maintenance dose 20 mg daily in 2-3 divided doses
  • Heart Failure: 0.5 mg 2-4 times daily, increased to 4 mg daily in divided doses, maintenance dose 4-20 mg daily in divided doses
  • Benign Prostate Hyperplasia: Initially 0.5 mg twice daily for 3-7 days, maintenance dose 2 mg twice daily
  • Raynaud’s Syndrome: Initially 0.5 mg twice daily, increased if necessary after 3-7 days to the usual maintenance dose 1-2 mg twice daily

Side Effects

  • Headache
  • Dry mouth
  • Drowsiness
  • Oedema
  • Postural hypotension
  • Urinary incontinence
  • Priapism
  • Urinary frequency
  • Weakness
  • Palpitations
  • Nausea
  • Somnolence

Drug Interactions

  • Estrogen, NSAIDs may decrease the effect of prazosin
  • Concomitant use with propranolol or other beta blockers may cause severe hypotension

Key Issues to Note

  • Advise the patient to avoid alcohol
  • Inform the patient that prazosin may cause dizziness or drowsiness and impair the ability to perform activities requiring alertness
  • Advise the patient to rise slowly from sitting or lying position
  • Advise the patient to take the first dose of prazosin at bedtime to avoid dizziness

Drugs for Heart Failure

Heart failure is a clinical syndrome caused by the inability of the heart to pump sufficient blood to meet the metabolic demands of the body. Inadequate perfusion of the tissues leads to a variety of symptoms such as breathlessness, fatigue, and oedema. Drugs used in the treatment of heart failure include:

Advertisements

  • Diuretics

  • Cardiac glycosides

  • ACE inhibitors

  • Beta blockers
Diuretics

Diuretics are the first-line drugs in the treatment of heart failure. They are recommended in all patients with clinical evidence of fluid retention.

Classification of Diuretics

Diuretics are classified as follows:

  • Loop diuretics
  • Thiazide diuretics
  • Potassium-sparing diuretics
  • Carbonic anhydrase inhibitors

Loop Diuretics

Loop diuretics are potent diuretics used in the treatment of moderate to severe heart failure. They may be used alone or in combination with thiazides, especially metolazone, to achieve a profound diuresis.

Examples:

  • Frusemide
  • Bumetanide

Mode of Action

Loop diuretics inhibit reabsorption of sodium chloride from the ascending limb of the loop of Henle.

Frusemide

Available Preparations:

  • Tablets: 40 mg
  • Injection: 20 mg/ml

Available Brands: Lasix®, Agomide®, Frusina®

Pharmacokinetics

Frusemide is well absorbed from the GIT and excreted in the urine and partially metabolized in the liver and feces.

Indications

  • Oedema
  • Hypertension

Contraindications

  • Renal failure with anuria
  • Dehydration
  • Known hypersensitivity to frusemide
  • Hyponatraemia
  • Severe hypokalaemia
  • Severe hypernatraemia
  • Hypercalcaemia
  • Associates with liver cirrhosis

Dosage

Adult:

  • Oedema: Oral, initially 40 mg in the morning, maintenance 20-40 mg, 80 mg or more in resistant oedema
  • Children: 1-3 mg/kg daily, max 40 mg daily

Hypertension: 20-40 mg twice daily

Slow IV/IM: Initially 20-50 mg, increased if necessary in steps of 20 mg, not less than every 2 hours, doses greater than 50 mg by IV infusion only, max 20 mg daily

Side Effects

  • Gout
  • Rash
  • Nausea
  • Hypotension
  • Hypokalaemia
  • Hyponatraemia
  • Hypomagnesaemia
  • Hyperglycaemia
  • Tinnitus
  • Deafness
  • Dehydration
  • Abdominal cramps
  • Diarrhoea or constipation

Drug Interactions

  • Amphotericin B may increase the risk of nephrotoxicity caused by frusemide
  • Frusemide may decrease the effect of anticoagulants
  • Frusemide may increase the risk of lithium toxicity
  • Gentamycin may increase the risk of ototoxicity when given concurrently with frusemide
  • Cephalosporins enhance the nephrotoxicity caused by frusemide
  • Frusemide may increase the risk of digoxin toxicity

Key Issues to Note

  • Frusemide may be administered with food or milk to minimize GI distress
  • Frusemide may cause photosensitivity reactions (e.g., exposure to sunlight may cause severe sunburn)

Thiazide and Related Diuretics

Thiazide diuretics are used in the treatment of mild heart failure and are the diuretics of choice in the treatment of hypertension. They are relatively weak to be used alone in heart failure.

Examples:

  • Bendrofluazide
  • Hydrochlorothiazide
  • Chlorthalidone
  • Metolazone

Mode of Action

They act by inhibiting sodium and chloride reabsorption at proximal sites of the distal convoluted tubule. Excretion of potassium and magnesium is also enhanced, while calcium excretion is diminished.

Bendrofluazide

Available Preparations:

  • Tablets: 5 mg

Available Brands: Aprinox®, Benduric®

Pharmacokinetics

Bendrofluazide is completely absorbed from the gastrointestinal tract, a small percentage is metabolized in the liver, and is excreted unchanged in the urine.

Indications

  • Oedema
  • Hypertension

Contraindications

  • Hypersensitivity to bendrofluazide
  • Refractory hypokalaemia
  • Hyponatraemia
  • Symptomatic hyperuricaemia
  • Hypercalcaemia
  • Addison’s disease

Dosage

  • Oedema: Initially 5-10 mg daily in the morning or on alternate days, maintenance 5-10 mg 1-3 times weekly
  • Hypertension: 2.5 mg daily in the morning, higher doses rarely necessary

Side Effects

  • Gout
  • Fatigue
  • Impotence
  • Hypokalaemia
  • Hyperglycaemia
  • Hyponatraemia
  • Nausea
  • Dizziness
  • Postural hypotension
  • Hypomagnesaemia

Drug Interactions

  • The effects of digoxin may be increased by bendrofluazide
  • NSAIDs may reduce the diuretic effect of bendrofluazide
  • Bendrofluazide may increase lithium levels in the blood

Potassium-Sparing Diuretics

These drugs are relatively weak diuretics as single drugs for heart failure and are not effective for use alone in heart failure. They are used in combination with other diuretics to prevent loss of potassium caused by thiazide or loop diuretics.

Example:

  • Spironolactone

Mode of Action

They inhibit sodium reabsorption in the distal tubule by antagonizing aldosterone. As a result, distal tubule sodium-potassium exchange is reduced.

Spironolactone

Available Preparations:

  • Tablets: 25 mg, 50 mg

Available Brands: Aldactone®

Pharmacokinetics

Spironolactone is well absorbed from the gastrointestinal tract, metabolized in the liver, and excreted in urine and feces.

Indications

  • Liver cirrhosis associated with refractory oedema and ascites
  • Ascites associated with malignancy
  • Oedema in congestive heart failure
  • Nephrotic syndrome
  • Hypertension
  • Primary hyperaldosteronism

Contraindications

  • Pregnancy
  • Hyperkalaemia
  • Addison’s disease
  • Breastfeeding
  • Hyponatraemia
  • Severe renal impairment

Dosage

  • Congestive Heart Failure: 100 mg daily, increased to 400 mg daily in severe cases, maintenance dose 25-200 mg/day
  • Oedema: Initially 100 mg daily, maintenance 25-200 mg daily
  • Hypertension: 25-100 mg once daily
  • Nephrotic Syndrome: 100-200 mg/day

Side Effects

  • Ataxia
  • Nausea and vomiting
  • Confusion
  • Diarrhoea
  • Dehydration
  • Deepening of the voice
  • Menstrual irregularities
  • Hyperkalaemia
  • Hyponatraemia
  • Fever
  • Weakness
  • Headache
  • Impotence
  • Skin rash
  • Drowsiness
  • Renal impairment
  • Gynaecomastia

Drug Interactions

  • Serum concentration of digoxin may be increased when given together with spironolactone
  • NSAIDs may decrease the antihypertensive effects of spironolactone
  • Potassium supplements, ACE inhibitors, angiotensin II antagonists may increase the risk of hyperkalaemia caused by spironolactone
  • Spironolactone may decrease the anticoagulant effect of heparin

Key Issues to Note

  • Spironolactone may be administered with food
  • It may cause drowsiness and impair the ability to perform activities requiring mental alertness

Osmotic Diuretics

These drugs include:

  • Mannitol

Mode of Action

Osmotic diuretics induce diuresis by elevating the osmolarity of the glomerular filtrate, thereby hindering the tubular reabsorption of water. Excretion of sodium and chloride is increased.

Mannitol

Available Preparation:

  • Intravenous infusion: 20%

Pharmacokinetics

Following intravenous infusion, mannitol is excreted rapidly by the kidneys before any significant metabolism can take place in the liver.

Indications

  • Cerebral oedema
  • Acute anuria
  • Acute renal failure due to massive haemorrhage, trauma, shock, and major surgery
  • To promote urinary excretion of toxic substances (e.g., lithium and salicylates)

Contraindications

  • Pulmonary oedema
  • Intracranial bleeding
  • Congestive heart failure
  • Hypersensitivity to mannitol
  • Severe dehydration
  • Renal failure (anuria)

Dosage

  • Cerebral Oedema: By IV infusion 1 g/kg as a 20% solution
  • Diuresis: By IV infusion 50-200 g over 24 hours, preceded by a test dose of 200 mg/kg by slow intravenous injection
  • Advertisements

Side Effects

  • Oedema
  • Thrombophlebitis
  • Chills
  • Hypotension
  • Headache
  • Fever
  • Thirst
  • Electrolyte imbalance
  • Circulatory overload
  • Nausea and vomiting
  • Increased urinary frequency and urine volume

Drug Interactions

  • Mannitol may increase the risk of digoxin toxicity associated with mannitol-induced hypokalaemia

Hyperlipidaemia

Hyperlipidaemia refers to the presence in the blood of an abnormally high concentration of cholesterol and/or triglycerides in the form of lipoproteins. It may be divided into two:

  • Primary hyperlipidaemia
  • Secondary hyperlipidaemia

Primary hyperlipidaemia is where the raised plasma lipid concentration is the result of a genetic defect. 

Secondary hyperlipidaemia may be due to metabolic problems such as diabetes mellitus, chronic renal failure, excessive alcohol intake, hypothyroidism, etc. 

The main risk is atherosclerosis, in which fatty deposits called atheroma build up in the arteries, restricting and disrupting the flow of blood. The restriction of blood flow may lead to the formation of blood clots resulting in a stroke or heart attack.

Drugs used in the treatment of hyperlipidaemia include:

  • Statins
  • Bile acid binding resins
  • Fibrates
  • Nicotinic acid and its derivatives
  • Others (omega-3)
Statins

Statins include drugs such as:

  • Simvastatin
  • Atorvastatin
  • Fluvastatin
  • Pravastatin

Mode of Action

Statins competitively inhibit 3-hydroxy methylglutaryl co-enzyme (HMG-CoA) reductase enzyme, the rate-limiting enzyme in cholesterol synthesis, especially in the liver.

Atorvastatin

Available Preparations:

  • Tablets: 10 mg, 20 mg

Available Brands: Lipitor®, Atorva®, Atostin®, Lipiget®

Pharmacokinetics

Atorvastatin is rapidly absorbed from the gastrointestinal tract, undergoes first-pass metabolism, is metabolized in the liver, and excreted as metabolites in bile.

Indications

  • Combined or mixed hyperlipidaemia
  • Prevention of cardiovascular events in patients with type 2 diabetes
  • Primary hypercholesterolemia

Contraindications

  • Hypersensitivity to atorvastatin
  • Active liver disease
  • Pregnancy
  • Lactation

Dosage

  • Adults: Initially 10 mg daily, adjusted according to response at intervals of 4 weeks to 40 mg/day max
  • Children (10-17 years): 10 mg once daily
  • Prevention of Cardiovascular Events: 10 mg once daily

Side Effects

  • Insomnia
  • Weight gain
  • Back pain
  • Nausea
  • Skin rash
  • Impotence
  • Anorexia
  • Dizziness
  • Chest pain
  • Malaise
  • Headache
  • Muscle pain or weakness
  • Tinnitus
  • Peripheral neuropathy
  • Angina

Drug Interactions

  • Atorvastatin may increase the anticoagulant effect of warfarin, digoxin, itraconazole, oral contraceptives
  • May increase atorvastatin blood concentration resulting in severe muscle inflammation, pain, and weakness
  • Antacids and propranolol decrease atorvastatin activity
  • Clarithromycin and erythromycin elevate plasma concentrations of atorvastatin

Key Issues to Note

  • Take atorvastatin with or without regard to meals but preferably in the evening
  • Advise the patient to report symptoms of myalgia, muscle tenderness, weakness, or gastric upset
  • Female patients of childbearing age should be advised to use effective contraception


Blood and Blood Forming Organs

Anticoagulants

These are drugs that prevent the clotting of blood. Anticoagulants help to maintain normal blood flow in people who are at risk of clot formation. They can either prevent the formation of blood clots or stabilize an existing clot so that it does not break.

Anticoagulants are divided into two categories:

  • Parenteral anticoagulants
  • Oral anticoagulants

Parenteral Anticoagulants

These drugs are normally used when immediate action is required.

Examples:

  • Heparin
  • Enoxaparin (low molecular weight heparin)

Heparin

Available Preparations:

  • Injection: 5000 IU/ml

Available Brands: Cal-heparin®, Heparen®

Pharmacokinetics: After intravenous or subcutaneous injection, the onset of action is immediate, within 1-2 hours. Heparin is extensively bound to plasma proteins and is excreted in the urine mainly as metabolites.

Indications:

  • Deep vein thrombosis
  • Pulmonary embolism
  • Prophylaxis in general and gynecological surgery
  • Prophylaxis in orthopedic surgery
  • Myocardial infarction
  • Unstable angina

Contraindications:

  • Hemophilia
  • Severe hypertension
  • Recent eye surgery
  • Peptic ulcers
  • Known hypersensitivity to heparin
  • Acute bacterial endocarditis
  • Thrombocytopenia
  • Severe liver disease

Dosage:

Deep Venous Thrombosis, Pulmonary Embolism, and Unstable Angina:

  • Adults: By IV injection, loading dose of 5000 units (10,000 units in severe pulmonary embolism), followed by continuous infusion of 18 units/kg/hour or by SC injection of 15,000 units every 12 hours.
  • Children and small adults: Loading dose 50 units/kg, then 15-25 units/kg/hour by intravenous infusion or subcutaneous injection of 250 units/kg every 12 hours.

Side Effects:

  • Hemorrhage
  • Hyperkalemia
  • Chills
  • Epistaxis
  • Thrombocytopenia
  • Anaphylaxis
  • Headache
  • Nausea and vomiting
  • Urticaria

Drug Interactions:

  • Heparin increases the risk of hemorrhage when given together with oral anticoagulants like warfarin.

Key Issues to Note:

  • Advise the patient to report any signs of bleeding from the gums, under the skin, urine, or stool.
  • Advise the patient to limit alcohol intake during treatment.
  • Do not administer IM due to pain, irritation, and hematoma formation.
  • When given together with oral anticoagulants, heparin should be withdrawn once effective oral anticoagulation is established.

Oral Anticoagulants

Oral anticoagulants are effective in the primary and secondary prevention of venous thromboembolism.

Examples:

  • Warfarin

Warfarin

Available Preparations:

  • Tablets: 3 mg, 5 mg

Available Brands: Marevan®

Pharmacokinetics: Warfarin is readily absorbed from the gastrointestinal tract, crosses the placenta but does not occur in significant quantities in breast milk. It is extensively metabolized in the liver and excreted in urine and bile.

Indications:

  • Prophylaxis of embolism in rheumatic heart disease and atrial fibrillation
  • Prophylaxis after insertion of prosthetic heart valve
  • Prophylaxis and treatment of venous thrombosis and pulmonary embolism
  • Myocardial infarction

Contraindications:

  • Hypersensitivity to the drug
  • Peptic ulcer
  • Severe hypertension
  • Bacterial endocarditis
  • Pregnancy
  • Alcoholism
  • Bleeding disorders

Dosage:

  • Initially 5 mg daily for 2-5 days, then adjust according to response to the usual maintenance dose of 3-9 mg daily.

Side Effects:

  • Hemorrhage
  • Rash
  • Jaundice
  • Hepatic dysfunction
  • Vomiting
  • Skin rash
  • Nausea and vomiting
  • Hypersensitivity
  • Diarrhea
  • Headache
  • Pancreatitis
  • Urticaria
  • Abdominal cramps

Drug Interactions:

  • Drugs that decrease warfarin anticoagulant effect include alcohol, carbamazepine, phenytoin, cholestyramine, rifampicin, oral contraceptives, and vitamin K.
  • Concomitant use with amiodarone, metronidazole, cimetidine, and streptokinase may increase the anticoagulant effect of warfarin.

Key Issues to Note:

  • Warn the patient that bleeding may occur, especially at the beginning of treatment and with high doses.
  • Warfarin may be administered on an empty or full stomach.
  • Adequate anticoagulation is not observed until about 3-4 days after initial administration of warfarin; heparin should be used concurrently if immediate effect is required.
  • Advertisements

Antiplatelet Drugs

Antiplatelet drugs inhibit thrombus formation by decreasing platelet aggregation. They are used to prevent further thromboembolic events in patients who have suffered myocardial infarction, ischemic stroke or transient ischemic attacks, or unstable angina.

Examples:

  • Aspirin (low dose)
  • Clopidogrel
  • Dipyridamole

Aspirin

Available Preparations:

  • Tablets: 75 mg, 100 mg

Available Brands: Ecorin®, Aspirem®, Ascard®, Bayer Aspirin Cardio®

Indications:

  • Acute myocardial infarction
  • Unstable angina
  • Primary and secondary prevention of stroke

Contraindications:

  • Children and adolescents under 16 years
  • Hypersensitivity to aspirin or NSAIDs
  • Aspirin-sensitive asthma
  • Active peptic ulcer
  • Breastfeeding
  • Hemophilia

Dosage:

  • 75 mg daily. 150-300 mg daily may be required in acute conditions (MI, acute ischemic stroke, unstable angina).

Side Effects:

  • Bronchospasms
  • Nausea and vomiting
  • Increased bleeding time
  • Urticaria
  • Ringing in the ears
  • Dizziness
  • Heartburn
  • Gastrointestinal bleeding

Drug Interactions:

  • Aspirin increases the risk of bleeding when given together with oral anticoagulants and heparin.
  • Aspirin decreases the diuretic effect of spironolactone and frusemide.
  • Aspirin decreases the antihypertensive effect of captopril and beta-blockers.

Key Issues to Note:

  • The drug should be administered with food.
  • Avoid alcohol while taking aspirin.
  • Avoid use of OTC preparations for pain without recommendation of a clinician.
Thrombolytics

Thrombolytics are drugs used to break up or dissolve blood clots that have already formed. Thrombolytic enzymes are used to lyse the thrombi that obstruct coronary or pulmonary arteries.

Examples:

  • Streptokinase
  • Urokinase

Mode of Action: They act by converting plasminogen to plasmin, which catalyzes the breakdown of fibrin and therefore is able to dissolve blood clots.

Streptokinase

Available Preparations:

  • Injection: 1,500,000 IU

Available Brands: Stpase®

Indications:

  • Acute myocardial infarction
  • Deep vein thrombosis
  • Pulmonary embolism
  • Acute arterial thromboembolism

Contraindications:

  • Active internal bleeding
  • Recent trauma to the head
  • Severe uncontrollable hypertension
  • Uncontrollable clotting disorders
  • Intracranial surgery
  • Recent cerebral vascular accident
  • Severe allergic reactions
  • Recent abortion or delivery

Dosage:

  • Myocardial Infarction: IV infusion 1,500,000 units over 30-60 minutes.
  • Deep Vein Thrombosis, Pulmonary Embolism, Acute Arterial Thromboembolism, Arterial Thrombosis: By IV infusion 250,000 units infused over 30 minutes, then 100,000 units/hour for up to 12-72 hours according to the patient’s condition.

Side Effects:

  • Fever
  • Headache
  • Skin rash and itching
  • Vomiting
  • Convulsions
  • Nausea
  • Nephritis
  • Hypotension
  • Malaise
  • Superficial bleeding at puncture site

Drug Interactions:

  • Heparin, oral anticoagulants, aspirin, dipyridamole may increase the risk of bleeding when given together with streptokinase.
Antifibrinolytic Drugs

These drugs inhibit the dissolution of blood clots.

Examples:

  • Tranexamic acid

Tranexamic Acid

Available Preparations:

  • Tablets/Capsules: 500 mg

Available Brands: Tranlok®, Hemsamic®

Combinations: Tranfib-MF® (tranexamic acid/mefenamic acid) 500/250

Mode of Action: Tranexamic acid acts primarily by blocking the binding of plasminogen and plasmin to fibrin.

Pharmacokinetics: Tranexamic acid is rapidly and completely absorbed from the GIT, crosses the placenta, distributes into breast milk. It is metabolized in the liver and excreted in urine.

Indications:

  • Menorrhagia
  • Prevention of bleeding in prostatectomy and dental extraction in patients with hemophilia
  • Epistaxis
  • Thrombolytic overdose
  • Prophylaxis of hereditary angioedema

Contraindications:

  • Hypersensitivity to tranexamic acid
  • Severe renal impairment
  • Thromboembolic disease

Dosage:

Oral:

  • Menorrhagia (inhibited when menstruation has started): 1 g 3 times daily for 3-4 days
  • Hereditary Angioedema: 1-1.5 g 2-3 times daily
  • Epistaxis: 1 g 3 times daily for 7 days

Side Effects:

  • Nausea
  • Diarrhea
  • Thrombosis
  • Vomiting
  • Hypotension
  • Disturbances in color vision

Drug Interactions:

  • Heparin, oral anticoagulants, aspirin, dipyridamole may increase the risk of bleeding when given together with tranexamic acid.


Drugs Used in the Treatment of Anaemia

Anaemia is defined as a decrease in hemoglobin concentration below that necessary for tissue oxygenation. It may be caused by increased RBC loss, decreased production of RBCs, or increased destruction of RBCs.

Ferrous Sulphate

Available Preparations:

  • Tablets: 200 mg

Available Brands: Cyano Iron®, Ferol®

Indications:

  • Iron deficiency anaemia

Contraindications:

  • Haemolytic anaemias
  • Peptic ulcer disease
  • Patients receiving blood transfusion
  • Hemosiderosis
  • Haemochromatosis

Dosage:

  • Iron Deficiency Anaemia: 200 mg 2-3 times daily
  • Prophylaxis of Anaemia: 200 mg daily

Side Effects:

  • Constipation
  • Diarrhea
  • Anorexia
  • Epigastric pain
  • Dark stool
  • Gastrointestinal irritation
  • Nausea

Drug Interactions:

  • Antacids and cimetidine decrease the absorption of ferrous sulphate
  • Chloramphenicol may increase the serum levels of ferrous sulphate
  • Ferrous sulphate decreases the anti-infective effect of quinolones when given concurrently
  • The drug may be given with meals

Folic Acid

Available Preparations:

  • Tablets: 5 mg

Available Brands: Folacid®, Asflic®, Folon®

Pharmacokinetics: Folic acid is rapidly absorbed from the gastrointestinal tract, distributed to all body tissues, metabolized in the liver to the active form, and excreted in urine.

Indications:

  • Folate-deficient megaloblastic anaemia
  • Prophylaxis in chronic hemolytic states or renal dialysis
  • Prevention of neural tube defects in pregnancy
  • Nutritional supplement

Contraindications:

  • Folate-dependent malignant disease
  • Aplastic anaemia
  • Hypersensitivity to folic acid

Dosage:

  • Megaloblastic Anaemia: 5 mg once daily for 4 months, up to 15 mg daily may be given in malabsorption states
  • Prevention of Neural Tube Defect: 400 micrograms daily before conception and during the first 12 weeks of pregnancy
  • Prevention of Recurrence of Neural Tube Defect: 5 mg daily from at least 4 weeks before conception until 12 weeks of pregnancy
  • Children (Folic Acid Deficiency): 1-2 mg daily

Side Effects:

  • Nausea
  • Headache
  • Insomnia
  • Irritability
  • Skin rash
  • Fever
  • Diarrhea
  • Bronchospasm

Drug Interactions:

  • Folic acid may decrease serum phenytoin concentrations
  • Antifolate drugs such as trimethoprim may interfere with folic acid metabolism and may cause deficiency in patients with low folic acid stores
  • Chloramphenicol may antagonize the hematologic response to folic acid

Combination Preparations: Ferrous Salts with Folic Acid

Available Preparations:

  • Capsules
  • Suscaps
  • Tablets

Available Brands: Aktiferrin-F®, Fefol®, Fef®, Fefan®

Indications:

  • Prevention of iron and folic acid deficiencies in pregnancy, after delivery, and lactation

Contraindications:

  • Known hypersensitivity to any of the ingredients

Dosage:

  • One capsule/suscap/tablet once daily

Side Effects:

  • Sensation of fullness
  • Nausea and vomiting
  • Diarrhea
  • Constipation

Drugs Used in the Treatment of Cardiovascular Disorders Read More »

Drugs Acting on the Respiratory System

Drugs Acting on the Respiratory System

Drugs Acting on the Respiratory System

Drugs used in the treatment of respiratory tract disorders include:

  • Drugs for Asthma
  • Drugs for Allergic Rhinitis
  • Drugs for Cough
  • Drugs for Common Cold and Flu

Drugs Used in the Treatment of Asthma

Asthma is a chronic disease of the airways characterized by inflammation and reversible bronchospasm. It is associated with symptoms such as wheezing, breathlessness, chest tightness, and cough. Drugs used in the treatment of asthma are broadly divided into two categories:

  • Bronchodilators
  • Anti-inflammatory drugs

Table 1: Classification of Anti-Asthmatic Drugs

Class

Examples

Bronchodilators

Beta2 agonists, Xanthine derivatives, Anticholinergics

Anti-inflammatory drugs

Corticosteroids, Mast cell stabilizers, Leukotriene receptor antagonists

Beta2 Agonists

Beta2 agonists promote bronchodilation by stimulating beta2 receptors in bronchial smooth muscles. They are further divided into short-acting and long-acting beta2 agonists.

  • Short-acting beta2 agonists such as salbutamol and terbutaline have a rapid onset and short duration of action. They are recommended for the treatment of acute asthma attacks.
  • Long-acting beta2 agonists such as salmeterol and formoterol have a delayed onset and long duration of action. These drugs are usually combined with inhaled corticosteroids such as budesonide for the long-term control of chronic asthma.

Salbutamol

Available Preparations:

  • Inhaler: 100 mcg
  • Nebulized solution: 5 mg/ml
  • Syrup: 2 mg/5 ml
  • Tablets: 4 mg

Available Brands: Ventolin®, Vental®, Kamvent®

Pharmacokinetics: Salbutamol is readily absorbed from the gastrointestinal tract, metabolized in the liver, rapidly excreted in the urine as metabolites and as unchanged drug, and a small amount is excreted in the feces.

Indications:

  • Prophylaxis and treatment of asthma
  • Chronic obstructive pulmonary disease
  • Arrest premature labor

Contraindications:

  • Hypersensitivity to salbutamol
  • Eclampsia and severe preeclampsia

Dosage:

Oral:

Adults: 4 mg 3-4 times daily, max single dose 8 mg

Children:

  • 7-12 years: 2 mg 3-4 times daily
  • 2-6 years: 1-2 mg 3-4 times daily
  • 1 month-2 years: 100 mcg/kg 3-4 times daily

Aerosol Inhalation:

  • Adults: 100-200 mcg (1-2 puffs, for persistent symptoms up to 4 times daily)
  • Children: 100 mcg (1 puff), increased to 200 mcg (2 puffs) if necessary, for persistent symptoms up to 4 times daily

Nebulized Solution:

  • Children: > 2 years: 2.5-5 mg, repeat 3-4 times daily as necessary
  • Children: < 2 years: 0.1 mg/kg up to 2.5 mg, repeat 3-4 times daily

Prophylaxis in Exercise-Induced Bronchospasm:

  • Adults: 200-400 mcg (2 puffs)
  • Children: 100-200 mcg up to 4 times daily

Side Effects:

  • Tachycardia
  • Arrhythmias
  • Nervousness
  • Angioedema
  • Fine tremor, especially of hands
  • Hypersensitivity reactions
  • Palpitations
  • Insomnia
  • Muscle cramps
  • Headache

Drug Interactions:

  • Diuretics or digoxin: risk of cardiac arrhythmias is increased
  • Corticosteroids: risk of hypokalemia and hyperglycemia is increased

Key Issues to Note:

  • Salbutamol may delay labor in pregnant mothers near term
  • Patients should swallow tablets whole with a glass of water
  • Do not administer salbutamol within 1 hour of ingesting antacids, milk, or dairy products
  • Salbutamide is habit-forming; therefore, long-term use may result in laxative dependency and loss of normal bowel function
  • Onset of action is 6-12 hours for tablets, 15-60 minutes for suppository
  • Warn the patient that prolonged use of salbutamol suppositories may cause proctitis

Xanthines

Xanthines include:

  • Aminophylline
  • Theophylline

They act by relaxing bronchial smooth muscle by inhibiting phosphodiesterase, the enzyme which breaks down cyclic AMP. Aminophylline is usually preferred to theophylline when greater solubility in water is required, particularly in intravenous formulations.

Aminophylline

Available Preparations:

  • Tablets: 100 mg
  • Injection: 250 mg/10 ml

Indications:

  • Acute severe asthma
  • Reversible airway obstruction
  • Relieve apnea in neonates
  • Nocturnal asthma

Contraindications:

  • Porphyria
  • Known hypersensitivity to aminophylline

Dosage:

Chronic Asthma:

  • Oral: 100-200 mg 3-4 times daily, after food

Acute Severe Asthma (not treated with theophylline before):

Adults: IV loading dose 5-6 mg/kg slowly over 20-30 min diluted in normal saline or dextrose 5%

Maintenance: IV infusion 0.5 mg/kg/hour

Children: IV loading dose 4-6 mg/kg slowly over 20-30 min suitably diluted and 1.5-2.5 mg per kg in those using oral theophylline

Maintenance: By IV infusion

  • 6 months-9 years: 1 mg/kg/hour
  • 10-16 years: 0.8 mg/kg/hour

Side Effects:

  • Restlessness
  • Anxiety
  • Palpitations
  • Insomnia
  • Convulsions
  • Urticaria
  • Gastrointestinal irritation
  • Hypotension, especially if given by rapid injection
  • Tremor
  • Headache
  • Dizziness
  • Arrhythmias
  • Epigastric pain

Drug Interactions:

  • Beta blockers: may decrease the effects of aminophylline
  • Cimetidine, ciprofloxacin, erythromycin, norfloxacin: may increase aminophylline blood concentration and risk of aminophylline toxicity
  • Phenytoin, rifampicin, carbamazepine: may increase aminophylline metabolism
  • Smoking: may decrease aminophylline blood concentration
  • Caffeine: may intensify the adverse effects of aminophylline on the CNS and heart
  • Advertisements

Key Issues to Note:

  • Rapid IV injection should be avoided as it may result in hypotension, seizures, and arrhythmias (less than 20-25 mg/min) is required
  • Patients taking oral aminophylline should not receive intravenous aminophylline unless plasma concentration is available to guide dosage
  • Patients should avoid caffeine-containing beverages and other sources of caffeine
Corticosteroids

Corticosteroids may be given parenterally, orally, or as inhalers. Inhaled corticosteroids include:

  • Beclomethasone
  • Budesonide
  • Fluticasone

These drugs are the most effective in the treatment of chronic asthma. Corticosteroids reduce bronchial mucosal inflammation and bronchial hyper-reactivity. They are recommended for the prophylaxis of asthma in patients who have not responded to beta2 agonists or if symptoms disturb sleep more than once a week. Corticosteroid inhalers must be used regularly for effective control of symptoms. Alleviation of symptoms usually occurs after 7 days of initiating treatment.

Beclomethasone

Available Preparations:

  • Metered Inhaler: 50 mcg

Available Brands: Becotide®, Beclate®

Indications:

  • Prophylaxis of asthma

Contraindications:

  • Status asthmaticus
  • Hypersensitivity to beclomethasone
  • Acute infections uncontrolled by antimicrobial chemotherapy

Dosage:

  • Adults: 200 mcg twice daily or 100 mcg 3-4 times daily
  • Children: 50-100 mcg 2-4 times daily or 100 mcg twice daily

Side Effects:

  • Oropharyngeal candidiasis
  • Hoarseness
  • Paradoxical bronchospasm
  • Adrenal suppression
  • Impaired bone metabolism
  • Glaucoma and cataracts

Systemic Corticosteroids

These drugs are given either orally or by injection. Examples include:

  • Prednisolone/Prednisone
  • Betamethasone
  • Triamcinolone
  • Hydrocortisone
  • Dexamethasone
  • Methylprednisolone

Table 2: Characteristics of Corticosteroids

Class

Examples

Short-acting

Hydrocortisone

Intermediate-acting

Prednisolone, Prednisone, Methylprednisolone, Triamcinolone

Long-acting

Dexamethasone, Betamethasone

Prednisolone

Available Preparations:

  • Tablets: 5 mg

Available Brands: Kampred®

Indications:

  • Bronchial asthma
  • Cerebral edema
  • Allergic reactions
  • Acute leukemia
  • Rheumatic disease
  • Inflammatory bowel disease
  • Suppression of inflammatory reactions
  • Acute or chronic adrenal insufficiency

Contraindications:

  • Systemic infection (unless life-threatening)
  • Avoid live virus vaccines
  • Hypersensitivity to prednisolone

Dosage:

  1. Initially: 10-20 mg daily (up to 60 mg in severe diseases) preferably taken in the morning after breakfast, and often be reduced within a few days but may need to be continued for several weeks or months
  2. Maintenance: 2.5-15 mg daily but higher doses may be needed
  3. Children:
  • 1-6 years: 5 mg daily up to 15 mg in severe cases
  • 7-12 years: 5-10 mg daily up to 30 mg in severe cases

Side Effects:

  • Dyspepsia
  • Osteoporosis
  • Glaucoma
  • Skin atrophy
  • Weight gain
  • Menstrual irregularities
  • Peptic ulcer
  • Increased appetite
  • Acne
  • Adrenal suppression
  • Striae

Drug Interactions:

  • Prednisolone may decrease the effect of diuretics, insulin, oral antidiabetics, and potassium supplements
  • Prednisolone may increase the risk of digoxin toxicity caused by hypokalemia
  • Prednisolone may decrease the patient’s antibody response to vaccines

Key Issues to Note:

  • Take the drug after meals, with food or milk to decrease GI upset
  • Advise the patient to avoid alcohol, limit caffeine
  • Advise the patient not to decrease the dose or discontinue without doctor’s approval

Dexamethasone

Available Preparations:

  • Tablets: 0.5 mg
  • Injection: 4 mg/ml

Available Brands: Dexona®

Pharmacokinetics: Dexamethasone is readily absorbed from the gastrointestinal tract, crosses the placenta with minimal inactivation, and is excreted in urine within 24 hours.

Indications:

  • Cerebral edema
  • Rheumatic diseases
  • Anaphylaxis
  • Septic shock
  • Nausea and vomiting due to anti-cancer drugs
  • Bacterial meningitis (in combination with antibiotics)
  • Acute exacerbation of chronic allergic disorders

Contraindications:

  • Hypersensitivity to dexamethasone
  • Systemic infections
  • Avoid live virus vaccines

Dosage:

Oral:

  • Adults: 0.5-2 mg daily but higher doses may be required depending on the severity of the condition
  • Children: 100-1000 mcg/kg daily in 1-2 divided doses

Injection:

  • Adults: 1M or slow IV or infusion: 0.5-24 mg daily
  • Children: 200-400 mcg/kg daily in 1-2 divided doses

Cerebral Edema Associated with Malignancy:

  • IV injection (as dexamethasone phosphate): initially 10 mg then 4 mg by IM every 6 hours for 2-4 days gradually reduced and stopped over 5-7 days
  • Children: IV 0.25 mg/kg/day in divided doses for up to 2 days then gradually taper down over the next 5 days

Side Effects:

  • Hypertension
  • Hyperglycemia
  • Edema
  • Glaucoma
  • Weight gain
  • Growth suppression in children
  • Increased appetite
  • Muscle atrophy
  • Cataracts
  • Peptic ulcer
  • Hypokalemia
  • Advertisements

Drug Interactions:

  • Increased risk of hypokalemia when used concurrently with amphotericin B or loop diuretics
  • Concurrent use with aspirin may lead to increased gastrointestinal tract side effects

Key Issues to Note:

  • Administer the drug with food or milk to minimize GI side effects
  • Advise the patient to avoid alcohol and limit caffeine intake
  • Advise the patient to avoid exposure to measles or chickenpox
  • Inform the patient not to decrease the dose or stop treatment without doctor’s recommendation

Hydrocortisone

Available Preparations:

  • Injection: 100 mg

Available Brands: Cardilan®, Primacort®, Stricort®

Indications:

  • Hypersensitivity reactions including anaphylaxis
  • Inflammatory bowel disease
  • Asthmatic attack
  • Hemorrhoids
  • Rheumatic diseases
  • Adrenocortical insufficiency
  • Angioedema

Contraindications:

  • Systemic infections
  • Avoid live virus vaccines in those receiving immunosuppressive doses
  • Hypersensitivity to hydrocortisone

Dosage:

Anaphylaxis; Acute Severe Asthma and Shock:

IV slow IV injection or infusion:

Adults: 100-500 mg 3-4 times daily

Children:

  • 6-12 years: 100 mg 3-4 times daily
  • 1-5 years: 50 mg 3-4 times daily
  • Up to 1 year: 25 mg 3-4 times daily

Side Effects:

  • Dyspepsia
  • Adrenal suppression
  • Weight gain
  • Glaucoma
  • Nausea
  • Peptic ulceration
  • Menstrual irregularities
  • Increased appetite
  • Acne
  • Malaise

Drug Interactions:

  • Anti-convulsants, rifampicin: reduce the effectiveness of hydrocortisone
  • Hydrocortisone: reduces the action of antidiabetic drugs
  • Hydrocortisone: reduces the effect of antihypertensive drugs
  • Hydrocortisone: may decrease the patient’s antibody response to vaccines, increase vaccine side effects, and potentiate virus replication when given with live virus vaccine
Leukotriene Receptor Antagonists

This class includes:

  • Zafirlukast
  • Montelukast

These drugs act by suppressing the effects of leukotrienes, compounds that promote bronchoconstriction as well as eosinophil infiltration, mucus production, and airway edema.

Zafirlukast

Available Preparations:

  • Tablets: 20 mg

Available Brands: Accolate®

Pharmacokinetics: Zafirlukast is rapidly absorbed after oral administration, extensively metabolized in the liver, and excreted in feces.

Indications:

  • Prophylaxis of asthma
  • Exercise-induced asthma

Contraindications:

  • Hypersensitivity to zafirlukast
  • Breastfeeding
  • Hepatic impairment

Dosage:

  • Adults: 20 mg twice daily at least 1 hour before or 2 hours after meals
  • Children under 12 years: Not recommended

Side Effects:

  • Headache
  • Diarrhea
  • Insomnia
  • Dyspepsia
  • Dizziness
  • Nausea
  • Fever
  • Malaise
  • Vomiting
  • Abdominal pain

Drug Interactions:

  • Blood levels are increased by aspirin
  • Blood levels are decreased by erythromycin and theophylline
  • Zafirlukast increases the effects and risk of bleeding with warfarin

Key Issues to Note:

  • Give the drug at least 1 hour before or 2 hours after a meal
  • Advise the patient to take the drug as prescribed even during symptom-free periods
  • Do not use the drug to treat acute episodes of asthma
  • Advise the patient not to decrease the dose or stop unless instructed by the doctor
  • Nursing women should not take zafirlukast
  • Inform the patient to report symptoms such as abdominal pain, nausea, fatigue, itching, or anorexia


Drugs for Allergic Rhinitis

Rhinitis is an inflammation of the nasal mucous membrane and is characterized by periods of nasal discharge, sneezing, and nasal congestion. 

Rhinitis may be allergic or non-allergic in origin.

Allergic Rhinitis

Allergic rhinitis is defined as a nasal mucous membrane inflammation caused by a hypersensitivity response to foreign allergens mediated by IgE antibodies.

Drugs used in the treatment of allergic rhinitis include:

  • Antihistamines
  • Decongestants
  • Corticosteroids
  • Mast cell stabilizers

Antihistamines

Antihistamines are the mainstay in the treatment of seasonal and perennial allergic rhinitis. They relieve symptoms such as rhinorrhea, edema, nasal itching, sneezing, and ocular symptoms such as conjunctivitis. They are more effective when taken before the start of symptoms.

Classification of Antihistamines

Antihistamines are classified as follows:

  1. Sedating antihistamines
  2. Non-sedating antihistamines

Sedating Antihistamines

They are also called first-generation antihistamines. Sedating antihistamines cross the blood-brain barrier and are associated with marked sedation and depression.

Examples:

  • Chlorpheniramine
  • Hydroxyzine
  • Promethazine
  • Cyproheptadine

Chlorpheniramine

Available Preparations:

  • Tablets: 4 mg
  • Syrup: 2 mg/5 ml

Available Brands: Piriton®, Piton®

Pharmacokinetics: Chlorpheniramine is well absorbed following oral administration, distributed to body tissues, including the placenta. It is metabolized in the liver and excreted in urine.

Indications:

  • Conjunctivitis
  • Allergic rhinitis
  • Pruritus of allergic origin
  • Acute urticaria
  • Insect stings
  • Severe angioedema

Contraindications:

  • Hypersensitivity to chlorpheniramine
  • Acute attack of asthma
  • Third trimester of pregnancy
  • Breastfeeding
  • Narrow-angle glaucoma

Dosage:

Adults and Children over 12 years: 4 mg every 4-6 hours

Advertisements

Children:

  • 6-12 years: 2 mg every 4-6 hours
  • 1-5 years: 1 mg 3 times daily
  • 6 months-12 months: 1 mg twice daily

Side Effects:

  • Drowsiness
  • Dizziness
  • Epigastric pain
  • Headache
  • Palpitations
  • CNS depression
  • Urinary retention
  • Dry mouth
  • Blurred vision
  • Sweating
  • Tremor

Drug Interactions:

  • Chlorpheniramine potentiates sedative effects of barbiturates, hypnotics, opioid analgesics
  • Increased sedative effects with alcohol

Key Issues to Note:

  • Advise the patient to take the drug after food to minimize GI distress
  • Inform the patient that chlorpheniramine may cause drowsiness and impair the ability to perform activities requiring mental alertness
  • Advise the patient to avoid direct exposure to sunlight since it may cause severe sunburn
  • Avoid alcohol while taking chlorpheniramine

Non-Sedating Antihistamines

Non-sedating antihistamines are less sedating than the first generation.

Examples:

  • Cetirizine
  • Loratadine
  • Desloratadine
  • Levocetirizine
  • Ebastine

Cetirizine

Available Preparations:

  • Tablets: 10 mg
  • Syrup: 5 mg/5 ml

Available Brands: Zyrtec®, Finallergy®, Zyncet®, Allercet®, Alerid®

Pharmacokinetics: Cetirizine is rapidly and almost completely absorbed from the GIT, undergoes slow first-pass metabolism, and is excreted in urine primarily as unchanged drug.

Indications:

Symptomatic relief of allergy such as:

  • Allergic rhinitis
  • Allergic conjunctivitis
  • Atopic dermatitis
  • Chronic urticaria

Contraindications:

  • Hypersensitivity to cetirizine
  • Breastfeeding
  • Pregnancy
  • Acute attacks of asthma

Dosage:

Adults and Children over 6 years: 10 mg daily or 5 mg twice daily

Children:

  • 2-5 years: 2.5 mg once daily or 2.5 mg twice daily
  • 6 months-1 year: 2.5 mg once daily

Side Effects:

  • Somnolence
  • Insomnia
  • Headache
  • Dizziness
  • Dry mouth
  • Abdominal pain
  • Nausea and vomiting
  • Diarrhea
  • Bronchospasm
  • Pharyngitis
  • Malaise

Drug Interactions:

  • Alcohol and other CNS depressants may increase CNS depression

Key Issues to Note:

  • The drug can be given without regard to food
  • Cetirizine may cause drowsiness and impair the ability to perform activities requiring mental alertness
  • Cetirizine may cause dry mouth; therefore, advise the patient to drink a lot or to use sugarless gum
  • Avoid alcohol while taking cetirizine

Drugs Used in the Treatment of Cough

Cough is a useful natural response to irritation of the lungs and airways aimed at removing foreign substances or excessive secretions.

Cough may occur as a symptom of an underlying disorder such as asthma, pneumonia, sinusitis, or gastroesophageal reflux disease.

It may be classified as follows:

  • Non-productive cough
  • Productive cough

Productive Cough

Productive cough is characterized by the presence of sputum and may be associated with conditions such as chronic bronchitis, asthma, and pneumonia. It is commonly treated with cough expectorants or mucolytics.

Non-Productive Cough

This type of cough is associated with no mucus production and is regarded as a useless cough. It is commonly associated with the common cold and is treated with cough suppressants or antitussives.

Cough Expectorants

Cough expectorants facilitate the expulsion of mucus and other materials from the lungs. Cough expectorants contain one or more of the following:

  • Guaifenesin
  • Ammonium chloride
  • Ipecacuanha
  • Squill
  • Volatile oils
  • Guaiacol
  • Iodides
  • Sodium citrate
  • Creosote

Preparations which contain cough expectorants include:

  • Cadistin syrup®
  • Cadiphen syrup®
  • Histalin syrup®
  • Hydrylin syrup®
  • Delased chesty®
  • Actified expectorant®
  • Menthodex syrup®
  • Zecuf herbal syrup®
Mucolytic Expectorants

Mucolytics reduce the viscosity of bronchial secretions by breaking down the structure of tenacious sputum, thereby facilitating its removal by coughing. Mucolytics are often used in chronic bronchitis and chronic asthma where sputum production is high.

Examples:

  • Bromhexine
  • Carbocisteine
  • Ambroxol
Common compound preparations containing mucolytics include:
  • Rhinathiol syrup®
  • Brozedex®
  • Ascoril®
  • Bisolvin®
  • Ambrodil®

Demulcents

Demulcent cough preparations coat the mucosa of the pharynx and provide short-lived relief of the irritation that provokes the cough reflex. They contain soothing substances such as:

  • Glycerol
  • Honey
  • Liquorice
  • Sucrose syrup

Compound preparations containing demulcents include:

  • Simple linctus
  • Menthodex lozenges
  • Zecuf lozenges
Cough Suppressants

Cough suppressants act centrally to reduce the sensitivity of the cough center. They should be avoided in chronic obstructive airway diseases as they may also depress respiration. Most cough suppressants are opiate derivatives and may cause constipation and abuse. They should be avoided in children below one year.

Examples include codeine, pholcodine, and dextromethorphan; the latter two generally have fewer adverse effects than codeine.

Compound preparations containing cough suppressants include: Benylin with codeine®, Benylin DM®, Rhinathiol dry cough®, Piritex with codeine®, Hydryllin DM®, Piritex Junior®, Actifed syrup®, Delased dry cough®, and Zedex®.

Drugs Acting on the Respiratory System Read More »

Medicines Acting on Specific Body Systems

Medicines Acting on Specific Body Systems

Medicines Acting on Specific Body Systems

Medicines play a big role in modern healthcare, providing solutions to a wide range of diseases and disorders. The human body is a network of interconnected systems, each with its functions and challenges. To address these challenges, pharmacologists have developed drugs that act on specific body systems, ensuring targeted and effective treatment for various conditions.

These medicines are designed to interact with specific organs, tissues, or biochemical pathways, either by enhancing normal physiological functions or by correcting pathological imbalances. For example, cardiovascular drugs regulate heart function and blood pressure, while respiratory drugs help manage conditions like asthma and chronic obstructive pulmonary disease (COPD). Similarly, gastrointestinal drugs address issues such as acid reflux, ulcers, and irritable bowel syndrome, and endocrine drugs help manage hormonal imbalances like diabetes or thyroid disorders.


Drugs Acting on the Gastrointestinal System

Drugs Acting on the Gastrointestinal System

Drugs for Peptic Ulcer Disease

Peptic Ulcer Disease (PUD)

Peptic ulcer disease develops when there is an imbalance between mucosal protective substances such as mucus and bicarbonate, and destructive substances like acid, H. pylori bacteria, and pepsin. Drugs used in the treatment of peptic ulcer disease include:

  • Antacids
  • H2 receptor antagonists
  • Proton pump inhibitors
  • Mucosal protectives
  • Antibiotics

Antacids

These are alkaline compounds that neutralize stomach acid, raising the gastric pH and thereby relieving pain. They are often given concurrently with acid-suppressing drugs such as H2 receptor antagonists and proton pump inhibitors in the treatment of peptic ulcers and reflux esophagitis. Most antacids contain aluminum hydroxide, magnesium hydroxide, sodium bicarbonate, or calcium carbonate. Other ingredients added to antacids include simethicone and alginic acid.

  • Simethicone: Added to antacids to relieve flatulence and dyspepsia. It may be beneficial in relieving colic pain in infants. Common brands containing simethicone include Maalox Plus®, Alcid®, and Gestid®.
  • Alginates: Added to antacids as protectants and are useful in the treatment of reflux esophagitis. Common brands containing alginate include Gaviscon®.
  • Local anesthetics: Such as oxethazaine are added to antacids to reduce the pain associated with dyspepsia. Common brands containing oxethazaine include Mucogel® suspension and Mucaine® suspension.

Antacids containing sodium bicarbonate have a fast onset of action, but their absorption may worsen hypertension and heart failure.

Indications

Symptomatic relief of:

  • Dyspepsia
  • Gastroesophageal reflux disease
  • Peptic ulcer disease
  • Gastritis
  • Heartburn

Contraindications

  • Patients with severe abdominal pain of unknown cause
  • Lactation
  • Patients with cardiovascular problems (antacids with sodium)

Side Effects

  • Magnesium-containing antacids tend to cause diarrhea, whereas aluminum-containing antacids may cause constipation and delay gastric emptying. A combination of the two may reduce the side effects of each.

Key Issues to Note

  • Antacids should be taken between meals or at bedtime when symptoms are expected to occur.
  • Optimum antacid effect is obtained if taken 1-3 hours after meals.
  • Liquid antacids are generally more effective than tablets and have a rapid onset of action.
  • Antacids are effective for a short period and should be given on a 6-hourly basis.
  • Antacids may interact with numerous other drugs, affecting the rate and extent of their absorption. For example, tetracycline, ciprofloxacin, iron, indomethacin, and digoxin. A minimum interval of at least 2 hours should be left between the administration of antacids and other drugs.
Common Antacid Preparations

ACICONE-S®

Available Preparations: Tablets, Suspension

Composition:

  • Tablets: Magaldrate 720 mg, Simethicone 25 mg
  • Suspension: Magaldrate 540 mg, Simethicone 40 mg

Indications:

  • Heartburn in reflux esophagitis
  • Prophylaxis against ulcer complications
  • Adjunct to the treatment of peptic ulcers

Dosage:

  • Tablets: 1 tablet to be chewed 4 times daily after meals or at bedtime
  • Suspension: 5-10 ml 4 times daily after meals or at bedtime

AGOCID®

Available Preparations: Suspension

Composition: Dried aluminum gel 250 mg, Magnesium hydroxide 250 mg, Simethicone 50 mg

Indications:

  • Acid dyspepsia
  • Heartburn
  • Pregnancy heartburn
  • Adjunct to peptic ulcer treatment
  • Reflux esophagitis

Dosage: 5-10 ml 4 times daily between meals

ALCID®

Available Preparations: Suspension

Composition: Aluminum hydroxide gel 400 mg, Magnesium hydroxide 400 mg, Simethicone 50 mg

Indications:

  • Gastritis
  • Flatulence
  • Hiatus hernia
  • Adjunct to the treatment of peptic ulcers
  • Heartburn associated with reflux esophagitis
  • Heartburn in pregnancy

Dosage: 5-10 ml 4 times a day between meals and at bedtime

CENTACID®

Available Preparations: Suspension

Composition: Aluminum hydroxide gel 250 mg, Magnesium hydroxide 200 mg, Simethicone 40 mg

Indications:

  • Acid dyspepsia
  • Reflux esophagitis
  • Gastritis
  • Pregnancy heartburn
  • Hiatus hernia

Dosage: 5-10 ml 4 times a day between meals and at bedtime

RELCERGEL®

Available Preparations: Suspension

Composition: Aluminum hydroxide gel 6 g, Magnesium hydroxide 80 mg, Simethicone 100 mg, Deglycyrrhizinated liquorice 400 mg

Indications:

  • Gastritis
  • Flatulence
  • Heartburn associated with reflux esophagitis
  • Heartburn in pregnancy
  • Adjunct to the treatment of peptic ulcers

Dosage: 5-10 ml 3-4 times daily after meals


Mucosal Protective Drugs

Bismuth Subsalicylate

  • Has cytoprotective properties and is bactericidal against H. pylori. It promotes healing of peptic ulcers by forming a complex (bismuth/glycoprotein) that coats the base of the peptic ulcer.
  • It needs an acidic environment to work; hence, it should not be used in combination with antacids.

Available Preparations: Tablets (262 mg), Suspension

Available Brands: Pepto-Bismol®, Bismol®

Pharmacokinetics: Following oral administration, the drug is only slightly absorbed. Increased gastric pH may increase bismuth absorption. Unabsorbed drug is excreted in feces. The absorbed portion of the drug is distributed throughout body tissues and is slowly excreted in urine and bile.

Indications:

  • Peptic ulcer
  • Nausea
  • Diarrhea
  • Abdominal cramps
  • Indigestion
  • Prevention of traveler’s diarrhea

Contraindications:

  • Hypersensitivity to bismuth salts
  • Moderate to severe renal impairment
  • Children under 3 years

Dosage:

Adults: 30 ml or 2 tablets 4 times daily, 30 minutes before food

Children:

  • 9-12 years: 15 ml or 1 tablet 4 times daily
  • 6-9 years: 10 ml 4 times daily
  • 3-6 years: 5 ml 4 times daily

Side Effects:

  • Black stool
  • Discolors mucous membranes, tongue, and teeth
  • Constipation
  • Metallic taste
  • Skin reactions
  • Stomatitis

Drug Interactions:

  • Bismuth subsalicylate decreases the absorption of tetracyclines.
  • It increases the toxicity of aspirin due to the absorption of salicylate.
  • Advertisements

Key Issues to Note:

  • Chew or dissolve tablets in the mouth before swallowing.
  • Shake suspension before using.
  • Stop use if symptoms do not improve within 2 days.


Prostaglandin Analogues

Misoprostol

Available Preparations: Tablets (200 mcg)

Available Brands: Cytotec®

Mode of Action: Misoprostol helps to protect the stomach by suppressing secretion of gastric acid, promoting secretion of bicarbonate and cytoprotective mucus, and maintaining blood flow.

Indications:

  • Peptic ulcer disease
  • Prophylaxis of NSAID-induced ulcers
  • Induction of labor
  • Management of postpartum hemorrhage

Contraindications:

  • Pregnancy or those planning to become pregnant
  • Women in childbearing age
  • Breastfeeding
  • Patients allergic to prostaglandin derivatives
  • Inflammatory bowel disease

Dosage:

  • By mouth: 800 mcg daily in 2-4 divided doses with food for 4-8 weeks
  • Prophylaxis of NSAID-induced ulcers: 200 mcg 2-4 times daily taken with NSAID

Side Effects:

  • Diarrhea
  • Flatulence
  • Abdominal cramps
  • Dyspepsia
  • Dizziness
  • Nausea
  • Vomiting
  • Abnormal vaginal bleeding
  • Rashes

Drug Interactions:

  • Misoprostol diminishes the bioavailability of aspirin.
  • Magnesium antacids enhance diarrhea associated with misoprostol.
H2 Receptor Antagonists

H2 receptor antagonists reduce gastric acid secretion by blocking the action of histamine at the H2 receptor in the parietal cells of the stomach.

Examples:

  • Cimetidine
  • Famotidine
  • Nizatidine
  • Ranitidine

Ranitidine

Available Preparations: Tablets (150 mg, 300 mg), Injection (25 mg/ml, 2 ml)

Available Brands: Zantac®, Ranidenk®, Ranitin®, Rantac®, Aciloc®, R-Loc®

Pharmacokinetics: Ranitidine is readily absorbed from the gastrointestinal tract, widely distributed, metabolized in the liver, and excreted in urine.

Indications:

  • Peptic ulcer
  • Prophylaxis of NSAID-induced duodenal or gastric ulcer
  • Stress ulcer prophylaxis
  • Gastroesophageal reflux disease
  • Zollinger-Ellison syndrome
  • Dyspepsia

Contraindications:

  • Patients allergic to ranitidine
  • Children less than 8 years

Dosage:

Peptic ulcer:

  • Adults and children over 12 years: 150 mg twice daily or 300 mg at night for 4 to 8 weeks

Prophylaxis of NSAID-induced duodenal or gastric ulcer: 150 mg twice daily

Gastroesophageal reflux disease: 150 mg twice daily or 300 mg at night up to 8 weeks; moderate to severe cases: 150 mg every 6 hours daily for up to 12 weeks

Zollinger-Ellison syndrome: 150 mg 3 times daily

Stress ulcer prophylaxis: 150 mg twice daily until the risk factor is removed

Dyspepsia: 150 mg twice daily for 4-8 weeks

  • IV: 50 mg diluted to 20 ml with normal saline or dextrose 5% every 6-8 hours by slow injection over not less than 5 minutes
  • IV Infusion: 25 mg/hour for 2 hours may be repeated every 6-8 hours

Side Effects:

  • Skin rash
  • Visual disturbance
  • Gynecomastia
  • Headache
  • Diarrhea
  • Malaise
  • Tachycardia
  • Constipation
  • Hypersensitivity reaction
  • Myalgia

Drug Interactions:

  • Antacids may decrease the absorption of ranitidine.
  • Ranitidine may decrease the absorption of ketoconazole, cefpodoxime, cefuroxime.
  • Ranitidine may increase the hypoglycemic effects of glipizide.
  • Ranitidine may interfere with warfarin clearance.

Proton Pump Inhibitors

Proton pump inhibitors (PPIs) act by irreversibly binding to and inhibiting the enzyme H+/K+-ATPase (proton pump) of the gastric parietal cells, resulting in long-lasting but reversible acid suppression. PPIs inhibit gastric acid secretion more than H2 receptor antagonists.

Examples:

  • Omeprazole
  • Lansoprazole
  • Pantoprazole
  • Esomeprazole
  • Rabeprazole

Omeprazole

Available Preparations: Enteric-coated capsules/tablets (20 mg)

Available Brands: Gasec®, Omepren®, Omizac®, Ocid®, Belifax®

Pharmacokinetics: Omeprazole is rapidly but variably absorbed after oral administration. Absorption is not affected by food. It is almost completely metabolized in the liver, and 80% of the metabolites are excreted mainly in urine and the rest in feces.

Indications:

  • Peptic ulcers
  • Zollinger-Ellison syndrome
  • NSAID-associated duodenal or gastric ulcer
  • Gastric acid reduction during anesthesia
  • Gastroesophageal reflux disease
  • Acid-related dyspepsia

Contraindications:

  • Allergy to omeprazole or any other component in the capsule
  • Pregnancy
  • Lactation

Dosage:

  • Gastric ulcer or reflux esophagitis: 20-40 mg once daily for 4-8 weeks
  • Duodenal ulcer: 20 mg once daily for 4 weeks; continued for a further 4 weeks if not fully healed
  • NSAID-associated duodenal or gastric ulcer: 20 mg once daily for 4 weeks; continued for a further 4 weeks if not fully healed
  • Zollinger-Ellison syndrome: Initially 60 mg once daily, usual range 20-120 mg; doses over 80 mg given in 2 divided doses
  • Acid-related dyspepsia: 20 mg once daily for 2-4 weeks
  • Prophylaxis of acid aspiration: 40 mg on the evening before, then 40 mg 2-6 hours before surgery

Side Effects:

  • Headache
  • Nausea
  • Flatulence
  • Vomiting
  • Constipation
  • Skin rashes
  • Diarrhea
  • Abdominal pain
  • Dry mouth
  • Gynecomastia
  • Impotence

Drug Interactions:

  • Omeprazole increases the plasma concentration of diazepam, carbamazepine, digoxin, phenytoin
  • Omeprazole decreases the plasma concentration of itraconazole, ketoconazole, cefpodoxime, cefuroxime, iron salts, and cyanocobalamin
  • Omeprazole may increase the absorption and potential for hypoglycemia of glipizide, tolbutamide

Key Issues to Note:

  • Administer before food and the capsule should be swallowed whole without chewing
  • Capsules should be used within one month of opening the package
  • Possible malignancy must be excluded prior to starting treatment to avoid delay in diagnosis
  • Dosage reduction may be required in hepatic disease

Esomeprazole

Available Preparations: Tablets (20 mg, 40 mg)

Available Brands: Nexium®, S-prazo®, Nexpro®, Esoz®

Pharmacokinetics: Esomeprazole is rapidly absorbed following oral administration. It is extensively metabolized by the liver and excreted in urine and a small percentage in feces.

Indications:

  • Gastroesophageal reflux disease
  • Zollinger-Ellison syndrome
  • Peptic ulcer disease
  • Prevention of relapse of H. pylori-associated peptic ulcer
  • Prevention of gastric and duodenal ulcers associated with NSAID therapy

Contraindications:

  • Known hypersensitivity to benzimidazoles
  • Pregnancy

Dosage:

  • Peptic ulcer disease: Triple therapy regimen: 40 mg of esomeprazole once daily with amoxicillin 1 g twice daily and clarithromycin 500 mg twice daily for 7 days
  • Gastroesophageal reflux disease: 40 mg once daily for 4-8 weeks depending on the response; maintenance: 20 mg daily
  • Gastric ulcer associated with NSAID therapy: 20 mg once daily for 4-8 weeks

Side Effects:

  • Taste disturbances
  • Dizziness
  • Diarrhea
  • Nausea
  • Headache
  • Abdominal pain
  • Skin rash
  • Vomiting
  • Flatulence
  • Dry mouth

Drug Interactions:

  • Reduction in gastric acidity due to esomeprazole use may decrease the absorption of ketoconazole, itraconazole, digoxin, and iron

Key Issues to Note:

  • Food delays and decreases the absorption of esomeprazole; therefore, take it at least 1 hour before meals
  • The tablet should be swallowed whole; do not chew or crush
  • Advertisements

Lansoprazole

Available Preparations: Capsule (30 mg)

Available Brands: Lancid®, Lan-30®, Zolanas-30®

Pharmacokinetics: Lansoprazole is rapidly absorbed after oral administration, extensively metabolized in the liver, and metabolites are excreted primarily in feces via the bile.

Indications:

  • Peptic ulcers
  • Zollinger-Ellison syndrome
  • Gastroesophageal reflux disease
  • Acid-related dyspepsia
  • Prophylaxis of NSAID-associated duodenal and benign gastric ulcer

Contraindications:

  • Hypersensitivity to lansoprazole
  • Breastfeeding
  • Pregnancy

Dosage:

  • Benign gastric ulcer: 30 mg daily in the morning for 8 weeks
  • Duodenal ulcer: 30 mg daily in the morning for 4 weeks; maintenance: 15 mg daily
  • Zollinger-Ellison syndrome: Initially 60 mg once daily, adjusted according to response to a daily dose of 120 mg or more in two divided doses
  • Gastroesophageal reflux disease: 30 mg daily in the morning for 4-8 weeks; maintenance: 15-30 mg daily
  • Acid-related dyspepsia: 30 mg daily in the morning for 2-4 weeks

Side Effects:

  • Abdominal pain
  • Diarrhea or constipation
  • Fatigue
  • Nausea
  • Dizziness
  • Flatulence
  • Headache
  • Skin rash
  • Altered appetite
  • Impotence
  • Malaise
  • Vomiting

Drug Interactions:

  • Lansoprazole may interfere with the absorption of drugs where gastric pH is an important determinant of bioavailability such as ketoconazole, itraconazole, ampicillin, iron salts, digoxin
  • Antacids may reduce the absorption of lansoprazole when given at the same time
  • Lansoprazole may reduce the effect of oral contraceptives, phenytoin, carbamazepine, warfarin, and theophylline

Key Issues to Note:

  • Swallow capsule whole without crushing or chewing
  • For patients unable to swallow, open the capsule and pour the contents onto a teaspoon and swallow
  • Take the drug after meals


Drugs for Nausea and Vomiting

Common Terms Used

  • Nausea: A sensation often leading to the urge to vomit.
  • Vomiting (Emesis): The forceful expulsion of gastric contents through the mouth, occurring due to stimulation of the vomiting center situated in the medulla oblongata of the brain.
  • Vomiting Center: The area in the brain involved in stimulating the events that lead to nausea and vomiting.
  • Chemoreceptor Trigger Zone: The area in the brain involved with the sensation of nausea and vomiting.
  • Prokinetic Drug: Drugs that increase the activity of gastrointestinal smooth muscles.
  • Antiemetic Drug: A drug given to relieve nausea and vomiting.

Vomiting is not a disease but a symptom of an underlying disease or disorder of the gastrointestinal tract (GIT). Common causes of vomiting include:

  • Drugs such as opioid analgesics and digoxin
  • Gastrointestinal disease
  • Motion sickness
  • Vestibular disorders like migraine headache
  • Early pregnancy (morning sickness)
  • Psychological factors
  • Infectious diseases

Drugs used in the treatment of vomiting include:

  • Promethazine
  • Dimenhydrinate
  • Metoclopramide
  • Prochlorperazine
  • Cinnarizine
  • Meclozine
  • Chlorpromazine
  • Domperidone
  • Cyclizine
  • Granisetron
  • Haloperidol

Key Issues to Note

  • Identify and treat the cause if possible
  • Ensure adequate hydration
  • Antiemetics should be prescribed only when the cause of vomiting is known
  • Antiemetics are more effective when given prophylactically than when given to stop vomiting that has already started
  • They are unnecessary and sometimes harmful, especially when the cause can be treated

Promethazine

Available Preparations:

  • Tablets: 25 mg
  • Injection: 25 mg/ml, 2 ml
  • Syrup: 5 mg/5 ml

Available Brands: Intamine®, Prozin®, Phenergan®

Pharmacokinetics: Promethazine is well absorbed after oral or intramuscular administration, widely distributed, metabolized in the liver, and excreted in urine and bile.

Indications:

  • Nausea and vomiting
  • Urticaria and angioedema
  • Vertigo
  • Postoperative emesis
  • Motion sickness
  • Allergic rhinitis
  • Pruritus in eczema

Contraindications:

  • Known hypersensitivity to promethazine
  • Porphyria
  • Children under 2 years
  • Severe CNS depression or coma
  • Vomiting of unknown cause
  • Lactation
  • Concomitant therapy with MAOIs

Dosage:

Nausea and Vomiting:

  • Adult (Oral): 25 mg repeated every 4-6 hours, max 100 mg daily
  • Adult (IM): 12.5-25 mg every 6 hours as needed
  • Children (5-12 years): 6.25-12.5 mg
  • Children (12-16 years): 12.5-25 mg

Morning Sickness:

  • Adult: 25 mg at bedtime or 2 hours before traveling, repeated if needed up to 4 times daily
  • Children (5-10 years): 10 mg at bedtime and the following morning if necessary
  • Children (2-5 years): 5 mg at night and the following morning if necessary

Side Effects:

  • Drowsiness
  • Anorexia
  • Dry mouth
  • Constipation
  • Sedation
  • Disorientation
  • Urinary retention
  • Hypotension
  • Skin rashes
  • Dizziness
  • Headache
  • Fatigue
  • Epigastric pain

Drug Interactions:

  • Alcohol and other CNS depressants may increase CNS depressant effects of promethazine
  • Promethazine may block the anti-Parkinsonian action of levodopa
  • Additive anticholinergic effects with anticholinergic drugs

Key Issues to Note:

  • Inform the patient that promethazine may cause drowsiness and impair the ability to perform activities requiring mental alertness
  • Advise the patient to avoid prolonged exposure to sunlight since promethazine may cause photosensitivity reactions
  • Maintain fluid intake
  • Avoid alcohol intake

Chlorpromazine

Available Preparations:

  • Tablets: 25 mg, 100 mg
  • Injection: 100 mg/2 ml

Available Brands: Largactil®

Pharmacokinetics: Chlorpromazine is readily absorbed from the gastrointestinal tract, undergoes first-pass metabolism, and is distributed to the body tissues. It is extensively metabolized in the liver and excreted in the urine.

Indications:

  • Nausea and vomiting due to radiation therapy and chemotherapy
  • Acute and chronic schizophrenia
  • Acute mania, as in bipolar disorder
  • Anxiety disorders
  • Intractable hiccup
  • Severe behavioral disturbances in children
  • Nausea and vomiting of terminal illness

Contraindications:

  • Hypersensitivity to chlorpromazine
  • Comatose states
  • Severe CNS depression
  • Bone marrow depression
  • Parkinson’s disease
  • Liver damage
  • Cerebral or coronary arteriosclerosis

Dosage:

Schizophrenia, Mania, Severe Anxiety: Initially 25 mg 3 times daily or 75 mg at night, adjusted according to response. Maintenance dose: 75-300 mg daily

Intractable Hiccup: 25-50 mg 3-4 times daily

Severe Nausea and Vomiting: 10-25 mg 4 times daily

Children: 0.5-1 mg/kg 6 hourly

Deep Intramuscular Injection:

  • Adult: 25-50 mg every 4-6 hours until vomiting stops
  • Children (1-12 years): 0.5-1 mg/kg every 6-8 hours

Side Effects:

  • Drowsiness
  • Dry mouth
  • Slurred speech
  • Poor coordination
  • Hypotension
  • Blurred vision
  • Constipation
  • Urinary retention
  • Somnolence
  • Dizziness

Drug Interactions:

  • Chlorpromazine may reduce the effect of drugs for Parkinsonism
  • Alcohol and other CNS depressants may increase respiratory depression and hypotensive effects of chlorpromazine
  • Lithium may decrease the absorption of chlorpromazine and produce adverse neurologic effects
  • Concurrent use with antihypertensives may result in additive hypotensive effects
  • Advertisements

Key Issues to Note:

  • Administer chlorpromazine with water, food, or milk to decrease GI upset
  • Inform the patient that chlorpromazine may cause drowsiness and impair the ability to perform activities requiring mental alertness

Metoclopramide

Available Preparations:

  • Tablets: 10 mg
  • Injection: 5 mg/ml, 2 ml ampoule

Available Brands: Plasil®, Reglan®, Camet®

Pharmacokinetics: Metoclopramide is rapidly and almost completely absorbed from the gastrointestinal tract following oral administration, undergoes hepatic first-pass metabolism, and is widely distributed in the body. It is excreted in feces via the bile.

Indications:

Disorders of decreased gastrointestinal motility such as:

  • Dyspepsia
  • Gastroesophageal reflux disease
  • Diabetic gastroparesis
  • Stimulation of lactation

Nausea and vomiting due to:

  • Migraine
  • Following gastric surgery
  • Cancer therapy or radiotherapy

Contraindications:

  • Gastrointestinal obstruction
  • Intestinal perforation
  • 3-4 days after gastrointestinal surgery
  • History of seizure disorders
  • Pheochromocytoma

Dosage:

Nausea and Vomiting:

  • Adult and Children (over 60 kg): 10 mg 3 times daily
  • Children (9-18 years): 5 mg 3 times daily
  • Children (5-9 years): 2.5 mg 3 times daily
  • Children (3-5 years): 2 mg 2-3 times daily
  • Children (1-3 years): 1 mg 2-3 times daily
  • Neonate: 100 mcg/kg every 6-8 hours

Stimulation of Lactation: 10 mg 3 times daily, reduce dose gradually over 7-10 days before stopping

Cancer Chemotherapy: Initial dose of up to 2 mg/kg by intravenous infusion over at least 15 minutes may be given in combination with dexamethasone before cancer therapy and repeated every 2 or 3 hours

Side Effects:

  • Hyperprolactinemia
  • Drowsiness
  • Tardive dyskinesia
  • Diarrhea
  • Edema
  • Skin rash
  • Hypotension
  • Depression
  • Dizziness
  • Pruritus
  • Headache
  • Restlessness
  • Parkinsonism

Drug Interactions:

  • Metoclopramide reduces the absorption of oral digoxin
  • Metoclopramide increases the absorption of aspirin, paracetamol, and diazepam

Key Issues to Note:

  • May cause drowsiness; therefore, warn the patient not to drive or operate machinery that requires mental alertness
  • Advise the patient to take the drug 30 minutes before meals and at bedtime

Drugs for Hemorrhoids and Piles

Hemorrhoids (Piles)

Hemorrhoids are clusters of venous swellings of the tissues around the anus caused by straining during bowel movements. They are associated with constipation, diarrhea, and prolonged straining. Hemorrhoids may be divided into two:

  • Internal hemorrhoids
  • External hemorrhoids

Most preparations for hemorrhoids contain any of the following:

  • Astringents (e.g., bismuth subgallate, zinc oxide, resorcinol)
  • Local anesthetics (e.g., lignocaine, cinchocaine)
  • Corticosteroids (e.g., hydrocortisone)
  • Lubricants
  • Vasoconstrictors
  • Antiseptics

Key Issues to Note:

  • Creams or ointments are used for external hemorrhoids
  • Suppositories are preferred for internal hemorrhoids
  • Hemorrhoids developing during pregnancy should be managed conservatively as most will resolve after delivery
  • Local anesthetics are used to relieve pain associated with hemorrhoids
  • Corticosteroids are used to reduce inflammation where infection is not present
  • In case of infection, metronidazole 400 mg 8 hourly for 5 days is used
  • Surgery may be required in resistant cases

Commonly Used Compound Preparations:

  • Anusol ointment/suppository
  • Preparation-H ointment
  • Scheriproct ointment/suppository
  • Sediproct ointment/suppository
  • Pylocaine ointment

Anusol

Available Preparations:

  • Ointment
  • Suppository

Composition:

  • Bismuth subgallate 59 mg
  • Bismuth oxide 24 mg
  • Zinc oxide 296 mg

Indications:

  • Soothe the pain and irritation of hemorrhoids

Contraindications:

  • Serious rectal pathology

Dosage:

  • Suppository: Insert 1 suppository at night and morning
  • Ointment: Apply twice daily, at night and morning

Side Effects:

Hypersensitivity reactions such as:

  • Redness
  • Irritation
  • Swelling

Sediproct

Available Preparations:

  • Cream
  • Suppository

Composition:

  • Hydrocortisone 500 mg
  • Cinchocaine 500 mg

Indications:

  • Hemorrhoids associated with inflammation
  • Anal fissures
  • Anal pruritus
  • Proctitis

Contraindications:

  • Hypersensitivity to any of the active ingredients

Dosage:

  • Cream: Apply the cream into the rectum twice daily, at night and morning after bowel movement
  • Suppository: Insert 1 suppository twice daily, at night and morning

Side Effects:

  • Local irritation
  • Skin rash

Scheriproct

Available Preparations:

  • Suppository
  • Ointment

Composition:

  • Cinchocaine 0.5%
  • Prednisolone 0.19%

Indications:

  • Hemorrhoids

Contraindications:

  • Known hypersensitivity to the active ingredients

Dosage:

  • Ointment: Apply twice daily for 5-7 days, then once daily for a few days after symptoms have cleared
  • Suppository: Insert 1 suppository daily after a bowel movement for 5-7 days (in severe cases, initially apply 2-3 times daily)

Side Effects:

  • Local irritation
  • Skin rash

Drugs for Inflammatory Bowel Disease

Inflammatory bowel disease is a chronic non-specific inflammatory condition of the gastrointestinal tract. 

It is divided into two:

  • Crohn’s disease (affects the gut from mouth to anus)
  • Ulcerative colitis (affects only the large bowel)

Both ulcerative colitis and Crohn’s disease frequently run a course characterized by exacerbations and remissions, tend to be chronic in nature, have similar extra-intestinal manifestations, and may be associated with a positive family history of inflammatory bowel disease. 

Drugs used in the treatment of inflammatory bowel disease either control symptoms or modify the disease by inducing and maintaining long-term bowel healing.

Examples:

  • Aminosalicylates
  • Corticosteroids

Aminosalicylates

This group of drugs includes:

  • Sulfasalazine
  • Mesalazine

Aminosalicylates treat mild to moderate inflammatory bowel disease and are equally effective. The choice is based on the location of the disease and the side effect profile of the individual drugs.

Sulfasalazine

Available Preparation: Tablets: 500 mg

Available Brands: Salazopyrin®

Indications:

  • Active ulcerative colitis
  • Severe rheumatoid arthritis
  • Active Crohn’s disease

Contraindications:

  • Children less than 2 years
  • Pregnancy at term and lactation
  • Severe hepatic impairment
  • Severe renal dysfunction
  • Salicylate and sulfonamide hypersensitivity

Dosage:

Acute Attack:

  • Adult: 1-2 g 4 times daily until remission occurs (3 weeks), reduced to a maintenance dose of 500 mg 4 times daily
  • Children over 2 years:
  • Acute attack: 10-15 mg/kg 4-6 times daily until remission occurs
  • Maintenance: 30 mg/kg/day in 4 divided doses

Rheumatoid Arthritis:

  • Adult: 500-1000 mg/day for 1 week, increased by 0.5 g/week up to 3 g/day
  • Advertisements

Side Effects:

  • Anorexia
  • Vomiting
  • Fever
  • Skin rash
  • Abdominal discomfort
  • Nausea
  • Headache
  • Folate deficiency
  • Reversible male infertility

Drug Interactions:

  • Sulfasalazine may increase the effect of anticonvulsants, methotrexate, oral anticoagulants, and oral antidiabetics
  • Sulfasalazine may decrease the absorption of digoxin

Key Issues to Note:

  • Administer the drug with food to reduce stomach upset
  • Do not administer the drug with antacids
  • Sulfasalazine impairs the absorption of folic acid; therefore, folic acid supplements may be necessary during treatment

Corticosteroids

Corticosteroids are used for the treatment of both ulcerative colitis and Crohn’s disease. They are often able to induce the remission of ulcerative colitis but have proved less valuable in maintaining remission.

Drugs for Constipation (Laxatives)

Constipation is a reduced frequency of defecation characterized by hardening of the stool, straining on defecation, or a feeling of incomplete evacuation. 

It may be caused by any of the following:

  • Lack of fluid or fiber intake
  • Lack of exercise
  • Pregnancy
  • Drugs like aluminum-containing antacids, codeine, or iron
  • Irritable bowel syndrome
  • Anorectal conditions like hemorrhoids
  • Psychiatric and neurological disorders

Laxatives are drugs that stimulate defecation by forming bulk, stimulating peristalsis, or providing lubrication. 

They increase the frequency of bowel evacuation or the passage of softer or bulkier stool. Laxatives are used in the treatment of constipation and for bowel evacuation before investigational procedures, such as endoscopy, radiological examination, or before surgery.

Classification of Laxatives

Laxatives are classified according to their mode of action as follows:

  • Bulk-forming laxatives
  • Saline laxatives
  • Lubricant laxatives
  • Stimulant laxatives
  • Osmotic laxatives
Bulk-Forming Laxatives

Mode of Action: Bulk-forming laxatives relieve constipation by absorbing water, thereby increasing fecal bulk, which stimulates peristalsis. They are useful for mild constipation, small hard stools, patients with hemorrhoids, fissures, and irritable bowel disease, and as adjuncts in ulcerative colitis. Adequate fluid intake is important to lubricate the colon and minimize the risk of intestinal obstruction.

Examples:

  • Methylcellulose
  • Wheat bran
  • Ispaghula husk

Ispaghula Husk

Available Preparations:

  • Granules: 3.5 g sachet

Available Brands: Fybogel®

Indications:

  • Constipation, especially in diverticular disease and irritable bowel syndrome
  • Constipation following anorectal surgery, hemorrhoids, pregnancy
  • Management of diarrhea
  • Adjusting fecal consistency in patients with colostomies

Contraindications:

  • Difficulty in swallowing
  • Intestinal obstruction
  • Colonic atony
  • Fecal impaction
  • Hypersensitivity to any of the ingredients

Dosage:

  • Adult: 1 sachet or 2 level 5 ml spoonfuls in water given morning and evening after meals
  • Children (6-12 years): 1/2 – 1 level 5 ml spoonful in water twice daily
  • Children (below 6 years): Give on doctor’s advice only

Side Effects:

  • Flatulence and abdominal distension during the first few days of treatment
  • Gastrointestinal obstruction or impaction
  • Hypersensitivity reaction
Osmotic Laxatives

Mode of Action: Osmotic laxatives are poorly absorbed; therefore, the unabsorbed solute in the intestine draws water from the body into the bowel by osmosis, causing bowel distention, which in turn increases peristalsis. These drugs are used for acute and rapid evacuation of the bowel, except for lactulose.

Examples:

  • Lactulose
  • Magnesium salts

Lactulose

Available Preparations: Syrup: 3.350 g/5 ml

Available Brands: Laxolac®, Duphalac®, Sedalac®

Indications:

  • Constipation
  • Hepatic encephalopathy

Contraindications:

  • Intestinal obstruction
  • Known hypersensitivity to lactulose
  • Galactosemia

Dosage:

Constipation:

  • Adults: 15 ml twice daily
  • Children (6-12 years): 10 ml twice daily, adjusted according to response
  • Children (1-5 years): 5 ml twice daily, adjusted according to response
  • Children (less than 1 year): 2.5 ml twice daily, adjusted according to response

Hepatic Encephalopathy: 30-45 ml 3 times daily, adjust dose to produce 2-3 soft stools per day

Side Effects:

  • Flatulence
  • Cramps
  • Diarrhea
  • Nausea
  • Abdominal discomfort
  • Vomiting if excess doses are given

Key Issues to Note:

  • Administer the drug with juice, milk, or water to increase palatability
  • Do not take other laxatives while on lactulose therapy
Lubricants and Fecal Softeners

Mode of Action: They promote stool passage by coating the fecal surface with an oil layer that retains fecal fluid and prevents absorption of fecal water by the colon.

Examples:

  • Glycerol
  • Docusate sodium
  • Liquid paraffin
  • Mineral oil

Glycerol

Available Preparations:

  • Suppositories: 4 g

Indications:

  • Constipation

Contraindications:

  • Patients with known hypersensitivity to glycerin
  • Glycerin suppositories are contraindicated in patients who are recovering from rectal surgery

Dosage:

By rectum:

  • Adults: 4 g suppository moistened with water before use, once daily when required
  • Children (1-12 years): 2 g suppositories as required
  • Children (1 month – 1 year): 1 g suppository once daily when required

Side Effects:

  • Rectal discomfort
  • Diarrhea
  • Rectal mucosal erosion
  • Dizziness
  • Mild headache
  • Nausea
  • Mild hyperglycemia
  • Vomiting

Drug Interactions:

  • Concomitant use with diuretics may result in an additive effect

Key Issues to Note:

  • Onset of action is 5-30 minutes
  • Do not use longer than 1 week
  • Prolonged or frequent use may result in dependency
Stimulant Laxatives

Mode of Action: Stimulant laxatives increase peristalsis by directly stimulating nerve endings in the colonic mucosa, thereby increasing intestinal motility. They are useful for more severe forms of constipation, but tolerance is common with regular use, and they can produce abdominal cramps.

Examples:

  • Bisacodyl
  • Senna
  • Castor oil

Bisacodyl

Available Preparations:

  • Tablets: 5 mg
  • Suppository: 10 mg

Available Brands: Dulcolax®

Pharmacokinetics: Absorption of bisacodyl after oral administration is minimal; the absorbed drug is metabolized in the liver and excreted in urine, feces, and breast milk.

Indications:

  • Constipation
  • Bowel evacuation before investigational procedures or surgery

Contraindications:

  • Intestinal obstruction
  • Appendicitis
  • Severe dehydration
  • Acute inflammatory bowel disease
  • Hypersensitivity to the drug

Dosage:

Constipation:

  • Adults: 5-10 mg daily administered at night or 10 mg as a suppository or enema administered in the morning
  • Children (10-18 years): 5-10 mg at night, increased if necessary to max. 20 mg
  • Children (5-10 years): 5 mg at night
  • Children (2-5 years): 5 mg in the morning (rectally)

Complete Bowel Evacuation:

  • Adult: 10-20 mg followed by 10 mg as a suppository the next morning
  • Children (4-10 years): 5 mg at bedtime for 2 days before the procedure, increased if necessary by suppository 10 mg 1 hour before the procedure
  • Advertisements

Side Effects:

  • Nausea
  • Vomiting
  • Diarrhea
  • Faintness
  • Mild cramps
  • Abdominal discomfort
  • Suppositories may cause irritation and proctitis

Drug Interactions:

  • Antacids, cimetidine, famotidine, ranitidine, milk, and other drugs that increase gastric pH level may cause premature dissolution of the enteric coating of bisacodyl, resulting in abdominal cramping

Key Issues to Note:

  • Patients should swallow tablets whole with a glass of water
  • Do not administer bisacodyl within 1 hour of ingesting antacids, milk, or dairy products
  • Bisacodyl is habit-forming; therefore, long-term use may result in laxative dependency and loss of normal bowel function
  • Onset of action is 6-12 hours for tablets, 15-60 minutes for suppository
  • Warn the patient that prolonged use of bisacodyl suppositories may cause proctitis

Antidiarrheal Drugs

Diarrhea is the frequent passage of watery stools at least 3 times or more in a day. It affects all age groups and is more severe and life-threatening in children and immunocompromised patients. Diarrhea may be caused by any of the following:

  • Infections
  • Inflammation
  • Drugs such as antacids
  • Malabsorption

Drugs used in the treatment of diarrhea include:

  • Adsorbents
  • Antimotility drugs
  • Antisecretory compounds
  • Antimicrobials
  • Intestinal microflora

Adsorbent Drugs

Examples:

  • Kaolin
  • Pectin
  • Activated charcoal

Adsorbent drugs act by absorbing the toxins produced by pathogens, thereby reducing GIT motility. These drugs are used for symptomatic relief of diarrhea. They are not recommended for infectious acute diarrhea and when the patient is taking other drugs (prevent absorption of other drugs).

Antisecretory Drugs

Examples:

  • Bismuth subsalicylate

Bismuth subsalicylate appears to produce its antidiarrheal effect by inhibiting intestinal secretions. It is recommended in the treatment of infectious diarrhea such as traveler’s diarrhea. It is available in the form of tablets and suspension.

Intestinal Microflora

Example: Lactobacillus

These drugs are intended to replace colonic microflora, which restores intestinal function and suppresses the growth of pathogenic microorganisms.

Antimotility Drugs

Examples:

  • Loperamide
  • Codeine
  • Diphenoxylate

Antimotility drugs act by reducing GIT motility, thereby allowing enough time for fluid absorption from gut contents. They are recommended in the treatment of acute and chronic diarrhea in combination with fluid replacement. They are not recommended in children less than 2 years and infectious diarrhea.

Loperamide

Available Preparations:

  • Capsules: 2 mg
  • Tablets: 2 mg

Available Brands: Imodium®, Loperium®, Loperax®, Kamodium®, Gallop®

Pharmacokinetics: About 40% of loperamide is absorbed from the gastrointestinal tract, undergoes first-pass metabolism in the liver, and is excreted in the feces as unchanged drug and a small amount in urine.

Indications:

  • Acute diarrhea
  • Chronic diarrhea
  • Traveler’s diarrhea

Contraindications:

  • Known hypersensitivity to loperamide
  • Infants below 2 years of age
  • Abdominal distension
  • Acute inflammatory bowel disease
  • Antibiotic-associated colitis
  • Patients who must avoid constipation

Dosage:

Acute Diarrhea:

  • Adult: 4 mg start followed by 2 mg after each loose stool until diarrhea is relieved. Max dose 16 mg daily
  • Children (9-12 years): 2 mg 4 times daily up to 5 days
  • Children (4-8 years): 1 mg 3-4 times daily for up to 3 days only

Chronic Diarrhea:

  • Adult: 4-8 mg daily in 2 divided doses

Side Effects:

  • Flatulence
  • Blurred vision
  • Drowsiness
  • Headache
  • Fatigue
  • Constipation
  • Dry mouth
  • Hypersensitivity reaction
  • Abdominal cramps
  • Dizziness
  • Nausea and vomiting
  • Abdominal bloating
  • Urticaria
  • Toxic megacolon
  • Paralytic ileus

Drug Interactions:

  • Concomitant use of loperamide with opioid analgesics may cause severe constipation

Key Issues to Note:

  • Advise the patient to drink plenty of fluids to prevent dehydration
  • Do not exceed the maximum daily dosage
  • Loperamide may impair the ability to perform activities requiring mental alertness
  • Advise the patient to avoid the use of alcohol during treatment
  • Loperamide should not be used alone in patients with dysentery

Codeine

Available Preparations:

  • Tablets: 30 mg

Pharmacokinetics: Codeine is absorbed from the gastrointestinal tract, metabolized in the liver to morphine and other metabolites, and excreted in urine.

Indications:

  • Diarrhea
  • Pain
  • Cough suppression (lower dosage)

Contraindications:

  • Hypersensitivity to codeine
  • Premature infants
  • Conditions where inhibition of peristalsis should be avoided such as abdominal distension, ulcerative colitis, acute respiratory depression

Dosage:

  • Adults: 30-60 mg 3-4 times daily
  • Children: Not recommended

Side Effects:

  • Headache
  • Constipation
  • Anorexia
  • Abdominal pain
  • Dizziness
  • Hypotension
  • Sedation
  • Dry mouth
  • Nausea and vomiting
  • Respiratory depression
  • Somnolence
  • Decreased urination

Drug Interactions:

  • Alcohol, narcotic analgesics, hypnotics, and tricyclic antidepressants may increase CNS or respiratory depression

Key Issues to Note:

  • Administer codeine with water or food to decrease nausea and GI upset
  • Avoid long-term use because of addictive potential
  • Codeine may cause drowsiness; therefore, do not drive or operate machinery

Prokinetic Drugs

Prokinetic drugs enhance the tone and motility of the gastrointestinal tract. Examples include metoclopramide, domperidone, and cisapride. These drugs are used to treat gastroesophageal reflux disease (GERD), chemotherapy-induced nausea and vomiting, and diabetic gastroparesis. Metoclopramide, specifically, is used to suppress nausea and vomiting caused by anticancer drugs (e.g., cisplatin, dacarbazine), postoperative vomiting, radiation therapy-induced emesis, toxins, and opioids. It also treats diabetic gastroparesis and GERD.

Drugs for Obesity

Obesity is linked to numerous health problems, including diabetes mellitus, hypertension, and hyperlipidemia. Increased abdominal fat and waist circumference further elevate health risks.

Orlistat

Available preparations: 120mg capsules (brand name: Xenical®)

Mode of action: Inhibits lipases in the stomach and small intestine, preventing dietary fat absorption.

Indications: Obesity in adults with a body mass index (BMI) > 30, or > 27 with additional risk factors like hypertension or diabetes.

Contraindications: Chronic malabsorption syndrome, breastfeeding, cholestasis.

Dosage: Adults and children over 12 years: 120mg three times daily with each meal.

Side effects: Flatulence, fecal incontinence, headache, anxiety.

Drug interactions: Orlistat may reduce the absorption of fat-soluble vitamins. Supplementation with fat-soluble vitamins (including vitamin D and beta-carotene) may be necessary.

Key note: If a meal is fat-free, the dose can be omitted.

Medicines Acting on Specific Body Systems Read More »

Terminologies and Sources of Drugs

Terminologies and Sources of Drugs

Terminologies and Sources of Drugs

TERMINOLOGIES

Pharmacology: The scientific study of drugs, their origins, chemical properties, actions, and uses in the treatment, diagnosis, and prevention of disease. 

  • Pharmacology is the scientific study of drugs and their use in medicine.
  • This includes pharmacokinetics (what the body does to the drug) and pharmacodynamics (what the drug does to the body). 
  • In midwifery, pharmacology focuses on medications used during pregnancy, labor, delivery, and the postpartum period, considering the impact on both the mother and the fetus/newborn.
  • The study of pharmacology helps a midwife to use the drugs appropriately while caring for the pregnant mother.
  • Pharmacology is divided into two major branches namely;
  • Pharmacokinetics and Pharmacodynamics.

Pharmacokinetics: The study of the movement of drugs within the body, including absorption, distribution, metabolism, and excretion (ADME). Understanding pharmacokinetics is vital in midwifery to determine appropriate dosage and timing of medications, considering changes in maternal physiology during pregnancy and lactation.

Pharmacodynamics: The study of the biochemical and physiological effects of drugs and their mechanisms of action. This includes drug receptor interactions and the relationship between drug concentration and effect. In midwifery, pharmacodynamics helps predict a drug’s efficacy and potential side effects in pregnant and breastfeeding women.

Drug: A substance intended for use in the diagnosis, cure, mitigation, treatment, or prevention of disease in humans or other animals. 

  • A drug is a chemical substance which alters the functioning of the body.
  • Most drugs used in clinical practice are used to prevent, diagnose and treat diseases.
  • A drug can have more than two names : chemical name, generic name and a brand name.
  • The chemical names are normally used by chemists and are not used in
  • clinical practice because they are usually very difficult to remember and write.
  • This is a name given to a drug by an international body. Generic name of a drug is known worldwide. The Ministry of Health of Uganda recommends that all drug prescriptions should be written with generic names to avoid confusion. Examples include Oxytocin, Misoprostol.
  • A brand name also called a trade name is a name given to a drug by a manufacturing company.
  • All brand names begin with a capital letter and bear a symbol *. Example Amoxil*, Duramox*, Unixil*.

Medication: A drug administered for therapeutic purposes. This highlights the intentional use of a drug to achieve a specific clinical outcome.

Therapeutics: The branch of medicine concerned with the treatment of disease and the use of drugs in the prevention and treatment of disease. 

  • In midwifery, therapeutic interventions include pain management, infection control, and management of obstetrical complications.

Toxicology: The study of poisons and the adverse effects of drugs and other chemicals on living organisms. 

  • In midwifery, toxicology is important for understanding the potential risks of medications to the mother and fetus, including teratogenicity (the ability to cause birth defects) and fetotoxicity (harm to the fetus).

Chemotherapy: The use of chemical agents (drugs) to treat diseases. 

  • In the context of midwifery, this might include the treatment of infections (e.g., with antibiotics) or the management of certain cancers. Specific consideration needs to be given to the potential effects on breastfeeding.

Teratogen: An agent that can cause birth defects. Many drugs are potential teratogens, and careful consideration is needed when prescribing medications during pregnancy.

Sources of Drugs

Drugs, substances used to prevent, diagnose, treat, or cure diseases, originate from different sources. These sources can be broadly categorized as natural or synthetic.

1. Natural Sources: These sources utilize naturally occurring substances extracted or purified from living organisms or minerals.

  • Plants: A rich source of medicinal compounds, plants have been used for centuries in traditional medicine. Many modern drugs are derived from or inspired by plant-based compounds. Examples include:
  1. Atropine: An anticholinergic alkaloid derived from plants like Atropa belladonna (deadly nightshade) used to treat certain types of poisoning and slow heart rate.
  2. Morphine: An opiate alkaloid extracted from the opium poppy (Papaver somniferum), a potent analgesic used to manage severe pain.
  3. Quinine: An antimalarial alkaloid obtained from the bark of the cinchona tree (Cinchona species).
  4. Digoxin: A cardiac glycoside extracted from the foxglove plant (Digitalis purpurea), used to treat heart failure and arrhythmias.
  5. Pilocarpine: A cholinergic alkaloid from Pilocarpus species, used to treat glaucoma and dry mouth.
  6. Physostigmine: A cholinesterase inhibitor from the Calabar bean (Physostigma venenosum), used to treat myasthenia gravis.
  • Animals: Certain animal tissues and secretions yield valuable medicinal compounds. Examples include:
  1. Insulin: A hormone crucial for glucose metabolism, originally extracted from the pancreas of pigs and cattle, now primarily produced via recombinant DNA technology.
  2. Adrenaline (Epinephrine): A hormone and neurotransmitter vital in the ”fight-or-flight” response, originally extracted from adrenal glands, now synthesized.
  3. Heparin: An anticoagulant extracted from animal tissues (e.g., pig intestines, cattle lungs), now also produced synthetically.
  4. Gonadotropins: Hormones regulating reproductive function, originally extracted from animal pituitary glands or pregnant women’s urine, now often produced via recombinant DNA technology.
  5. Antitoxic Sera: Preparations containing antibodies obtained from animals immunized against specific toxins.
  6. Advertisements

  • Minerals: Inorganic substances from the earth have also found therapeutic applications. Examples include:
  1. Magnesium Sulfate: Used as a laxative, anticonvulsant, and in other applications.
  2. Aluminum Hydroxide: An antacid used to neutralize stomach acid.
  3. Iron Salts: Used to treat iron deficiency anemia.
  4. Sulfur: Used in various topical treatments.
  5. Radioactive Isotopes: Used in nuclear medicine for diagnostic and therapeutic purposes (e.g., iodine-131 for thyroid cancer).
  • Microorganisms: Bacteria and fungi are sources of several crucial antibiotics:
  1. Penicillin: A beta-lactam antibiotic produced by Penicillium fungi.
  2. Cephalosporins: A class of beta-lactam antibiotics derived from Cephalosporium fungi.
  3. Tetracyclines: A broad-spectrum antibiotic class obtained from Streptomyces bacteria.
  • Humans: Certain human-derived substances have therapeutic applications:
  1. Immunoglobulins: Antibodies obtained from human blood plasma, used to provide passive immunity.
  2. Growth Hormone: A hormone regulating growth and development, originally extracted from human pituitary glands, now produced via recombinant DNA technology.
  3. Chorionic Gonadotropin: A hormone produced during pregnancy, originally extracted from pregnant women’s urine, now often produced synthetically.

2. Synthetic Sources: The majority of modern drugs are now produced synthetically, offering advantages such as precise control over purity, consistent quality, and scalability. These are chemically synthesized in laboratories, often mimicking or improving upon naturally occurring compounds. Examples include:

  • Quinolones: A class of broad-spectrum antibiotics.
  • Omeprazole: A proton pump inhibitor used to reduce stomach acid production.
  • Sulfonamides: (Sulfa drugs): A class of antibiotics.
  • Pancuronium: A neuromuscular blocking agent.
  • Neostigmine: A cholinesterase inhibitor.

Sources and Examples of Drugs

Source

Example Drug(s)

Plants

Atropine, Morphine, Quinine, Digoxin, Pilocarpine, Physostigmine

Animals

Insulin, Adrenaline, Heparin

Minerals

Magnesium Sulphate, Aluminum Hydroxide

Microorganisms

Penicillin, Cephalosporins, Tetracyclines

Humans

Immunoglobulins, Growth Hormone

Synthetic

Quinolones, Omeprazole, Sulfonamides


the-chief-aspects-of-pharmacology-n


Pharmacokinetics

Pharmacokinetics involves the study of how drugs move through the body, focusing on four key processes: absorption, distribution, metabolism, and excretion. In brief, it is what the body does to the drug.

Absorption

Absorption refers to how a drug enters the bloodstream from its site of administration.

Factor Influencing Absorption

Description

Impact

Route of administration

Method by which the drug is given (e.g., oral, IV)

Affects speed and efficiency of absorption

Surface area

Area available for drug absorption (e.g., intestines have a large surface area)

Larger surface areas increase absorption rate

Blood flow

Circulation at the absorption site

Higher blood flow enhances absorption

Presence of food

Interaction of food with the drug in the GI tract

Can either enhance or delay absorption

Drug formulation

Physical form of the drug (e.g., tablet, liquid)

Different forms have different absorption rates

Distribution

Distribution is how the drug is transported from the bloodstream to various tissues and organs.

Factor Influencing Distribution

Description

Impact

Protein binding

Degree to which a drug binds to plasma proteins

Only unbound drugs are active

Lipid solubility

Ability to dissolve in fats

Lipophilic drugs easily cross cell membranes

Blood circulation

Blood flow to different tissues

Organs with high blood flow receive drugs faster

Blood-brain barrier

A selective barrier protecting the brain

Only certain drugs can cross into the CNS

Bioavailability

Bioavailability is the proportion of a drug that reaches the systemic circulation and is available for therapeutic effect.

Route

Bioavailability

Notes

Intravenous (IV)

100%

Directly enters the bloodstream

Oral (PO)

Varies (20-80%)

Affected by first-pass metabolism and GI absorption

Subcutaneous (SC)

Moderate

Slower, sustained release into the bloodstream

Metabolism

Metabolism involves the biochemical alteration of a drug, primarily in the liver, into an inactive or less active form.

Factor Influencing Metabolism

Description

Impact

Age

Metabolic capacity varies with age

Neonates and elderly often metabolize drugs more slowly

Enzyme activity

Presence of drug-metabolizing enzymes

Advertisements

Drugs can induce or inhibit enzyme activity, affecting metabolism

Genetic factors

Individual genetic makeup

Variations can lead to differences in drug metabolism

Disease states

Conditions affecting organs

Liver diseases can impair metabolism, leading to drug accumulation

Excretion

Excretion is the removal of drugs or their metabolites from the body, mainly via the kidneys.

Route

Description

Examples

Renal (urine)

Primary route via kidneys

Most drugs and metabolites

Biliary (feces)

Excretion via bile into the intestines

Some drugs are excreted unchanged

Pulmonary (breath)

Exhalation of volatile drugs

Inhaled anesthetics

Others (sweat, saliva, breast milk)

Minor routes

Depends on drug properties

Pharmacodynamics

Pharmacodynamics involves the study of the effects of drugs on the body, including mechanisms of action, dose-response relationships, and therapeutic outcomes.

Term

Definition

Examples

Mechanism of Action

How a drug produces its effects

Inhibition of enzymes, receptor binding

Dose-Response Relationship

Relationship between dose and effect

Higher doses generally lead to greater effects

Therapeutic Index

Ratio of toxic dose to therapeutic dose

A higher index indicates a safer drug

Side Effects

Unintended drug effects at therapeutic doses

Nausea, drowsiness

Toxicity

Harmful effects from excessive dosing

Overdose leading to organ damage

Adverse Drug Reactions (ADRs)

Harmful reactions to normal doses

Allergic reactions, anaphylaxis

Application of Pharmacology to Midwifery Nursing and Patient Education

Pharmacological knowledge is important for safe and effective patient care and education. The nursing process provides a framework for applying this knowledge.

Pre-administration Assessment

The pre-administration assessment aims to:

1. Establish Goals:

  • Collect baseline data to evaluate both therapeutic and adverse responses. This requires understanding the medication’s intended effects and potential side effects.
  • Identify high-risk patients based on factors like age, renal/hepatic function, genetic predispositions, allergies, pregnancy, and concurrent medications.
  • Assess the patient’s capacity for self-care, including understanding, dexterity(ability to use hands), and cognitive abilities.

2. Collecting Baseline Data: Gathering data (vital signs, lab results, symptom assessment) before medication administration establishes a benchmark to measure therapeutic effectiveness and detect adverse effects.

3. Identifying High-Risk Patients: This involves recognizing predisposing factors such as:

  • Pathophysiology: Compromised liver or kidney function significantly impacts drug metabolism and excretion.
  • Genetic Factors: Genetic polymorphisms can alter drug metabolism and response.
  • Drug Allergies: A history of allergic reactions necessitates careful medication selection.
  • Pregnancy: Pregnancy alters physiology, impacting drug absorption, distribution, metabolism, and excretion. Fetal safety must be prioritized.
  • Age: Both very young and older adults often require dosage adjustments due to differences in organ function.
  • Comorbidities and Concurrent Medications: Interactions between multiple medications or underlying health conditions significantly impact drug response.

4. Tools for identification include patient history, physical examination, and laboratory tests. Knowledge of potential drug interactions is crucial.

Implementing the Medication Order

A. Making PRN Decisions: A PRN (pro re nata, ”as needed”) order requires the nurse to exercise clinical judgement regarding the timing and dosage based on the patient’s needs and assessment. The rationale for medication use must be clearly understood.

B. Managing Toxicity: Early recognition and management of drug toxicity are very key. Nurses must be familiar with the early signs of toxicity for each medication and the appropriate intervention protocols.

Application of Pharmacology in Patient Education

Patient education is paramount for safe and effective drug therapy. Essential information includes:

  • Drug Name and Therapeutic Category: Include both generic and trade names.
  • Dosage Size and Schedule: Clear instructions on how much to take and when.
  • Route and Technique of Administration: Detailed instructions on how to administer the medication (oral, injection, topical, etc.).
  • Duration of Treatment: Specify the length of therapy.
  • Method of Drug Storage: Instructions on proper storage to maintain drug efficacy and safety (e.g., refrigeration, protection from light).
  • Expected Therapeutic Response and Onset: Explain the expected benefits and when they should appear.
  • Non-drug Measures: Discuss complementary therapies or lifestyle modifications that can enhance treatment.
  • Symptoms of Major Adverse Effects: Educate patients on recognizing and reporting adverse effects. Include strategies for minimizing discomfort or harm.
  • Major Adverse Drug-Drug and Drug-Food Interactions: Explain potential interactions and precautions to take.
  • Contact Information: Provide contact information for reporting adverse effects or treatment concerns.
  • Advertisements

Application of the Nursing Process in Drug Therapy

The nursing process provides a systematic approach to medication administration and patient care:

A. Review of the Nursing Process:

  1. Assessment: Data collection via interview, medical history, physical exam, observation, and laboratory tests.
  2. Analysis/Nursing Diagnosis: Identifying actual and potential health problems related to medication therapy. This includes judging the appropriateness of the prescribed regimen, identifying potential drug-induced problems, and assessing the patient’s capacity for self-care.
  3. Planning: Defining goals, setting priorities, and identifying interventions to maximize therapeutic effects and minimize adverse effects.
  4. Implementation (Intervention): Carrying out the planned interventions, including medication administration and patient education. This includes both independent (nurse-initiated) and collaborative (physician-ordered) interventions.
  5. Evaluation: Determining the effectiveness of the interventions by analyzing data collected during implementation. This guides adjustments to the care plan as needed.

B. Applying the Nursing Process in Drug Therapy:

1. Pre-administration Assessment: This section summarizes essential information needed before administering a drug. It includes:

  • Patient History: Reviewing allergies, current medications (prescription and over-the-counter), relevant medical history (renal/hepatic function, etc.), and any potential drug interactions.
  • Baseline Data: Obtaining vital signs, relevant lab results, and other pertinent assessment data to establish a benchmark against which to measure therapeutic and adverse effects.
  • Patient Understanding: Assessing the patient’s understanding of the medication, their ability to self-administer, and their overall capacity for adherence to the treatment regimen.

2. Implementation: 

Administration: This section outlines the safe and effective administration of the medication, including:

  • Routes of Administration: Describing appropriate routes (oral, intravenous, intramuscular, subcutaneous, topical, etc.) and any specific techniques for each.
  • Dosage and Adjustment Guidelines: Summarizing appropriate dosage ranges, factors influencing dosage adjustments (e.g., age, renal function), and any special instructions for dose titration.
  • Special Considerations: Highlighting any unique considerations during administration (e.g., rate of infusion, injection site selection, monitoring for adverse effects during administration).

Enhancing Therapeutic Effects: This section focuses on strategies to optimize the medication’s therapeutic effect, including:

  • Dietary Modifications: Describing any necessary dietary changes to enhance drug absorption or minimize interactions (e.g., taking medication with food or avoiding certain foods).
  • Comfort Measures: Identifying strategies to improve patient comfort and adherence (e.g., managing side effects with antiemetics or analgesics).
  • Adherence Strategies: Outlining methods to promote adherence, such as medication reminders, pill organizers, or support systems.

3. Ongoing Evaluation and Intervention: This section outlines the ongoing monitoring and management of both therapeutic and adverse responses to the medication.

  • a. Monitoring: Summarizes physiological and psychological parameters requiring monitoring to detect both therapeutic and adverse responses. This includes regular vital signs, lab tests (as appropriate), and ongoing assessments of the patient’s subjective experience.
  • b. Evaluating Therapeutic Effects: Describes the criteria and procedures for evaluating the effectiveness of the medication in achieving its intended therapeutic goal. This should include specific, measurable outcomes.
  • c. Minimizing Adverse Effects: Summarizes major adverse reactions that should be monitored for and outlines appropriate interventions to minimize harm. This could include both pharmacological and non-pharmacological interventions.
  • d. Minimizing Adverse Interactions: Summarizes potential drug-drug and drug-food interactions and provides interventions to mitigate the risks.
  • e. Managing Toxicity: Describes the major symptoms of drug toxicity and the appropriate treatment protocols. This section is crucial for early recognition and intervention to prevent serious complications.

4. Patient Education: This section summarizes essential information to be provided to the patient to promote safe and effective use of the medication. It should include:

  • Medication Name and Purpose: Clearly explaining both the generic and brand name, along with its intended therapeutic use.
  • Dosage, Route, and Schedule: Providing clear and concise instructions for medication administration.
  • Expected Therapeutic Effects and Onset: Informing the patient what to expect and when to expect it.
  • Common Side Effects and Management Strategies: Educating the patient on potential side effects and how to manage them safely.
  • Adverse Reactions Requiring Immediate Attention: Clearly outlining warning signs and symptoms requiring immediate medical attention.
  • Medication Storage and Disposal: Instructing the patient on the proper storage and disposal methods.
  • Follow-up Care: Instructing the patient on any scheduled follow-up appointments or tests.

Terminologies and Sources of Drugs Read More »

Want notes in PDF? Join our classes!!

Send us a message on WhatsApp
0726113908

Scroll to Top
Enable Notifications OK No thanks